Deflux — Dextranomer / Hyaluronic Acid
Deflux is a dextranomer/hyaluronic-acid implant for endoscopic treatment of vesicoureteral reflux (VUR) grades II–IV in children under US labeling. It was first FDA approved in 2001.[1] The current US product information is maintained by Teleflex; the supplied implant's instructions remain the reference for eligibility, preparation and administration.[1][2]
Its purpose is to improve ureteral coaptation. Radiographic reflux resolution, freedom from febrile infection and preservation of renal function are different outcomes and should be reported separately.
Material and Mechanism
The sterile gel contains dextranomer 50 mg/mL in stabilized non-animal hyaluronic acid 15 mg/mL. Microspheres range from 80–250 μm. Injection near the ureteral orifice supports the distal ureter, and host connective tissue subsequently surrounds the microspheres. The implant is biodegradable, but visible deposits can persist and calcify.[1]
The label warns against injection in patients with known allergy to hyaluronic-acid products, streptococcal proteins or dextran. Inflammation, migration and obstruction can occur despite particle size and biocompatibility.[1]
Contraindications and Selection
Do not use in patients with nonfunctional kidney(s), Hutch diverticulum, ureterocele, active voiding dysfunction, ongoing UTI, or primary refluxing megaureters with distal stenosis. Do not inject Deflux intravascularly; the label places this instruction under WARNINGS because vascular occlusion may occur.[1]
The label separately identifies uncertainty in children younger than one year, treatment of duplex systems, and use of more than 6 mL in one session (3 mL at each ureteral orifice). Grossly dilated ureteral orifices may make a patient unsuitable.[1]
The EAU 2026 guideline (limited update, March 2026) gives a weak recommendation to select management from renal scars, clinical course, reflux grade, ipsilateral renal function, bilaterality, bladder function, associated anomalies, age and sex, compliance and parental preference. It gives a strong recommendation to offer reimplantation for persistent high-grade reflux and endoscopic correction for lower grades, and a weak recommendation to offer either for frequent breakthrough infections. It states that the lack of robust prospective trials limits the strength of these recommendations. It strongly recommends investigating every child for lower urinary tract dysfunction and treating it first when found, and managing children presenting at age one to five years conservatively at first.[3]
Administration Principles
Deflux is injected under cystoscopic guidance by a trained surgeon. The US IFU describes STING, HIT and double HIT. It recommends a 3.7 Fr, 23-gauge, 350 mm needle through a pediatric cystoscope with at least a 4 Fr working channel and a semi-filled bladder. For HIT, the needle enters the submucosa of the mid to distal ureteral tunnel about 4 mm at the 6 o'clock position; 0.5 to 1.0 mL usually creates a sufficient bolus, the needle is held 15 to 30 seconds to prevent extrusion, and the endpoint is an orifice that no longer hydrodistends.[1]
- STING. Subureteric injection supporting the ureteral orifice.
- HIT. Intraureteric submucosal injection after hydrodistention identifies the ureteral tunnel.
- Double HIT. A second, more distal intraureteric injection when needed to complete coaptation.
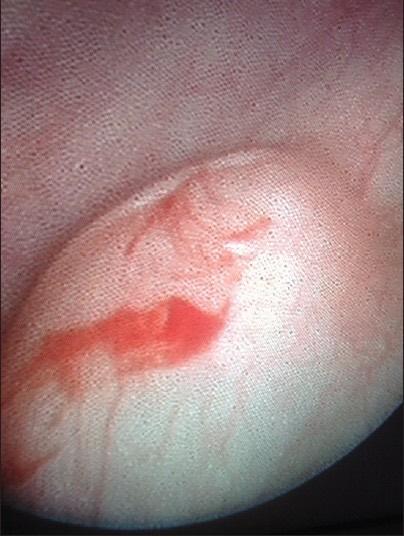
Cystoscopic appearance at the end of a subureteric Deflux injection at the 6 o'clock position: the mound gives a "volcano" appearance with a slit-like ureteric orifice on top. In this series, this appearance together with an orifice that stayed closed on hydrodistention marked the injection endpoint. From Chandrasekharam VVS. Indian J Urol. 2013;29(3):173-176, Figure 1 (CC BY-NC-SA 3.0).[25]
Six observational comparisons pooled in a 2016 review reported radiographic resolution in 82.5% of HIT-treated versus 71.4% of STING-treated ureters.[4] The frequently cited “92% use double HIT” figure came from 50 respondents to a 2012 survey, with an 18% response rate.[5]
Keep the product sterile, do not mix it with other products or resterilize it, and document the agent and injection history. Provide the implant card: Deflux is radiographically opaque and can be mistaken for distal ureteral calculi.[1]
Major Comparative Evidence
Swedish Reflux Trial: Three Different Endpoints
This open randomized trial enrolled 203 children aged one to younger than two years with grade III–IV reflux: 69 assigned to antibiotic prophylaxis, 66 to endoscopic treatment and 68 to surveillance.[6][7][8] Children in the injection arm continued prophylaxis until postoperative imaging showed absent or nondilating reflux.[6][7][8]
| Outcome | Finding | Interpretation |
|---|---|---|
| Reflux after two years | Resolution or downgrading to grades I–II was reported in 71% after endoscopy, 39% with prophylaxis and 47% with surveillance. Only 52/66 children assigned to endoscopy completed the two-year VCUG. | The 71% is not complete reflux eradication or a fully observed all-randomized result. Recurrent dilating reflux after initial improvement was reported in 13/66 children assigned to endoscopy (20%) at two years.[6] |
| Febrile UTI in girls | Recurrence affected 10/43 (23%) after endoscopic treatment, 8/43 (19%) with prophylaxis and 24/42 (57%) with surveillance. | Endoscopy and prophylaxis reduced infections compared with surveillance in girls. Their difference from each other was not significant; few boys had recurrent febrile UTI.[7] |
| New renal damage | New damage occurred in 13 girls: five in the endoscopic arm, none with prophylaxis and eight under surveillance; two boys also developed new damage. | New renal damage was significantly more frequent with surveillance than prophylaxis.[8] |
Across the wider evidence base, the 2019 Cochrane review found uncertain additional benefit of endoscopic injection, with or without antibiotics, over antibiotics alone for febrile UTI by one to two years (RR 0.74, 95% CI 0.31–1.78, low-certainty evidence).[9] A 2026 meta-analysis of 15 mostly nonrandomized studies favored ureteral reimplantation over Dx/HA injection for radiographic resolution (risk ratio for nonresolution 4.30) and reoperation (risk ratio 6.42), with no difference in febrile or recurrent UTI; in its two-center cohort (179 injection, 130 reimplantation), postoperative UTI was 19.6% versus 3.8%, while injection had shorter operative time and stay.[26]
Comparisons with Other Bulking Materials
Two trials in the Cochrane review favored Macroplastique for persistent reflux, but patient-important infection outcomes were inconclusive and renal-parenchymal outcomes were not reported for that comparison. In the larger prospective study, reflux was fully corrected at three-month VCUG in 182/202 Macroplastique-treated ureters versus 159/197 Deflux-treated ureters.[10] Macroplastique's US indication is different.[9]
The often quoted grade-specific estimates from 5,527 patients/8,101 renal units combine endoscopic-injection literature across agents.[3] The EAU also notes greater concern about delayed obstruction with polyacrylate-polyalcohol copolymer than with Dx/HA.[3]
Durability and Interpreting Follow-up
Large single-center Deflux cohorts report high anatomical resolution rates, often after repeated injections. A series of 1,551 children (2,341 ureters, grades II–V) reported resolution after the first, second and third injection in 87.1%, 11.3% and 1.6% of ureters, respectively. VCUG and ultrasound were performed at three months, then ultrasound annually; median overall follow-up was 5.6 years. Febrile UTI occurred in 69/1,551 children (4.4% by calculation; the abstract reports 4.6%), and no patient required reimplantation.[20] A cohort of 851 children with 1,287 grade IV–V refluxing units reported first-injection resolution in 895/1,287 (69.5%).[11] Subsequent clinical and ultrasound follow-up extended for a median 8.5 years, but routine VCUG was performed at three months.[11]
In another series, 111/150 ureters initially cured and reassessed at one year remained reflux-free. The authors' 46.1% combined one-year success estimate used a selected denominator of 241 ureters, including initial failures, rather than all 337 initially treated ureters. The one-year data show recurrence in some ureters, with incomplete follow-up and a selected denominator.[12]
In the label's pivotal randomized study, VCUG grade 0 at 12 months was achieved in 27/39 (69%) children after Deflux versus 7/21 (33%) on antibiotic prophylaxis (p = 0.0041). In the 165-child post-approval study, VCUG grade 0 at 3 months was 66% (109/165); later success was defined as absence of febrile UTI, or grade 0 on a VCUG prompted by an event, and was 69% (96/139) at 12 months and 40% (32/80) at 5 years. Only 31/165 (18.8%) had complete five-year data, and 30% were retreated.[1]
Complex Anatomy and Factors Associated with Success
Uncontrolled single-center series describe treatment in complete duplex systems. One series of 123 children with complete duplex systems (136 refluxing units, mostly grade III–IV) reported resolution after the first, second and third injection in 68.4%, 25.7% and 5.9% of units, with febrile UTI in 4.1% and no reimplantations. VCUG and ultrasound were performed at three months, then ultrasound every two years; mean overall follow-up was 6.7 years.[21] The label's stated uncertainty about duplex systems, noted above, remains.
Reported factors associated with lower endoscopic success:
- Reflux grade. In the 851-child cohort, first-injection resolution was 70.4% for grade IV and 61.9% for grade V.[11]
- Sex. In a single-surgeon retrospective series of 49 children with grade IV–V reflux (median follow-up 32 months), 84% needed no further intervention after one injection and 98% after further injections. Boys did better than girls on multivariable analysis.[22]
- Bladder and bowel dysfunction. In the AUA guideline meta-analysis, initial reflux resolution after endoscopic surgery was 50% with bladder and bowel dysfunction and 89% without it, while open surgery resolved 97% in both groups. The guideline recommends treating the dysfunction first, preferably before reflux surgery.[24]
- Experience. In the Lee series, one-injection radiographic success was 65.9% (112/170 ureters) in the first half and 80.2% (134/167) in the second half.[12]
Safety and Surveillance
Potential complications include infection, hematuria, dysuria, transient dilation, new contralateral reflux and ureteral obstruction with or without hydronephrosis. Delayed obstruction can require stenting or reimplantation and may affect renal function. The label and published case reports document late presentations, including occasional asymptomatic renal deterioration years after treatment.[1][13]
A four-center series found five patients requiring stenting among 745 treated, and all had received no more than 1 mL at the relevant injection; four had neurogenic bladder or dysfunctional voiding. The affected subgroup is too small for reliable risk prediction.[14]
Histology Is Not a Population Complication Rate
Giant-cell reactions were found in 94% of a selected 16-child surgical-excision series after failed injection.[15] Calcification was seen in nine ureters among 13 treated children in a different failed-treatment or reimplantation series.[16]
A sonographic volume study had 296 ureters measured at two weeks but only 20 at 24–36 months. Its approximately 65% late volume retention does not validate avoiding reflux imaging solely because a mound remains visible.[17]
Follow-up is arranged according to reflux severity, renal status and infection history. The IFU suggests postoperative VCUG to assess persistence, and the AUA guideline recommends voiding cystography after endoscopic injection and renal ultrasound after any reflux surgery to look for obstruction.[1][24] In a series of 160 children (220 ureters, 30 with grade IV–V reflux), bladder ultrasound detected the mound in 89% of low-grade and 43.3% of high-grade ureters at last follow-up, which led the authors to propose ultrasound follow-up for low-grade reflux and VCUG for high-grade reflux.[23] New febrile UTI, flank pain, hydronephrosis or deteriorating renal function warrants evaluation. In adults previously treated as children, distinguish a calcified extraluminal implant from a ureteral stone and assess for obstruction.[1][3]
Solesta Is a Separate Product and Indication
Related Dx/HA technology is marketed as Solesta, originally FDA approved in 2011 for fecal incontinence in adults aged at least 18 who have failed conservative therapy.[18] ASCRS 2023 states that injection of biocompatible bulking agents into the anal canal is not routinely recommended for FI .[19] See Fecal Incontinence for treatment selection.[18][19]
See also: Macroplastique, Ureteral Reimplantation.
References
1. Palette Life Sciences/Teleflex. Deflux US Instructions for Use. 90-96532-04, current manufacturer-linked document. Instructions.
2. Teleflex. Deflux US healthcare-professional information. Product website.
3. EAU. Paediatric Urology Guidelines. 2026, section 17, Vesicoureteric Reflux. Guideline chapter.
4. Yap TL, Chen Y, Nah SA, et al. STING Versus HIT Technique of Endoscopic Treatment for Vesicoureteral Reflux: A Systematic Review and Meta-Analysis. Journal of Pediatric Surgery. 2016;51(12):2015-2020. doi:10.1016/j.jpedsurg.2016.09.028
5. Kirsch AJ, Arlen AM, Lackgren G. Current Trends in Dextranomer Hyaluronic Acid Copolymer (Deflux) Injection Technique for Endoscopic Treatment of Vesicoureteral Reflux. Urology. 2014;84(2):462-468. doi:10.1016/j.urology.2014.04.032
6. Holmdahl G, Brandström P, Läckgren G, et al. The Swedish Reflux Trial in Children: II. Vesicoureteral Reflux Outcome. The Journal of Urology. 2010;184(1):280-285. doi:10.1016/j.juro.2010.01.059. See also Brandström P. The Swedish Reflux Trial, doctoral thesis, methods/results. University repository.
7. Brandström P, Esbjörner E, Herthelius M, et al. The Swedish Reflux Trial in Children: III. Urinary Tract Infection Pattern. J Urol. 2010;184:286–291. doi:10.1016/j.juro.2010.01.061.
8. Brandström P, Nevéus T, Sixt R, et al. The Swedish Reflux Trial in Children: IV. Renal Damage. J Urol. 2010;184:292–297. doi:10.1016/j.juro.2010.01.060.
9. Williams G, Hodson EM, Craig JC. Interventions for Primary Vesicoureteric Reflux. Cochrane Database of Systematic Reviews. 2019;2:CD001532. doi:10.1002/14651858.CD001532.pub5
10. Moore K, Bolduc S. Prospective Study of Polydimethylsiloxane vs Dextranomer/Hyaluronic Acid Injection for Treatment of Vesicoureteral Reflux. The Journal of Urology. 2014;192(6):1794-1799. doi:10.1016/j.juro.2014.05.116
11. Friedmacher F, Colhoun E, Puri P. Endoscopic Injection of Dextranomer/Hyaluronic Acid as First Line Treatment in 851 Consecutive Children With High Grade Vesicoureteral Reflux: Efficacy and Long-Term Results. The Journal of Urology. 2018;200(3):650-655. doi:10.1016/j.juro.2018.03.074
12. Lee EK, Gatti JM, DeMarco RT, Murphy JP. Long-Term Followup of Dextranomer/Hyaluronic Acid Injection for Vesicoureteral Reflux: Late Failure Warrants Continued Followup. The Journal of Urology. 2009;181(4):1869-1874. doi:10.1016/j.juro.2008.12.005
13. Pham H, Au J, Jones E. Deflux Calcification Leading to Delayed Obstruction and Loss of Renal Function: A Case Report. Urology. 2022;166:246-249. doi:10.1016/j.urology.2022.04.025
14. Vandersteen DR, Routh JC, Kirsch AJ, et al. Postoperative Ureteral Obstruction After Subureteral Injection of Dextranomer/Hyaluronic Acid Copolymer. The Journal of Urology. 2006;176(4 Pt 1):1593-1595. doi:10.1016/j.juro.2006.06.101
15. Routh JC, Ashley RA, Sebo TJ, et al. Histopathological Changes Associated With Dextranomer/Hyaluronic Acid Injection for Pediatric Vesicoureteral Reflux. The Journal of Urology. 2007;178(4 Pt 2):1707-1710. doi:10.1016/j.juro.2007.03.165
16. Stenberg A, Larsson E, Läckgren G. Endoscopic Treatment With Dextranomer-Hyaluronic Acid for Vesicoureteral Reflux: Histological Findings. The Journal of Urology. 2003;169(3):1109-1113. doi:10.1097/01.ju.0000053013.49676.89
17. McMann LP, Scherz HC, Kirsch AJ. Long-Term Preservation of Dextranomer/Hyaluronic Acid Copolymer Implants After Endoscopic Treatment of Vesicoureteral Reflux in Children: A Sonographic Volumetric Analysis. The Journal of Urology. 2007;177(1):316-320. doi:10.1016/j.juro.2006.08.144
18. US Food and Drug Administration. Solesta, P100014 approval record. May 27, 2011. Approval.
19. Bordeianou LG, Thorsen AJ, Keller DS, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Fecal Incontinence. Diseases of the Colon and Rectum. 2023;66(5):647-661. doi:10.1097/DCR.0000000000002776
20. Puri P, Kutasy B, Colhoun E, Hunziker M. Single Center Experience With Endoscopic Subureteral Dextranomer/Hyaluronic Acid Injection as First Line Treatment in 1,551 Children With Intermediate and High Grade Vesicoureteral Reflux. The Journal of Urology. 2012;188(4 Suppl):1485-1489. doi:10.1016/j.juro.2012.02.023
21. Hunziker M, Mohanan N, Puri P. Dextranomer/Hyaluronic Acid Endoscopic Injection Is Effective in the Treatment of Intermediate and High Grade Vesicoureteral Reflux in Patients With Complete Duplex Systems. The Journal of Urology. 2013;189(5):1876-1881. doi:10.1016/j.juro.2012.11.048
22. Tiboni SG, Bethell GS, Davidson JR, Farrugia MK. Factors Influencing Success in Endoscopic Treatment of Grade 4-5 Primary Vesicoureteric Reflux (VUR) in Infancy and Childhood. Journal of Pediatric Surgery. 2025;60(3):162157. doi:10.1016/j.jpedsurg.2025.162157
23. Aboutaleb H, Eldib DB, Farahat Y, Abouelgreed TA, Zanaty F. Efficacy of Bladder Ultrasound in Prediction of Resolution of Vesicoureteral Reflux After Endoscopic Subureteral Hyaluronic Acid/Dextranomer (Deflux) Injection. Urology. 2022;165:299-304. doi:10.1016/j.urology.2022.01.015
24. Peters CA, Skoog SJ, Arant BS, et al. Summary of the AUA Guideline on Management of Primary Vesicoureteral Reflux in Children. The Journal of Urology. 2010;184(3):1134-1144 (guideline amended 2017). doi:10.1016/j.juro.2010.05.065
25. Chandrasekharam VVS. Endoscopic Treatment of Vesicoureteric Reflux With Dextranomer/Hyaluronic Acid Copolymer (Deflux): Single-Surgeon Experience With 48 Ureters. Indian Journal of Urology. 2013;29(3):173-176. doi:10.4103/0970-1591.117269
26. Kim JK, Miranda B, Rickard M, et al. "Comparative Analysis of Ureteral Reimplantation and Dextranomer/Hyaluronic Acid Injection Between Two Centers With Systematic Review and Meta-Analysis." J Urol. 2026;216(3):420-432. doi:10.1097/JU.0000000000005138