Percutaneous Tibial Nerve Stimulation — Office-Based Devices
PTNS is an office-based tibial nerve stimulation therapy delivered by external devices, and the treatment burden is the main practical difference from implanted systems. For patient assessment, insertion technique and clinical alternatives, see PTNS procedure.
Available Systems
| System | Hardware |
|---|---|
| Urgent PC — Laborie | External stimulator (9 V alkaline battery) with a single-use lead set: lead wire with a fuse that limits it to one session, two 34-gauge needle electrodes and a surface electrode. The international IFU lists urgency, frequency, urge incontinence and fecal incontinence[7] |
| NURO — Medtronic | External stimulator with a rechargeable lithium battery and a permanently attached lead wire, run on purchased therapy credits (one per session) with single-use needle, holder and electrode pad. The 2013 FDA 510(k) (K132561, Advanced Uro-Solutions) covers OAB symptoms and cites Urgent PC (K101847) as the equivalent predicate[2][8] |
Both deliver tibial stimulation without an implant. Urgent PC, originally marketed by Uroplasty and now by Laborie, received FDA 510(k) clearance in 2005 and was the first widely used PTNS system.[6] Electrode placement, connections and programming follow each system's instructions. The PTNS procedure page lists the needle position and electrical parameters from the Urgent PC instructions (20 Hz, 200 μs, current 0 to 9 mA, 30-minute sessions).[1][2][7] The NURO 510(k) summary states the same waveform, pulse width and frequency for both devices.[8]
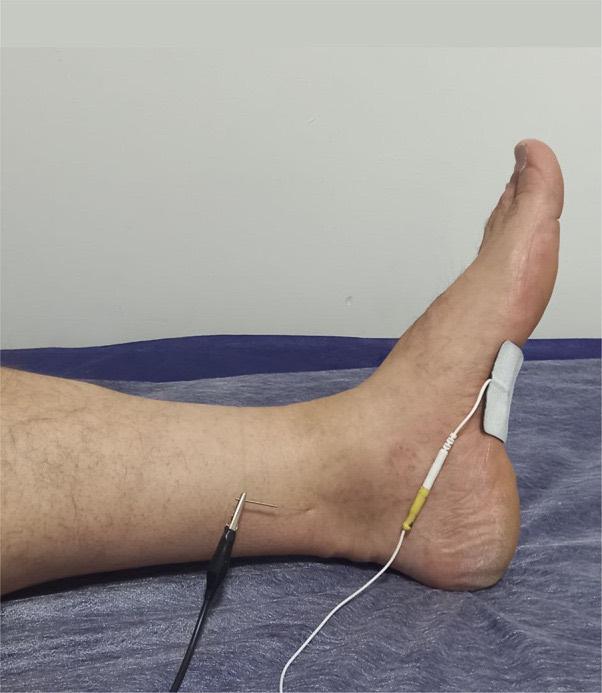
Electrode positions for percutaneous tibial nerve stimulation: a 34-gauge needle electrode inserted about 5 cm cephalad to the medial malleolus and posterior to the tibia (connected to the active pole), with an adhesive surface reference electrode on the medial foot. From Ahadi T, et al. Basic Clin Neurosci. 2024;15(4):499-508, Figure 1 (CC BY-NC 4.0).[9]
Course and Evidence
A commonly studied induction course is 30 minutes weekly for 12 weeks. In the 220-participant SUmiT sham-controlled trial, 54.5% versus 20.9% reported moderately or markedly improved overall bladder symptoms at 13 weeks.[3]
Maintenance is individualized. STEP enrolled 50 initial SUmiT responders, of whom 29 completed three years; after a taper, the median maintenance frequency was 1.1 treatments per month. Across the 50 enrolled initial responders, 29 of whom completed the protocol, a Bayesian model accounting for early withdrawal estimated that 77% (95% CI 64–90) maintained moderate or marked improvement in overall bladder symptoms at three years, and the burden of ongoing visits and possible symptom recurrence is part of counseling.[4] The visit burden of induction and maintenance was one driver for implantable tibial systems.
Eligibility and Precautions
US manufacturer summaries describe OAB-associated urgency, frequency and urge incontinence. They list contraindications including pacemakers or implantable defibrillators, excessive bleeding risk, relevant nerve damage, and pregnancy or planned pregnancy.[2] Treatment through compromised skin is avoided, and the full device instructions govern use. Minor insertion-site bleeding, discomfort and inflammation can occur.[1][2]
The 2024 AUA/SUFU guideline states that clinicians should offer tibial nerve stimulation, SNM and/or intradetrusor botulinum toxin after inadequate response to, or intolerable side effects from, behavioral therapy or medication , and that clinicians may offer minimally invasive therapies in shared decision-making without prior behavioral, non-invasive or pharmacologic trials .[5] The 2026 EAU guideline on non-neurogenic female LUTS recommends offering posterior tibial nerve stimulation as an option for symptomatic improvement of OAB and UUI .[10]
Implants and Surface-Electrode Therapy
eCoin, Revi and Altaviva reduce repeat office stimulation visits but introduce implantation, maintenance and device-specific safety requirements. The AUA 2024 implantable-device section does not transfer the PTNS recommendation to these systems.[5]
Transcutaneous tibial nerve stimulation (TTNS) uses surface electrodes and can support a home protocol. Its device, regimen, population and evidence differ from percutaneous and implanted stimulation. See the procedure hub for that comparison.
References
1. Laborie. My PTNS Program. Current Urgent PC manufacturer information and US safety footer. Manufacturer resource.
2. Medtronic. Percutaneous Tibial Neuromodulation: Indications, Safety and Warnings. Current NURO manufacturer summary. Safety information.
3. Peters KM, Carrico DJ, Perez-Marrero RA, et al. Randomized Trial of Percutaneous Tibial Nerve Stimulation Versus Sham Efficacy in the Treatment of Overactive Bladder Syndrome: Results From the SUmiT Trial. J Urol. 2010;183:1438–1443. doi:10.1016/j.juro.2009.12.036.
4. Peters KM, Carrico DJ, Wooldridge LS, et al. Percutaneous Tibial Nerve Stimulation for the Long-Term Treatment of Overactive Bladder: 3-Year Results of the STEP Study. J Urol. 2013;189:2194–2201. doi:10.1016/j.juro.2012.11.175.
5. AUA/SUFU. Idiopathic Overactive Bladder Guideline, 2024. Statements 23–25 and implantable-tibial-stimulation discussion, pp 30–32. Unabridged guideline.
6. US Food and Drug Administration. Urgent PC Neuromodulation System (Uroplasty), 510(k) K052025. FDA 510(k) database.
7. Cogentix Medical. Urgent PC Stimulator Instructions for Use, UPC 200-B (international edition, English section). Manufacturer document.
8. US Food and Drug Administration. 510(k) Summary K132561: NURO Neuromodulation System (Advanced Uro-Solutions), decision November 5, 2013. FDA 510(k) summary.
9. Ahadi T, Noori I, Khalifeh Soltani S, Ghaboosi P, Raissi GR. Efficacy of Percutaneous vs Transcutaneous Posterior Tibial Nerve Stimulation in Overactive Bladder Syndrome: A Randomized Clinical Trial. Basic Clin Neurosci. 2024;15(4):499–508. doi:10.32598/bcn.2023.4896.1
10. European Association of Urology. EAU Guidelines on Management of Non-Neurogenic Female Lower Urinary Tract Symptoms. Harding CK (Chair), et al. EAU Guidelines Office, Arnhem, 2026, section 4.1.4.a.5.d.1 (posterior tibial nerve stimulation). EAU guideline