Inflatable Penile Prosthesis
An inflatable penile prosthesis (IPP) is an implanted hydraulic device that gives patient-controlled rigidity for erectile dysfunction. It is used when other treatments are unsuitable or have failed, or when an informed patient prefers definitive prosthetic treatment. It requires surgery, realistic expectations and the ability to operate the device. Trying every nonsurgical option first is not an absolute prerequisite.[1]
For surgical selection, operative approaches, reservoir placement and salvage, see the Penile Implants atlas. For patients who may be better served by persistent firmness and simpler operation, see Malleable Penile Prosthesis.
History and Evolution
F. Brantley Scott published the first inflatable penile prosthesis in 1973.[30][31] The design changes since then, in the order they were introduced:[32][33]
- The first implant was a three-piece device: intracavernosal cylinders, a scrotal pump and a retropubic reservoir. Self-contained two-piece devices (cylinders and pump, no separate reservoir) followed.
- Kink-resistant tubing, changes to the cylinder fabric weave and shear-resistant coatings, rear tip extenders and lockout valves to prevent autoinflation were added.
- Antibiotic or antimicrobial surface treatments were introduced: InhibiZone (rifampin and minocycline, AMS) and the Coloplast hydrophilic coating, which the surgeon soaks in antibiotic.
- Steve Wilson described ectopic (submuscular) reservoir placement in 2002. It avoids the space of Retzius and a second incision, and lockout valves and flat reservoirs made it practical.[33]
Components and Current Models
A three-piece implant contains paired corporal cylinders, a scrotal pump and a separate fluid reservoir. Inflation and deflation transfer fluid between these components. A two-piece design has fluid storage within the cylinders and therefore avoids a separate abdominal reservoir. Neither configuration eliminates infection, mechanical failure or revision.[2][3]
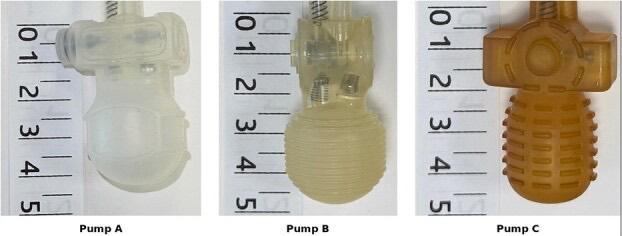
Pumps of three commonly used IPP systems (A, B and C) beside a centimeter scale; each is about 4.5 cm long, so overall pump dimensions are similar across devices. From Canguven O, et al. Sex Med. 2026;14(5):qfag067, Figure 4 (CC BY 4.0).[47]
| Platform | Current device distinctions | Interpretation |
|---|---|---|
| AMS 700 — Boston Scientific | CX/CXR provide girth expansion; LGX adds length expansion. TENACIO and earlier MS pumps have distinct instructions. Specified components have rifampin/minocycline InhibiZone treatment. | Length expansion does not reliably restore perceived penile length. The IFU cautions that LGX cylinders in Peyronie's disease may not give a satisfactory result. Identify the actual pump and cylinder model. |
| Titan / Titan Prime — Coloplast | Bioflex cylinders and hydrophilic surface; pump/model variants differ. Titan Prime introduces the Press pump and revised components. | — |
| Infla10 — Rigicon | X provides girth expansion; AX provides length and girth expansion. HydroShield hydrophilic coating includes components, connectors and rear-tip extenders. | The manufacturer's current page states that it is not available for sale in the US. |
| AMS Ambicor — Boston Scientific | Prefilled, preconnected two-piece device; fluid reservoirs are in the proximal cylinders. | It has no separate abdominal reservoir. Deflation involves bending the cylinders as taught for this model, not pressing a three-piece deflation button. |
Match the actual implant, supplied instructions and local authorization. No high-quality evidence establishes one brand as best for every patient. In a three-cadaver study, all implants performed similarly at maximum inflation, and the circumferentially expanding devices had greater rigidity in load testing; the study did not test clinical satisfaction or durability.[4][5][6][3][7]
Titan Prime: 2026 Approval and Availability
FDA approved supplement P000006/S072 on June 2, 2026.[8] The linked Titan Prime GUDID record identifies the new model, while Coloplast's June announcement described a phased US launch beginning in late 2026. The manufacturer's tubing-resistance and button-force findings are bench tests, and the announcement reports no long-term comparative patient outcomes.[8][5]
Device Safety Notices
AMS 700 with TENACIO: FDA Class II recall event 97603, initiated September 11, 2025, concerns specified devices with potential inflation or deflation problems from a nonconforming component. Check the exact catalog number or UPN, UDI and lot in the linked records. Affected unused inventory is not used and is returned through the recall process. The notice states that no action is required for an implanted affected device that is functioning properly, and inflation or deflation difficulties warrant evaluation. The recall does not cover every TENACIO implant and does not call for routine explantation.[9]
An earlier Titan Touch recall, event 91800, concerns specified lots with a pump-wall thickness issue that could lead to premature failure. Its affected-inventory instructions also require exact model and lot matching. Not every Titan is affected; consult the current record and manufacturer action notice.[10]
Indications and Selection
An IPP may be chosen when PDE5 inhibitors, vacuum devices or intracavernosal injections are ineffective or unsuitable, or when an informed patient prefers prosthetic treatment.[1] Common indications are:
- erectile dysfunction with Peyronie's disease;
- erectile dysfunction after radical prostatectomy that has not responded to rehabilitation;
- acute ischemic priapism that is untreated for >36 hours or refractory to shunting, with or without tunneling , or ED after established corporal fibrosis;[46]
- corporal fibrosis from prior priapism, infection, trauma or explantation;
- gender-affirming phalloplasty;
- patient preference for definitive surgical treatment.
Preoperative assessment covers HbA1c, active urinary infection, hand function and key pinch strength for pump operation, the partner's sexual function, and consent about irreversibility, possible shortening, mechanical failure and infection.
Consider the patient's erectile goals, hand function, cognition, tissue quality and ability to obtain follow-up. A clinic demonstration can identify practical problems with the chosen pump. The Ambicor label still requires manual dexterity and strength, so a two-piece device is not automatically suitable for a patient who cannot operate a three-piece pump.[1][3]
Counseling covers irreversible corporal changes, perceived shortening, altered rigidity or sensation, persistent pain, infection, erosion and future surgery. An implant is not a lifetime device and does not restore libido, fertility or an absent orgasmic response. Urination, sensation and ejaculation can be affected by surgery or its complications.[2][3]
Active infection and device-specific material or medication hypersensitivity need review. AMS 700 InhibiZone components have additional contraindications including the listed antibiotic allergies and systemic lupus erythematosus. Diabetes and other comorbidities are optimized before surgery; no single HbA1c value is a validated infection-safe threshold.[2][1]
Prior pelvic surgery or hernia mesh changes reservoir planning but does not automatically prohibit a three-piece device. The space of Retzius reservoir carries risk of bladder, iliac vessel and bowel injury. High submuscular (HSM) placement is increasingly used: in a retrospective CT comparison of 139 imaged cases among 1,010 IPP procedures, HSM reservoirs (n = 107) were about five times farther from the bladder (49 vs 10 mm) and iliac vessels (23 vs 5 mm) than space-of-Retzius reservoirs (n = 32), with less mass effect on the bladder (9% vs 72%) and iliac vessels (4% vs 34%).[11] In one surgeon's 733 IPP procedures, 561 first-time implants were analyzed: revision for a reservoir-related complication was needed in 10 of 430 HSM and 6 of 131 space of Retzius cases (p = 0.22), mostly herniation; after the "five-step" HSM technique was adopted, 3 of 297 first-time HSM cases (1.0%) needed revision, all for herniation.[12] Ectopic placement (lateral retroperitoneal, intraperitoneal or epigastric extraperitoneal) has its own risks of injury, malposition, herniation and discomfort. See Reservoir Placement.
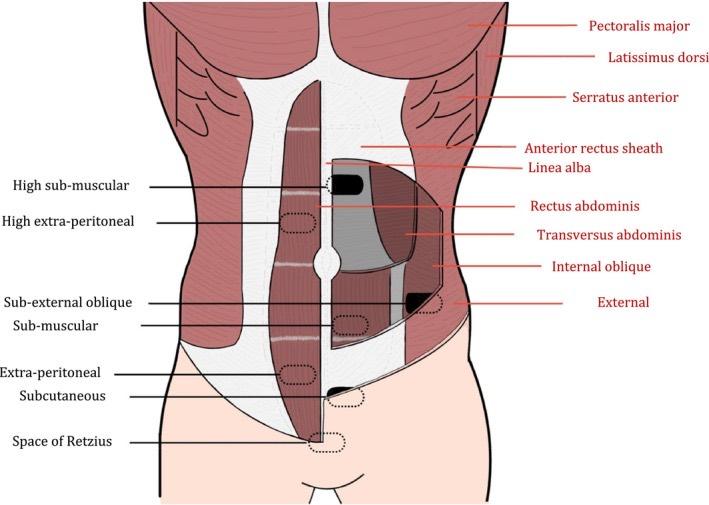
Reservoir implantation sites in anterior view, with the abdominal wall layers labelled: high submuscular, high extraperitoneal, sub-external oblique, submuscular, extraperitoneal, subcutaneous and space of Retzius. From Michael S, et al. BJUI Compass. 2026;7(7):e70246, Figure 2 (CC BY 4.0).[48]
The incision is penoscrotal, infrapubic or subcoronal. A critical review found no difference between penoscrotal and infrapubic approaches in implant size, achieved length, satisfaction, infection or urethral injury. Dorsal nerve injury risk appears greater with the infrapubic approach.[34]
Device Handling
- AMS 700 InhibiZone: the treated system can include cylinders, pump and reservoir. The TENACIO IFU prohibits soaking treated components; a brief rinse or dip is distinct from soaking. This is different from the AMS 800 AUS, whose PRB is not treated.
- Hydrophilic devices: follow the model's specified preparation.
- Cycling: pump controls differ. Autoinflation and unintended deflation remain possible despite design features intended to reduce them.
- After implantation: intracavernosal injection therapy can damage the prosthesis and should not be continued. Preserve the device identification and component records.[2][6][3]
For patient teaching and troubleshooting, use Device Operation with the actual manufacturer's instructions.
Infection Prevention
Infection prevention combines patient assessment, skin preparation, antimicrobial selection, appropriate device handling and operative technique. No single coating or irrigation solution eliminates infection.
| Study | Findings |
|---|---|
| Eid 2012, single-surgeon series, 2,347 IPPs | Infection was 5.3% with 132 noncoated implants, 2% with 704 coated implants (2003–2005) and 0.46% (7 of 1,511) after the "no touch" technique was added (2006–2010)[13] |
| Bole 2023, single-institution retrospective series, 1,071 procedures | Infection was 2.6% overall and 0.9% (8 of 919) after 5% povidone-iodine irrigation was replaced with vancomycin-gentamicin; median time to symptoms was 36 days; 19 of 21 positive cultures (90.5%) grew organisms of high virulence[14] |
| Chawareb 2025, retrospective cohort, 5,261 primary or revision patients at 16 centers | 102 infections (1.9%); diabetes (OR 1.68) and prior IPP infection (OR 4.67) were independent risk factors, and perioperative IV antifungal use was associated with lower infection odds (OR 0.22). Prolonged IV (>24 hours) and postoperative oral antibiotics were not associated with protection[15] |
These findings support review of local protocols and stewardship, with allergy, renal function, organism history and local susceptibility considered. Prolonged postoperative antibiotics have not been shown to protect. See the operative infection page for the procedure-specific discussion.[13][14][15][1]
In a meta-analysis of 14 studies (9,910 first implants), infection was 2.32% with noncoated and 0.89% with coated devices (p < 0.01), roughly a 50% reduction.[35] The "no touch" technique includes plastic draping of the skin edges to prevent skin-to-implant contact, glove changes before handling the device, and minimal device exposure time.[13]
EAU 2026 summarizes infection as 2–3% after primary implantation in low-risk men at high-volume centers, falling to 1–2% with an antibiotic-impregnated or hydrophilic-coated device,[45] and cites decolonization of nasal Staphylococcus aureus carriers with mupirocin and chlorhexidine (deep S. aureus surgical-site infection: 4.4% with placebo versus 0.9% with decolonization among surgical patients in a mixed-surgery trial).[49] It lists prolonged postoperative antibiotics beyond 24 hours, clipper shaving and chlorhexidine-alcohol preparation as measures that might help but lack definitive evidence, identifies diabetes, hypogonadism and spinal cord injury (infection up to 16% in some series) as risk factors, and describes vancomycin plus gentamicin as the most effective dip in one large diabetic cohort.[45] Removal with antibiotics is the standard response to infection; immediate washout salvage has succeeded in over 80% of cases, and no recommendation is made on how to proceed after explantation.[45] Impending erosion occurs in 1–6% and glans ischemia or necrosis in about 1.5%, more often with vascular impairment or concomitant lengthening.[45] In a 2025 database analysis of 18,475 men, infection was 3.1% at a median follow-up of 3 years, with 2.5% in the first 6 months.[36] Type 2 diabetes with comorbidities (HR 1.56), spinal cord injury (HR 2.81), obesity (HR 1.74) and concomitant circumcision (HR 2.01) were associated with infection.[36]
Outcomes and Durability
Satisfaction and Function
Many recipients report substantial improvement, but response rates, questionnaires and follow-up affect the estimate. In Luna's cohort of 542 first implants, 322 answered the questionnaire (93.1% positive responses) and 109 attended clinical reassessment.[16] Of those 109, 60.5% complained of a decrease in penile size, although objective length was greater in 61.4% and girth in 49.4%, and shortening was measured in 11% and 3.7%.[16] In a comparison of AMS 700CX and Coloplast Titan at a mean follow-up of about 58 months, EDITS scores were 77.2 and 77.5 (p = 0.956).[17] In a series of 149 men implanted before 2001, 51 were reassessed at a median 206 months; at 20 years, an estimated 41% were still using a device, and quality-of-life scores were high among continuing users.[37]
Long-Term Survival
Miller's 2022 systematic review included 12 studies and 20,161 recipients. Estimated implant survival was 87.2% at five years, 76.8% at ten, 63.7% at fifteen and 52.9% at twenty years. The pooled estimates combine different implant eras and cohorts. Five-year survival was 90.6% in newer studies and 82.1% in older ones (p = 0.01), and the authors estimate a median device survival of about 20 years.[18]
The 2025 EAU-panel systematic review included 151 studies and 92,777 patients. In a systematic review spanning inflatable and malleable penile prostheses and combined procedures, reported device-infection rates ranged from 0.03% to 14.3%, with most studies below 5%, and erosion rates from 0.02% to 32.5%. Follow-up and methods differed substantially, and mechanical failure accumulates over time.[19]
Reading Mechanical-Failure Reports
In Griggs's 72 mechanical revisions (63 Boston Scientific, 9 Coloplast), Boston Scientific failures were cylinder rupture in 41.3%, pump in 33.3%, tubing fracture in 11.1%, cylinder aneurysm in 9.5% and reservoir in 4.8%; Coloplast failures were tubing fracture in 7 of 9.[20] Median time to mechanical failure was 48 months (Boston Scientific) and 41 months (Coloplast). In Smelser's 68 revisions (46 Boston Scientific, 22 Coloplast), Coloplast devices failed at the tubing in 19 of 22, Boston Scientific devices had no predominant site, and time to failure did not differ (p = 0.096).[21] New pain, loss of rigidity, difficulty cycling, erosion or infection needs assessment for the specific cause.[20][21]
Special Clinical Settings
Peyronie's disease: concomitant ED and residual deformity influence device selection and any additional straightening. In a multicenter series of 499 men (mean preoperative curvature 39.4°), 17.6% underwent IPP placement alone.[22] Manual modeling, with or without the scratch technique, was used in 74.7% (median correction 26°), tunica plication in 4.8% (40°) and grafting in 2% (55°, in men with median preoperative curvature of 60°).[22] Adjunctive maneuvers for residual curvature are reviewed in reference 23. In a 37-man series of collagen-fleece grafting (PICS), 31 (84%) had a straight penis after implantation; in a separate 145-man scratch-technique series, mean residual curvature across three plaque locations was 14–22° immediately after surgery and 8–9° after 24 weeks of postoperative vacuum therapy.[38][39] See Prosthesis With Straightening.[23]
Ischemic priapism. AUA/SMSNA permits considering a prosthesis for untreated acute ischemic priapism >36 hours or failure of shunting, with or without tunneling .[52] Discuss the risks and benefits of early versus delayed placement ; its discussion describes early placement as within 2 weeks.[46][52] Evidence is predominantly retrospective. One series of 50 men who received immediate implants for acute ischemic priapism (43 malleable, 7 inflatable) reported 96% satisfaction and no penile shortening, with infection in 6%.[40] EAU 2026 recommends delaying implantation after a shunt to reduce infection and erosion .[24] Delayed implantation after established fibrosis may need cavernotomes, narrow-base cylinders and corporal reconstruction with grafting.[24][46] Device choice and timing depend on viable tissue, prior treatment and the patient's goals. See Priapism.[24]
After phalloplasty: the absence of native erectile tissue changes anchoring and complication risks. Cylinders are wrapped (Dacron, Gore-Tex or allograft) and fixed to the pubic bone. In a systematic review of 792 prostheses, 36.2% of patients had a complication, 60.0% still had the original implant at a mean of 3.0 years, and 83.9% achieved penetration.[26] In a 247-patient cohort (328 inflatable implants; mean follow-up 20 months), estimated 5-year device survival was 78%, infection occurred in 8.5% and revision in 43%; nonvalidated questionnaires found 88% satisfaction and 77% device use for intercourse.[41] Five-year retention in flap phalloplasty has been reported at 42–78%, lower than in native anatomy.[42] The 2026 international protocol is expert consensus.[25] See Penile Implant After Phalloplasty.
Combined AUS and IPP: a single-institution series found no increase in device infection, erosion or malfunction with combined or staged implantation, although operative time was longer (218 vs 146 minutes for IPP alone).[43] A claims-based analysis found no difference in 30- or 90-day complications or long-term device survival.[44] A database study found a higher likelihood of IPP reoperation with dual implantation at 1 year (OR 2.08) and 3 years (OR 2.60), without a statistically significant increase in AUS reoperation at either time point.[28] See AUS device hub.[27]
MRI, Activation and Follow-up
These devices are MR Conditional, not universally MRI-safe. TENACIO, Ambicor, current Titan/Prime and older implants have different specified conditions, and MRI staff check the implant's gradient, RF, SAR and duration limits, not field strength alone. Newer Titan conditions do not apply to Genesis or older models. The TENACIO IFU lists 1.5 T or 3 T, a spatial gradient up to 40 T/m, normal operating mode at 2 W/kg for up to 60 minutes and artifact extending about 33 mm, whatever the cylinder, reservoir, extender or connector.[2] The MS Pump IFU lists the same field, SAR and duration limits with about 36 mm of artifact.[50] An earlier AMS 700 with MS Pump IFU lists a static field of 3 T or less and a spatial gradient of 720 gauss/cm or less.[51] Ambicor and Coloplast devices have their own MRI conditions.[3][29]
Activation and intercourse depend on wound healing, comfort, device operation and the surgeon's instructions. The cited AMS labels describe initial cycling around 3–6 weeks and assessment for intercourse around 4–6 weeks; complicated salvage or priapism may alter timing.[2][50] The TENACIO and MS Pump IFUs state that bench testing verified reliability to at least 1,000 inflate-deflate cycles, about two erections a week for 10 years;the devices are not intended as lifetime implants.[2][50] Arrange ongoing, usually annual, device review and earlier assessment for new pain, redness, drainage, urinary problems or impaired function.[2][3]
References
1. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026: erectile dysfunction, penile prosthesis section (5.6.11.c) and recommendations (5.6.12). Guideline.
2. Boston Scientific. AMS 700 with TENACIO Pump — Instructions for Use, 51558342-01A. US English IFU. Accessed September 12, 2026.
3. Boston Scientific. AMS Ambicor Inflatable Penile Prosthesis — Directions for Use, 50654573-01C, English section. IFU. Accessed September 12, 2026.
4. Boston Scientific. AMS 700 Inflatable Penile Prosthesis, current model and ordering information. Manufacturer. Accessed September 12, 2026.
5. Coloplast. Titan Prime IPP: current product description and June 3, 2026 approval/launch announcement. Product; announcement.
6. Rigicon. Infla10 Inflatable Penile Prosthesis, current models and availability; Safety Information, INF10-07-03.2020. Manufacturer; safety document. Accessed September 12, 2026.
7. Wallen JJ, Barrera EV, Ge L, et al. Biomechanical Comparison of Inflatable Penile Implants: A Cadaveric Pilot Study. The Journal of Sexual Medicine. 2018;15(7):1034-1040. doi:10.1016/j.jsxm.2018.05.014
8. FDA. Titan Inflatable Penile Prosthesis, PMA supplement P000006/S072, approved June 2, 2026. Approval record; Titan Prime AccessGUDID record.
9. FDA. AMS 700 with TENACIO Pump, Class II recall event 97603, initiated September 11, 2025; affected models/lots and actions. All associated records; example record with action text. Accessed September 12, 2026.
10. FDA. Titan Inflatable Penile Prosthesis with Touch Pump, Class II recall event 91800, initiated March 1, 2023. Affected-device records; example action record. Accessed September 12, 2026.
11. Kavoussi M, Cook GS, Nordeck SM, et al. Distance From Critical Pelvic Structures: Radiographic Comparison of High Submuscular and Space of Retzius IPP Reservoir Placement Techniques. Urology. 2022;160:136-141. doi:10.1016/j.urology.2021.11.034
12. Baumgarten AS, Kavoussi M, VanDyke ME, et al. Avoiding Deep Pelvic Complications Using a 'Five-Step' Technique for High Submuscular Placement of Inflatable Penile Prosthesis Reservoirs. BJU International. 2020;126(4):457-463. doi:10.1111/bju.15106
13. Eid JF, Wilson SK, Cleves M, Salem EA. Coated Implants and "No Touch" Surgical Technique Decreases Risk of Infection in Inflatable Penile Prosthesis Implantation to 0.46%. Urology. 2012;79(6):1310-1315. doi:10.1016/j.urology.2011.11.076
14. Bole R, Habashy E, Yang D, et al. Timing and Causative Organisms Associated With Modern Inflatable Penile Prosthesis Infection. The Journal of Sexual Medicine. 2023;20(1):107-112. doi:10.1093/jsxmed/qdac001
15. Chawareb EA, Hammad MAM, Azad B, et al. Perioperative Antimicrobial Strategies in IPP Surgery: Associations Between Antifungals, Oral Antibiotics, and IV Antibiotic Duration, and Infection Outcomes. The Journal of Urology. 2025. doi:10.1097/JU.0000000000004716
16. Luna E, Rodriguez D, Barrios D, et al. Evaluation of Quality of Life After Inflatable Penile Implantation. The Journal of Sexual Medicine. 2022;19(9):1472-1478. doi:10.1016/j.jsxm.2022.06.018
17. Morgado A, Cavadas AS, Pacheco Figueiredo L, Tomada N. Long-Term Patient-Reported Satisfaction With Different Inflatable Penile Prosthesis: AMS 700CX vs Coloplast Titan. Revista Internacional de Andrologia. 2018;16(3):112-118. doi:10.1016/j.androl.2017.07.003
18. Miller LE, Khera M, Bhattacharyya S, et al. Long-Term Survival Rates of Inflatable Penile Prostheses: Systematic Review and Meta-Analysis. Urology. 2022;166:6-10. doi:10.1016/j.urology.2022.03.026
19. Cocci A, Capogrosso P, Minhas S, et al. Penile Prosthesis Implantation: A Systematic Review of Intraoperative and Postoperative Complications. International Journal of Impotence Research. 2026;38:93–122 (online June 2025). doi:10.1038/s41443-025-01108-4
20. Griggs R, Henry G, Vasylieva V, Karpman E. Mechanical Failure of Inflatable Penile Prostheses: Time to Failure and Reasons for Replacement. The Journal of Sexual Medicine. 2025;22(5):909-915. doi:10.1093/jsxmed/qdaf053
21. Smelser AM, VanDyke ME, Nealon SW, et al. Mechanical Indications for Inflatable Penile Prosthesis Revision. The Journal of Sexual Medicine. 2023;20(7):1044-1051. doi:10.1093/jsxmed/qdad064
22. Hammad MAM, Barham DW, Simhan J, et al. A Multicenter Evaluation of Penile Curvature Correction in Men With Peyronie's Disease Undergoing Inflatable Penile Prosthesis Placement. The Journal of Sexual Medicine. 2025;22(2):349-355. doi:10.1093/jsxmed/qdae192
23. Berookhim BM, Karpman E, Carrion R. Adjuvant Maneuvers for Residual Curvature Correction During Penile Prosthesis Implantation in Men With Peyronie's Disease. The Journal of Sexual Medicine. 2015;12 Suppl 7:449-454. doi:10.1111/jsm.13001
24. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026: priapism, immediate penile prosthesis (10.1.3.b.2) and recommendations (10.1.4). Guideline.
25. Levy M, Falcone M, Bohr J, et al. Penile Implants After Phalloplasty in Transgender Individuals: A Consensus-Based Surgical Clinical Protocol. The Journal of Sexual Medicine. 2026;23(2):qdaf365. doi:10.1093/jsxmed/qdaf365
26. Rooker SA, Vyas KS, DiFilippo EC, et al. The Rise of the Neophallus: A Systematic Review of Penile Prosthetic Outcomes and Complications in Gender-Affirming Surgery. The Journal of Sexual Medicine. 2019;16(5):661-672. doi:10.1016/j.jsxm.2019.03.009
27. Ammirati E, Polisini G, Giammò A. Surgical Treatment Options and Outcomes for Concomitant Treatment of Post-Prostatectomy Erectile Dysfunction and Male Stress Urinary Incontinence. International Journal of Impotence Research. 2026;38(3):193-205. doi:10.1038/s41443-025-01202-7
28. Patel N, Golan R, Halpern JA, et al. A Contemporary Analysis of Dual Inflatable Penile Prosthesis and Artificial Urinary Sphincter Outcomes. The Journal of Urology. 2019;201(1):141-146. doi:10.1016/j.juro.2018.07.046
29. Coloplast. MRI Compatibility and Latex Content: Penile Prostheses, August 2026. Manufacturer MRI conditions.
30. Mobley DF. Early History of Inflatable Penile Prosthesis Surgery: A View From Someone Who Was There. Asian Journal of Andrology. 2015;17(2):225-229. doi:10.4103/1008-682X.140962
31. Giordano A, Smarrazzo F, Cilio S, et al. History of Penile Implants: From Implants Made of Bone to Modern Inflatable Penile Implants. International Journal of Impotence Research. 2023;35(7):601-608. doi:10.1038/s41443-023-00695-4
32. Pastuszak AW, Lentz AC, Farooq A, Jones L, Bella AJ. Technological Improvements in Three-Piece Inflatable Penile Prosthesis Design Over the Past 40 Years. The Journal of Sexual Medicine. 2015;12 Suppl 7:415-421. doi:10.1111/jsm.13004
33. Hakky T, Lentz A, Sadeghi-Nejad H, Khera M. The Evolution of the Inflatable Penile Prosthesis Reservoir and Surgical Placement. The Journal of Sexual Medicine. 2015;12 Suppl 7:464-467. doi:10.1111/jsm.13011
34. Otero JR, Manfredi C, Wilson SK. The Good, the Bad, and the Ugly About Surgical Approaches for Inflatable Penile Prosthesis Implantation. International Journal of Impotence Research. 2022;34(2):128-137. doi:10.1038/s41443-020-0319-4
35. Mandava SH, Serefoglu EC, Freier MT, Wilson SK, Hellstrom WJ. Infection Retardant Coated Inflatable Penile Prostheses Decrease the Incidence of Infection: A Systematic Review and Meta-Analysis. The Journal of Urology. 2012;188(5):1855-1860. doi:10.1016/j.juro.2012.07.022
36. Brant W, Sato R, Rojanasarot S, et al. Infection Rates and Risk Factors Following Inflatable Penile Prosthetic Implantation: An Analysis of Real-World Hospital Data. The Journal of Sexual Medicine. 2025;22(11):2123-2129. doi:10.1093/jsxmed/qdaf224
37. Chierigo F, Capogrosso P, Dehò F, et al. Long-Term Follow-Up After Penile Prosthesis Implantation: Survival and Quality of Life Outcomes. The Journal of Sexual Medicine. 2019;16(11):1827-1833. doi:10.1016/j.jsxm.2019.08.001
38. Falcone M, Preto M, Peretti F, et al. The Use of Collagen Fleece to Correct Residual Curvature During Inflatable Penile Prosthesis Implantation (PICS Technique). The Journal of Sexual Medicine. 2023;20(2):229-235. doi:10.1093/jsxmed/qdac003
39. Antonini G, De Berardinis E, Del Giudice F, et al. Inflatable Penile Prosthesis Placement, Scratch Technique and Postoperative Vacuum Therapy. The Journal of Urology. 2018;200(3):642-647. doi:10.1016/j.juro.2018.04.060
40. Ralph DJ, Garaffa G, Muneer A, et al. The Immediate Insertion of a Penile Prosthesis for Acute Ischaemic Priapism. European Urology. 2009;56(6):1033-1038. doi:10.1016/j.eururo.2008.09.044
41. Falcone M, Garaffa G, Gillo A, et al. Outcomes of Inflatable Penile Prosthesis Insertion in 247 Patients Completing Female to Male Gender Reassignment Surgery. BJU International. 2018;121(1):139-144. doi:10.1111/bju.14027
42. Kocjancic E, Jaunarena JH, Schechter L, Acar Ö. Inflatable Penile Prosthesis Implantation After Gender Affirming Phalloplasty With Radial Forearm Free Flap. International Journal of Impotence Research. 2020;32(1):99-106. doi:10.1038/s41443-019-0153-8
43. Segal RL, Cabrini MR, Harris ED, et al. Combined Inflatable Penile Prosthesis-Artificial Urinary Sphincter Implantation: No Increased Risk of Adverse Events. The Journal of Urology. 2013;190(6):2183-2188. doi:10.1016/j.juro.2013.06.084
44. Boysen WR, Cohen AJ, Kuchta K, Park S, Milose J. Combined Placement of Artificial Urinary Sphincter and Inflatable Penile Prosthesis Does Not Increase Risk of Perioperative Complications or Impact Long-Term Device Survival. Urology. 2019;124:264-270. doi:10.1016/j.urology.2018.10.033
45. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026, section 5.6.11.c (penile prostheses).
46. American Urological Association/Sexual Medicine Society of North America. The Diagnosis and Management of Priapism: an AUA/SMSNA Guideline. 2022, statements 14–15 and discussion.
47. Canguven O, Al Saeedi A, Al Kubaisi K, Majzoub A, Elbardisi H. Scrotal Size Index: A Novel Anatomical Classification of Scrotal Morphology in Inflatable Penile Prosthesis Surgery. Sexual Medicine. 2026;14(5):qfag067. doi:10.1093/sexmed/qfag067
48. Michael S, Grice P, Oumeziane A, et al. Recognition to Repair: Managing Reservoir Complications in Inflatable Penile Prosthesis Surgery. BJUI Compass. 2026;7(7):e70246. doi:10.1002/bco2.70246
49. Bode LGM, Kluytmans JAJW, Wertheim HFL, et al. "Preventing surgical-site infections in nasal carriers of Staphylococcus aureus." N Engl J Med. 2010;362(1):9-17. doi:10.1056/NEJMoa0808939
50. Boston Scientific. AMS 700 with MS Pump: Inflatable Penile Prosthesis — Instructions for Use, 51491574-01A, English section. IFU.
51. American Medical Systems. AMS 700 with MS Pump Penile Prosthesis Product Line — Instructions for Use, 92162915-01 (2017-08), English section. IFU.
52. Bivalacqua TJ, Allen BK, Brock G, et al. "Acute Ischemic Priapism: An AUA/SMSNA Guideline." J Urol. 2021;206(5):1114-1121. doi:10.1097/JU.0000000000002236