Malleable (Semirigid) Penile Prosthesis
A malleable (semirigid) penile prosthesis is a pair of implanted rods with a bendable core. It gives support without an inflatable pump or separate reservoir, and the penis is bent upward for intercourse and downward for concealment. It is an option for erectile dysfunction when other treatments are unsuitable or unsuccessful, or when an informed patient prefers definitive prosthetic treatment. Selection depends on anatomy, tissue health, dexterity, expectations, access and cost.[1]
The three-piece inflatable prosthesis is the more common device in the United States. The malleable device is often chosen for poor manual dexterity, infection salvage, ischemic priapism after prolonged (over 48 hours) episodes, gender-affirming phalloplasty, hostile pelvis and cost-limited settings. Outside the United States it is implanted more often than the inflatable device because reimbursement is lacking and it costs less.[1][25][26][11]
For implantation and salvage, see the Penile Implants atlas.
History and Evolution
Intracorporeal penile supports began with rib cartilage in a reconstructed phallus after traumatic amputation (Bogoras, 1935–1936), followed by acrylic and polyethylene devices.[27][2] In 1975, Small and Carrion reported 31 patients with a paired silicone-rod prosthesis, which began the modern era of penile prostheses.[2] The malleable design then evolved through the current Genesis and Spectra devices, and newer models now include Rigi10, TUBE and the Zephyr ZSI 100 and 100 FTM (designed for phalloplasty).[2][26]
Construction and Current Models
Malleable designs evolved from early fixed supports and silicone devices to several different flexible cores. Tactra and the older Spectra are distinct designs with different construction and outcomes, and current malleable devices do not share one material or bending mechanism.[2][3]
| Device | Verified construction and size distinctions | Practical boundary |
|---|---|---|
| Tactra — Boston Scientific | Nitinol core with dual-layer silicone per the product description (the IFU describes a soft silicone jacket over an internal cable and does not name the metal); diameters 9.5, 11 and 13 mm with working lengths of 14–23, 16–25 and 18–27 cm, an 8 cm proximal trimmable zone and 0, 0.5 and 1 cm rear tip extenders | — |
| Genesis — Coloplast | Silver-wire coil and hydrophilic surface; diameters 9.5, 11 and 13 mm | Follow the product-specific preparation instructions; the surface is hydrophilic. |
| Rigi10 — Rigicon | Stainless-steel core, titanium end caps and HydroShield hydrophilic coating; 9, 10, 11, 12, 13 and 14 mm | The manufacturer excludes the 14 mm model from US availability. Size is chosen from corporal anatomy. |
| TUBE — Promedon | Silver-wire core, PTFE layer and silicone construction | A separate product from the Shah implant, not a Nitinol device. |
Confirm the actual model, local authorization, available sizes and supplied instructions before selection. Devices designed for a neophallus have different anchoring and tissue-support requirements from paired implantation into native corpora.[3][4][5][6][7]
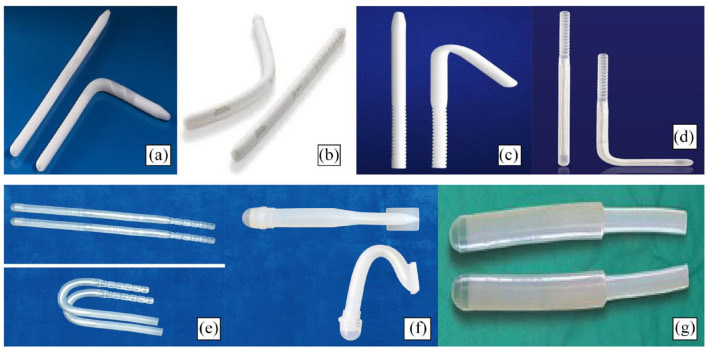
Commercially available malleable penile prostheses: (a) Coloplast Genesis; (b) Boston Scientific Tactra; (c) Rigicon Rigi10; (d) Promedon TUBE; (e) Zephyr ZSI 100; (f) Zephyr ZSI 100 FTM, designed for use after phalloplasty; (g) Shah prosthesis. From Chung E, Wang J. Ther Adv Urol. 2023;15:17562872231179008, Figure 1 (CC BY 4.0).[26]
What the Patient Trades Off
Malleable rods stay semirigid and are positioned for intercourse or concealment. They avoid pump cycling, but the patient must still position the implant, so hand function is still assessed. Persistent firmness and concealability are the main counseling points. Malleable implants give no girth or length expansion and look less natural than an inflatable device.[1]
There are no hydraulic components to leak, but mechanical failure still occurs, as do rod or shell damage, migration, erosion, pain, infection and revision. Omitting the reservoir removes that placement step but not the risk of urethral, corporal, vascular or soft-tissue injury.[3][4]
Candidate Selection and Safety
- ED and patient preference: discuss malleable, two-piece and three-piece devices in terms of the patient's priorities. Concealability is a preference to weigh and is not a contraindication to malleable implantation.
- Limited dexterity or difficult reservoir placement: malleable implantation may simplify operation or avoid a separate reservoir.[1] A two-piece inflatable implant may also be relevant.[1]
- Infection or tissue compromise: resolve active infection and assess tissue quality before routine implantation. Salvage of an infected device is a separate operation (see below) and does not make primary implantation through infection safe.
- Device-specific exclusions: Tactra safety information contraindicates use where compromised tissue would make constant pressure harmful, in patients requiring repeated endoscopic procedures beyond routine cystoscopy, and outside its stated corporal-length range. Other models have their own exclusions.[3]
Tactra's proximal nonmalleable section must remain proximal to the penoscrotal junction. Follow its marked proximal trimming instructions and avoid bending beyond the natural U shape. The IFU also states that the 0 cm extender must always be attached, that trimming should not go below the lowest graduation, that the cylinders should be dilated about 1 mm beyond their diameter with a corporotomy of about 3 cm or more for the penoscrotal approach, and that the implant is placed as a matched pair. It warns that uncircumcised men may have more wound complications with the subcoronal approach. These instructions apply to Tactra only; other rod designs have their own trimming and rear-tip extender instructions.[3]
Preparation depends on the surface and exact model. Hydrophilic devices have model-specific wetting or dipping instructions, and no single antibiotic mixture applies to all. The rods are trimmed to the measured corporal length. The approach is penoscrotal, infrapubic or subcoronal. For broader infection-prevention evidence, see the IPP hub.
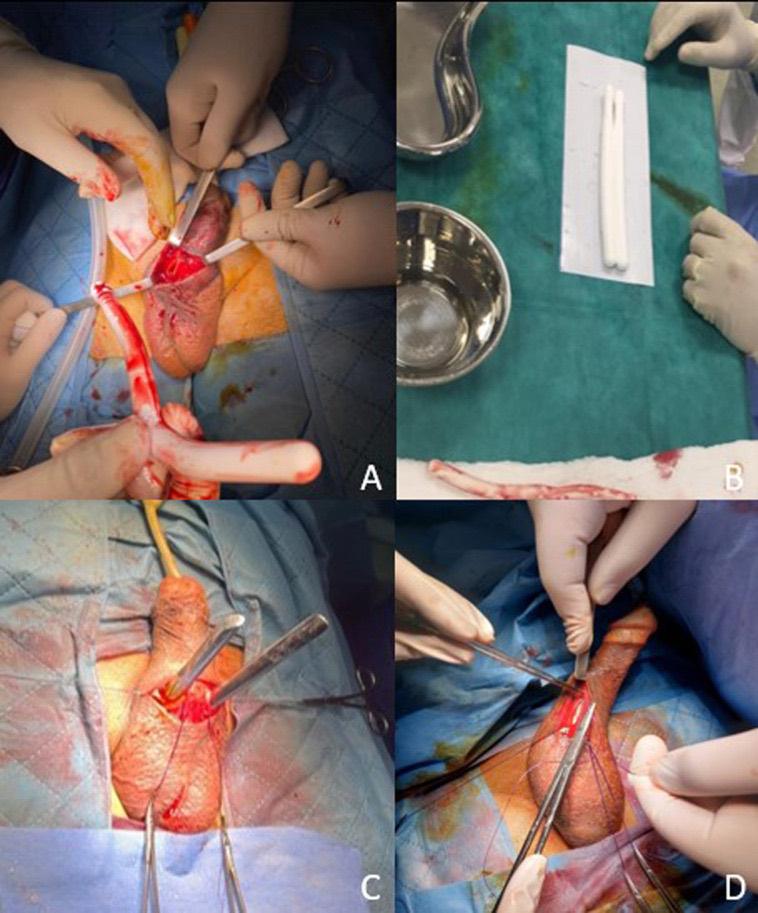
Reimplantation of a malleable penile prosthesis after urethral erosion of the previous device: (A) extraction of the right prosthesis after corporotomy; (B) selection of the new malleable rods; (C) dilation of the corpora cavernosa; (D) placement of the new rods within the corpora. From Rachid M, et al. Pan Afr Med J. 2024;49:131, Figure 2 (CC BY 4.0).[29]
Outcomes and Durability
Malleable Versus Inflatable Devices
A 2026 global EHR analysis of 29,385 men (18,749 inflatable, 10,636 semirigid) reported similar five-year revision or removal for inflatable and semirigid implants: 13.9% versus 13.7%. Mechanical breakdown was less frequent with semirigid devices (6.7% versus 9.1%), device displacement was less frequent (1.6% versus 2.3%), and explantation was more frequent (8.4% versus 6.5%). Infection did not differ. These are observational, code-based outcomes with unmeasured differences in selection and follow-up.[8]
Comparative satisfaction studies used different questionnaires, devices and populations. In a study of couples (mean follow-up 68 months), satisfaction was significantly higher with three-piece inflatable than malleable implants (p < 0.001), with no difference by brand; 27 malleable recipients (7.7%) converted to a three-piece device for dissatisfaction, versus 1 (0.2%) of inflatable recipients converted to malleable.[9] Revision for corporal perforation was most frequent with malleable devices (2.6%) and revision for malfunction with three-piece devices (5.5%).[9] Within malleable devices, Genesis and Spectra had similar EDITS satisfaction (77.1% and 75.6%, p = 0.50, n = 60), and in 46 men with Spectra (mean follow-up 3.2 years) IIEF-5 rose from 5.86 to 22.5 and EDITS was 71.1.[10][21]
Model-Specific Reports
The Rigi10 report included 605 first-time patients (46 surgeons, 15 countries), with revision or explantation in 6 (0.99%), infection in 2 (0.33%), erosion in 1, and an estimated 99.2% freedom from revision at three years. Mean follow-up was about 22 months. It used manufacturer patient-information forms and had no comparator, so it is an early device-surveillance estimate.[11]
Length Expectations
In Habous's 133 patients (88 malleable, 45 inflatable), erect length increased by 0.22 cm and girth by 0.7 cm with malleable devices, and by 0.62 cm and 1.7 cm with inflatable devices (p < 0.05), measured against preimplant stretched length and flaccid girth. Perceived length over years was not assessed. Fibrosis, prior surgery, anatomy and baseline expectations limit length, and neither device guarantees length restoration. Malleable rods are also used to conserve length in severe corporal fibrosis, because the solid rod maintains corporal space.[12][1]
Infection Salvage
The malleable implant salvage technique removes infected hardware, performs the salvage procedure and replaces it with a malleable implant, either definitively or with possible later conversion. In Gross's 58-patient retrospective series, 54 remained infection-free; 17 of those 54 later converted to an inflatable implant, at a mean of 6.7 months. In the same series 37 kept the malleable implant, and four had persistent infection and underwent explantation.[13]
In a 2026 Veterans Affairs retrospective series, 61 of 76 salvage patients at 30 centers received a malleable implant; 18 of 61 (29.5%) developed reinfection, with higher observed rates in men with diabetes (45.5% versus 20.5%, p = 0.04), while among the 43 without reinfection, 30 (70%) kept the malleable device and 12 (28%) converted electively to an inflatable device. Outcomes vary by setting and patient selection. The malleable implant also maintains corporal space during healing and may allow a later inflatable device with longer, wider cylinders. The appropriate procedure depends on infection severity, tissue viability, comorbidity, prior surgery and the patient's goals.[14]
Ischemic Priapism
AUA/SMSNA permits considering a prosthesis for untreated acute ischemic priapism >36 hours or failure of shunting, with or without tunneling , and recommends discussing the risks and benefits of early versus delayed placement .[28] Its discussion describes early placement as within 2 weeks.[28] Early implantation may limit fibrosis and shortening.[22][28] A malleable device may later be exchanged for an inflatable one, at the cost of another operation.[15] In one series of 50 men receiving immediate implants for acute ischemic priapism (43 malleable, 7 inflatable), 96% were satisfied and none reported shortening, with infection in 6%.[22] EAU 2026 recommends delaying implantation after a shunt to reduce infection and erosion risk , while describing immediate malleable implantation as the way to avoid the difficulty of delayed surgery in fibrosed corpora (a semi-rigid device is usually easier and shorter to place, although immediate inflatable placement is possible in well-counseled patients who begin cycling at once).[15] Timing decisions follow the Priapism pathway.[15]
Use After Phalloplasty
A neophallus lacks normal corporal containment; fixation, sensation and soft-tissue coverage change the risk profile. A 2024 meta-analysis of nine studies estimated complication rates of 37% for malleable and 38% for inflatable devices, with wide confidence intervals (18–62% and 21–59%) and no significant difference. The leading malleable complications were dislocation (14.9%), infection (11.2%), dysfunction (9.1%) and extrusion (7.6%). Explantation was 13% for malleable and 19% for inflatable devices (not significant).[16]
Sun's single-center series implanted 40 infrapubic malleable devices (mean follow-up 34.9 months in the 30 followed); revision was needed in 12 of 30 (40%), with no erosion or flap loss.[17] Pigot's early ZSI 100 FTM series of 25 patients (mean follow-up 6.3 months) had explantation for complications in 8 (32%).[18] In a 2025 cohort of 50 men receiving 85 ZSI FTM implants (66 hydraulic, 19 malleable), 3-year explantation-free survival after first implantation was 39% for hydraulic and 31% for malleable devices (p = 0.64), and second implantation was associated with a higher risk of late complications than first implantation (OR 3.5).[24] In a 2026 retrospective comparison of 32 patients, 74% of ZSI FtM 100 devices remained free of long-term complications at 24 months after first implantation versus 12% of conventional models (p < 0.001), although ZSI FtM 100 devices had more breakage.[19] A 2026 two-round Delphi panel of 21 experts produced a consensus protocol for preoperative assessment, surgical technique and postoperative care.[7] See the Gender-Affirming Reconstruction atlas.
Peyronie's Disease
A malleable prosthesis can be combined with plaque incision, multiple corporeal incisions and collagen-fleece grafting for complex Peyronie's disease with ED. In a series of 43 men with either implant type, mean lengthening was 2.5 cm; among the 39 who completed the satisfaction questionnaire, 89.7% would recommend the surgery. Operative time was 71.6 minutes for the malleable and 86.7 minutes for the inflatable procedure.[23]
Imaging and Follow-up
MRI eligibility is model-specific and conditional. The August 2026 Coloplast memo lists different conditions for Genesis and current Titan models, and the newer Titan parameters do not apply to Genesis or older implants. MRI staff check the implant's field, gradient, RF and scanning-duration conditions.[20] The Tactra IFU lists 1.5 T and 3 T, a spatial gradient up to 130 T/m (13,000 gauss/cm), body transmit and receive coils, normal operating mode at 2 W/kg for 15 minutes of continuous RF, a temperature rise of about 1.1 °C at 1.5 T and 0.6 °C at 3 T, and artifact extending about 29.5 mm.[3]
Provide the implant identification record and arrange ongoing device review. New pain, skin change, drainage, exposure, urinary difficulty, loss of support or difficulty positioning the device merits assessment. Persistent firmness is expected; progressive pressure injury or erosion is not.[3][4]
References
1. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026: erectile dysfunction, penile prosthesis section (5.6.11.c) and recommendations (5.6.12). Guideline.
2. Martinez DR, Terlecki R, Brant WO. The Evolution and Utility of the Small-Carrion Prosthesis, Its Impact, and Progression to the Modern-Day Malleable Penile Prosthesis. The Journal of Sexual Medicine. 2015;12 Suppl 7:423-430. doi:10.1111/jsm.13014
3. Boston Scientific. Tactra Malleable Penile Prosthesis: current product description and safety information, 51519609-01A. Product; safety information. Accessed September 12, 2026.
4. Coloplast. Genesis Malleable Penile Prosthesis: current product and brief safety information, PM-16954, April 2024. Manufacturer. Accessed September 12, 2026.
5. Rigicon. Rigi10 Malleable Penile Prosthesis: device construction, ordering and availability. Manufacturer. Accessed September 12, 2026.
6. Promedon. TUBE Malleable Penile Prosthesis: device construction. Manufacturer brochure. Accessed September 12, 2026.
7. Levy M, Falcone M, Bohr J, et al. Penile Implants After Phalloplasty in Transgender Individuals: A Consensus-Based Surgical Clinical Protocol. The Journal of Sexual Medicine. 2026;23(2):qdaf365. doi:10.1093/jsxmed/qdaf365
8. Kohl S, Goebel C, Kuzina A, et al. Inflatable Penile Prostheses Long-Term Revision and Removal Rates Compared to Semi-Rigid Penile Prostheses: A Real-World Analysis From a Global EHR Database. The Journal of Sexual Medicine. 2026;23(3):qdag034. doi:10.1093/jsxmed/qdag034
9. Çayan S, Aşcı R, Efesoy O, et al. Comparison of Long-Term Results and Couples' Satisfaction With Penile Implant Types and Brands: Lessons Learned From 883 Patients With Erectile Dysfunction Who Underwent Penile Prosthesis Implantation. The Journal of Sexual Medicine. 2019;16(7):1092-1099. doi:10.1016/j.jsxm.2019.04.013
10. Casabé AR, Sarotto N, Gutierrez C, Bechara AJ. Satisfaction Assessment With Malleable Prosthetic Implant of Spectra (AMS) and Genesis (Coloplast) Models. International Journal of Impotence Research. 2016;28(6):228-233. doi:10.1038/ijir.2016.33
11. Wilson SK, Wen L, Carrion R, et al. Safety Outcomes of the First Rigi10™ Malleable Penile Prostheses Implanted Worldwide. International Journal of Impotence Research. 2024;36(8):833-837. doi:10.1038/s41443-023-00761-x
12. Habous M, Giona S, Tealab A, et al. Penile Length Is Preserved After Implant Surgery. BJU International. 2019;123(5):885-890. doi:10.1111/bju.14604
13. Gross MS, Phillips EA, Balen A, et al. The Malleable Implant Salvage Technique: Infection Outcomes After Mulcahy Salvage Procedure and Replacement of Infected Inflatable Penile Prosthesis With Malleable Prosthesis. The Journal of Urology. 2016;195(3):694-697. doi:10.1016/j.juro.2015.08.091
14. Angulo-Llanos L, Sandler MD, Howell NB, Williams A, Masterson TA. Outcomes of Salvage Procedures With Malleable Implants for Penile Prosthesis Infections in the Veterans Affairs National Medical System. The Journal of Sexual Medicine. 2026;23(3):qdag042. doi:10.1093/jsxmed/qdag042
15. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026: priapism, immediate penile prosthesis (10.1.3.b.2) and recommendations (10.1.4). Guideline.
16. Fraiman E, Nandwana D, Loria M, et al. Complication and Explantation Rates of Penile Prostheses in Transmasculine Patients: A Meta-Analysis. Urology. 2024;194:260-268. doi:10.1016/j.urology.2024.08.022
17. Sun HH, Isali I, Mishra K, et al. Surgical Outcomes at a Single Institution of Infrapubic Insertion of Malleable Penile Prosthesis in Transmen. Urology. 2023;173:209-214. doi:10.1016/j.urology.2023.01.001
18. Pigot GLS, Sigurjónsson H, Ronkes B, Al-Tamimi M, van der Sluis WB. Surgical Experience and Outcomes of Implantation of the ZSI 100 FtM Malleable Penile Implant in Transgender Men After Phalloplasty. The Journal of Sexual Medicine. 2020;17(1):152-158. doi:10.1016/j.jsxm.2019.09.019
19. Levy M, van Abbema EL, Ronkes BL, et al. Out With the Old, in With the New? A Retrospective Comparison of Malleable Erectile Implants in Phalloplasty. BJU International. 2026. doi:10.1111/bju.70166
20. Coloplast. MRI Compatibility and Latex Content: Penile Prostheses, August 2026. Manufacturer MRI conditions.
21. Akdemir F, Okulu E, Kayıgil Ö. Long-Term Outcomes of AMS Spectra Penile Prosthesis Implantation and Satisfaction Rates. International Journal of Impotence Research. 2017;29(5):184-188. doi:10.1038/ijir.2017.16
22. Ralph DJ, Garaffa G, Muneer A, et al. The Immediate Insertion of a Penile Prosthesis for Acute Ischaemic Priapism. European Urology. 2009;56(6):1033-1038. doi:10.1016/j.eururo.2008.09.044
23. Fernández-Pascual E, Gonzalez-García FJ, Rodríguez-Monsalve M, et al. Surgical Technique for Complex Cases of Peyronie's Disease With Implantation of Penile Prosthesis, Multiple Corporeal Incisions, and Grafting With Collagen Fleece. The Journal of Sexual Medicine. 2019;16(2):323-332. doi:10.1016/j.jsxm.2018.11.014
24. Levy M, van der Sluis WB, van Abbema EL, et al. Hydraulic and Malleable Female-to-Male Penile Implants After Phalloplasty in Transgender Individuals: A Retrospective Cohort Analysis. BJU International. 2025. doi:10.1111/bju.16911
25. Khera M, Mulcahy J, Wen L, Wilson SK. Is There Still a Place for Malleable Penile Implants in the United States? Wilson's Workshop #18. International Journal of Impotence Research. 2023;35(2):82-89. doi:10.1038/s41443-020-00376-6
26. Chung E, Wang J. State-of-Art Review of Current Malleable Penile Prosthesis Devices in the Commercial Market. Therapeutic Advances in Urology. 2023;15:17562872231179008. doi:10.1177/17562872231179008
27. Giordano A, Smarrazzo F, Cilio S, et al. History of Penile Implants: From Implants Made of Bone to Modern Inflatable Penile Implants. International Journal of Impotence Research. 2023;35(7):601-608. doi:10.1038/s41443-023-00695-4
28. American Urological Association/Sexual Medicine Society of North America. The Diagnosis and Management of Priapism: an AUA/SMSNA Guideline. 2022, statements 14–15 and discussion. Companion publication: Bivalacqua TJ, Allen BK, Brock G, et al. Acute Ischemic Priapism: An AUA/SMSNA Guideline. The Journal of Urology. 2021;206(5):1114-1121. doi:10.1097/JU.0000000000002236
29. Rachid M, Lazrak O, Rais H, El Omri G, Houry Y, Heddat A. Reimplantation of a Malleable Penile Prosthesis in a Patient With Urethral Erosion: A Case Report. Pan African Medical Journal. 2024;49:131. doi:10.11604/pamj.2024.49.131.45236