Penrose Drain
A Penrose drain is a flexible, open, passive wound drain that allows fluid to travel along its surfaces into a dressing or collection appliance. It has no suction reservoir.[1] The Cardinal product line is latex and radiopaque.[1]
The drain is named for Charles Bingham Penrose, an American gynecologist. It was the standard surgical drain for much of the twentieth century and has been largely replaced by closed-suction systems.[4]
For broader indications and removal decisions, see JP and wound-drain guidance. For a closed silicone channel drain, see Blake Drain.
Design
The Cardinal catalog lists sterile radiopaque latex Penrose drains in widths from 1/4 to 1 inch and lengths of 12, 18 and 36 inches.[1] The flat tube collapses when empty and is cut to length at the operation. One end lies in the wound or cavity and the other exits through the skin. Fluid moves along the tube surface by capillary action and gravity into a dressing, so the drain applies no negative pressure.
When the design is useful
An open passive drain may suit a selected superficial wound or cavity that needs a maintained drainage route. Its usefulness depends on position, the wound opening, the fluid and continued drainage.
| Feature | Clinical implication |
|---|---|
| Passive drainage | No bulb activation is needed, but positioning, dressing care and patency still require attention. |
| Open exit | Drainage reaches the dressing or appliance; protect surrounding skin and monitor soiling. |
| No measuring reservoir | Precise output measurement is harder and may require a suitable collection appliance. |
| Flexible tube | Securement is needed to avoid inward migration or displacement. Softness does not remove the risks of retention, tissue injury or difficult removal. |
| Material | Check latex allergy and use an appropriate alternative when needed.[1] |
Neither design guarantees freedom from infection.
Open versus closed drainage
| Feature | Penrose (open) | JP or Blake (closed) |
|---|---|---|
| Drainage mechanism | Gravity and capillary action | Negative pressure |
| Collection | Dressings, with no reservoir | Sealed bulb or canister |
| Barrier to external bacteria | None | Closed system |
| Output measurement | Not reliable | Measured in the reservoir |
| Drain-fluid creatinine for urine leak | Difficult, because the fluid mixes with skin and dressings | Direct sampling |
Bacterial migration
In a rabbit splenectomy model, the skin near the drain exit was inoculated with Streptococcus. At 72 hours, none of the 20 undrained controls had positive intraperitoneal cultures. Cultures of the splenic bed were positive in 18 of 20 animals (90%) with a Penrose drain; with a JP drain, 4 of 20 (20%) had a positive culture from the drain or splenic bed (P < 0.001).[5] A two-center prospective observational study across surgical divisions associated open drains with surgical site infection compared with closed drains (OR 3.68, 95% CI 1.88 to 6.89).[6] The association varied with the surgical division, wound class and duration of surgery.[6] These data explain the decline of open drainage.
Sampling and monitoring
Assess wound appearance, pain, swelling, fever, drainage character and the adequacy of ongoing drainage. A sudden reduction in discharge with worsening swelling or systemic symptoms requires reassessment.
Contaminated dressing fluid is an unreliable specimen. If testing is needed, obtain fresh fluid aseptically using a collection method agreed with the laboratory. IDSA/ASM cautions that cultures from long-standing drains, particularly after more than three days, can reflect colonization rather than the cause of infection.[2]
Give the patient or caregiver explicit instructions for dressings, skin care, protecting the drain, recognizing displacement and contacting the treating team.
Urologic use
Partial nephrectomy. Some surgeons prefer a Penrose after open partial nephrectomy because they expect suction to prolong a urine leak from the collecting-system repair or to promote delayed hemorrhage. In a retrospective series of 197 partial nephrectomies (184 patients) at one center, with the drain chosen by the surgeon, no significant difference in urine leak or hemorrhage was found.[7]
| Parameter | Closed suction (n = 123) | Penrose (n = 74) |
|---|---|---|
| Mean drainage duration | 7.8 days | 7.1 days |
| Prolonged urinary drainage | 8.9% | 5.4% |
| Wound infection or perinephric abscess | 2.4% | 5.4% |
| Delayed hemorrhage | 2.4% | 0% |
None of the differences was statistically significant. Randomized and observational data on omitting the drain altogether are summarized on the JP drain page.
Other settings. An open drain may be chosen for a contaminated or infected open wound, such as after Fournier debridement, where a wick or open-cavity route is wanted. After radical prostatectomy or cystectomy, closed suction is the usual choice when a drain is placed.
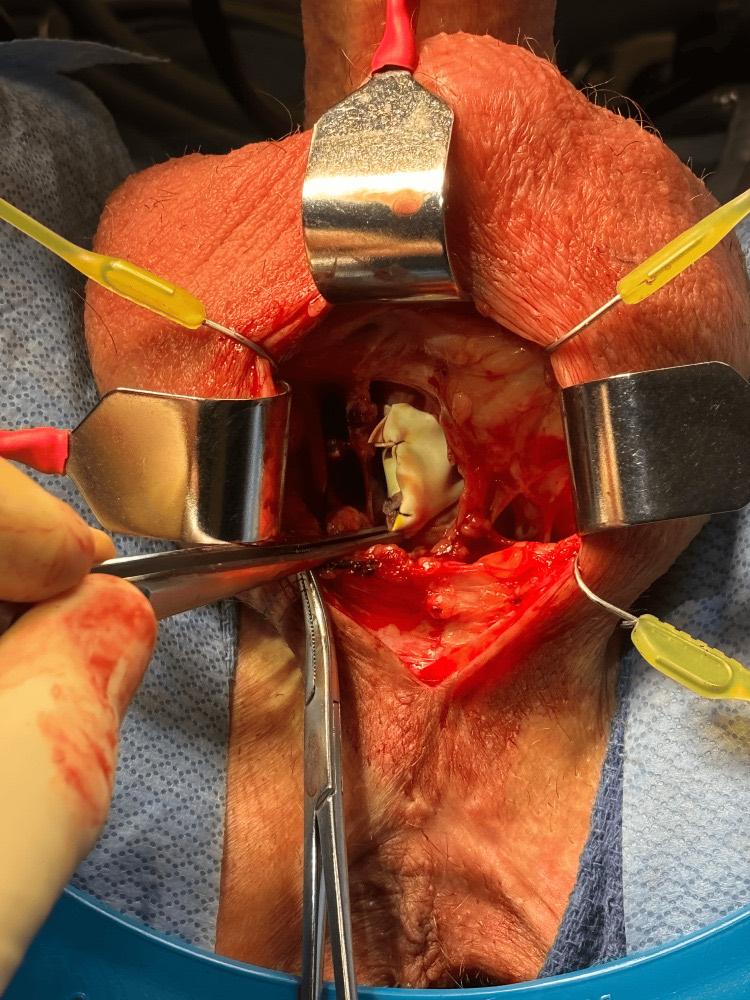
Perineal view of a 1-inch Penrose drain placed around the urethra as a temporary spacer after removal of an artificial urinary sphincter cuff during rectourethral fistula repair, to preserve the periurethral space for later cuff reimplantation. From Sheiber J, Wiegand LR. Cureus. 2024;16(11):e73137, Figure 1 (CC BY 4.0).[9]
Complications
- Retrograde bacterial migration and surgical site infection. See the comparison above.[5][6]
- Loss of output measurement. Output flows into dressings, so daily volume is difficult to measure and fluid absorbed by a dressing is unsuitable for drain-fluid creatinine testing. If testing is needed, collect fresh fluid by a method agreed with the laboratory.
- Skin maceration. Drainage contacts the skin at the exit site.
- Unpredictable drainage. Flow depends on patient position, and an open passive drain can obstruct.
- Latex allergy. The Cardinal Penrose line is latex.[1]
- Retained drain. A drain sutured to surrounding tissue can be retained. Secure it so it cannot migrate inward, and confirm removal is complete.
Closed-suction systems generated maximal negative pressures of 71 to 175 mm Hg with empty reservoirs in a bench study, and stripping raised pressure further.[8] A Penrose applies no suction to the tissue. It also needs no evacuator teaching and is easy to remove at the bedside.
Removal and antibiotics
Set a removal plan based on the purpose of drainage, wound condition and clinical progress. Do not apply a universal calendar or a closed-suction output threshold to an open drain. WHO conditionally suggests removing closed wound drains when clinically indicated; the evidence did not identify an optimal time for SSI prevention.[3]
Remove the securing material and drain with attention to unexpected resistance, then confirm that the device is intact. Continued swelling, discharge or infection may require further assessment even after removal.
Do not continue prophylactic antibiotics solely because a drain remains. Antibiotics for an established infection follow the diagnosis, source-control assessment and microbiology.[3]
References
1. Cardinal Health. Jackson-Pratt Wound Drains: product catalog. 2021. Manufacturer catalog (distributor-hosted copy).
2. Miller JM, Binnicker MJ, Campbell S, et al. Guide to utilization of the microbiology laboratory for diagnosis of infectious diseases: 2024 update by IDSA and ASM. Clin Infect Dis. 2024. Interventional Radiology and Drain Devices. doi:10.1093/cid/ciae104.
3. World Health Organization. Global Guidelines for the Prevention of Surgical Site Infection. 2nd ed. 2018. Section 4.26: antibiotics and drain removal and Web Appendix 27: systematic review.
4. Meyerson JM. A brief history of two common surgical drains. Ann Plast Surg. 2016;77(1):4–5. doi:10.1097/SAP.0000000000000734.
5. Raves JJ, Slifkin M, Diamond DL. A bacteriologic study comparing closed suction and simple conduit drainage. Am J Surg. 1984;148(5):618–620. doi:10.1016/0002-9610(84)90336-2.
6. Mujagic E, Zeindler J, Coslovsky M, et al. The association of surgical drains with surgical site infections: a prospective observational study. Am J Surg. 2019;217(1):17–23. doi:10.1016/j.amjsurg.2018.06.015.
7. Sánchez-Ortiz R, Madsen LT, Swanson DA, Canfield SE, Wood CG. Closed suction or Penrose drainage after partial nephrectomy: does it matter? J Urol. 2004;171(1):244–246. doi:10.1097/01.ju.0000099940.02698.38.
8. Grobmyer SR, Graham D, Brennan MF, Coit D. High-pressure gradients generated by closed-suction surgical drainage systems. Surg Infect (Larchmt). 2002;3(3):245–249. doi:10.1089/109629602761624207.
9. Sheiber J, Wiegand LR. Novel utilization of a Penrose drain as a spacer during temporary artificial urinary sphincter explantation and rectourethral fistula repair. Cureus. 2024;16(11):e73137. doi:10.7759/cureus.73137.