Double-J (DJ) Ureteral Stent
A double-J (DJ) stent provides internal drainage from the renal pelvis to the bladder across a ureteral obstruction or healing repair. Its two pigtail curls help retain position; migration, obstruction and encrustation can still occur. Before placement, decide why the stent is needed, how its function will be checked, and who will remove or exchange it.[1][2] Finney described the double-J catheter stent in 1978.[14]
For device-specific long-term options, see Metal & Long-Term Stents. Nephrostomy provides external drainage, while a nephroureteral catheter retains an external access port.
History
- 1967. Davis and Zimskind described indwelling silicone ureteral tubing for internal drainage.[15]
- 1972. Robert Gibbons developed the first commercially available ureteral stent. It had collapsible "wings" against distal migration, a barium-impregnated proximal tip for radiographic visualization, a distal flange that limited proximal migration and trigonal irritation, and a tail to aid removal. Its introduction established CPT code 52332, still in use.[15]
- 1978. Finney introduced the self-retaining double-J stent, with a J curl at each end.[14]
- 1984. Andriole and colleagues reported 87 patients with indwelling double-J stents for temporary and permanent drainage.[16]
- Since the 1990s. Materials (polyurethane, silicone, copolymers), coatings (hydrophilic, antibacterial, anti-encrustation) and designs (metallic, biodegradable, drug-eluting) have evolved.[1][47]
Selection and Placement
Choose the length, caliber, material and dwell limit of the actual product, accounting for ureteral length, obstruction, transplant or reconstructed anatomy, expected debris and tolerance. In a retrospective ureteric-stricture series, migration followed 22/45 placements into orthotopic neobladders versus 4/35 into native bladders; 18/22 migrated neobladder stents had dysfunction.[51] A smaller diameter can improve symptoms in some settings.[1][2]
Diameter. Adult stents range from about 4.7 to 8.5 Fr, and 6 Fr is common. In a randomized comparison of 181 patients with ureteral stones undergoing staged ureteroscopy, USSQ scores favored 4.7 Fr over 6 or 7 Fr stents. Differences were significant in all subdomains only for 4.7 versus 7 Fr, and success of the second ureteroscopy exceeded 82% in every group.[17]
Length. Adult stents are usually 22–28 cm, with shorter lengths for children. Two approaches are compared here, and the evidence conflicts on which is more accurate.
- Height formula. With a height of less than 178 cm, a 22 cm stent is used; 178–193 cm, 24 cm; above 193 cm, 26 cm. In 41 ureters with 8 Fr Percuflex stents, this formula gave an acceptable length in 61%, and no stent was too short. Direct ureteral measurement oversized the stent in 83%, and the authors suggested that a redundant ureter shortens under the stent.[18]
- CT or direct endoscopic measurement. In 59 ureters, ureteral length on CT correlated with directly measured length (rho 0.63–0.64), whereas height correlated poorly (rho 0.18). Ideal position (both curls fully coiled, bladder curl not crossing midline) was reached in 100% when stent length matched measured ureteral length versus 70.9% when mismatched (p = 0.006).[19]
- Pediatric length. A single-center CT study of healthy children under 16 (at least 10 measurements per age class) proposed stent length equal to age in years plus 12 cm, based on mean right/left ureteral lengths of 9.7/9.91 cm before age 1, 20.10/21.08 cm at age 7 and 26.55/27.46 cm at age 16. The authors call for prospective confirmation before treating this as a validated sizing standard.[50]
| Material | Characteristics | Typical use |
|---|---|---|
| Polyurethane | Tunable stiffness and good radiopacity; firmer designs are associated with more hematuria and lower body pain, while encrustation also depends on dwell time and patient factors[33][55] | Short to medium term |
| Silicone | Softer and better tolerated; higher friction and lower radial strength | Longer term or sensitive patients |
| Hybrid copolymers (for example Percuflex, C-Flex) | Proprietary blends with product-specific flexibility; encrustation risk depends on dwell time and patient factors[1][33] | General use |
| Metallic (for example Resonance, Memokath, Allium) | Resist extrinsic compression; higher cost and specialized placement | Malignant or chronic extrinsic obstruction |
| Biodegradable | Degrade without removal; investigational | Not in routine clinical use |
The material characteristics above are general descriptions of device classes; individual products differ, and the product's instructions for use govern dwell limits.
Polymer and silicone products differ in stiffness, coatings and permitted duration. The tightly coiled metallic Resonance is not a nitinol self-expanding segmental stent; its delivery method and 12-month maximum indwell are addressed in the metal-stent hub. No material guarantees freedom from biofilm or encrustation.[1][3]
Retrograde placement usually uses cystoscopy, a guidewire and imaging; antegrade or combined access is useful when retrograde access fails. After PCN for an infected obstructed system, elective antegrade internalization follows clearance of infection.[2] Confirm the wire and both curls are in their intended locations. Resistance requires reassessment rather than force. Avoid assuming that an apparently well-positioned stent is functionally draining a compressed ureter or a high-pressure bladder.[2][4]
When a Stent Helps
| Situation | Practical role |
|---|---|
| Sepsis with an obstructing stone | Urgent decompression by a stent or PCN, with immediate antibiotics and cultures; defer definitive stone treatment until sepsis resolves. EAU 2026 strongly recommends urgent decompression by percutaneous drainage or ureteral stenting when an obstructing stone causes sepsis, and strongly recommends delaying definitive stone treatment until sepsis has resolved. Stents and nephrostomy tubes are equally effective for decompression (LE 1b); the EAU text notes that a stent affects quality of life more than a nephrostomy tube because of stent symptoms, while nephrostomy is associated with a longer hospital stay. Choose the approach most likely to achieve timely drainage.[5] |
| Benign or malignant obstruction | Bypass an obstruction when internal drainage is feasible. Consider PCN, a PCNU, selected long-term devices or reconstruction if access, patency or tolerance is inadequate.[2] |
| Ureteral injury or reconstruction | Support drainage across a repair or selected partial injury. Complete injury, devitalized tissue and persistent leaks may require reconstruction or additional diversion; a stent is not a substitute for a viable, tension-free repair.[6] |
| Ureteroscopy | Selective postoperative drainage or staged access, as below.[5] |
| Kidney transplantation | Prophylactic anastomotic stenting reduces major urological complications; technique and removal timing remain transplant-specific.[7] |
A prophylactic ureteral catheter can aid identification during complex pelvic surgery. EAU 2026 weakly recommends preoperative stents in cases at high risk of ureteral injury and strongly recommends visual identification; it states that prophylactic stents do not prevent injury and emphasizes careful dissection.[6]
Stenting Around Ureteroscopy
The EAU 2026 guideline gives a strong recommendation not to insert a stent in uncomplicated cases (evidence summary LE 1a: a post-procedure stent need not be inserted after uncomplicated URS). It advises inserting a stent in patients at increased risk of complications, and in all doubtful cases (for example ureteral trauma, residual fragments, bleeding, perforation, UTI or pregnancy). The ideal duration is not known; the text cites a trial in which 3 days gave better urinary, pain and general health scores than 7 days. Smaller-diameter stents may reduce symptoms and pain, and a stent on a string or a ureteral catheter left for one day after uncomplicated URS gave shorter indwelling time and similar or better patient-reported outcomes. The EAU evidence summary states that pre-stenting improves outcomes for renal stones (level 2a) but not for ureteral stone procedures, and that patients have stent symptoms while waiting. A stent followed by another attempt after 7–14 days is an option when ureteral access cannot be obtained safely.[5]
Comparative evidence supports this balance. A 2016 meta-analysis of 17 studies (1,943 participants) found that unstented patients had more unplanned medical visits (OR 1.63, 95% CI 1.15–2.30) but less dysuria (RR 0.39, 95% CI 0.25–0.62).[48] The 2019 Cochrane review judged that stenting may slightly reduce unplanned return visits (very low certainty), may leave secondary interventions unchanged (RR 1.15, 95% CI 0.39–3.33; low certainty), and is probably associated with similar pain on the day of surgery.[49]
Postoperative dwell time depends on the reason for drainage, injury, residual burden and planned second procedure.[5]
- A 2026 systematic review (32 studies, 4,373 patients) found that dwell times most often ranged from 10 to 14 days in uncomplicated cases, with longer dwell associated with more encrustation and removal difficulty. The authors suggested 10–14 days as a window balancing healing against encrustation.[25]
- In a cohort of 4,437 procedures, emergency department visits were more likely when a string-stent dwell was 4 days or less in non-prestented patients; the authors recommended at least 5 days.[8]
- In a 3-day versus 7-day removal comparison, the 3-day group reported better urinary, pain and general-health scores, with no significant difference in complications.[9]
Kidney Transplantation: What the Evidence Establishes
| Evidence | Finding and limit |
|---|---|
| Cochrane 2024 | Twelve studies, 1,960 recipients. Major urological complications were reduced in 11 studies/1,834 recipients: RR 0.30 (95% CI 0.16–0.55), moderate certainty, with the benefit also seen for urine leak and ureteral obstruction separately. The benefit held for stenting of 14 days or less (RR 0.39, 0.21–0.72) and for longer stenting (RR 0.22, 0.08–0.61). The UTI effect remained uncertain: RR 1.32 (0.97–1.80), very low certainty. Longer stents (20 cm or more) left in place beyond 6 weeks had more encrustation and migration. The review calls for further trials to define the optimal duration.[7] |
| DUET trial, 2025 | Single-center randomized comparison of external Single-J removed on day 9 versus internal Double-J removed at 3 weeks. PCN within 6 months occurred in 21/145 (14.5%) versus 7/155 (4.5%), respectively (p = 0.003). This compares two care protocols, including different duration and discharge rules. Reconstructed tracts and bladder dysfunction requiring catheterization were excluded.[10] |
| Yin 2026 meta-analysis | Sixteen RCTs (2,486 patients) contributed to the urine-leak estimate (RR 0.25, 95% CI 0.13–0.47); 14 trials contributed to the ureteral obstruction or stricture estimate (RR 0.42, 0.25–0.71) and 14 to the UTI estimate (RR 1.41, 1.08–1.84). These are Yin estimates from a larger study set than the 12-study Cochrane review.[7][11] |
| Patel 2017 RCT | Multicenter randomized comparison of day-5 versus 6-week stent removal (227 randomized, 205 analyzed). In the per-protocol analysis, composite stent-related complications within 3 months occurred in 6/79 (7.6%) with early versus 36/126 (28.6%) with late removal (p < 0.001), mostly UTI (7.6% vs 24.6%).[12] |
| Amara 2026 NSQIP cohort | 3,407 recipients, 75.6% stented. Major urological complications were similar (2.4% unstented vs 2.5% stented). UTI was higher with stenting (7.4% vs 3.2%; adjusted OR 2.22, 1.48–3.43). This registry analysis is observational.[39] |
Shorter transplant stenting can reduce the UTI burden in appropriate protocols. Coordinate removal with the transplant team, particularly after a leak, difficult implantation or impaired drainage.[7][12]
Symptoms and Complications
Frequency, urgency, dysuria, hematuria and flank discomfort are common.[1][2] Fever, rigors, worsening flank pain, reduced urine output or persistent or heavy bleeding warrant assessment for infection, obstruction, migration or another complication.[1][2] In patients with a chronic stent or a history of pelvic oncologic surgery, vascular surgery or irradiation, intermittent hematuria warrants urgent assessment for arterio-ureteral fistula.[52]
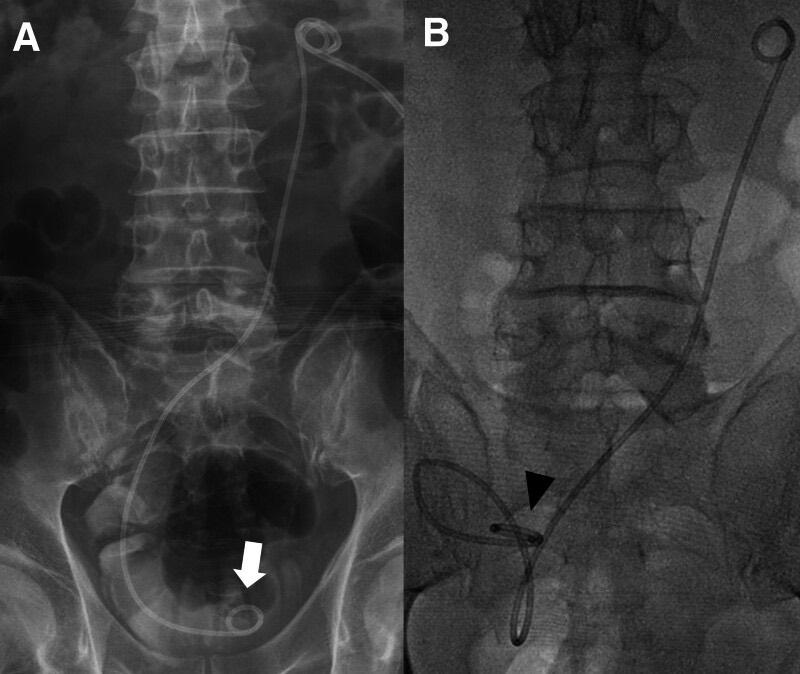
Proximal migration of a double-J stent placed antegrade for ureteroileal anastomotic stricture after radical cystectomy and orthotopic neobladder. (A) Radiograph just after placement shows the distal curl (arrow) correctly positioned. (B) Two weeks later the distal tip (arrowhead) has migrated proximally to near the ureteroileal anastomosis. From Oh CH, et al. Medicine (Baltimore). 2024;103(16):e37765, Figure 4 (CC BY 4.0).[51]
In a prospective observational study of 232 patients who completed the USSQ after ureteroscopy with stenting, 59.1% had daytime frequency of at least once per hour, 90.1% had nocturia, 86.6% urgency and 82.3% burning. Pain was reported by 83.2% (kidney 67.9%, bladder area 31.3%), and it interfered with daily life in 92.2%. Of the patients, 62% would be dissatisfied if another stent were proposed, and younger patients and women were more affected. The study lacked baseline evaluation.[20]
Stent pain is multifactorial. Reviews attribute it to mucosal irritation (including trigonal irritation from the bladder curl) and retrograde reflux of urine through the stent during voiding, with ureteral spasm also proposed.[21]
Medical management
Check position and drainage, then individualize symptom treatment. EAU 2026 states that an α-blocker can reduce stent-related symptoms and colic episodes after URS (LE 1a), and strongly recommends offering medical expulsive therapy for stent-related symptoms and after laser lithotripsy to facilitate fragment passage.[5] In a meta-analysis of five trials (461 patients), α-blockers lowered the USSQ urinary symptom score by a mean of 8.4 points (95% CI 5.6–11.1) and the body pain score by 7.2 (2.5–11.8); in three trials reporting pain episodes, 51/114 (45%) α-blocker recipients versus 88/116 (76%) controls had episodes during study-defined follow-up (RR 0.59, 0.47–0.71).[5][23] Pharmacology, dosing and hypotension precautions belong in the alpha-blocker hub.
A Bayesian network meta-analysis of 26 randomized studies found that the most effective regimen differed by symptom domain:[22]
| Symptom domain | Highest-ranked regimen |
|---|---|
| Urinary symptoms | Silodosin 8 mg plus solifenacin 10 mg |
| Pain | Silodosin 8 mg plus solifenacin 10 mg |
| Sexual performance | Tadalafil 5 mg |
| General health | Silodosin 8 mg plus solifenacin 10 mg plus tadalafil 5 mg |
| Work performance | Solifenacin 10 mg |
These regimen rankings are indirect. Silodosin is contraindicated at creatinine clearance <30 mL/min and is dosed at 4 mg once daily with a meal at 30–50 mL/min.[53] Solifenacin is limited to 5 mg once daily at creatinine clearance <30 mL/min/1.73 m² and is contraindicated in urinary retention.[54] In a 2024 randomized comparison, solifenacin 10 mg plus tamsulosin 0.4 mg reduced pain more than control (p = 0.001), and no single drug was clearly superior.[24] A 2025 meta-analysis found that mirabegron improved USSQ urinary symptoms versus control in four RCTs (158 versus 167 patients; mean difference −8.71, 95% CI −15.81 to −1.61) and reduced analgesic use in four RCTs (227 versus 239 patients; mean difference −1.56, 95% CI −2.70 to −0.41).[57]
Bacteriuria or colonization alone does not establish symptomatic UTI. Manage infection and procedure-specific antimicrobial needs through the UTI treatment and perioperative prophylaxis hubs. Planned mucosa-traumatizing endourologic procedures and pregnancy have separate bacteriuria recommendations.[13]
Removal, Exchange and Follow-Up
- Record side, product, size, insertion date, indication, removal or exchange deadline and responsible clinician in a stent register; give the patient the plan and a route to contact the service.
- Follow the device's maximum dwell limit and shorten the interval for encrustation, infection, obstruction or other clinical concerns.
- Removal may be cystoscopic or, for an appropriate device and patient, by an extraction string or another specified retrieval system.
- Do not force removal of a retained or encrusted stent. Image and plan endoscopic or staged removal according to the burden and location of encrustation.
- Confirm resolution of the underlying drainage problem when clinically required.[1][2]
Dwell time and encrustation
In a European multicenter retrospective study of 473 removed stents (indwelling 60–679 days), one-third had been in place more than 6 months and 9% more than 1 year. For non-stone indications, clinically significant encrustation was 1.3% before 4 months and 5.2% before 6 months, rising to about 10% long term. For stone indications, it was 8% before 4 months and nearly 17% after.[26] In a retrospective series of 33 patients, the reported dwell-time associations at 45–90 days (p = 0.008) and >90 days (p = 0.01) concerned low-grade encrustation; tests for moderate and severe grades at those intervals were not statistically significant.[27] Encrustation risk factors include prolonged dwell, stone history, infection, pregnancy and cystinuria.[33][26]
Extraction strings and removal methods
Across 32 studies, removal was by rigid cystoscopy in 48.7%, flexible cystoscopy in 19.9%, extraction string in 23.5% and device-assisted methods in 7.9%. Flexible cystoscopy and string removal were associated with lower pain scores, and strings carried a small risk of premature dislodgement.[25] A systematic review of 22 studies (8,382 patients, mostly after ureteroscopy) reported shorter dwell, less pain and cost savings with strings, and more than 90% of patients willing to remove the stent at home.[28] In a prospective series of 168 patients, self-removal succeeded in 79%, stents dislodged early in 3.0% and the string detached in 1.8%.[29] In a controlled trial, string removal about 10 days after ureteroscopy was less painful than cystoscopic removal (mean VAS 2.73 vs 5.67, p < 0.001); the difference was significant in men and not in women.[30]
Retained and forgotten stents
A forgotten stent is preventable. A 45-year-old woman with a stent retained for 6 years after open ureterolithotomy presented with a 4.2 cm vesical stone that required pneumatic lithotripsy.[34] Management scales with the encrustation burden, and computerized stent tracking has been advocated.[33] In a prospective series of 51 patients, a complete retrograde ureteroscopic approach with holmium laser stent cutting removed the stent in 98%, and laser transection was useful in 71%; mean operating time was 110 minutes and 10% had nonobstructive pyelonephritis.[31] In 58 patients with encrusted stents (indwelling under 6 months in 22%, 6–12 months in 57%, over 12 months in 21%), all stents were removed. Ureteroscopy was used in 90%, and 10% needed second-stage PCNL or combined intrarenal surgery; the stone-free rate was 84% at 1 month and complications occurred in 10.5%.[32]
Metallic, Biodegradable and Drug-Eluting Stents
Metallic stents were developed for malignant ureteral obstruction, where polymeric stents can fail from extrinsic compression. Device-specific detail is in Metal & Long-Term Stents.
- Resonance. In 50 ureteral units in 42 patients with malignant obstruction after polymeric stent failure, the Resonance stent had a mean 4-month longer functional duration (p < 0.0001), and hydronephrosis resolved or was stable in 90%.[35] In a single-center chronic-obstruction cohort, metal stents stayed in longer (228.6 vs 146.1 days) and needed fewer changes per year (1.4 vs 6.3), with no significant cost-per-day difference.[37] In a 23-patient series with yearly exchange, all 3 failures occurred in 2 patients with malignant obstruction, and the authors limited their conclusion to patients without urolithiasis.[38]
- Covered metallic stent. In a randomized comparison of 10 covered metallic and 12 double-J ureters for malignant obstruction, median patency was 239 versus 80 days (overall patency p = 0.041). The trial was very small.[36]
- Biodegradable stents. Biodegradable designs aim to degrade in situ and avoid retrieval. Materials under study include PLGA, PCL, PLA and PDO. Degradation timing, mechanical strength and transient obstruction from degradation products remain limitations, and clinical data are limited. A modified biodegradable mesh stent has been described in animal models.[41][40]
- Surface-modified and drug-eluting stents. Hydrophilic coatings aim to reduce friction, and antibacterial and anti-encrustation coatings aim to reduce biofilm.[46] In a randomized trial of 20 patients, a triclosan-eluting stent reduced flank, abdominal and urethral pain scores but had no significant effect on culture, biofilm or encrustation in short-term stenting.[42] Antibacterial coatings (a propolis-derived coating eliminated more than 90% of attached biofilm in vitro and reduced infection and encrustation in an animal model), rapamycin-eluting and dual-drug silk fibroin/PDO stents remain preclinical.[43][44][45]
Reconstructive Use
In reconstruction the stent acts as an intraoperative scaffold.
| Setting | Commonly used dwell |
|---|---|
| Ureteroneocystostomy, Boari flap, psoas hitch | About 4–6 weeks |
| Pyeloplasty | About 4–6 weeks in common practice; in one 82-patient randomized series of primary minimally invasive repairs, 2 versus 6 weeks yielded unobstructed drainage in 29/30 versus 30/31 imaged patients at 24 months.[58] |
| Buccal mucosa graft ureteroplasty, appendiceal interposition | About 6–8 weeks or longer |
| Kidney transplant anastomosis | Day-5 removal was tested in one RCT.[12] A 2026 scoping review of 55 studies associated removal at 14–21 days with fewer UTIs without more major urological complications.[56] |
After ureteral injury during pelvic, colorectal or gynecologic surgery, see the EAU trauma guideline.[6]
References
1. Sali GM, Joshi HB. "Ureteric stents: overview of current clinical applications and economic implications." Int J Urol. 2020;27(1):7–15. doi:10.1111/iju.14119
2. Ryan AG, Irvine I, Bardgett H, et al. CIRSE Standards of Practice on Nephrostomy and Ureteric Stent Placement and Exchange. Cardiovasc Intervent Radiol. 2026;49:464–479. doi:10.1007/s00270-025-04328-9
3. Cook Medical. Resonance Metallic Ureteral Stent Set: Instructions for Use, IFU0020-18. English pages 3–5; version linked from the US product page.
4. Linder BJ, Occhino JA. "Cystoscopic ureteral stent placement: techniques and tips." Int Urogynecol J. 2019;30(1):163–5. doi:10.1007/s00192-018-3762-8
5. European Association of Urology. EAU Guidelines on Urolithiasis, 2026 (limited update, March 2026). Sections 3.4.2 (sepsis and obstructed kidney), 3.4.3 (MET) and 3.4.6 (stenting before and after URS, summary 3.4.6.a).
6. Waterloos M, Campos-Juanatey F, Hallscheidt P, et al. EAU Guidelines on Urological Trauma. Limited update, March 2026. Sections 4.2.3–4.2.4 (ureteral trauma: prevention and management).
7. Patterson LG, Tingle SJ, Rix DA, et al. Routine intraoperative ureteric stenting for kidney transplant recipients. Cochrane Database Syst Rev. 2024;7:CD004925. doi:10.1002/14651858.CD004925.pub4
8. Ghani KR, Olumolade OO, Daignault-Newton S, et al. What Is the Optimal Stenting Duration After Ureteroscopy and Stone Intervention? Impact of Dwell Time on Postoperative Emergency Department Visits. The Journal of Urology. 2023;210(3):472-480. doi:10.1097/JU.0000000000003555
9. Heidenberg DJ, Nauheim J, Grant C, et al. Timing of Ureteral Stent Removal After Ureteroscopy on Stent-Related Symptoms: A Validated Questionnaire Comparison of 3 and 7 Days Stent Duration. Journal of Endourology. 2023. doi:10.1089/end.2023.0189
10. Oudmaijer CAJ, Muller K, van Straalen E, et al. Long-Term Double-J Stenting Is Superior to Short-Term Single-J Stenting in Kidney Transplantation. PLoS One. 2025;20(1):e0317991. doi:10.1371/journal.pone.0317991
11. Yin S, Hao X, Cai X, et al. Do Ureteral Stents Improve Clinical Outcomes in Renal Transplantation? A Systematic Review and Meta-Analysis. PeerJ. 2026;14:e20665. doi:10.7717/peerj.20665
12. Patel P, Rebollo-Mesa I, Ryan E, et al. Prophylactic Ureteric Stents in Renal Transplant Recipients: A Multicenter Randomized Controlled Trial of Early Versus Late Removal. American Journal of Transplantation. 2017;17(8):2129-2138. doi:10.1111/ajt.14223
13. Nicolle LE, Gupta K, Bradley SF, et al. Clinical Practice Guideline for the Management of Asymptomatic Bacteriuria: 2019 Update by IDSA. Clin Infect Dis. 2019;68:e83–e110. doi:10.1093/cid/ciy1121
14. Finney RP. Experience With New Double J Ureteral Catheter Stent. The Journal of Urology. 1978;120(6):678-681. doi:10.1016/s0022-5347(17)57326-7
15. Donahue RP, Stamm AW, Gibbons RP, et al. Evolution of the Ureteral Stent: The Pivotal Role of the Gibbons Ureteral Catheter. Urology. 2018;115:3-7. doi:10.1016/j.urology.2018.02.007
16. Andriole GL, Bettmann MA, Garnick MB, Richie JP. Indwelling Double-J Ureteral Stents for Temporary and Permanent Urinary Drainage: Experience With 87 Patients. The Journal of Urology. 1984;131(2):239-241. doi:10.1016/s0022-5347(17)50324-9
17. Nestler S, Witte B, Schilchegger L, Jones J. Size Does Matter: Ureteral Stents With a Smaller Diameter Show Advantages Regarding Urinary Symptoms, Pain Levels and General Health. World Journal of Urology. 2020;38(4):1059-1063. doi:10.1007/s00345-019-02829-0
18. Pilcher JM, Patel U. Choosing the Correct Length of Ureteric Stent: A Formula Based on the Patient's Height Compared With Direct Ureteric Measurement. Clinical Radiology. 2002;57(1):59-62. doi:10.1053/crad.2001.0737
19. Barrett K, Foell K, Lantz A, et al. Best Stent Length Predicted by Simple CT Measurement Rather Than Patient Height. Journal of Endourology. 2016;30(9):1029-1032. doi:10.1089/end.2016.0105
20. Bosio A, Alessandria E, Dalmasso E, et al. How Bothersome Double-J Ureteral Stents Are After Semirigid and Flexible Ureteroscopy: A Prospective Single-Institution Observational Study. World Journal of Urology. 2019;37(1):201-207. doi:10.1007/s00345-018-2376-6
21. Koprowski C, Kim C, Modi PK, Elsamra SE. Ureteral Stent-Associated Pain: A Review. Journal of Endourology. 2016;30(7):744-753. doi:10.1089/end.2016.0129
22. Hinojosa-Gonzalez DE, Segall MR, Eisner BH. Pharmacological Management of Ureteral Stent-Related Symptoms: A Systematic Review, Bayesian Network Meta-Analysis, and Meta-Regression. The Journal of Urology. 2023;210(5):739-749. doi:10.1097/JU.0000000000003616
23. Lamb AD, Vowler SL, Johnston R, Dunn N, Wiseman OJ. Meta-Analysis Showing the Beneficial Effect of α-Blockers on Ureteric Stent Discomfort. BJU International. 2011;108(11):1894-1902. doi:10.1111/j.1464-410X.2011.10170.x
24. Pricop C, Bandac CA, Ivanuță M, et al. Comparative Approaches in Treating Double-J Stent Syndrome: Monotherapy or Combination Therapy? Journal of Clinical Medicine. 2024;13(14):4278. doi:10.3390/jcm13144278
25. Katsimperis S, Manolitsis I, Lazarou L, et al. Clinical and Procedural Factors Influencing Ureteral Stent Dwell Time and Removal Methods After Endourological Procedures: A Systematic Review. World Journal of Urology. 2026;44(1):337. doi:10.1007/s00345-026-06436-8
26. Legrand F, Saussez T, Ruffion A, et al. Double Loop Ureteral Stent Encrustation According to Indwelling Time: Results of a European Multicentric Study. Journal of Endourology. 2021;35(1):84-90. doi:10.1089/end.2020.0254
27. Maxim LS, Rotaru RM, Scarneciu CC, et al. The Impact of Ureteral Stent Indwelling Duration on Encrustation Degree and Extraction Difficulty: A Retrospective Study. Journal of Clinical Medicine. 2025;14(12):4334. doi:10.3390/jcm14124334
28. Harrison NL, Hughes C, Somani BK. Is Stent on a String the New Gold Standard for Postureteroscopy Ureteral Drainage? Evidence From a Systematic Review. Journal of Endourology. 2024;38(2):159-169. doi:10.1089/end.2023.0412
29. Liu J, Cundy TP, Parker N, et al. Implementing Routine Use of Self-Removed Ureteric Stents on Extraction Strings: Prospective Patient-Reported Outcome Measures and Complications. World Journal of Urology. 2023;41(12):3759-3764. doi:10.1007/s00345-023-04653-z
30. Inoue T, Okada S, Hamamoto S, et al. Impact of Ureteric Stent Removal by String on Patient's Quality of Life and on Complications at Post-Ureteroscopy for Urolithiasis: A Controlled Trial. BJU International. 2019;124(2):314-320. doi:10.1111/bju.14622
31. Thomas A, Cloutier J, Villa L, et al. Prospective Analysis of a Complete Retrograde Ureteroscopic Technique With Holmium Laser Stent Cutting for Management of Encrusted Ureteral Stents. Journal of Endourology. 2017;31(5):476-481. doi:10.1089/end.2016.0816
32. Tsaturyan A, Faria-Costa G, Peteinaris A, et al. Endoscopic Management of Encrusted Ureteral Stents: Outcomes and Tips and Tricks. World Journal of Urology. 2023;41(5):1415-1421. doi:10.1007/s00345-023-04361-8
33. Tomer N, Garden E, Small A, Palese M. Ureteral Stent Encrustation: Epidemiology, Pathophysiology, Management and Current Technology. The Journal of Urology. 2021;205(1):68-77. doi:10.1097/JU.0000000000001343
34. Zhang F, Yu J, Wang Q, Lu Y. Urinary Bladder Stone Due to Retained Indwelling Ureteral Stent: A Case Report. Medicine. 2020;99(39):e22293. doi:10.1097/MD.0000000000022293
35. Chow PM, Chiang IN, Chen CY, et al. Malignant Ureteral Obstruction: Functional Duration of Metallic Versus Polymeric Ureteral Stents. PLoS One. 2015;10(8):e0135566. doi:10.1371/journal.pone.0135566
36. Kim JW, Hong B, Shin JH, et al. A Prospective Randomized Comparison of a Covered Metallic Ureteral Stent and a Double-J Stent for Malignant Ureteral Obstruction. Korean Journal of Radiology. 2018;19(4):606-612. doi:10.3348/kjr.2018.19.4.606
37. Law YXT, Zhou A, Consigliere DT, Goh BYS, Tiong HY. Use of Metallic Ureteric Stents for Chronic Ureteric Obstruction and Its Association With Value-Based Care. Singapore Medical Journal. 2025;66(1):28-32. doi:10.4103/singaporemedj.SMJ-2021-418
38. Benson AD, Taylor ER, Schwartz BF. Metal Ureteral Stent for Benign and Malignant Ureteral Obstruction. The Journal of Urology. 2011;185(6):2217-2222. doi:10.1016/j.juro.2011.02.008
39. Amara D, Melehy A, Parekh J, et al. Prophylactic Ureteral Stenting in Kidney Transplantation: A Multivariable and Propensity Score-Matched Analysis of 3407 Recipients From NSQIP Transplant. Transplantation. 2026;110(5):e1100-e1111. doi:10.1097/TP.0000000000005660
40. Wang Y, Ren X, Ji C, et al. A Modified Biodegradable Mesh Ureteral Stent for Treating Ureteral Stricture Disease. Acta Biomaterialia. 2023;155:347-358. doi:10.1016/j.actbio.2022.11.022
41. Hu K, Hou Z, Huang Y, et al. Recent Development and Future Application of Biodegradable Ureteral Stents. Frontiers in Bioengineering and Biotechnology. 2024;12:1373130. doi:10.3389/fbioe.2024.1373130
42. Mendez-Probst CE, Goneau LW, MacDonald KW, et al. The Use of Triclosan Eluting Stents Effectively Reduces Ureteral Stent Symptoms: A Prospective Randomized Trial. BJU International. 2012;110(5):749-754. doi:10.1111/j.1464-410X.2011.10903.x
43. Zhao Y, Chen G, Yushanjiang S, et al. In Vitro and In Vivo Study of Antibacterial and Anti-Encrustation Coating on Ureteric Stents. BJU International. 2024;134(1):72-80. doi:10.1111/bju.16326
44. Hu J, Wang Z, Hu H, et al. In Vitro and In Vivo Assessment of a Bilayered Degradable Rapamycin-Eluting Stent for Ureteral Stricture Caused by Holmium:YAG Laser Lithotripsy. Acta Biomaterialia. 2023;172:321-329. doi:10.1016/j.actbio.2023.10.009
45. Duan L, Wang J, Miao Z, et al. Silk Fibroin/Dual Drugs Eluting Polydioxanone Monofilament Braided Ureteral Stent With Antibacterial and Anti-Stenotic Functions. International Journal of Biological Macromolecules. 2025;319:145304. doi:10.1016/j.ijbiomac.2025.145304
46. Xia K, Shen X, Ang X, et al. Surface Modification of Ureteral Stents: Development History, Classification, Function, and Future Developments. Expert Review of Medical Devices. 2023;20(5):401-416. doi:10.1080/17434440.2023.2198702
47. Lange D, Bidnur S, Hoag N, Chew BH. Ureteral Stent-Associated Complications: Where We Are and Where We Are Going. Nature Reviews Urology. 2015;12(1):17-25. doi:10.1038/nrurol.2014.340
48. Pais VM, Smith RE, Stedina EA, Rissman CM. Does Omission of Ureteral Stents Increase Risk of Unplanned Return Visit? A Systematic Review and Meta-Analysis. The Journal of Urology. 2016;196(5):1458-1466. doi:10.1016/j.juro.2016.05.109
49. Ordonez M, Hwang EC, Borofsky M, et al. Ureteral Stent Versus No Ureteral Stent for Ureteroscopy in the Management of Renal and Ureteral Calculi. Cochrane Database of Systematic Reviews. 2019;2:CD012703. doi:10.1002/14651858.CD012703.pub2
50. Forzini T, Demouron M, Uhl M, et al. Computed Tomography Evaluation of Ureteral Length in Children. Journal of Pediatric Urology. 2019;15(5):555.e1-555.e5. doi:10.1016/j.jpurol.2019.06.011
51. Oh CH, Cho SB, Lee HJ, Kwon H, Hwang YG. "Migration of double-J ureteral stent in patients with ureteroileal anastomosis stricture undergoing radical cystectomy and orthotopic neobladder: analysis risk factors of stent migration." Medicine (Baltimore). 2024;103(16):e37765. doi:10.1097/MD.0000000000037765
52. Kamphorst K, Lock TMTW, van den Bergh RCN, et al. "Arterio-ureteral fistula: systematic review of 445 patients." J Urol. 2022;207(1):35–43. doi:10.1097/JU.0000000000002241
53. Alembic Pharmaceuticals Inc. Silodosin capsules: US prescribing information. DailyMed; revised July 2021. Label.
54. HEC Pharm USA Inc. Solifenacin succinate tablets: US prescribing information. DailyMed; updated July 2026. Label.
55. Putrantyo II, Warli SM, Siregar GP, Prapiska FF, Kadar DD, Sihombing B. "Role of ureteral stent material and coating to prevent ureteral stent related issue: A systematic review and meta analysis." Arch Ital Urol Androl. 2024;96(1):12067. doi:10.4081/aiua.2024.12067
56. Chow KM, Lau RSE, Ong JHW, et al. "An evidence-based review by the EAU Endourology on standard practices and future directions for ureteral stents in transplant patients." World J Urol. 2026;44(1):290. doi:10.1007/s00345-026-06400-6
57. Madarshahian D, Habeeb A, Chandra-Segaran N, et al. "Ureteral stent symptoms: a systematic review and meta-analysis comparing the use of mirabegron and tamsulosin." BJUI Compass. 2025;6(9):e2485. doi:10.1002/bco2.485
58. Birkhäuser FD, von Rütte T, Moltzahn F, Huber P, Zehnder P. "A short double-J ureteral stent indwelling time is safe and effective following minimally invasive pyeloplasty: long-term results from a prospective randomized controlled trial." Eur Urol Open Sci. 2025;74:28–33. doi:10.1016/j.euros.2025.01.014