Percutaneous Nephrostomy (PCN)
A percutaneous nephrostomy (PCN) drains the renal collecting system through a catheter placed under image guidance through the flank and renal parenchyma. It provides decompression, access for subsequent intervention or diversion from a urinary leak. For obstructed renal tracts, the CIRSE review reports PCN technical success of 82%–99%.[1] It is distinct from a PCNU, which also traverses the ureter, and an internal double-J stent.[1][2][10]
Choosing Drainage
Sepsis with an obstructing stone requires urgent decompression and immediate antibiotics. EAU 2026 gives a Strong recommendation for urgent decompression by either PCN or ureteral stenting in sepsis with an obstructing stone; choose according to anatomy, clinical stability, access and available expertise. Definitive stone treatment waits until sepsis is controlled. Resuscitation and correction of dangerous electrolyte or coagulation abnormalities proceed alongside the drainage plan rather than creating an automatic delay.[1][3]
Other uses include benign or malignant obstruction, ureteral injury or leak (diversion away from the injury), antegrade pyelography, and access for antegrade stenting, balloon dilation of strictures or endourology.[8][10] There is no absolute contraindication when drainage is urgent. Severe coagulopathy and thrombocytopenia are reversed before PCN and, if uncorrectable, favor retrograde stenting when feasible. Hyperkalemia (potassium > 6 mEq/L) or acidemia (pH < 7.2) prompts nephrology management to reduce the risk of intraprocedural arrhythmia. Terminal illness in which drainage would not change the outcome is a relative concern.[1][9] In advanced malignancy, discuss symptom relief, renal recovery, possible cancer treatment, tube burden and the patient's goals.[1][2]
A 2024 review of 18 comparative studies and 1,228 patients with malignant obstruction found less procedure or intervention failure with PCN, but less displacement, shorter procedure time and shorter stay with retrograde stents. Studies of antegrade versus retrograde stent placement answer a different question from PCN versus stent drainage.[4]
| Setting | Finding |
|---|---|
| Malignant obstruction, meta-analysis of 18 studies (1,228 patients) | PCN had lower procedure and intervention failure rates; retrograde stenting had less displacement, shorter procedure time and shorter stay. Infection, blockage and unplanned exchange rates did not differ.[4] |
| Malignant obstruction, antegrade versus retrograde stent placement (retrospective, 61 antegrade and 76 retrograde placements) | Technical success 98.4% antegrade and 47.4% retrograde. Retrograde failure was associated with age of 65 years or more, ureteral orifice invasion and extrinsic cancer.[16] |
| Acute obstructive uropathy, meta-analysis of 7 trials (667 patients) | No difference in septic parameters, quality of life, failure rates, pain or analgesic use. PCN was associated with less hematuria and dysuria and a longer hospital stay.[17] |
| Obstructive urolithiasis, STONE trial (204 randomized) | PCN was noninferior to an internal stent for time to clinical recovery (mean 1.7 versus 1.5 days; 1-day noninferiority margin). Fourteen assigned to PCN crossed to stenting, 11 after technical failure, versus four reverse crossovers. A secondary as-treated analysis found no statistically significant between-group difference in overall quality of life or mean daily pain; PCN recipients reported more self-care difficulty, whereas stent recipients reported more urinary symptoms and higher peak pain. The follow-up email-survey response rate was 59%.[21][22] |
| Malignant obstruction, quality of life (74 PCN, 30 tandem stents) | Similar quality-of-life and tube-symptom scores. Of 13 patients who had used both, 11 preferred tandem ureteral stents.[18] |
A PCN has a larger bore than a stent, which helps drain pus or debris, allows exchange, irrigation and nephrostogram, and needs no cystoscopy, so it can be placed in a septic or bed-bound patient.
Planning and Safe Access
| Check | Purpose |
|---|---|
| Imaging and route | Review collecting-system anatomy, kidney position, intervening bowel, pleura and vessels; altered anatomy or a nondilated system may require a different imaging approach. |
| Bleeding risk | Check blood count, coagulation and antithrombotics; agree correction/interruption with the procedural team, balancing urgency and thrombosis risk. |
| Infection | Obtain relevant blood and urine cultures and collect urine from the renal pelvis during PCN for culture when treating infected obstruction; procedural prophylaxis is a separate decision.[1][3] |
| Catheter and future plan | Choose caliber, retention mechanism and calyceal access for drainage contents and possible later antegrade intervention. |
Use image-guided access through an appropriate calyx and verify intraluminal wire and catheter position. Posterior calyceal access is intended to reduce vascular injury; the exact calyx and angle are adapted to the kidney and the planned intervention (see Technique). Supracostal access has pleural risks. In an infected system, avoid unnecessary manipulation and pressurized distension.[1]
Drug choice depends on local susceptibility, prior cultures, allergy and renal function. Ceftriaxone lacks reliable Enterococcus coverage. Use the UTI antibiotic, perioperative prophylaxis and antithrombotic workflow companions for agent and interruption decisions.[5]
Technique
Ultrasound guidance for initial access is combined with fluoroscopy for wire and catheter manipulation.[8][10]
- Position. The patient may be positioned prone, prone-oblique or decubitus; obstructed transplant kidneys are accessed supine.[1]
- Entry site. Entry is ideally subcostal (below the 12th rib when feasible, and not above the 11th rib unless other routes are exhausted) and lateral to the paraspinous muscles.[8][9]
- Calyx. A posterior calyx is punctured through the relatively avascular zone between the anterior and posterior renal arterial territories (Brödel's line), at a 20° to 30° posterolateral oblique angle, with a single-wall puncture of the calyx.[8][9] If antegrade stenting is anticipated, consider an interpolar calyx because lower-pole access can make crossing a tight stricture more difficult.[1]
- Seldinger sequence. A needle, a guidewire coiled in the renal pelvis, serial dilation and a self-retaining catheter are used. Contrast placed over the wire can confirm intracollecting-system position when pus or known infection is absent; avoid contrast injection into a pus-filled or known infected collecting system.[1] A safety wire is recommended for complex manipulations so that access to an obstructed kidney is not lost.[8][9]
- Nondilated systems. Access is more demanding. CIRSE 2026 recommends direct calyceal puncture rather than a two-puncture (renal pelvis first, then calyceal) technique and, for nondilated kidneys, initial ultrasound guidance aimed at the central apex of a mid- or lower-pole renal pyramid with Doppler to avoid vessels; it reports technical success of 82% to 96%.[1] A double-puncture technique with intravenous contrast and air or carbon dioxide distension achieved catheter placement in 25 of 26 nondilated kidneys in a 15-patient retrospective series. Two major complications occurred among the 25 treated kidneys (8%): one transfusion and one renal pelvic injury thought to result from excessive dilation of the pelviureteral junction rather than faulty puncture.[11]
- Infected system. Avoid overdistension and unnecessary prolonged manipulation.[9]
Supracostal access reaches upper-pole calyces but carries pleural risk, including pneumothorax and nephropleural fistula.
Reported technical success.
| System | Success | Source |
|---|---|---|
| Dilated system | 96.4% primary (389 total procedures); 98.2% primary (500 total procedures) | [13][12] |
| Nondilated system | 82.7% and 82% primary success in the same two series; 96% with the double-puncture technique (25/26 kidneys) | [13][12][11] |
| All comers | 94.6% primary (389 procedures); 97% (765 PCNs by urologists); more than 90% in a review | [13][14][10] |
Complications That Change Management
- Obstruction, kinking or displacement. New low output, flank pain, fever, pericatheter leakage or rising creatinine warrants urgent tube assessment. CIRSE 2026 advises exchange within 24 hours when symptoms suggest obstruction or malposition. Do not assume leakage means the tube drains adequately.[1]
- Infection or sepsis. Assess the patient and tube function, culture appropriately, begin treatment and arrange source control when needed.
- Bleeding. Mild early hematuria can occur. Persistent, recurrent or heavy bleeding, hemodynamic change or falling hemoglobin warrants investigation for vascular injury; selective embolization may be needed. Balloon tamponade of the tract can temporize active bleeding.[9]
- Bowel or pleural injury. Obtain urgent specialist assessment and imaging. Catheter removal, repositioning or retention depends on the injury and drainage needs; blind withdrawal is not a universal solution. Dyer et al. describe a transcolonic PCN injury managed by withdrawing the nephrostomy over a wire into the colon and placing an internal double-J stent for urinary drainage. They used broad-spectrum antibiotics, left the tube for 10–14 days to allow the colonic tract to epithelialize, and repeated CT before removal to check for retroperitoneal infection.[8]
- Dislodgement. Contact the drainage service urgently. Tract age and anatomy determine whether image-guided recannulation is possible; a fixed “7–10 days means mature” rule is unsafe.[1][6]
Published complication frequencies vary with indication and population. A review reports about 10% major and minor complications together and 4% to 5% major complications.[10] Individual series report major complications in 0.45% (Montvilas et al.; 500 PCNs in 353 patients), 3.89% (26/667 patients in Rana et al.) and 9.6% (Degirmenci et al.; 389 insertions in 322 patients, with more in nondilated systems), and minor complications in 9.1% to 14.2%.[12][14][13]
Dislodgement is the commonest long-term problem. In 147 patients with malignant obstruction and long-term PCN (229 renal units), the tube was replaced for dislodgement in 76% of renal units and pyelonephritis occurred at least once in 41.5% of patients. Follow-up time, BMI, diabetes, chemotherapy and catheter-related skin infection were associated with complications.[15]
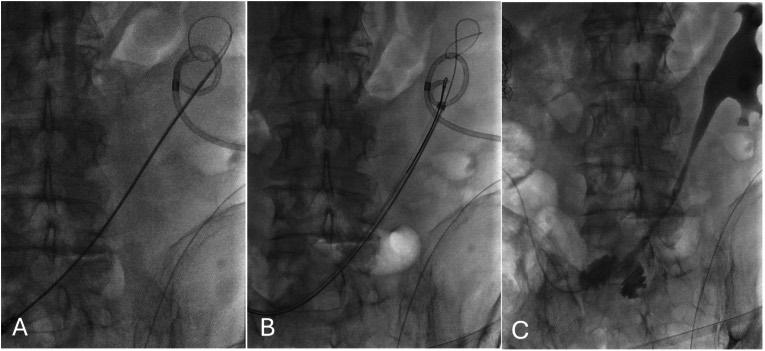
Retrograde removal of a fragmented, retained pigtail nephrostomy tube through an ileal conduit. (A) The fragment lies coiled in the left kidney; a 5 Fr open-ended ureteral catheter has been advanced through the conduit into the renal pelvis. (B) Over a guidewire a 12 Fr sheath is placed in the proximal ureter and a loop snare grasps the retained tube. (C) Retrograde pyelography after removal shows no extravasation from the renal pelvis, ureteral anastomosis or conduit. From Awad A, et al. Urol Case Rep. 2025;62:103176, Fig. 1 (CC BY-NC 4.0).[20]
Ongoing Care and Exchange
Secure the catheter without traction, keep the prescribed drainage arrangement functioning, and teach the patient to recognize leakage, reduced output, fever and displacement. Monitor fluid balance after relief of obstruction because post-obstructive diuresis may require replacement and electrolyte monitoring. Flushing should follow the prescribed device or service plan; resistance or pain should prompt reassessment rather than force.[1][6]
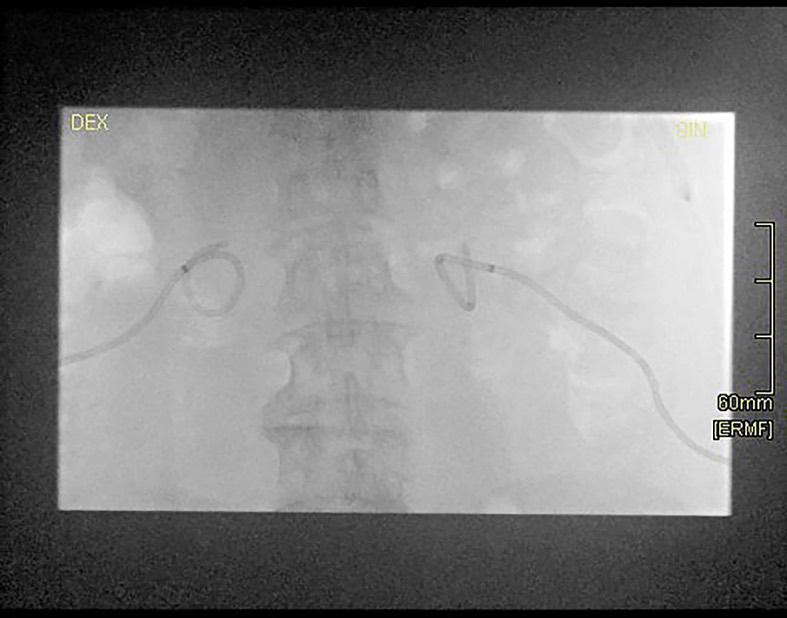
Bilateral loop percutaneous nephrostomy catheters with strings on fluoroscopy 6 months after placement. Both loops remain correctly positioned, although the single skin suture on the right side was no longer fixing the catheter. From Kuhelj D, et al. Radiol Oncol. 2025;59(4):522-525, Figure 2 (CC BY 4.0).[19]
Set an individualized exchange date. CIRSE 2026 describes an initial 6–8-week interval, extendable to 8–12 weeks if encrustation is not a problem; some patients need earlier changes. In pregnancy, CIRSE 2026 advises PCN exchange every 4–6 weeks, especially in stone formers, because encrustation risk is increased.[1] Product instructions, catheter performance and clinical circumstances take precedence over a universal 3-month rule. Exchange does not sterilize a chronically colonized urinary tract.[1][3]
Asymptomatic bacteriuria is common and does not usually require antibiotics solely because a tube is present. Pregnancy and planned endourologic procedures involving mucosal trauma are important exceptions to a blanket “never treat” statement; device manipulation also requires its own procedural assessment.[6][7]
A PCN may be temporarily capped in a planned trial when internal drainage is being assessed, including after ureteral stent placement. Give explicit instructions about symptoms that require reconnecting drainage and contacting the team. Removal requires evidence that drainage or diversion is no longer needed; a cap trial alone does not prove native ureteral healing. Release the catheter's locking mechanism before removal; if a ureteral stent remains in place, CIRSE advises PCN removal over a wire under fluoroscopic guidance.[1]
Special Situations
- Pregnancy. Coordinate obstetric and urologic care and minimize radiation. Both PCN and stenting remain drainage options; ureteroscopy is another option in selected patients.[3]
- Children. Use age-appropriate equipment and pediatric expertise.[1]
- Long-term PCN in cancer patients. Dislodgement, obstruction and pyelonephritis are frequent (see above), so plan tube changes and teach the patient to recognize failure.[15]
- Suspected upper-tract urothelial malignancy. Include the tumor and access route in drainage planning; urgent decompression and subsequent oncologic management require coordinated decisions.[1]
See also Nephropleural Fistula and Renal Anatomy.
References
1. Ryan AG, Irvine I, Bardgett H, et al. CIRSE Standards of Practice on Nephrostomy and Ureteric Stent Placement and Exchange. Cardiovasc Intervent Radiol. 2026;49:464–479. doi:10.1007/s00270-025-04328-9
2. Scheidt MJ, Hohenwalter EJ, Pinchot JW, et al. ACR Appropriateness Criteria® Radiologic Management of Urinary Tract Obstruction. Journal of the American College of Radiology. 2020;17(5S):S281-S292. doi:10.1016/j.jacr.2020.01.039
3. European Association of Urology. EAU Guidelines on Urolithiasis, 2026. Sections on sepsis, ureteroscopy, stenting and pregnancy.
4. Ahmad MU, Siddiqui S, Ashraf FA, et al. Retrograde Ureteral Stents Versus Percutaneous Nephrostomy in the Management of Malignant Ureteral Obstruction: A Systematic Review and Meta-Analysis. Urology. 2024;192:158-167. doi:10.1016/j.urology.2024.05.042
5. Baxter Healthcare. Ceftriaxone injection: prescribing information. Microbiology section, updated October 7, 2024. DailyMed.
6. Yoo MJ, Bridwell RE, Inman BL, Henderson JD, Long B. Approach to Nephrostomy Tubes in the Emergency Department. The American Journal of Emergency Medicine. 2021;50:592-596. doi:10.1016/j.ajem.2021.09.034
7. Nicolle LE, Gupta K, Bradley SF, et al. Clinical Practice Guideline for the Management of Asymptomatic Bacteriuria: 2019 Update by IDSA. Clin Infect Dis. 2019;68:e83–e110. doi:10.1093/cid/ciy1121
8. Dyer RB, Regan JD, Kavanagh PV, et al. Percutaneous Nephrostomy With Extensions of the Technique: Step by Step. RadioGraphics. 2002;22(3):503-525. doi:10.1148/radiographics.22.3.g02ma19503
9. Zagoria RJ, Dyer RB. Do's and Don't's of Percutaneous Nephrostomy. Academic Radiology. 1999;6(6):370-377. doi:10.1016/s1076-6332(99)80233-5
10. Hausegger KA, Portugaller HR. Percutaneous Nephrostomy and Antegrade Ureteral Stenting: Technique, Indications, Complications. European Radiology. 2006;16(9):2016-2030. doi:10.1007/s00330-005-0136-7
11. Patel U, Hussain FF. Percutaneous Nephrostomy of Nondilated Renal Collecting Systems With Fluoroscopic Guidance: Technique and Results. Radiology. 2004;233(1):226-233. doi:10.1148/radiol.2331031342
12. Montvilas P, Solvig J, Johansen TE. Single-Centre Review of Radiologically Guided Percutaneous Nephrostomy Using "Mixed" Technique: Success and Complication Rates. European Journal of Radiology. 2011;80(2):553-558. doi:10.1016/j.ejrad.2011.01.109
13. Degirmenci T, Gunlusoy B, Kozacioglu Z, et al. Utilization of a Modified Clavien Classification System in Reporting Complications After Ultrasound-Guided Percutaneous Nephrostomy Tube Placement. Urology. 2013;81(6):1161-1167. doi:10.1016/j.urology.2013.02.038
14. Rana AM, Zaidi Z, El-Khalid S. Single-Center Review of Fluoroscopy-Guided Percutaneous Nephrostomy Performed by Urologic Surgeons. Journal of Endourology. 2007;21(7):688-691. doi:10.1089/end.2006.0281
15. Alma E, Ercil H, Vuruskan E, et al. Long-Term Follow-Up Results and Complications in Cancer Patients With Persistent Nephrostomy Due to Malignant Ureteral Obstruction. Supportive Care in Cancer. 2020;28(11):5581-5588. doi:10.1007/s00520-020-05662-z
16. Kim HJ, Yoon CJ, Lee S, et al. Comparison Between Antegrade Versus Retrograde Ureteral Stent Placement for Malignant Ureteral Obstruction. Journal of Vascular and Interventional Radiology. 2022;33(10):1199-1206. doi:10.1016/j.jvir.2022.06.024
17. Zul Khairul Azwadi I, Norhayati MN, Abdullah MS. Percutaneous Nephrostomy Versus Retrograde Ureteral Stenting for Acute Upper Obstructive Uropathy: A Systematic Review and Meta-Analysis. Scientific Reports. 2021;11(1):6613. doi:10.1038/s41598-021-86136-y
18. Shvero A, Haifler M, Mahmud H, et al. Quality of Life With Tandem Ureteral Stents Compared to Percutaneous Nephrostomy for Malignant Ureteral Obstruction. Supportive Care in Cancer. 2022;30(11):9541-9548. doi:10.1007/s00520-022-07354-2
19. Kuhelj D, Sustersic A, Zdesar U. The Influence of Catheter Type, the Number of Sutures and Patients' Age on Percutaneous Nephrostomy Displacement. Radiology and Oncology. 2025;59(4):522-525. doi:10.2478/raon-2025-0037
20. Awad A, Ahrar J, Abdelsalam ME. Cystoscope Assisted Trans-Conduit Removal of Fragmented Percutaneous Nephrostomy Catheter. Urology Case Reports. 2025;62:103176. doi:10.1016/j.eucr.2025.103176
21. Hendriks N, Schuil HW, Duijnhoven RG, et al. "The STent Or NEphrostomy Study: A Randomised Controlled Trial Evaluating the Effectiveness of Percutaneous Nephrostomy Versus Internal Stent in Patient with Urolithiasis and an Indication for Decompression." Eur Urol Focus. Published online December 11, 2025. doi:10.1016/j.euf.2025.10.012
22. Schuil HW, Hendriks N, Duijnhoven RG, et al. "Patient-reported outcome measures of percutaneous nephrostomy vs JJ stent in obstructive urolithiasis: results of the STent Or NEphrostomy (STONE) randomised controlled trial." BJU Int. 2026;137(6):1088-1096. doi:10.1111/bju.70249