Council Tip Catheter
A Council-tip catheter (spelled "Councill-tip" in older literature) is an indwelling balloon catheter with an open end-hole at the tip. The end-hole allows it to be threaded over a guidewire already positioned in the bladder, in a Seldinger-style sequence. It is used when ordinary catheter passage is difficult or a controlled wire-guided placement is planned, for example in post-radiation, post-prostatectomy and post-reconstruction outlet problems. The end-hole does not make a blind wire safe or guarantee that the catheter has followed the urethral lumen.[1][2]
Design and selection
| Feature | Clinical implication |
|---|---|
| Distal end-hole | Allows true over-wire passage, unlike an unmodified closed-tip Foley. Confirm that the selected wire fits the catheter. |
| Drainage lumen and balloon channel | Retains the indwelling Foley function. Balloon volume, inflation fluid, length, material, and dwell limit remain model-specific. |
| Straight or curved / two- or three-way variants | Check the exact product; "Council-tip" describes wire access rather than one standard size or balloon. A Council-coudé combines a curved tip with an end-hole. |
Choose the smallest catheter that drains adequately and meets the operative need. A guidewire-stiffened closed-tip Foley, such as the Liss maneuver, is different from advancing a catheter over a wire that has already reached the bladder; see Coudé Catheter. General handling and maintenance are covered in Foley Catheter.[1][3]
An end-hole may add a drainage port. In a bench model of manual bladder washout, open-ended catheters needed less force to clear simulated clot than a rounded-tip Foley with standard eyes, which suggests a possible advantage for clot evacuation. This has not been tested in patients.[11]
When wire-guided access helps
Typical situations include a known stricture or outlet stenosis, false passage after prior instrumentation, altered postoperative anatomy, and unsuccessful standard catheterization. Cystoscopy can identify the true lumen and permit wire placement under direct vision. Fluoroscopic urethrography and wire and catheter guidance are alternatives when appropriate expertise is available, including when cystoscopy has failed or is not immediately available.[1][2]
Select the drainage route before repeated attempts. A patient needing urethral rest before reconstruction may benefit from suprapubic drainage. The EAU stricture guideline text states that a suprapubic catheter should be inserted if incapacitating obstructive symptoms or retention develop during urethral rest (narrative text, not a strength-rated recommendation).[4]
Placement principles
This is an access procedure for a trained operator with a plan for failure.[1][2][3]
- Assess the urethra and establish access. Use cystoscopic or fluoroscopic guidance where indicated by difficult anatomy, prior trauma, or failed attempts. Do not force a wire through resistance.
- Confirm the wire's route and intravesical position. Direct visualization or appropriate imaging provides anatomic confirmation. A small open-ended catheter passed over the wire can permit urine drainage or contrast confirmation; urine cannot be aspirated through a solid guidewire.
- Decide whether dilation is appropriate. The ability to pass a wire does not automatically justify dilating a stricture. A smaller catheter or suprapubic drainage may be preferable.
- Advance the compatible catheter over the controlled wire. Maintain wire access and avoid pushing against resistance or buckling. A stiff-wire exchange is not obligatory and can add injury risk if position is lost.
- Establish catheter and balloon position in the bladder before inflation. Urine return alone does not confirm that the balloon is in the bladder. Inflate only with the specified fluid and volume, remove the wire once drainage is secured, and document the access findings and exchange plan.
Wire selection
Bench testing of 0.035-inch wires found that hydrophilic and floppy-tipped wires suit initial access, and stiffer-shaft wires suit coaxial passage of catheters.[5] The Glidewire required the least force to pull through a tortuous path and the most force to puncture aluminum foil, about four times that of the other wires tested. The Amplatz Super Stiff wire resisted bending most. A common approach is to gain access with a hydrophilic wire and then exchange for a stiffer wire before advancing the catheter. In one series, the Glidewire was passed per urethra like a filiform, its intravesical position was confirmed with a ureteral catheter, and it was exchanged for a PTFE-coated wire before dilation or catheter placement.[5][6]
Improvised open-tip catheter
When a true Council-tip device is not available, a shielded IV catheter (18 gauge or larger) can convert a standard closed-tip catheter into one that will pass over a wire, at a fraction of the cost of a dedicated Council-tip device. The IV catheter is advanced through a lateral eyelet and out through the center of the tip, and its needle shield is deployed; the guidewire is then threaded through the IV catheter until several centimeters protrude from the eyelet, the IV catheter is withdrawn while the wire's position is held, and the exposed wire is drawn back through the eyelet into the drainage lumen before the catheter is advanced over the wire.[12]
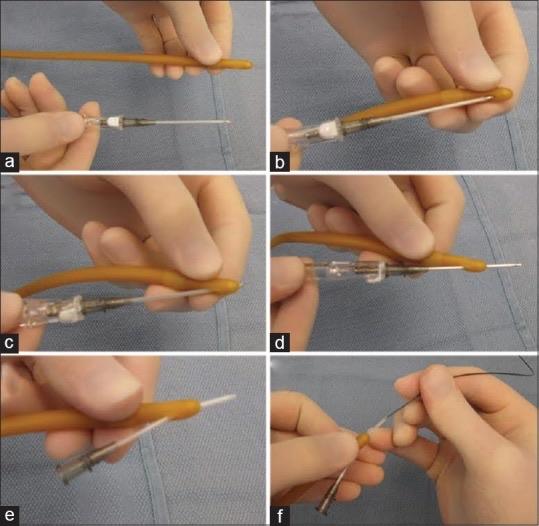
Converting a standard catheter for over-the-wire passage, steps a to f. (a) Any style of catheter and an 18-gauge or larger IV catheter. (b) The IV catheter is passed through the lateral eyelet and (c) advanced through the center of the catheter tip. (d) Both the IV catheter shaft and needle pass through the tip. (e) The push-button needle shield retracts the needle, leaving the IV catheter in place. (f) With the guidewire already placed into the bladder, its proximal end is advanced through the tip of the IV catheter. From Abbott JE, et al. Urol Ann. 2015;7(3):367-370, Figure 2 (CC BY-NC-SA).[12]
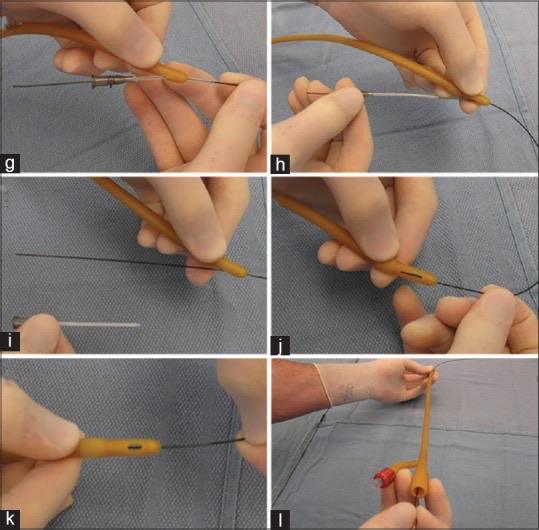
Steps g to l. (g) The guidewire is passed through the full length of the IV catheter, and (h) the IV catheter is removed. (i) The wire is held in position through the catheter tip and out of the lateral eyelet. (j) The wire is withdrawn slowly until it re-enters the lateral eyelet. (k) Keeping the wire within the central tip, it is redirected to advance through the catheter lumen. (l) With the catheter positioned over the wire, the catheter is guided into the bladder. From Abbott JE, et al. Urol Ann. 2015;7(3):367-370, Figure 3 (CC BY-NC-SA).[12]
What the supporting studies establish
| Source | Finding and limitation |
|---|---|
| Beaghler 1994 | Prospective series: cystoscopy, wire-guided dilation where used, and Council-tip drainage succeeded in 52/54 patients, with no reported complications. [1] |
| Kim 2024 | Retrospective series of 179 fluoroscopic catheterizations in 149 men after failed blind or cystoscopy-assisted attempts. Technical and clinical success were reported in all procedures, with four reported complications. The study used catheters with a manually created end-hole, not exclusively commercial Council-tip devices, and had no randomized comparator. [2] |
| Freid 1996 | Glidewire technique (as above) succeeded in 19/20 attempts, several after failed filiform passage, in strictures, bladder-neck contractures and BPH, with no reported complications. The authors recommended it over filiforms and followers when cystourethroscopy is not immediately available. Small uncontrolled series. [6] |
| Clayman 2004 | Bench testing showed substantial differences in wire flexibility, friction and puncture force. A roughly fourfold difference in the force needed to puncture aluminum foil is not a measured fourfold improvement in clinical perforation safety. |
These studies support understanding the technique and the available options.[1][2][5]
Place in the difficult-catheterization sequence
Practice reviews place cystoscopic or wire-guided catheterization after failed blind attempts and any curved-tip (coudé) reattempt, and before suprapubic drainage. An emergency-medicine algorithm adds direct-visualization technology and urology consultation when severe obstruction or perforation is suspected.[10] The Liss report notes that if guidewire stiffening of a Foley fails, the same wire can be used with a flexible endoscope to place a Council catheter.[9] See Coudé Catheter.
Use during radical prostatectomy
A short technical report described a Council-tip catheter placed transurethrally to facilitate placement of urethral sutures during the vesicourethral anastomosis after radical retropubic prostatectomy.[7]
Alternatives and related devices
- Urethral Catheterisation Device (UCD). A commercial device that integrates a hydrophilic nitinol guidewire into a 16 Fr 3-way silicone catheter, intended for second-line catheterization when a standard Foley fails. The published evaluation was in men undergoing cardiac surgery, and its authors propose a male catheterization algorithm.[8]
- Filiforms and followers. The traditional alternative for obstructed urethras; hydrophilic-wire techniques have been proposed as less traumatic.[1][6]
- Suprapubic drainage. See Suprapubic Catheter.
Complications and subsequent exchanges
Wire or catheter passage can cause false passage, perforation, bleeding (including hematuria after stricture dilation), pain, or balloon malposition. Avoid forceful advancement; hydrophilic wires can assist access but do not eliminate false-passage risk. A very tight or near-obliterative stricture can defeat wire passage and point to suprapubic drainage and formal reconstruction. Later blockage, infection, spasm and urethral pressure injury remain possible during prolonged dwell.[2][3] Stop and reassess when passage or position is uncertain.[2][3]
Document whether future exchanges require a wire, cystoscopy or another route, especially after reconstruction. In reconstructive practice this includes post-radiation strictures, bladder-neck contracture, vesicourethral anastomotic stenosis and post-urethroplasty edema. See Bladder Neck Reconstruction, Male Urethral Stricture, and Suprapubic Catheter.
References
1. Beaghler M, Grasso M, Loisides P. Inability to pass a urethral catheter: the bedside role of the flexible cystoscope. Urology. 1994;44(2):268-270. doi:10.1016/s0090-4295(94)80148-7
2. Kim SW, Nam IC, Kim DR, et al. Safety and efficacy of fluoroscopy-guided urethral catheterization in case of failed blind or cystoscopy-assisted urethral catheterization. Sci Rep. 2024;14:9406. doi:10.1038/s41598-024-60224-1
3. European Association of Urology Nurses. Indwelling catheterisation in adults—urethral and suprapubic. 2024.
4. EAU. Urethral strictures guideline. Perioperative care of urethral surgery: urethral rest. 2026.
5. Clayman M, Uribe CA, Eichel L, et al. Comparison of guide wires in urology. Which, when and why? J Urol. 2004;171(6 Pt 1):2146-2150. doi:10.1097/01.ju.0000124486.78866.a5
6. Freid RM, Smith AD. The Glidewire technique for overcoming urethral obstruction. J Urol. 1996;156(1):164-165. doi:10.1016/s0022-5347(01)65975-5. PMID 8648783
7. See WA. Council-tip catheter facilitates vesicourethral anastomotic suture placement. Urology. 1995;46(3):401-402. doi:10.1016/S0090-4295(99)80228-3
8. Bugeja S, Mistry K, Yim IHW, et al. A new urethral catheterisation device (UCD) to manage difficult urethral catheterisation. World J Urol. 2019;37(4):595-600. doi:10.1007/s00345-018-2499-9
9. Liss MA, Leifer S, Sakakine G, Esparza M, Clayman RV. The Liss maneuver: a nonendoscopic technique for difficult Foley catheterization. J Endourol. 2009;23(8):1227-1230. doi:10.1089/end.2009.0043
10. Willette PA, Coffield S. Current trends in the management of difficult urinary catheterizations. West J Emerg Med. 2012;13(6):472-478. doi:10.5811/westjem.2011.11.6810
11. Kobatake K, Inoue S, Takemoto K, et al. Evaluation of urinary catheters for effective manual bladder washout. Sci Rep. 2022;12(1):14359. doi:10.1038/s41598-022-18778-5
12. Abbott JE, Heinemann A, Badalament R, Davalos JG. A clever technique for placement of a urinary catheter over a wire. Urol Ann. 2015;7(3):367-370. doi:10.4103/0974-7796.157959