Suprapubic Catheter (SPT)
A suprapubic catheter (SPC or SPT) is an indwelling catheter placed percutaneously or operatively through the anterior abdominal wall into the bladder, bypassing the urethra. It avoids a continuously indwelling urethral catheter. In appropriately selected adults with neurogenic lower urinary tract dysfunction (NLUTD) who require chronic indwelling drainage, AUA/SUFU recommends suprapubic rather than urethral catheterization . Intermittent catheterization is preferred when feasible and appropriate.[1]
Suprapubic drainage can protect the urethra and make catheter care or sexual activity easier for some patients. It still entails an invasive insertion and ongoing risks of blockage, infection, stones, leakage, spasm and tract loss; neither preserved sexual function nor freedom from infection is guaranteed.[1][2]
Indications and route selection
Suprapubic drainage is considered when long-term catheterization is needed or urethral catheterization is not feasible or desired.[2] Typical settings are:
- neurogenic bladder (spinal cord injury, multiple sclerosis) when intermittent catheterization is not feasible;
- chronic retention refractory to other management;
- urethral abnormalities such as stricture, false passage, bladder-neck obstruction or urethral fistula;
- pelvic fracture urethral injury: EAU strongly recommends suprapubic diversion followed by urethroplasty after at least three months for complete posterior disruption in men; partial posterior injuries may heal after suprapubic or transurethral drainage, while female injuries should be repaired within seven days once the patient is stable.[29]
- protective diversion during healing after urethral reconstruction;
- perineal skin breakdown worsened by a urethral catheter;
- refractory OAB, where AUA/SUFU advises chronic indwelling urethral or suprapubic catheters only when OAB therapies are contraindicated, ineffective or no longer desired, and always with shared decision-making ;[11]
- patient preference, for example to spare the urethra or ease sexual activity.
In acute urethral trauma, the ACS guideline places the suprapubic catheter by image-guided percutaneous insertion or open cystotomy, because a pelvic hematoma can displace the bladder or a bladder injury can leave it poorly filled. It advises a catheter of 14 Fr or larger, so the bladder drains and the tube can be irrigated, and prefers a true Foley catheter to pigtail types, which usually need exchange or upsizing for poor drainage and clogging. Coordinate with orthopaedics when pelvic hardware is planned.[27]
Suprapubic drainage is also used for urethral rest before definitive stricture surgery. The EAU stricture guideline text states that a suprapubic catheter should be inserted if incapacitating obstructive symptoms or retention develop during urethral rest (narrative text, not a strength-rated recommendation).[3]
The decision should include bladder storage pressures, urethral anatomy, hand function, caregiver support, mobility, skin and body habitus, anticipated duration, patient goals, and alternatives. An external collection device does not treat retention. For continence without an emptying indication, an indwelling catheter requires a separate, carefully justified discussion of alternatives and harms.[1][2]
See Intermittent Catheterization, Pelvic Fracture Urethral Injury, and Urinary Diversion.
Device and insertion planning
A suprapubic catheter is usually a Foley-type balloon catheter passed through the tract. Dedicated trocar-placed kits and pigtail or self-retaining designs also exist (product names include Cystofix, Bonanno and Stamey). Select a catheter and access system appropriate to the tract, urine and debris burden, anatomy, and product instructions. Balloon inflation fluid and volume and subsequent exchange compatibility remain device-specific.[2]
Peel-away kits are easy to place but often deliver a 12 or 14 Fr catheter that is prone to kinking and may need serial upsizing. Open placement permits a larger initial catheter but is more invasive, particularly in obese patients.[12] When access accompanies bladder augmentation, trauma repair or abdominal vesicovaginal-fistula repair, a 24–26 Fr catheter has been described for open suprapubic drainage; for augmentation, placing it through a separate bladder incision away from the cystotomy allows drainage and mucus washout without traversing the repair. The 24–26 Fr size reflects described operative practice.[28] No source sets a universal minimum caliber or fixed skin site. One institutional technique places a 17G Tuohy needle about 3 cm above the pubis (generally in the abdominal crease), 1 to 2 cm off midline toward the side where the patient prefers the drainage bag, and angles it to enter the bladder dome in the midline under cystoscopic vision so that the catheter lies flat. A 24 Fr nephrostomy balloon and sheath then allow initial placement of a catheter of 20 Fr or larger. In that 65-placement single-institution series, median operative time for placements without an additional procedure was 16 minutes, all placements of 20 Fr or larger succeeded, Clavien I/II complications occurred in 18%, one Clavien IIIb event occurred, and the first clinic exchange succeeded in 95% (2 patients needed replacement under anesthesia).[12]
Before percutaneous insertion, establish a safely accessible bladder and assess for interposed bowel, previous abdominal or pelvic surgery, altered anatomy, scars, mesh or vascular grafts. A bladder that is not palpable may still be localizable by imaging; a bladder that cannot be safely localized or accessed is not a target for a blind puncture. Prior surgery, pelvic radiation, pregnancy, anticoagulation or coagulopathy and infection at the proposed site require specialist planning. Known or suspected bladder cancer and unexplained gross hematuria require particular assessment because a suprapubic route may be unsuitable, including concern about tumor seeding.[2]
| Approach | Role and limitation |
|---|---|
| Image-guided percutaneous access | Ultrasound helps identify the bladder, trajectory and overlying structures; fluoroscopy may assist wire/catheter placement. An adequate safe window is required. |
| Trocar or Seldinger access | Different access methods selected for the situation and operator expertise. Trocar access is a single step through a puncture cannula; a bedside series of 72 men with a palpable bladder, excluding prior lower abdominal surgery, reported a mean procedure time under five minutes and no complications.[13] Seldinger access uses needle, wire and dilation. Neither method is universally safer in all anatomy. |
| Cystoscopic assistance | Confirms intravesical entry and position. Looking inside the bladder does not independently exclude bowel between skin and bladder. |
| Lowsley retractor or Van Buren sound | The bladder is entered by incision onto a sound or retractor passed per urethra, with cystoscopy. A retrospective series of 44 patients with neurogenic bladder included 49 primary Lowsley placements; mean operative time was about 20 minutes among the 19 placements with documented times, and no incorrect placements were reported.[14] A Van Buren sound technique has been described that allows wire exchange of the catheter before a tract is established; it needs an intact urethra and is contraindicated in pelvic trauma.[15] |
| Open placement | An option when percutaneous access is unsafe or when placement accompanies another operation. |

Commercially available stainless steel trocar with an outer sheath and an inner obturator. The inset shows the distal end of the trocar with a hole near the tip. From Goyal NK, et al. Ann R Coll Surg Engl. 2012;94(8):597-600, Figure 1 (CC BY).[13]
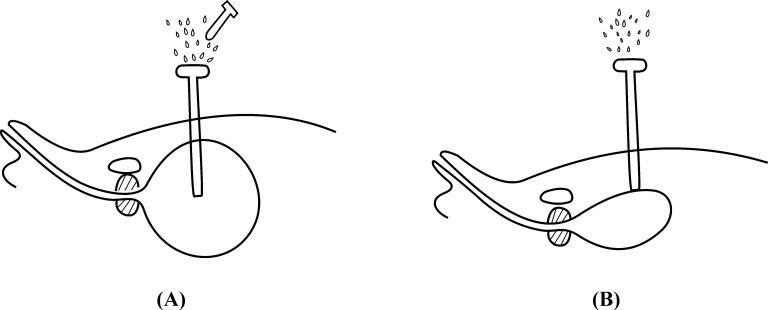
Mechanism of catheter misplacement with trocar access. (A) On removal of the obturator, urine leaks rapidly from the sheath. (B) The sudden bladder decompression can displace the sheath out of the bladder wall, so the catheter is then misplaced. From Goyal NK, et al. Ann R Coll Surg Engl. 2012;94(8):597-600, Figure 3 (CC BY).[13]
Jacob et al. described earlier BAUS advice to use ultrasound whenever possible to identify interposed bowel; the revised 2020 BAUS guideline recommends ultrasound when the bladder cannot readily be palpated and calls for a trained practitioner to assess the needle path in real time.[16][31] The conventional blind technique depends on bladder filling to displace bowel. In a historical series of 219 cystoscopy-guided suprapubic insertions, bowel injury occurred in five patients (reported as 2.4%), and overall 30-day mortality was 1.8%.[16][30] Contemporary data suggest a lower risk (see below).
When ultrasound shows bowel overlying the anterior bladder wall in a patient unfit for general anesthesia, hydrodissection has been described. In a single case report, the bladder was filled through the urethral catheter, and a 22G needle with 30 mL (10 mL 1% lidocaine plus 20 mL sterile water) was inserted under ultrasound between the pubic symphysis and the overlying bowel. Injection displaced the bowel, an 18G needle then entered the bladder, and the catheter was placed by Seldinger technique with no complications at 6 months.[17]
Do not force distension of a low-capacity or recently repaired bladder to meet a generic target. Plan analgesia or anesthesia and monitoring, including autonomic dysreflexia precautions when relevant.[2] See the hydrodissection hub.[2]
Trocar and Seldinger compared
A retrospective comparison of 125 image-guided cystostomies (Roberts 2020) found both approaches technically successful, with rare major complications. Trocar access was faster and needed less sedation and radiation. Occlusion was more frequent with trocar access, possibly because of a catheter-tract size mismatch.[18]
| Outcome | Trocar (n = 60) | Seldinger (n = 65) | p |
|---|---|---|---|
| Procedure time | 12.4 min | 25.7 min | <.001 |
| Catheter size | 13.1 Fr | 13.9 Fr | .044 |
| Mean midazolam dose | 1.2 ± 0.8 mg | 1.9 ± 1.1 mg | .003 |
| Radiation | 20.2 mGy | 100.7 mGy | <.001 |
| Catheter occlusion | 41.7% | 16.9% | .003 |
| Bladder spasm | 1.7% | 13.8% | .018 |
Overall, catheter occlusion was the most common complication (28.8%), followed by UTI (13.6%) and bladder spasm (8.0%).[18]
Complication evidence: use the right denominator
Hobbs 2022 retrospectively reviewed 1,000 elective insertions, predominantly in patients with spinal cord injury. Cystoscopy-guided puncture or an incision onto a urethral sound followed by cystoscopy accounted for 98% of procedures. Clavien–Dindo grade IIIb or higher complications occurred in 0.6%; no bowel injury was observed, and one patient died within 30 days from pulmonary embolism. Mostly minor complications occurred in 59% over variable follow-up (median 3.3 years).[4]
Hall 2019 identified 11,473 insertions in a UK administrative audit. Of 141 subsequent laparotomy cases, information was returned for 114 and one SPC-related bowel injury was identified. The accompanying published-series meta-analysis found 11/1,490 bowel injuries (0.7%); the authors proposed counseling low-risk patients with a risk below 0.25%. The ascertainment limits, different populations and methods prevent treating the national audit as a complete exact risk estimate or attributing a historical decline to one device.[5]
A more recent long-term cohort of 222 patients with at least two years of follow-up reported short-term (30.2%) and long-term (59.9%) complication rates that were mostly minor: Clavien–Dindo grade III or higher occurred in 4.5% and 23%. Ancillary lower-tract treatments (anticholinergics, intradetrusor onabotulinumtoxinA) were used in 46%, and discontinuation was 13.9% at a median of 12 months. In this 222-patient cohort, ancillary treatment was associated with catheter retention; pre-emptive prescribing was not tested. Absence of ancillary treatment (OR 56.8) and initial placement by interventional radiology (OR 2.03) predicted discontinuation univariately.[6]
A within-subject retrospective study of 37 elderly patients who moved from a urethral to a suprapubic catheter found lower CAUTI (38% vs 86%, p < 0.001), fewer emergency department visits (35% vs 68%, p < 0.001), fewer obstructions and less hematuria after the change.[19] Dislodgement and leakage did not differ. The design is retrospective and the cohort small.[19] The EAU 2026 infections guideline states that some limited studies show fewer CAUTIs with intermittent or suprapubic catheterization than with urethral catheterization, but that evidence is insufficient to recommend either routinely.[26] It cites a nursing-home cohort in which suprapubic catheters were associated with fewer CAUTIs and hospitalizations but more colonization with multidrug-resistant organisms, and notes that urine culture results are important because the organisms may differ from those of urethral catheters.[26]
Care and catheter exchanges
Use securement without traction, closed drainage, a bag below bladder level, routine hygiene, and individualized hydration advice. Assess constipation, debris, spasm, and catheter position when drainage fails or urine bypasses. Routine antibiotics or antimicrobial washouts are not standard prevention strategies.[2][7]
First and difficult exchanges
The first exchange requires an established tract and an operator capable of managing loss of access. Timing depends on the insertion method, healing, catheter system and local specialist protocol; a calendar date alone does not prove tract maturity. Document who will perform the first change and whether imaging or wire guidance is needed.[2]
- Record the original catheter type, size, balloon instructions, insertion details and planned exchange method.
- Deflate and remove according to the device instructions; do not pull against an inflated or retained balloon.
- Confirm the replacement catheter's intravesical position before balloon inflation. Unexpected depth, pain, resistance, absent drainage, or uncertainty requires reassessment rather than force.
- A wire-assisted exchange requires a compatible catheter and controlled access; it is not achieved by blindly pushing a wire or replacement catheter into an uncertain tract.
Dislodgement needs urgent assessment because the tract can close rapidly. An early or lost tract may require image-guided or operative replacement. Do not teach untrained patients or carers to force a catheter into it. Provide a clear emergency contact and backup drainage plan. Tract losses during routine community changes have been reported.[2][4]
A multifunctional suprapubic catheter (scale markings and modified drainage holes) reduced catheter occlusion (11.6% vs 37.5%, p = .005) and cystospasm compared with a conventional balloon catheter in a single-center randomized trial of 91 patients.[20]
Subsequent intervals
Base replacement on clinical need, the manufacturer's maximum dwell time, and the individual's blockage pattern. CDC does not recommend routine fixed-interval changes for every patient. The 2016 Cochrane review found only three small trials totaling 107 participants and insufficient evidence for a universal replacement policy.[7][8]
Long-term surveillance and cancer risk
AUA/SUFU advises interval catheter and site examination in NLUTD patients with indwelling catheters and urinary-tract imaging every 1–2 years for NLUTD patients with indwelling catheters who are at risk of calculi , with broader follow-up guided by NLUTD risk category.[9]
Chronic catheter use is associated with bladder cancer in observational cohorts.
- Ontario. The population cohort (36,903 chronically catheterized patients matched to 110,709 controls) reported bladder cancer in 1.1% vs 0.3% (adjusted subdistribution HR 4.80, 95% CI 4.26–5.42) and cancer-specific death HR 8.68. Risk was highest beyond 2.9 years of catheterization.[10] The study combined indwelling and intermittent catheterization.[10]
- Taiwan. A registry study of 72,971 patients with chronic indwelling catheters reported 213.29 vs 40.84 bladder cancers per 100,000 person-years (adjusted HR 5.16).[21] Another Taiwanese cohort reported HR 9.11 for chronic indwelling catheters without spinal cord injury versus a reference cohort.[22]
- Spinal cord injury. In 3,670 patients with 21 bladder cancers, sole indwelling catheter use carried RR 4.9 (95% CI 1.3–13.8) versus non-indwelling methods.[23] Biopsies in 208 patients with catheters for more than 8.5 years found malignancy in 17 (10 squamous cell carcinomas) and premalignant keratinizing squamous metaplasia or cystitis glandularis in 48 (23%).[24]
- Screening evidence. A scoping review found that screening is often recommended in spinal cord injury guidelines, but the evidence for tools and protocols is lacking.[25]
AUA/SUFU recommends against screening or surveillance cystoscopy in NLUTD patients, including those with chronic indwelling catheters . Hematuria, recurrent infections, suspected anatomic abnormality or other concerning changes warrant targeted evaluation; known bladder cancer follows its own surveillance pathway.[9]
Do not routinely screen for or treat asymptomatic bacteriuria. Pregnancy and selected urologic procedures breaching the mucosa are exceptions. New fever, flank pain, systemic illness, persistent hematuria, abdominal pain, failure to drain, or autonomic dysreflexia requires assessment rather than attribution to ordinary catheter colonization.[7][9]
References
1. Ginsberg DA, Boone TB, Cameron AP, et al. The AUA/SUFU guideline on adult neurogenic lower urinary tract dysfunction: treatment and follow-up. J Urol. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239. Statements 35–36.
2. European Association of Urology Nurses. Indwelling catheterisation in adults—urethral and suprapubic. 2024.
3. EAU. Urethral strictures guideline. Perioperative care of urethral surgery: urethral rest. 2026.
4. Hobbs C, Howles S, Derry F, Reynard J. Suprapubic catheterisation: a study of 1000 elective procedures. BJU Int. 2022;129(6):760-767. doi:10.1111/bju.15727
5. Hall S, Ahmed S, Reid S, et al. A national UK audit of suprapubic catheter insertion practice and rate of bowel injury with comparison to a systematic review and meta-analysis of available research. Neurourol Urodyn. 2019;38(8):2194-2199. doi:10.1002/nau.24114
6. Willging AM, Khawaja F, Erickson BA. Suprapubic catheter drainage for the definitive, long-term management of lower urinary tract dysfunction: utilization patterns and longitudinal outcomes. Urology. 2026;207:71–75. doi:10.1016/j.urology.2025.10.002
7. CDC. CAUTI prevention: summary of recommendations. 2009 guideline; web summary updated 2024.
8. Cooper FP, Alexander CE, Sinha S, Omar MI. Policies for replacing long-term indwelling urinary catheters in adults. Cochrane Database Syst Rev. 2016;7:CD011115. doi:10.1002/14651858.CD011115.pub2
9. Ginsberg DA, Boone TB, Cameron AP, et al. The AUA/SUFU guideline on adult neurogenic lower urinary tract dysfunction: diagnosis and evaluation. J Urol. 2021;206(5):1097-1105. doi:10.1097/JU.0000000000002235. Statements 18–25.
10. Hird AE, Saskin R, Liu Y, et al. Association between chronic bladder catheterisation and bladder cancer incidence and mortality: a population-based retrospective cohort study in Ontario, Canada. BMJ Open. 2021;11:e050728. doi:10.1136/bmjopen-2021-050728
11. Cameron AP, Chung DE, Dielubanza EJ, et al. The AUA/SUFU guideline on the diagnosis and treatment of idiopathic overactive bladder. J Urol. 2024;212(1):11-20. doi:10.1097/JU.0000000000003985. Statement 31.
12. Flynn KJ, Schlaepfer CH, Khawaja F, Erickson BA. Nephrostomy balloon and sheath suprapubic tube placement: a minimally invasive approach to large caliber suprapubic tube placement. Urology. 2022;164:e302. doi:10.1016/j.urology.2022.03.013
13. Goyal NK, Goel A, Sankhwar SN. Safe percutaneous suprapubic catheterisation. Ann R Coll Surg Engl. 2012;94(8):597-600. doi:10.1308/003588412X13373405385412
14. Edokpolo LU, Foster HE Jr. Suprapubic cystostomy for neurogenic bladder using Lowsley retractor method: a procedure revisited. Urology. 2011;78(5):1196-1198. doi:10.1016/j.urology.2011.07.1393
15. Wyner LM. Easy suprapubic tube placement using a Van Buren sound. Urology. 2018;114:245. doi:10.1016/j.urology.2018.01.006
16. Jacob P, Rai BP, Todd AW. Suprapubic catheter insertion using an ultrasound-guided technique and literature review. BJU Int. 2012;110(6):779-784. doi:10.1111/j.1464-410X.2011.10882.x
17. Chan KKC, Speirs A. Novel use of hydrodissection for the insertion of suprapubic catheter under ultrasound guidance. Urology. 2020;136:263-265. doi:10.1016/j.urology.2019.09.041
18. Roberts DG, Patel RB, Genshaft SJ, et al. Interventional radiology image-guided suprapubic cystostomy using trocar versus Seldinger technique: a comparative analysis of outcomes and complications. Urology. 2020;142:207-212. doi:10.1016/j.urology.2020.05.015
19. Perez D, Shapiro DS, Bohm D, et al. Comparative outcomes of indwelling urethral versus suprapubic catheters in elderly patients: a retrospective within-subject study. Neurourol Urodyn. 2025. doi:10.1002/nau.70133
20. Dong HJ, Lu Y, Zhang NZ, et al. Clinical evaluation of the multifunctional suprapubic catheter in patients requiring permanent suprapubic cystostomy: a prospective randomised trial in a single centre. J Clin Nurs. 2019;28(13-14):2499-2505. doi:10.1111/jocn.14208
21. Tseng WH, Lee CH, Lin RJ, et al. Risk of bladder cancer in patients with chronic indwelling catheters: a real-world data analysis. J Cancer. 2025;16(11):3464-3472. doi:10.7150/jca.114223
22. Ho CH, Sung KC, Lim SW, et al. Chronic indwelling urinary catheter increase the risk of bladder cancer, even in patients without spinal cord injury. Medicine (Baltimore). 2015;94(43):e1736. doi:10.1097/MD.0000000000001736
23. Groah SL, Weitzenkamp DA, Lammertse DP, et al. Excess risk of bladder cancer in spinal cord injury: evidence for an association between indwelling catheter use and bladder cancer. Arch Phys Med Rehabil. 2002;83(3):346-351. doi:10.1053/apmr.2002.29653
24. Delnay KM, Stonehill WH, Goldman H, Jukkola AF, Dmochowski RR. Bladder histological changes associated with chronic indwelling urinary catheter. J Urol. 1999;161(4):1106-1109. doi:10.1016/s0022-5347(01)61601-x. PMID 10081848
25. Welk B, McIntyre A, Teasell R, Potter P, Loh E. Bladder cancer in individuals with spinal cord injuries. Spinal Cord. 2013;51(7):516-521. doi:10.1038/sc.2013.33
26. European Association of Urology. EAU Guidelines on Urological Infections (section 3.8.4.c, alternatives to indwelling urethral catheterization). 2026 limited update, March 2026. Full guideline.
27. Johnsen N, Wessells H, Archer-Arroyo K, et al. Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons Trauma Quality Programs; August 2025. Initial management of urethral injury, p. 53.
28. Mahdy A, Karram MM. Suprapubic Catheter Placement. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1063-1070.
29. European Association of Urology. EAU Guidelines on Urological Trauma. 2026. Section 4.4, urethral trauma. Guideline.
30. Ahluwalia RS, Johal N, Kouriefs C, Kooiman G, Montgomery BSI, Plail RO. "The surgical risk of suprapubic catheter insertion and long-term sequelae." Ann R Coll Surg Engl. 2006;88(2):210–213. doi:10.1308/003588406X95101
31. Hall SJ, Harrison S, Harding C, Reid S, Parkinson R. "British Association of Urological Surgeons suprapubic catheter practice guidelines – revised." BJU Int. 2020;126(4):416–422. doi:10.1111/bju.15123