Nasal Speculum
The nasal speculum, including pediatric and other ENT variants, has been repurposed in reconstructive urology and urogynecology for deep, narrow exposure. Published urologic evidence is clearest for selected transurethral mesh-removal cases; use during deep posterior or redo urethroplasty is specialist operative teaching that remains incompletely documented in the sources reviewed here.
Design
The nasal speculum has two short, blunt, parallel blades joined at a hinge, opened either by squeezing a handle or via a thumb-screw lock. Common variants relevant to urology:
| Variant | Blade length | Typical urology niche |
|---|---|---|
| Pediatric nasal speculum (pattern unspecified) | Select by the actual model and urethral fit | Published two-case transurethral mesh-removal use[2] |
| Vienna | 26–33 mm in the FENTEX catalog[7]; dimensions vary by model | Narrow-corridor exposure described in operative teaching |
| Killian | Long-bladed ENT pattern | Deep perineal exposure described in operative teaching |
Exact blade length, opening mechanism and naming vary by manufacturer; inspect the actual instrument rather than selecting from the approximate historical labels alone.
Transurethral Application — Midurethral-Sling Mesh Erosion
Urethral mesh erosion is an uncommon but technically difficult complication of synthetic midurethral slings (TVT, TOT, etc.). Incidence estimates based on vaginal exposure, bladder or urethral erosion, diagnosis, removal and reoperation measure distinct outcomes. Endoscopic or transurethral approaches are minimally invasive alternatives to transvaginal or open removal in selected patients.[1][4][5]
Published descriptions
- Plowright 2013. Pediatric nasal speculum inserted at the urethral meatus to provide working exposure for transurethral resection of eroded mesh.[2] The two-case report describes complete resection, symptom resolution and no recurrence during the authors’ reported follow-up.[2]
- Solomon & Jelovsek 2015. Misplaced retropubic midurethral sling within the urethral mucosa in a 63-year-old with gross hematuria; intraurethral mesh dissected out using a full ENT tray: nasal speculum, ethmoid scissors, Blakesley graspers, and a headlamp. The technique allowed mesh resection without incising the urethral sphincter.[3]
Why the nasal speculum fits
- Narrow working profile. Permits direct access through the urethral meatus in the reported cases
- Potentially stable exposure when the selected model can be held or locked open
- Compatible with adjunct instruments. Fine scissors and graspers fit alongside the blades
- May avoid urethrotomy in a selected accessible erosion, as described in the single Solomon/Jelovsek case
Place in the mesh-erosion algorithm
Sobota's 2019 systematic review found heterogeneous, nonrandomized evidence and a trend toward better symptom resolution and fewer reinterventions with transvaginal than cystoscopic removal for urethral mesh erosion.[4] Karim's 2020 open systematic review found high reported final success for laser and other endoscopic methods, but all included studies were retrospective case series, 20–25% of patients could require more than one endoscopic procedure, and there was no open comparator group.[5]
Transurethral Application — Female Urethroplasty
In a vaginal-sparing ventral inlay buccal mucosal graft urethroplasty for a full-length female urethral stricture, the nasal speculum held the dilated urethra open after ventral urethrotomy so that the graft could be sutured from the proximal urethra and bladder neck to the meatus without a vaginal incision. This is a single-patient technical report: the repair was patent on flexible cystoscopy at 6 months, and the patient was voiding without incontinence at 10 months.[6] See Female Ventral Inlay BMG Urethroplasty.
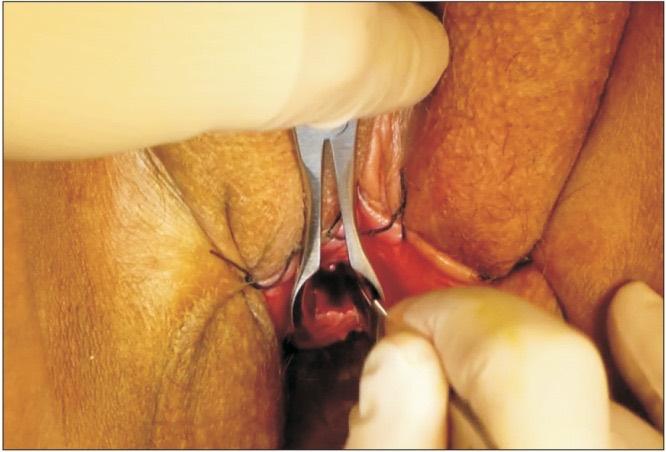
Vaginal-sparing ventral buccal mucosal graft urethroplasty for female urethral stricture: the urethra is dilated to accommodate a nasal speculum, and the ventral urethrotomy is made sharply with an 11-blade scalpel. From Hoag N, et al. Investig Clin Urol. 2016;57(4):298–302, Fig. 1 (CC BY-NC 4.0).[6]
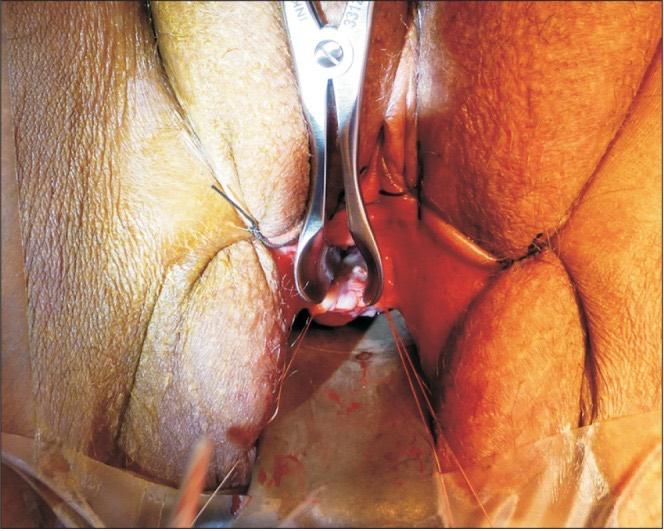
Same technique: with the nasal speculum inserted into the urethra, the buccal mucosal graft is placed ventrally and sutured into position from the proximal to the distal urethra. From Hoag N, et al. Investig Clin Urol. 2016;57(4):298–302, Fig. 3 (CC BY-NC 4.0).[6]
Posterior / Redo Urethroplasty Application
In posterior anastomotic urethroplasty for pelvic-fracture urethral injury (PFUI) and in redo or salvage urethroplasty for proximal bulbar or membranous strictures, exposure of the proximal urethral stump deep in the perineum is the rate-limiting step. Once corporal splitting and inferior pubectomy are complete, the deepest part of the working corridor is narrow and conical, too tight for a Breisky or Heaney blade and beyond the reach of Lone Star stays. The Jordan-Bookwalter / Perineal Bookwalter ring solves the superficial and mid-corridor exposure but does not reach the deep apex.
Some specialist operative teaching describes a long-bladed nasal speculum to retract tissue laterally at the deep apex without occupying the surgeon's line of sight. In posterior substitution urethroplasty, Kaldany et al. describe a 12 Fr nasal speculum as one option for visualizing the posterior urethra and prefer a lighted urethral speculum when available.[8] Other uses below remain specialist operative teaching:
- Visualization of the proximal urethral stump above the prostatic apex during transperineal anastomotic urethroplasty
- Exposure of the membranous urethra and dorsal vein complex in redo or radiation-injured fields where scar contracts the deep corridor
- Dissection alongside the elevated bulbar urethra during supracrural-rerouting and inferior-pubectomy steps when the field is funnel-shaped
- Salvage prostatectomy and complex bladder-neck dissection in limited-access posterior fields where line of sight is a priority
The concept resembles the historical gorget as a narrow-corridor exposure aid and may complement a perineal Bookwalter ring.
Pearls
- Match the actual blade profile and opening range to the corridor
- Use only the retention mechanism supplied for that model and minimize opening force and duration to reduce pressure injury
- Use with a headlamp or operative loupes. The deep corridor swallows ambient OR light
- Adapt the instrument tray to the field. Fine ENT scissors, Blakesley graspers, and bipolar forceps fit alongside the speculum blades where standard urology instruments do not
Related Instruments
- Gorget: historical perineal lithotomy instrument with the same deep narrow exposure niche
- Perineal Bookwalter (Jordan): ring retractor for the broader perineal opening
- Lone Star Retractor: hook-stay retractor for vaginal and perineal exposure
- Breisky: wider deep vaginal blade
References
1. Allagany F, Dekalo S, Welk B. "Endoscopic Management of Intraurethral Mesh Extrusion With the Holmium:YAG Laser Is an Acceptable Treatment Option in Selected Patients." Neurourol Urodyn. 2022;41(6):1511–1516. doi:10.1002/nau.24999
2. Plowright LN, Duggal B, Aguilar VC, Davila GW. "Endoscopic Transurethral Resection of Urethral Mesh Erosion With the Use of a Pediatric Nasal Speculum." Obstet Gynecol. 2013;121(2 Pt 2 Suppl 1):440–443. doi:10.1097/AOG.0b013e31827ee037
3. Solomon ER, Jelovsek JE. "Removing a Misplaced Retropubic Midurethral Sling From the Urethra and Bladder Neck Using Ear, Nose, and Throat Instruments." Obstet Gynecol. 2015;125(1):58–61. doi:10.1097/AOG.0000000000000568
4. Sobota R, Thomas D, Demetres M, et al. "The Management and Efficacy of Surgical Techniques Used for Erosive Mesh in the Urethra and Bladder: A Systematic Review." Urology. 2019;134:2–23. doi:10.1016/j.urology.2019.08.001
5. Karim SS, Pietropaolo A, Skolarikos A, et al. "Role of Endoscopic Management in Synthetic Sling/Mesh Erosion Following Previous Incontinence Surgery: A Systematic Review From European Association of Urologists Young Academic Urologists (YAU) and Uro-Technology (ESUT) Groups." Int Urogynecol J. 2020;31(1):45–53. doi:10.1007/s00192-019-04087-5
6. Hoag N, Gani J, Chee J. "Vaginal-Sparing Ventral Buccal Mucosal Graft Urethroplasty for Female Urethral Stricture: A Novel Modification of Surgical Technique." Investig Clin Urol. 2016;57(4):298–302. doi:10.4111/icu.2016.57.4.298
7. FENTEX medical. Rhinology – Rhinologie instrument catalog. Manufacturer catalog. Nasal specula, pp. 8–20.
8. Kaldany A, Cedars B, Nikolavsky D. "Substitution urethroplasty for posterior urethral stenosis." Transl Androl Urol. 2025;14(12):3962–3974. doi:10.21037/tau-2025-566