History of Prosthetics & Erectile Dysfunction Treatment
The history of erectile dysfunction treatment and penile prosthetics runs from ancient aphrodisiacs and spiritual remedies, through the mechanical inventions of the 1970s, to oral pharmacotherapy in the late 1990s. The inflatable penile prosthesis (first implanted in 1973) came from the same team, and the same hydraulic principle, as the artificial urinary sphincter.[3][4] Across the same decades, the vacuum erection device, intracavernosal injection therapy, and oral PDE5 inhibitors turned a condition once managed only surgically into a tiered pharmacological and procedural discipline.
Ancient and Pre-Modern Treatments
Erectile dysfunction has been recognized and treated since antiquity, with approaches ranging from the empirical to the magical.[1]
Ancient Egypt. The Ebers Papyrus (c. 1550 BC) lists plant remedies for impotence, and other Egyptian sources describe an ointment of baby crocodile hearts in oil applied topically to the penis. Internal remedies employed dried beetle preparations and sesame oils.
Ancient Greece and Rome. Galen described impotence as arising from excess cold, moist humors. Pliny the Elder (Naturalis Historia, 77 AD) catalogued botanical and zoological aphrodisiacs including hippocampus fat, hyena genitalia, and wolf liver. Dioscorides described orchid tubers (Orchis), which resemble testes, as erectile remedies, an early example of sympathetic magic in medicine.
Medieval Islamic Medicine. Avicenna (Ibn Sina, c. 1025 AD) in The Canon of Medicine described impotence from psychological, vascular, and neurological perspectives. He prescribed compound preparations including theriac, nutmeg, and clove.
Renaissance Europe. In the 16th century Ambroise Paré fashioned a wooden penis as a urinary conduit for a man who had lost his penis to trauma, one of the earliest recorded penile prostheses.[3]
19th and Early 20th Century: Physical Devices
Vacuum Erection Devices — Early Origins
The vacuum erection device has origins in 19th-century medicine. Vincent Marie Mondat described a suction device in the early 1800s.[1] The American physician John King described a glass vacuum exhauster applied to the penis in 1874. Otto Lederer filed a patent in 1913 (granted 1917) for a device combining suction with a constriction ring at the penile base. Neither achieved clinical traction, and the concept lay dormant until Geddings Osbon built a device for his own use in the 1960s and began marketing it in 1974.[11]
Early Penile Prostheses
Bogoras (1936). The Russian surgeon N.A. Bogoras is credited with the first reported penile reconstruction using a rib cartilage graft implanted into a phallic construct, published in Zentralblatt für Chirurgie (1936). The cartilage was meant to act like the os penis (baculum) of other mammals. This established the principle that internal rigid support could restore function after traumatic penile loss.[2]
Goodwin and Scott (1952). Willard Goodwin and William Wallace Scott reported the first use of a synthetic material for penile implantation, an acrylic rod positioned beneath Buck's fascia as an artificial baculum.[2]
Goodwin WE, Scott WW. "Phalloplasty." J Urol. 1952;68(6):903–908.
Harvey Lash (1964). Lash, Zimmerman and Loeffler described the first silicone penile prosthesis series, a single rod placed beneath Buck's fascia and outside the corpora cavernosa.[1]
G.E. Beheri (1966). Egyptian plastic surgeon Beheri was the first to describe placement of paired intracorporeal polyethylene rods within the corpora cavernosa, the anatomical shift that all future designs would follow. He published results of over 700 such procedures. Because he published in plastic surgery rather than urology journals, the technique initially gained little traction in urology.[3]
Pearman (1967). Pearman expanded on Lash's silicone work with a rod placed beneath Buck's fascia on the dorsum of the penis. Reviews differ on whether his 1967 rod lay outside the tunica albuginea or within the corpora.[1][3]
The Modern Era of Penile Prosthesis Surgery (1973–present)
AUA 1973: The Dual Announcement
At the 1973 Annual Meeting of the American Urological Association, two groups presented prototype penile prostheses, one inflatable and one semi-rigid, and the two devices entered practice almost simultaneously:[6]
- Baylor College of Medicine and the University of Minnesota (Scott, Bradley, Timm): the inflatable penile prosthesis
- University of Miami (Small, Carrion): the semi-rigid prosthesis
The simultaneous development reflected a growing understanding of erectile physiology, improved silicone manufacturing, and the needs of post-prostatectomy and post-priapism patients with no other options.
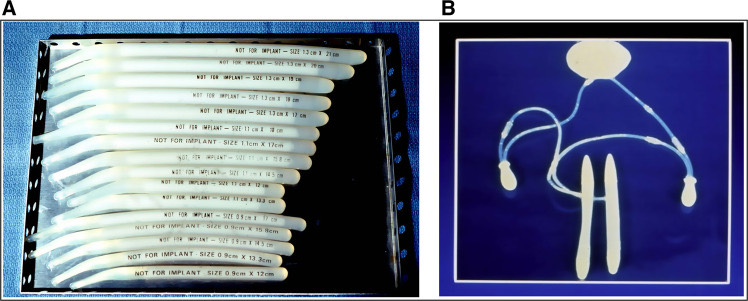
The two devices announced at the 1973 AUA meeting. (A) Small-Carrion semi-rigid prostheses in a range of lengths and diameters. (B) The early Scott (later AMS) inflatable prosthesis, with paired cylinders, two pumps and a reservoir. From Wilson SK, Gross MS. Int J Impot Res. 2023;35(7):596-600, Fig. 1 (CC BY 4.0).[6]
Scott, Bradley, and Timm — The Inflatable Penile Prosthesis (1973)
F. Brantley Scott, a urologist at Baylor College of Medicine in Houston, developed the device with William E. Bradley, a neurologist, and Gerald W. Timm, a biomedical engineer, both of the University of Minnesota. The work grew out of their concurrent development of the artificial urinary sphincter.[4][8] The design used a hydraulic mechanism to restore penile tumescence by fluid transfer between implanted components, mimicking the natural hemodynamics of erection.
The three-component device:
- Two inflatable cylinders implanted within the corpora cavernosa
- A saline reservoir implanted in the space of Retzius (prevesical space)
- A scrotal pump to transfer fluid, with a deflation valve
Around 15 devices of this first model were implanted from February 1973 to August 1974 before it was discontinued.[6] Scott, Bradley, and Timm had co-founded American Medical Systems (AMS) in Minnetonka, Minnesota, in 1972 with the businessman Robert Buuck to manufacture their devices.[4]
Scott FB, Bradley WE, Timm GW. "Management of erectile impotence. Use of implantable inflatable prosthesis." Urology. 1973;2(1):80–82. [PMID: 4766860][4]
Small and Carrion — The Semi-Rigid Prosthesis (1973/1975)
Michael P. Small and Hernan M. Carrion (University of Miami) described a simpler, paired sponge-filled semi-rigid silicone-covered rod prosthesis implanted via a perineal approach and available in four lengths (12–15.8 cm) and two diameters. The penis remained in a permanently semi-rigid state. Their 1975 report described 31 patients, and by December 1977, 260 patients had undergone insertion with minimal complications. The Small-Carrion was the first widely reproducible, commercially marketable prosthesis and the forerunner of the modern malleable penile prosthesis.[3][5]
Small MP, Carrion HM, Gordon JA. "Small-Carrion penile prosthesis: new implant for management of impotence." Urology. 1975;5(4):479–486. [PMID: 1093303][5]
Device Evolution: AMS Inflatable Prostheses (1973–2006)
The current device is described on the inflatable penile prosthesis page.[3][6]
| Year | Device | Innovation |
|---|---|---|
| 1973 | AMS prototype | First three-piece IPP; dual pump mechanism |
| 1983 | AMS 700 Series | PTFE sleeves, front and rear tips and a sutureless connecting system; simplified single inflation and deflation pump; became dominant device |
| 1983 | AMS 600M | Malleable prosthesis with stainless steel wire core and silicone exterior |
| 1985 | AMS Hydroflex | One-piece (unitary) self-contained inflatable rods; saline-filled non-distensible chambers |
| 1987 | AMS 700 CX | Three-ply cylinder (inner silicone, Dacron-Lycra woven fabric, outer silicone); controlled radial expansion; reduced aneurysmal dilation |
| 1990 | AMS 700 CXM | CX design in smaller diameter (9.5–14.2 mm) for smaller anatomy |
| 1990 | AMS Ultrex | First cylinder providing both length and girth expansion; higher initial mechanical failure rates; 1993 modification significantly improved reliability |
| 1994 | AMS Ambicor | Two-piece design; reservoir integrated into scrotal pump |
| 2001 | InhibiZone coating | Minocycline and rifampin surface impregnation; infection at 180 days 0.68% versus 1.61% in uncoated devices in a retrospective comparison; FDA cleared an infection-reduction promotional claim in 2009 [3][26] |
| 2006 | AMS 700 LGX | Combined post-1993 Ultrex cylinder improvements with 700 series; length and girth expansion; penile-length preservation is not assured[24] |
Coloplast Titan
Mentor introduced the Titan inflatable prosthesis in 2002, and Coloplast acquired Mentor's urology business in 2006.[3] The Titan has a hydrophilic coating that absorbs antibiotic solution applied intraoperatively and reduces bacterial adherence, a different infection-prevention strategy from the antibiotic impregnation used by AMS. Later refinements include the Titan Zero Degree (cylinder tubing exiting at a zero-degree angle) and the Titan OTR (one-touch release pump).[6]
In a 2017 review, freedom from revision for mechanical failure of modern three-piece devices exceeded 90%, and overall device survival was in the high 80s (percent) at 3 to 5 years.[6]
Mulcahy Salvage Technique for Infected Prosthesis (1996)
Before the 1996 Mulcahy series, an infected penile prosthesis was generally explanted with reimplantation delayed weeks to months, adding psychological and logistical burdens; Fishman, Scott, and Selim had nevertheless reported immediate salvage at the 1987 AUA meeting.[23] John Mulcahy described immediate prosthesis salvage; the first series, 11 patients, was published in 1996:[21]
- Device removal
- Original Mulcahy washout. The 1996 protocol used kanamycin and bacitracin, then half-strength hydrogen peroxide, half-strength povidone-iodine, saline, vancomycin and gentamicin, followed by the reverse sequence. Modern salvage protocols have omitted steps including hydrogen peroxide.[22]
- Immediate reimplantation
In one immediate inflatable-prosthesis salvage series, 45/55 men (82%) remained infection-free at a mean 35 months; in a separate malleable-prosthesis salvage series, 54/58 (93%) were infection-free at a mean 8.4 months.[25] The technique made immediate reimplantation an option for the most feared prosthesis complication.
Swanton AR, Gross MS, Munarriz RM, Mulcahy JJ. "Penile prosthesis salvage: a historical look at the Mulcahy technique and a review of the latest literature." Int J Impot Res. 2023;35(2):90–94. [PMID: 35027720][7]
The Artificial Urinary Sphincter
Scott, Bradley, and Timm — AMS AS721 and AMS 800 (1972–1983)
The artificial urinary sphincter (AUS) was developed in parallel with the IPP, and slightly before it, by the same Baylor and Minnesota team. The motivating problem was post-prostatectomy urinary incontinence. The same hydraulic principle applied: a circumferential cuff occludes the urethra under controlled pressure and is deflated by a scrotal pump for voiding.
- 1972. AMS founded; the AS 721 designed, with a fluid reservoir, separate inflation and deflation pumps, an inflatable cuff and four one-way valves
- 1973. First clinical report of the AS 721 (Urology, March 1973). The AS 742, introduced about a year after the AS 721, replaced the valves with a pressure-regulating balloon (PRB) that held the cuff at a preset pressure and limited unregulated urethral compression
- 1976. AS 761 introduced with an automatic cuff-closure system; the AS 791 and AS 792 (1979) combined the controls into a single unit
- 1982. AMS 800 introduced (some sources give 1983), with the valves and resistor inside the pump and a deactivation mechanism; Chung's 2024 review describes it as the gold standard for male stress urinary incontinence after more than 40 years of iterative engineering improvements
Scott FB, Bradley WE, Timm GW. "Treatment of urinary incontinence by an implantable prosthetic urinary sphincter." J Urol. 1974;112(1):75–80. [PMID: 4600662]
According to the manufacturer, more than 250,000 AMS artificial urinary sphincters have been sold since 1972. The AMS 800 (now marketed by Boston Scientific) remains the only FDA-approved AUS for male stress urinary incontinence.[8]
Intracavernosal Injection Therapy (1982–1983)
Virag — The Accidental Discovery (1982)
Ronald Virag (Paris) discovered the vasoactive effect of papaverine by accident during an arterial epigastric-cavernous anastomosis procedure, when inadvertent intracavernosal injection of papaverine produced a rigid erection lasting 2 hours. He reported this in a letter:
Virag R. "Intracavernous injection of papaverine for erectile failure." Lancet. 1982 Oct 23;2(8304):938. [PMID: 6126784]
Virag subsequently published the expanded clinical series: Virag R, et al. Angiology. 1984;35(2):79–87. [PMID: 6696289][9]
Giles Brindley — The AUA 1983 Demonstration
A widely retold episode in urological history occurred on April 18, 1983, at the 78th Annual Meeting of the AUA in Las Vegas. British neurophysiologist Giles Brindley (Medical Research Council, London) gave a lecture on cavernosal adrenergic blockade. He had injected himself in his hotel room before the lecture, then lowered his trousers before the audience to display the resulting erection and invited inspection. Klotz, who was in the audience, recalled the drug as papaverine; Brindley's published series used the alpha-blockers phenoxybenzamine and phentolamine.[9][10]
Brindley GS. "Cavernosal alpha-blockade: a new technique for investigating and treating erectile impotence." Br J Psychiatry. 1983;143:332–337. [PMID: 6626852]
The public demonstration changed clinical practice quickly. Together, Virag and Brindley established intracavernosal injection as a practical pharmacological treatment for ED, the first effective drug alternative to prosthesis implantation.[10]
Subsequent pharmacological developments:
- Zorgniotti (1985). Zorgniotti combined papaverine with phentolamine for improved efficacy.[9]
- Adaikan and Ishii (1986). Prostaglandin E1 (PGE1, alprostadil) was introduced as an intracavernosal agent.[9]
- FDA approval of intracavernosal alprostadil (Caverject). July 1995.[27] Pivotal trial: Linet OI, Ogrinc FG. N Engl J Med. 1996;334(14):873–877. [PMID: 8596569]
- MUSE (Medicated Urethral System for Erection, intraurethral alprostadil suppository). FDA approved November 1996.[28] Padma-Nathan H, et al. N Engl J Med. 1997;336(1):1–7. [PMID: 8970933]
Vacuum Erection Devices — Modern Era
Geddings Osbon and the ErecAid (1960s–1982)
Geddings David Osbon (1901–1986) of Augusta, Georgia, was a tire businessman with no formal education beyond the fifth grade. He experienced erectile dysfunction as a side effect of cardiac medication. Drawing on his knowledge of vacuum physics from tire retreading, he developed a vacuum-based erection device he called the Youth Equivalent Device, spending two decades refining it and navigating FDA regulatory requirements.
According to the manufacturer, on October 5, 1982, Osbon received what it describes as the first FDA permission to market a noninvasive impotence treatment product, 22 years after he was told nothing could be done for him.[11]
The first formal clinical validation appeared in:
Nadig PW, Ware JC, Blumoff R. "Noninvasive device to produce and maintain an erection-like state." Urology. 1986;27(2):126–131. [PMID: 3946035]
Of 35 men with organic impotence studied, 32 achieved rigidity sufficient for penetration; 24 of 30 followed long-term reported regular use and satisfaction. By the manufacturer's account, the ErecAid was the most commonly prescribed treatment for erectile dysfunction in the United States by 1991.[11]
The vacuum erection device remains a non-surgical option for ED and is used in penile rehabilitation protocols after radical prostatectomy.
The Sildenafil (Viagra) Revolution (1989–1998)
Accidental Discovery
Pfizer scientists in Sandwich, UK, began a program in 1986 to develop a selective PDE5 inhibitor for angina and hypertension. Compound UK-92,480 (sildenafil citrate) was selected for development in 1989 and entered clinical trials in 1991.[12]
In a clinical program in which Ian Osterloh worked, healthy-volunteer studies in 1992 reported penile erections as a side effect, while the drug's effect on angina proved modest. Pfizer redirected development toward erectile dysfunction, and the first study in men with ED began in late 1993.[12]
By 1997, over 4,500 subjects had received sildenafil, and 21 clinical trials had reported its efficacy. The publication:
Goldstein I, Lue TF, Padma-Nathan H, et al. "Oral sildenafil in the treatment of erectile dysfunction." N Engl J Med. 1998;338(20):1397–1404. [PMID: 9580646]
The FDA approved sildenafil for erectile dysfunction on March 27, 1998.[29] Sildenafil became one of the fastest-selling pharmaceutical products in history.
Mechanism. PDE5 degrades cyclic GMP (cGMP), which mediates smooth muscle relaxation in cavernosal tissue. Sildenafil blocks PDE5, potentiating the nitric oxide–cGMP pathway, but only in the context of sexual stimulation. This physiological selectivity distinguished it from non-selective vasoactive agents.
Subsequent PDE5 inhibitors: vardenafil (Levitra, 2003), tadalafil (Cialis, 2003, with a duration of up to 36 hours and a later once-daily dosing indication), avanafil (Stendra, 2012).[12]
Peyronie's Disease Surgery
First Description: François de la Peyronie (1743)
François Gigot de la Peyronie (1678–1747), first surgeon to King Louis XV of France and a co-founder of the Académie Royale de Chirurgie, provided the first systematic clinical description of the condition bearing his name in 1743. He described three patients with rosary-bead nodules of scar tissue causing upward penile curvature and painful, distorted erection. (Earlier anatomists Fallopius and Vesalius had noted penile curvature in passing c. 1561, but Peyronie provided the first purposeful clinical account.)
de la Peyronie F. "Sur quelques obstacles qui s'opposent à l'éjaculation naturelle de la semence." Mém Acad R Chir. 1743;1:425–434.[13]
Nesbit Corporoplasty (1965)
Reed M. Nesbit (University of Michigan) described excision of elliptical wedges of tunica albuginea opposite the curvature to correct penile deviation in three patients with congenital curvature. The technique was subsequently extended to Peyronie's disease and prosthesis-associated curvature.
Nesbit RM. "Congenital curvature of the phallus: report of three cases with description of corrective operation." J Urol. 1965;93:230–232. [PMID: 14260875]
The Nesbit corporoplasty remains the most widely referenced tunical shortening technique for Peyronie's disease and has been modified many times (Pryor 1979, Essed-Schroeder 1985, Yachia 1990, Lue 16-dot 2002).[14]
Plaque Incision and Grafting
Tom Lue (UCSF) and Ahmed El-Sakka described tunica incision with saphenous vein grafting for severe curvature (1998), a length-preserving approach that corrects curvature without penile shortening. Multiple graft materials have been evaluated in plaque incision and grafting since: saphenous vein, small intestinal submucosa, cadaveric pericardium, bovine pericardium, dermis, and human dura mater.[15]
Xiaflex (Collagenase Clostridium Histolyticum) — FDA Approval (2013)
On December 6, 2013, the FDA approved collagenase clostridium histolyticum (CCH, Xiaflex) for adult men with Peyronie disease, a palpable plaque and a curvature deformity of at least 30 degrees.[30] Approval was based on the IMPRESS I and IMPRESS II Phase III trials (832 treated adult men, up to four treatment cycles). In the pooled post hoc analysis of the 612-man modified intention-to-treat efficacy population, mean curvature improvement at week 52 was 34% (−17.0 ± 14.8°) with CCH versus 18.2% with placebo.[16]
Urinary Catheters
Benjamin Franklin's Flexible Catheter (1752)
Benjamin Franklin (1706–1790) designed a flexible silver catheter in 1752 for his brother John, who had a bladder stone and needed repeated catheterization. Working with a local silversmith, Franklin created a jointed design that was more flexible than the rigid silver tubes then in use.[17]
The Foley Balloon Catheter (1935/1937)
Frederic Eugene Basil Foley, MD (1891–1966), a urologist at Ancker Hospital in St. Paul, Minnesota (trained at Johns Hopkins, graduated 1918), designed the self-retaining balloon catheter bearing his name. Working with rubber chemist R.A. Lees, Foley created prototypes with an inflatable balloon near the catheter tip, retaining catheter position inside the bladder without external taping or strapping. Foley and Lees presented at the AUA national convention in 1935.
Foley FEB. "A hemostatic bag catheter: one-piece latex rubber structure for control of bleeding and drainage following prostatic resection." J Urol. 1937;38:134–139.
Foley lost a patent dispute with the Davol Company, but the catheter carries his name. The C.R. Bard Company of New Jersey began commercial distribution as the Foley catheter.
The Foley catheter became the standard indwelling urinary catheter across medical and surgical specialties.[18]
Penile Vascular Surgery
Vaclav Michal — First Penile Revascularization (1973)
Vaclav Michal (Czechoslovakia) described the first microvascular arterial bypass for penile revascularization in 1973, anastomosing the inferior epigastric artery directly to the corpus cavernosum (Michal I procedure). Later variations used the dorsal penile vein or the dorsal penile artery as the recipient vessel; the Michal II procedure used the dorsal penile artery. Irwin Goldstein trained under Michal and has performed penile revascularization since 1981.[19]
Penile Reconstruction and Phalloplasty
RFFF Phalloplasty — Chang and Hwang (1984)
The modern era of phalloplasty began with Chang and Hwang (China, 1984), who described the radial forearm free flap (RFFF) for total phallic construction, providing thin, pliable, sensate skin in a geometry suited to the requirements of phalloplasty. RFFF phalloplasty became the most frequently used procedure for gender-affirming phallic construction and penile reconstruction after traumatic loss; Monstrey and colleagues (2009) note that it is widely considered the standard technique, although no randomized data prove it.
Chang TS, Hwang WY. "Forearm flap in one-stage reconstruction of the penis." Plast Reconstr Surg. 1984;74(2):251–258. [PMID: 6463150][20]
Key Landmark Publications
| Year | Author(s) | Contribution | PMID |
|---|---|---|---|
| 1937 | Foley FEB | Balloon catheter publication | — |
| 1952 | Goodwin WE, Scott WW | First acrylic penile prosthesis | 13000938 |
| 1966 | Beheri GE | First intracorporeal rods (700+ cases) | 5913185 |
| 1973 | Scott FB et al. | IPP, inflatable prosthesis | 4766860 |
| 1974 | Scott FB et al. | AUS, artificial urinary sphincter | 4600662 |
| 1975 | Small MP et al. | Small-Carrion semi-rigid prosthesis | 1093303 |
| 1982 | Virag R | Papaverine ICI discovery | 6126784 |
| 1983 | Brindley GS | Cavernosal alpha-blockade | 6626852 |
| 1984 | Chang TS, Hwang WY | RFFF phalloplasty | 6463150 |
| 1986 | Nadig PW et al. | Vacuum erection device validation | 3946035 |
| 1996 | Linet OI, Ogrinc FG | Intracavernosal alprostadil | 8596569 |
| 1998 | Goldstein I et al. | Sildenafil Phase III trial | 9580646 |
| 2023 | Swanton AR et al. | Prosthesis salvage technique review | 35027720 |
References
1. Gurtner K, Saltzman A, Hebert K, Laborde E. "Erectile Dysfunction: A Review of Historical Treatments With a Focus on the Development of the Inflatable Penile Prosthesis." Am J Mens Health. 2017;11(3):479–486. doi:10.1177/1557988315596566. Lizza EF, Rosen RC. "Definition and classification of erectile dysfunction: report of the Nomenclature Committee of the International Society of Impotence Research." Int J Impot Res. 1999;11(3):141–143. doi:10.1038/sj.ijir.3900396
2. Bogoras NA. "Ueber die volle plastische Wiederherstellung eines zum Koitus fähigen Penis." Zentralbl Chir. 1936;63:1271–1276. Goodwin WE, Scott WW. "Phalloplasty." J Urol. 1952;68(6):903–908. doi:10.1016/S0022-5347(17)68301-0
3. Rodriguez KM, Pastuszak AW. "A history of penile implants." Transl Androl Urol. 2017;6(Suppl 5):S851–S857. doi:10.21037/tau.2017.04.02. Martinez DR, Terlecki R, Brant WO. "The Evolution and Utility of the Small-Carrion Prosthesis, Its Impact, and Progression to the Modern-Day Malleable Penile Prosthesis." J Sex Med. 2015;12(Suppl 7):423–430. doi:10.1111/jsm.13014
4. Scott FB, Bradley WE, Timm GW. "Management of erectile impotence. Use of implantable inflatable prosthesis." Urology. 1973;2(1):80–82. doi:10.1016/0090-4295(73)90224-0. Mobley DF. "Early history of inflatable penile prosthesis surgery: a view from someone who was there." Asian J Androl. 2015;17(2):225–229. doi:10.4103/1008-682X.140962
5. Small MP, Carrion HM, Gordon JA. "Small-Carrion penile prosthesis: new implant for management of impotence." Urology. 1975;5(4):479–486. doi:10.1016/0090-4295(75)90071-0. Small MP. "The Small-Carrion penile prosthesis: surgical implant for the management of impotence." Sex Disabil. 1978;1(4):282–291. doi:10.1007/BF01101018
6. Chung E. "Penile prosthesis implant: scientific advances and technological innovations over the last four decades." Transl Androl Urol. 2017;6(1):37–45. doi:10.21037/tau.2016.12.06. Wilson SK, Gross MS. "Celebrating 50 years of penile implants." Int J Impot Res. 2023;35(7):596–600. doi:10.1038/s41443-023-00663-y
7. Swanton AR, Gross MS, Munarriz RM, Mulcahy JJ. "Penile prosthesis salvage: a historical look at the Mulcahy technique and a review of the latest literature." Int J Impot Res. 2023;35(2):90–94. doi:10.1038/s41443-021-00515-7
8. Scott FB, Bradley WE, Timm GW. "Treatment of urinary incontinence by an implantable prosthetic urinary sphincter." J Urol. 1974;112(1):75–80. doi:10.1016/s0022-5347(17)59647-0. Scott FB, Bradley WE, Timm GW. "Treatment of urinary incontinence by implantable prosthetic sphincter." Urology. 1973;1(3):252–259. doi:10.1016/0090-4295(73)90749-8. Chung E. "Narrative review: evolution in device technology and advances in surgical techniques on AMS 800 device in the last 50 years." Transl Androl Urol. 2024;13(8):1657–1665. doi:10.21037/tau-23-10. Boston Scientific. AMS 800 Artificial Urinary Sphincter. Accessed October 2026.
9. Virag R. "Intracavernous injection of papaverine for erectile failure." Lancet. 1982;2(8304):938. doi:10.1016/s0140-6736(82)90910-2. Virag R, Frydman D, Legman M, Virag H. "Intracavernous injection of papaverine as a diagnostic and therapeutic method in erectile failure." Angiology. 1984;35(2):79–87. doi:10.1177/000331978403500203. Porst H, Lewis R, Virag R, Goldstein I. "A comprehensive history of injection therapy for erectile dysfunction, 1982–2023." Sex Med Rev. 2024;12(3):419–433. doi:10.1093/sxmrev/qeae020
10. Brindley GS. "Cavernosal alpha-blockade: a new technique for investigating and treating erectile impotence." Br J Psychiatry. 1983;143:332–337. doi:10.1192/bjp.143.4.332. Goldstein I. "The hour lecture that changed sexual medicine: the Giles Brindley injection story." J Sex Med. 2012;9(2):337–342. doi:10.1111/j.1743-6109.2011.02635.x. Klotz L. "How (not) to communicate new scientific information: a memoir of the famous Brindley lecture." BJU Int. 2005;96(7):956–957. doi:10.1111/j.1464-410X.2005.05797.x
11. Nadig PW, Ware JC, Blumoff R. "Noninvasive device to produce and maintain an erection-like state." Urology. 1986;27(2):126–131. doi:10.1016/0090-4295(86)90368-7. Augusta Medical Systems. Creator of vacuum therapy for ED was Geddings David Osbon (manufacturer history). Accessed October 2026.
12. Goldstein I, Lue TF, Padma-Nathan H, et al. "Oral sildenafil in the treatment of erectile dysfunction." N Engl J Med. 1998;338(20):1397–1404. doi:10.1056/NEJM199805143382001. Ghofrani HA, Osterloh IH, Grimminger F. "Sildenafil: from angina to erectile dysfunction to pulmonary hypertension and beyond." Nat Rev Drug Discov. 2006;5(8):689–702. doi:10.1038/nrd2030
13. de la Peyronie F. "Sur quelques obstacles qui s'opposent à l'éjaculation naturelle de la semence." Mém Acad R Chir. 1743;1:425–434. History review: Fuell W, McKnight D, Lewis R, et al. "History of Peyronie's disease: from early descriptions to modern treatments." Sex Med Rev. 2026;14(1):qeaf064. doi:10.1093/sxmrev/qeaf064
14. Nesbit RM. "Congenital curvature of the phallus: report of three cases with description of corrective operation." J Urol. 1965;93:230–232. doi:10.1016/S0022-5347(17)63751-0. Review: Martenstein C, Peruth J, Hamza A. "The role of Nesbit's procedure in surgical reconstruction of penile deviation." GMS Interdiscip Plast Reconstr Surg DGPW. 2012;1:Doc06. doi:10.3205/iprs000006
15. Lue TF, El-Sakka AI. "Venous patch graft for Peyronie's disease. Part I: technique." J Urol. 1998;160(6 Pt 1):2047–2049. doi:10.1097/00005392-199812010-00029. Review: Rice PG, Somani BK, Rees RW. "Twenty Years of Plaque Incision and Grafting for Peyronie's Disease: A Review of Literature." Sex Med. 2019;7(2):115–128. doi:10.1016/j.esxm.2019.01.001
16. Gelbard M, Goldstein I, Hellstrom WJ, et al. "Clinical efficacy, safety and tolerability of collagenase clostridium histolyticum for the treatment of Peyronie disease in 2 large double-blind, randomized, placebo controlled phase 3 studies." J Urol. 2013;190(1):199–207. doi:10.1016/j.juro.2013.01.087. FDA approval December 6, 2013.
17. Franklin B. Letter to John Franklin, 1752. Reprinted in: Bell RD. "Benjamin Franklin's catheter." Urol Dig. 1975. Review: Feneley RC, Hopley IB, Wells PN. "Urinary catheters: history, current status, adverse events and research agenda." J Med Eng Technol. 2015;39(8):459–470. doi:10.3109/03091902.2015.1085600
18. Foley FEB. "A hemostatic bag catheter." J Urol. 1937;38:134–139. doi:10.1016/S0022-5347(17)71935-0. Biographical review: DuBose JJ, Feliciano DV. "Frederic Eugene Basil Foley (1891–1966) and the Foley-type Balloon Catheter." Am Surg. 2023;89(6):2931–2933. doi:10.1177/00031348221088969
19. Michal V, Kramár R, Pospíchal J, Hejhal L. "Direct arterial anastomosis on corpora cavernosa penis in the therapy of erective impotence." Rozhl Chir. 1973;52(9):587–590. [PMID: 4795713]. Michal V, Kramár R, Pospíchal J, et al. "Vascular surgery in the treatment of impotence: its present possibilities and prospects." Czech Med. 1980;3(3):213–217. [PMID: 7438942]. Review: Dicks B, Bastuba M, Goldstein I. "Penile revascularization: contemporary update." Asian J Androl. 2013;15(1):5–9. doi:10.1038/aja.2012.146
20. Chang TS, Hwang WY. "Forearm flap in one-stage reconstruction of the penis." Plast Reconstr Surg. 1984;74(2):251–258. doi:10.1097/00006534-198408000-00014. Review: Monstrey S, Hoebeke P, Selvaggi G, et al. "Penile reconstruction: is the radial forearm flap really the standard technique?" Plast Reconstr Surg. 2009;124(2):510–518. doi:10.1097/PRS.0b013e3181aeeb06
21. Brant MD, Ludlow JK, Mulcahy JJ. "The prosthesis salvage operation: immediate replacement of the infected penile prosthesis." J Urol. 1996;155(1):155–157. doi:10.1016/S0022-5347(01)66580-7
22. Grimaud LW, Barquin DL, Kurnot JA, Adams ES, Lentz AC. "Overcoming barriers to immediate penile implant salvage surgery: a narrative review." Transl Androl Urol. 2024;13(4):613–621. doi:10.21037/tau-23-509
23. Adams ES, Tua-Caraccia RD, Lentz AC. "Narrative review of immediate salvage for penile prosthesis infection." Transl Androl Urol. 2024;13(4):584–595. doi:10.21037/tau-23-277
24. Wallen JJ, Madiraju SK, Wang R, Henry GD. "Implementation of length expanding inflatable penile prosthesis is not sufficient to prevent postsurgical penile shortening." Asian J Androl. 2019;21(1):98–100. doi:10.4103/aja.aja_77_18
25. Lao M, Graydon RJ, Bieniek JM. "Salvage penile prosthetic surgery utilizing temporary malleable implants." Transl Androl Urol. 2017;6(Suppl 5):S806–S812. doi:10.21037/tau.2017.05.12
26. Mulcahy JJ, Köhler TS, Wen L, Wilson SK. "Penile implant infection prevention part II: device coatings have changed the game." Int J Impot Res. 2021;33(8):801–807. doi:10.1038/s41443-020-0338-1
27. U.S. Food and Drug Administration. Clinical Review: Vardenafil Orally Dispersible Tablet, NDA 200179. 2010; tables 1 and 2. https://www.accessdata.fda.gov/drugsatfda_docs/nda/2010/200179Orig1s000MedR.pdf
28. U.S. Food and Drug Administration. Clinical Review: Vardenafil Orally Dispersible Tablet, NDA 200179. 2010; tables 1 and 2. https://www.accessdata.fda.gov/drugsatfda_docs/nda/2010/200179Orig1s000MedR.pdf
29. U.S. Food and Drug Administration. Clinical Review: Vardenafil Orally Dispersible Tablet, NDA 200179. 2010; tables 1 and 2. https://www.accessdata.fda.gov/drugsatfda_docs/nda/2010/200179Orig1s000MedR.pdf
30. U.S. Food and Drug Administration. Xiaflex supplemental biologics license application 125338/61 approval letter. December 6, 2013. https://www.accessdata.fda.gov/drugsatfda_docs/appletter/2013/125338Orig1s0061ltr.pdf