Acute Urinary Retention
Acute urinary retention (AUR) is a urological emergency marked by sudden inability to void, often with suprapubic pain or distress.[1] Immediate management is prompt and complete bladder decompression by catheterization.[1][2] Rapid, complete emptying is generally appropriate for AUR; routine clamping has not shown a clear benefit in the main comparative evidence. Decompression still requires monitoring in high-risk patients.[3]
Part I: Definition, epidemiology, and etiology
Definition and classification
The International Continence Society describes acute retention as an inability to pass urine with a full, palpable or percussible bladder; pain is usual but can be absent.[50] It is distinguished from chronic urinary retention (CUR), for which the AUA non-neurogenic consensus definition uses PVR >300 mL on two or more occasions persisting for ≥6 months.[49]
- Spontaneous AUR has no identifiable precipitant and carries a worse prognosis and higher surgical rates. In the Reten-World survey, 71% of BPH-associated AUR cases were spontaneous.[5]
- Precipitated AUR follows an identifiable event (anesthesia [28.5%], excessive alcohol [18.2%], medications, constipation, UTI) and had higher first-TWOC success in the Reten-World survey (66.3% versus 59.0% for spontaneous AUR).[5]
Epidemiology
AUR predominantly affects men. In a community cohort of 2,115 men aged 40 to 79 in Olmsted County, the incidence was 6.8 per 1,000 person-years and rose with age and symptom severity.[38] In an English hospital registry of 176,046 men older than 45 admitted with first AUR, one-year mortality exceeded that of age-matched men in the general population; the largest relative excess was at ages 45–54.[2][64] A 2012 Medicare claims study found urinary-retention diagnoses in 1,532 per 100,000 female beneficiaries, with neurologic conditions, UTI and prolapse associated with retention.[6]
Etiology
| Category | Common causes |
|---|---|
| Obstructive (most common) | BPH, urethral stricture, bladder-neck contracture, prostate cancer, phimosis, meatal stenosis, blood clots (clot retention), bladder stones |
| Obstructive — female-specific | Pelvic organ prolapse (cystocele, uterine prolapse), uterine leiomyomas (posterior / fundal with retroverted uterus), pelvic masses, urethral diverticulum |
| Infectious / inflammatory | Acute bacterial prostatitis, cystitis, urethritis, vulvovaginitis, herpes simplex (sacral radiculitis), periurethral abscess |
| Pharmacologic | Anticholinergics, alpha-adrenergic agonists (decongestants), opioids, benzodiazepines, NSAIDs, calcium-channel blockers, antihistamines, tricyclic antidepressants |
| Neurologic | Spinal cord injury, cauda equina syndrome, multiple sclerosis, diabetic neuropathy, stroke, Parkinson's disease, Fowler's syndrome (young women) |
| Postoperative | Regional / general anesthesia, pelvic surgery, prolonged immobilization, pain / opioid use |
Fowler's syndrome is a cause of AUR in young women (typically ages 20–30), characterized by impaired urethral sphincter relaxation, large bladder capacity, reduced sensation, and detrusor underactivity. It is associated with polycystic ovary syndrome and may respond to sacral neuromodulation in selected patients. SNM also has a role in other refractory nonobstructive retention phenotypes; published success rates depend on selection and test-phase response.[10][37]
Part II: Initial evaluation
Principle 1 — Rapid assessment before catheterization
While catheterization should not be delayed, a focused assessment guides the approach:[1][7]
- History. Duration of inability to void, pain severity, prior voiding symptoms (LUTS), medication review (anticholinergics, opioids, alpha-agonists, herbal supplements), prior urologic history (strictures, BPH, prior catheterization), and neurologic symptoms (saddle anesthesia, lower-extremity weakness, bowel dysfunction; red flags for cauda equina syndrome).
- Physical examination. Suprapubic palpation / percussion (distended bladder), digital rectal examination (prostate size, tenderness suggesting prostatitis, rectal tone), focused neurologic exam (perineal sensation, anal sphincter tone, lower-extremity reflexes), and pelvic exam in women (prolapse, masses).
- Bladder scanner. The RAND / UCLA expert panel (URECA algorithm) recommends bladder scanning as the preferred diagnostic tool over catheterization for confirming retention. Its adult inpatient thresholds are ≥300 mL when symptomatic and ≥500 mL when asymptomatic, with intermittent catheterization preferred at lower volumes. URECA adult-inpatient thresholds are not universal definitions and do not justify delaying drainage of a clinically urgent obstruction.[13]
- Laboratory and upper-tract assessment. Urinalysis can identify infection or hematuria; serum BUN, creatinine and electrolytes assess renal involvement. Obtain renal/bladder ultrasonography when hydronephrosis or upper-tract disease is suspected.[1]
- Urine indices do not diagnose obstruction. In oliguria or a rising creatinine without an obviously distended bladder, spot urine indices (urine sodium, specific gravity, fractional excretion of sodium or urea, renal failure index) help separate prerenal injury from acute tubular necrosis; in one series of 431 inpatients with AKI, urine sodium, specific gravity and renal failure index were highly specific for prerenal AKI and were not confounded by loop diuretics or ACE inhibition.[46] None of these identifies a postrenal cause; a bladder scan and renal ultrasound do.
Principle 2 — Rule out urethral injury before catheterization
In the trauma setting, urethral catheterization must be preceded by assessment for urethral injury. The ACS Best Practices Guidelines state:[14]
- Abort the procedure if any resistance is encountered during catheter advancement or if urine is not obtained.
- For suspected male urethral injury (meatal blood, perineal hematoma, inability to void or pelvic fracture), consider RUG before catheterization when feasible; a bedside RUG is especially useful with meatal blood and pelvic fracture. For suspected female injury, use cystourethroscopy and pelvic/speculum examination rather than RUG. A high-riding prostate on rectal examination is no longer used to diagnose urethral injury because it is neither sensitive nor specific.[14]
- When a RUG cannot be obtained in time and drainage is needed, a single attempt by an experienced team member with a 16 Fr straight-tip catheter is justified; any resistance or blood calls for urologic consultation.
- A straight-tip Foley catheter is preferred in trauma; coudé-tip catheters are not recommended in this setting.
Part III: Emergent bladder decompression — techniques
Principle 3 — Urethral catheterization: first-line approach
Urethral catheterization is the standard first-line intervention for AUR; in preliminary and final Reten-World cohorts of men with BPH-associated AUR, it was used in 87% and 89.8% of cases, respectively.[2][5]
Standard technique:
- Sterile preparation and draping; if using GLYDO 2% lidocaine jelly, follow its labeled dose and avoid use with lidocaine or amide-anesthetic hypersensitivity, infected or severely traumatized urethral mucosa, severe shock, or heart block. Allow 5–10 minutes after complete instillation for anesthetic effect.[58]
- Catheter size. 14–16 Fr for uncomplicated adult drainage; large-bore hematuria catheter, usually ≥22 Fr, for substantial clot retention when anatomy permits.
- Advance the catheter to the hub (in males) before inflating the balloon; inflating the balloon before it reaches the bladder risks urethral injury.[14]
- Inflate the balloon only after urine is seen draining in the tubing.[14]
- Secure the catheter to the thigh to prevent inadvertent traction / extraction.[14]
The coudé catheter. The coudé (curved-tip) catheter is designed to navigate the upward angulation at the prostatic urethra in men with BPH. Miller et al. reported 18/601 traumatic catheterizations (3.0%) in three surgical services before the program and 4/2,038 (0.2%) across all OR services after the combined nursing-education and coudé-kit program for adult men.[15] This was a single-center before-and-after project.[15] The tip is oriented with the curve facing anteriorly (toward the ceiling in supine patients) to glide over the prostatic obstruction.
Principle 4 — Managing difficult urethral catheterization
When standard catheterization fails, a stepwise escalation algorithm should be followed rather than repeated blind attempts (which cause urethral trauma, false passages, and edema):[16][17]
Step 1 — Optimize the initial attempt:
- Ensure adequate lubrication and anesthesia (lidocaine gel, 5–10 min dwell time).
- Try a coudé-tip catheter if a straight catheter fails.
- Stretch the penis to its full length and hold it perpendicular to the body to straighten the urethra.
- Obesity or a buried penis. Extra assistance to retract the pannus, or a nasal speculum to spread overlying tissue, can expose the meatus; a severe buried penis unresponsive to these maneuvers may need cystoscopy to locate the meatus and place the catheter over a wire.[40]
- Difficult-to-visualize female meatus. A nasal speculum can spread the labia for exposure. If the meatus still cannot be seen, a small coudé-tip catheter can be guided over a finger placed against the anterior vaginal wall to locate the retracted meatus.[55]
- BPH-related retention. An 18 Fr coudé catheter, rather than a smaller one, has more rigidity to negotiate the prostate; perineal pressure from an assistant and steady penile traction to limit lateral tip mobility can help guide the tip through the prostatic urethra.[40]
- Meatal stenosis or fossa navicularis stricture. Use a meatal dilator, or sequential urethral sounds starting with the largest that passes the distal urethra and calibrating to 2 Fr larger than the intended catheter; a disposable urethral dilation balloon is an alternative to serial dilation.[40][56]
Step 2 — Seek experienced assistance and define the obstruction:
- Suspected stricture, false passage or prior urethral surgery favors early flexible cystoscopy rather than repeated blind instrumentation.
- Under direct vision, pass a guidewire into the bladder, then advance an appropriate Council-tip catheter over it.
- Beaghler et al. reported placement in 52/54 patients in a prospective series.[17]
Step 3 — Selected guidewire/device approaches:
- Hydrophilic-wire and integrated devices have been described by experienced operators, including the UCD.[18] They are not a mandatory blind step before cystoscopy. Confirm intravesical wire position; do not force wire or catheter passage.
Step 4 — Fluoroscopy-guided catheterization:
- After failed blind or cystoscopy-assisted catheterization, Kim et al. reported 100% technical and clinical success in 179 procedures in 149 men in a retrospective cohort, with a 2.2% procedure-related complication rate.[19]
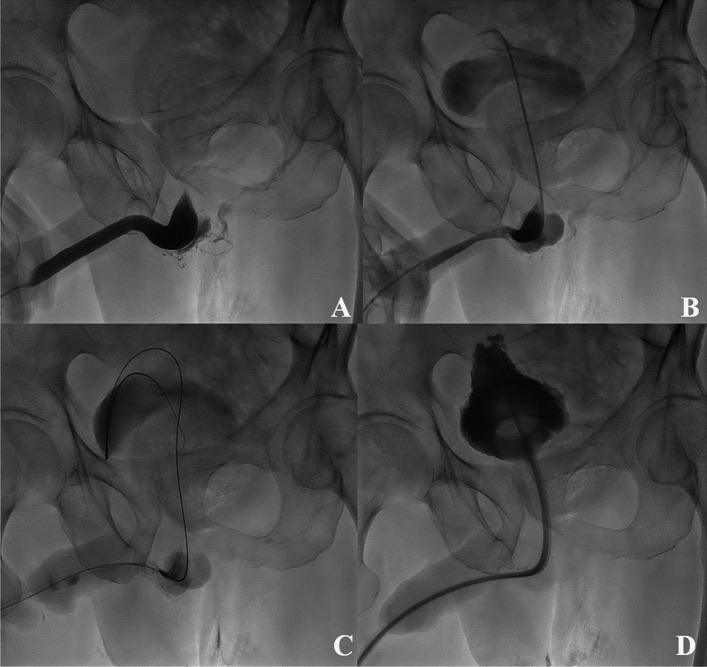
Fluoroscopy-guided urethral catheterization in an 83-year-old man with urinary retention after failed blind catheterization. (A) Retrograde urethrography shows total occlusion of the prostatic urethra and contrast leakage into the venous structures around the bulbar urethra. (B) A 5 Fr guiding catheter and a 0.035-inch hydrophilic guidewire pass the injured and occluded segments, and contrast injection confirms the 5 Fr catheter in the bladder. (C, D) A 20 Fr urethral catheter is placed in the bladder over the wire. From Kim SW, et al. Sci Rep. 2024;14(1):9406, Figure 2 (CC BY).[19]
Step 5 — Suprapubic catheterization (see below).
Principle 5 — Suprapubic catheterization: when urethral access fails or is contraindicated
Suprapubic catheter (SPC) placement is indicated when urethral catheterization fails, is contraindicated, or is not feasible:[20][21][22]
Indications:
- Failed urethral catheterization after stepwise escalation.
- Known urethral disruption (trauma) or complete urethral stricture.
- Acute bacterial prostatitis (relative indication, to avoid urethral manipulation through an infected gland).
- When long-term indwelling drainage is needed, SPC may offer comfort, sexual-function or urethral-protection advantages.[23][24]
Contraindications and precautions:
- A bladder that cannot be adequately distended and safely localized is unsuitable for blind percutaneous insertion.
- Known/suspected bladder cancer and gross hematuria require specialist assessment; EAUN lists both as absolute contraindications to suprapubic catheterization.[35]
- Prior lower-abdominal surgery, pregnancy, anticoagulation/coagulopathy and intervening abdominal-wall infection require individualized access planning; prior surgery is not an absolute ban on all SPC routes.[20][24][35]
Technique — percutaneous (bedside):
- Confirm bladder distension by palpation and ultrasound; Aguilera et al. reported 100% success with real-time ultrasound-guided SPC placement in 17 ED patients with zero complications.[22]
- Entry point: for routine percutaneous SPC, choose a safely imaged midline site above the pubic symphysis; Flynn et al. described puncture 3 cm above the pubis and 1–2 cm off midline for a large-caliber balloon/sheath technique in patients with preserved urethral access.[35][61]
- Choose the entry site and trajectory under imaging according to the visualized bladder and intervening structures; avoid an assumed blind trajectory.
- Goyal et al. reported successful bedside trocar SPC placement in 72 selected men with palpable distended bladders, with no observed complications and average procedure time <5 minutes; 17 other men received different methods because they did not meet the technique criteria.[21]
- Bowel injury is the primary concern, particularly in patients with prior abdominal surgery or an inadequately distended bladder. A national UK audit and meta-analysis estimated the rate at 0.7% (11/1,490 in the pooled studies) and suggested counseling low-risk patients with a risk below 0.25%.[39]
Technique — open cystostomy:
- Open cystostomy is an option when percutaneous SPC access is unsafe, including suspected adhesions after prior pelvic surgery or trauma with a displaced or poorly filled bladder.[14]
- A small infraumbilical midline or transverse incision is made, the rectus muscles are separated, the peritoneum is displaced cephalad, and the bladder is opened between stay sutures.
- A Malecot or Foley catheter is placed through the bladder wall and secured in a long oblique tunnel away from the symphysis.
Suprapubic versus urethral catheterization: In hospitalized-adult trials of intended catheter use for 14 days or less, SPCs were associated with less pain (low certainty), less asymptomatic bacteriuria (very low certainty), and fewer recatheterizations than indwelling urethral catheters; symptomatic UTI evidence was inconclusive (RR 1.01, 95% CI 0.61–1.69; five trials, n = 575).[24] Insertion complications were incompletely reported in short-term trials. In a separate NHS series of 219 cystoscopy-guided SPC insertions, the intraoperative complication-or-difficulty rate was 10%.[24][62]
Part IV: Rapid vs. gradual decompression — the evidence
Principle 6 — Rapid, complete emptying is recommended
The 1997 Nyman review predates randomized evidence.[3] A 294-patient randomized trial subsequently found no significant difference in hematuria (11.3% gradual versus 10.5% rapid) and no circulatory collapse.[32] A 2022 meta-analysis of four studies (435 participants) likewise found no clear increase in hematuria with rapid drainage (RR 0.91, 95% CI 0.62–1.35).[33]
Evidence is less uniform in chronic retention. A 2024 randomized study of 60 patients with CUR reported gross hematuria in 15 of 30 after rapid drainage versus 7 of 30 after gradual drainage (p = 0.032), with no significant difference in transfusion.[34]
The potential complications of decompression are hematuria, hypotension, and postobstructive diuresis; most are self-limited, but substantial bleeding, hypovolemia and pathologic diuresis can be serious:[3]
| Complication | Incidence | Significance | Management |
|---|---|---|---|
| Hematuria (ex vacuo) | 2–16% after quick, complete drainage[3] | Rarely clinically significant; decompression of overdistended mucosal vessels | Usually self-limited; continuous bladder irrigation if persistent; rarely requires intervention |
| Hypotension | Common (transient BP drop) | Usually normalizes spontaneously; rarely progresses to clinically significant hypotension | IV fluid bolus if symptomatic; monitor elderly and hypovolemic patients closely |
| Postobstructive diuresis (POD) | 0.5–52%[3] | Usually physiologic and self-limited (generally about 24 h); pathologic POD (>48 h) is potentially lethal[26] | See Part V below |
Part V: Postobstructive diuresis — recognition and management
Principle 7 — Physiologic vs. pathologic POD
Postobstructive diuresis is defined as urine output ≥200 mL/hour for 2 consecutive hours or >3 L over 24 hours following relief of urinary obstruction.[25][26]
Physiologic POD. Self-limited and self-resolving, usually within 24–48 hours.
- Represents the normal diuretic response to resolution of fluid overload and retained solute load.
Pathologic POD. >48 hours, potentially life-threatening.
- Results from intrinsic tubular damage caused by prolonged obstruction.
- Pathophysiology:[25][27][28]
- Medullary washout. Loss of the corticomedullary concentration gradient.
- Downregulation of sodium transporters in the thick ascending limb of Henle.
- Resistance to ADH (nephrogenic diabetes insipidus-like state).
- Osmotic diuresis from retained urea.
- Natriuresis from impaired tubular sodium reabsorption.
- Can lead to severe dehydration, electrolyte derangements (hyponatremia, hypokalemia, hypomagnesemia), hypotension, and shock if not recognized and treated.[25][26]
Risk factors for pathologic POD:
- Bilateral ureteral obstruction or obstruction of a solitary kidney.
- Chronic retention with renal insufficiency (elevated BUN / creatinine).
- Volume overload, CHF, or edematous states.
- Prolonged duration of obstruction.[26]
A 2025 review pooling nine studies (665 patients) found postobstructive diuresis in 15–78% of patients, lasting a mean of 2–5 days. In one 64-patient study included in the review, a serum creatinine above 105 μmol/L (about 1.2 mg/dL; OR 4.83, 95% CI 1.14–20.44) and larger decompressed bladder volume (OR 1.21 per 100 mL increment, 95% CI 1.06–1.40) were associated with postobstructive diuresis; across the reviewed studies, reported complications were hematuria (11–55%), hyponatremia (22–28%) and hypotension (9%), most self-limited. One included randomized trial found no significant difference in complications between rapid and gradual decompression.[47]
Principle 8 — Management of POD
- Monitor urine output hourly for the first 24–48 hours after decompression in high-risk patients (chronic retention, elevated creatinine, bilateral obstruction).
- Characterize the diuresis with urine sodium, potassium, and osmolality. A spot urine sodium >40 mEq/L suggests tubular injury and risk of prolonged salt-wasting POD. Specific gravity can approximate osmolality but may mislead in uncontrolled diabetes mellitus, nephrotic syndrome, saline diuresis, or after IV radiocontrast.[26][41][42]
- Replace fluids according to volume status and serial electrolytes. In initially volume-overloaded patients, narrative reviews describe replacing 50% of the prior hour's urine output intravenously or about 75% of the prior hour's output (the latter Level III evidence), with oral intake when feasible and a net negative fluid balance; individualize replacement to volume status and electrolytes.[59][26] Fluid composition and rate must be individualized; hypovolemia or shock requires appropriate resuscitation. Halbgewachs and Domes suggest 0.45% saline for cognitively impaired patients, while pathologic POD requires IV fluid tailored to volume status and electrolytes.[26][27]
- Monitor electrolytes (Na, K, Mg, phosphate) every 6–12 hours during active diuresis.
- Avoid overzealous fluid replacement. Excess replacement can perpetuate the diuresis.[27]
- Taper IV fluids as urine output decreases; transition to oral intake as tolerated.
- Nephrology consultation for pathologic POD lasting >48 hours or associated with hemodynamic instability.[25]
Part VI: Post-decompression management — trial without catheter (TWOC)
Principle 9 — Alpha-blocker therapy before TWOC
The Cochrane review rated its pooled evidence moderate quality, while the later EAU-panel review rated the agent-specific comparisons low certainty; both found that alpha-1 blockers increase TWOC success rates in men with presumed benign prostatic obstruction:[29][30]
- Alfuzosin. TWOC success 60% versus 39% placebo (OR 2.28, 95% CI 1.55–3.36; 7 RCTs, 940 patients).[29]
- Tamsulosin. TWOC success 47% versus 29% placebo (OR 2.40, 95% CI 1.29–4.45; 3 RCTs, 297 patients).[29]
- Alpha-blockers doubled the odds of successful TWOC in the Reten-World survey (OR 1.92, 95% CI 1.52–2.42).[5]
- Head-to-head alfuzosin versus tamsulosin evidence is very low certainty.[29]
- Reported adverse-event rates were low, but trial evidence was limited; assess dizziness, hypotension and falls risk.[30]
Principle 10 — Timing and conduct of TWOC
- For AUR attributed to LUTS/BPH, the 2026 AUA guideline states that a uroselective alpha blocker be taken for at least three days before TWOC .[67] Individualize timing to the cause, stabilization and catheter-related injury. Reten-World used a median of five days.[5] A 2024 systematic review of adult men with nontraumatic AUR found low-certainty comparative evidence favoring neither immediate nor delayed TWOC (two RCTs, n = 174; RR 1.22, 95% CI 0.84–1.76).[52] After a successful BPH-related TWOC, counsel that retention can recur .[67]
- In the observational Reten-World survey, catheterization >3 days was associated with greater morbidity without higher TWOC success.
- TWOC success. An earlier review reported 23–40% after catheter removal at 1–3 days; the final Reten-World survey reported 61.4% first-TWOC success after a median of five days in men with BPH-associated AUR, 85.9% of whom received alpha-blockers.[2][31][5]
- Predictors of TWOC failure. Age ≥70, prostate ≥50 g, severe LUTS, drained volume ≥1,000 mL, spontaneous (versus precipitated) AUR.[5]
- After failed TWOC. 49% undergo BPH surgery; 43.5% attempt a second TWOC (success rate 29.5%).[5]
Principle 11 — Surgical management after failed TWOC
Emergency surgery (within days of AUR) carries greater morbidity and mortality than elective surgery and is discouraged.[2][23] Current practice favors:
- Elective outlet surgery. Recurrent or refractory retention and upper-tract dilation due to benign prostatic obstruction, with or without renal insufficiency, are surgical indications in the 2026 EAU guideline.[60] Select TURP, enucleation or another appropriate procedure according to prostate anatomy, comorbidity, goals and expertise.[23]
- Laser enucleation (HoLEP, ThuLEP) is an increasingly used option; detailed selection is covered in the BPH treatment atlas.[23]
- Clean intermittent self-catheterization (CISC) may be a safe and useful option for men with acute urinary retention until definitive management.[23]
Part VII: Special populations
Clot retention
Clot retention is a specific form of AUR caused by blood clots obstructing the bladder outlet or catheter. Management requires:
- Large-bore hematuria catheter. Usually ≥22 Fr; a 3-way catheter allows subsequent irrigation and manual clot evacuation.
- Continuous bladder irrigation. Use normal saline, started only after clots have been cleared by manual or mechanical evacuation; irrigating a clot-obstructed bladder before the outlet is cleared can overdistend the bladder against the obstruction and cause perforation.
- If manual irrigation fails, cystoscopy with clot evacuation and fulguration of bleeding sources, positioned as for standard operative cystoscopy (dorsal lithotomy; see Endoscopy). The 3-way catheter and continuous irrigation are typically left running postprocedure until the effluent clears, then weaned.
- Identify and treat the underlying cause (bladder tumor, radiation cystitis, anticoagulation).
- VTE prophylaxis. For cystoscopic clot evacuation, assess patient and procedure thrombotic risk alongside active bleeding when selecting prophylaxis; the 2024 ESAIC urology guideline uses individualized assessment for urologic procedures requiring prophylaxis decisions (see VTE Prophylaxis).[63]
Acute bacterial prostatitis with retention
Drain clinically significant retention. The URECA catheterization thresholds of ≥300 mL for symptomatic and ≥500 mL for asymptomatic adult inpatients are not a validated prostatitis-specific rule.[13] Suprapubic drainage avoids manipulation through the infected gland; urethral catheterization is the more widely available option.
Neurogenic bladder
New urinary retention with saddle sensory change, bowel dysfunction or new leg weakness raises concern for cauda equina syndrome and warrants urgent spinal MRI and spine/neurosurgical assessment.[51] Patients with AUR from other neurologic causes, including spinal cord injury or MS, require treatment of the cause and risk-based follow-up.[1] Intermittent catheterization is preferred when ongoing assisted emptying is needed and feasible.[1] Acute prolonged bladder overdistension from undetected retention (e.g., after regional anesthesia or prolonged labor) can cause irreversible detrusor damage; vigilant monitoring is needed.[12]
Women with AUR
AUR in women is uncommon and warrants thorough evaluation for:[4][7][8][10][11]
- Pelvic organ prolapse (associated with retention in Medicare claims data).[6]
- Uterine leiomyomas (especially posterior / fundal with retroverted uterus) can compress the urethra or pelvic plexus.[8]
- Fowler's syndrome (young women with impaired urethral relaxation).[10]
- Neurologic causes should be assessed when acute retention accompanies new neurologic signs.[1]
- Psychological and functional neurologic comorbidity may complicate assessment; a cross-sectional series included 91 women with chronic idiopathic retention.[54]
- Postpartum retention after vaginal or cesarean delivery may be overt (inability to void) or covert (elevated postvoid residual after a spontaneous void). In one vaginal-delivery cohort, 347/745 women (47%) had covert retention, defined as postvoid residual ≥150 mL after the first void.[43][53] Observational studies associate epidural analgesia, longer labor, episiotomy, instrumental delivery, nulliparity, induction or augmentation, and perineal injury with postpartum retention.[44] In a vaginal-delivery cohort, higher birth weight was associated specifically with covert retention.[43] In a separate prospective cohort of covert retention after vaginal delivery, 92% regained adequate emptying within four days, and lower urinary tract symptoms at one year did not differ significantly between 119 women with covert retention and 105 controls.[45] A 2023 expert-review protocol proposes continued intermittent or indwelling drainage for retention persisting beyond postpartum day three and specialist follow-up when unresolved at discharge.[65] In a multicenter randomized trial of 85 women with overt retention after vaginal delivery, intermittent catheterization shortened median catheter duration from 24 to 12 hours (p < 0.01); among the 68 who completed three-month UDI-6 follow-up, bothersome micturition symptoms did not differ significantly between groups.[48] A later RCT randomized 147 patients with bladder volume >150 mL within six hours of vaginal or cesarean delivery to catheterization every six hours (up to four times) or a 24-hour indwelling catheter; intermittent catheterization shortened mean time to retention resolution (10.2 versus 26.5 hours), with no detected UTI difference.[53]
Part VIII: Catheter selection and infection prevention
| Catheter type | Advantages | Disadvantages | Best indication |
|---|---|---|---|
| Urethral indwelling (Foley) | Widely available; requires trained insertion and safe balloon positioning | UTI risk increases with duration; urethral trauma; patient discomfort | Short-term AUR management; perioperative use |
| Suprapubic catheter | In short-term trials, less pain and asymptomatic bacteriuria than indwelling urethral catheters; easier hygiene; avoids transurethral instrumentation | Requires trained placement; bowel-injury risk (about 0.7% in pooled studies); requires a safely localized bladder; symptomatic UTI advantage is unproven[24][39] | Failed urethral catheterization; selected long-term catheterization; urethral injury |
| Clean intermittent catheterization | Patient autonomy; avoids a continuously indwelling catheter; infection risk depends on setting | Requires dexterity and training; multiple daily insertions | Neurogenic bladder; bridge to surgery; chronic retention |
| Coudé-tip catheter | Navigates prostatic urethra; traumatic catheterization was 18/601 (3.0%) in three surgical services before and 4/2,038 (0.2%) across all OR services after a combined education and coudé-kit program[15] | Requires proper orientation technique | Selected difficult male catheterization or BPH; local trained protocol |
Infection prevention:
- Antimicrobial and antiseptic-impregnated catheters. Routine use has not shown a clinically important symptomatic UTI benefit; the CDC recommends considering them if CAUTI rates persist despite a comprehensive prevention strategy (Category IB).[1][66]
- Maintain a closed drainage system for an indwelling catheter and remove it as soon as clinically indicated; CAUTI risk increases with catheter duration.[20][35]
- Bacteriuria develops at approximately 3–7% per catheter day; catheter-associated asymptomatic bacteriuria generally does not require antibiotics, except during pregnancy or before selected invasive urologic procedures.[36]
Summary — stepwise approach to AUR and emergent decompression
- Confirm retention. Assess symptoms and scan; URECA uses ≥300 mL for symptomatic and ≥500 mL for asymptomatic adult inpatients.[13]
- Assess for urethral injury in trauma before blind catheterization: use RUG for suspected male injury and cystourethroscopy with pelvic examination for suspected female injury.[14]
- Urethral catheterization. Sterile technique and lidocaine gel; for routine male placement, a 16 Fr straight catheter is described, with a coudé for selected difficult placement when urethral injury is not suspected. Inflate the balloon only after urine drains and the catheter is fully inserted.[15][14][57]
- Rapid, complete decompression. No clamping; drain the bladder fully.[3]
- Monitor for POD. In patients at risk, consider 24-hour observation with urine output recorded every 2 hours and electrolytes checked every 12–24 hours. If POD develops, monitor more closely and tailor fluid replacement to volume status and electrolytes; replacing about 75% of the preceding hour’s output is a level-III starting approach that targets a negative fluid balance.[26]
- Start an alpha-blocker for presumed BPH-related AUR, if suitable.[29][30]
- Plan TWOC after stabilization and appropriate alpha-blocker exposure. Individualize timing and assess voiding.[2][5]
- If TWOC fails. Recatheterize, then elective surgery (TURP / laser) or second TWOC attempt.[5]
- If urethral catheterization fails. Escalate stepwise (trained coudé attempt when appropriate, then visualized guidewire/cystoscopy or image-guided access, then suprapubic drainage when needed).[16][17]
See Also
- Endoscopy (Cystoscopy & Ureteroscopy): cystoscopy technique for difficult catheterization and BNC / VUAS management.
- Urethral Stricture Disease: when stricture is the AUR cause.
- Pelvic Organ Prolapse: POP as a common female obstructive cause.
- Neurogenic Lower Urinary Tract Dysfunction: long-term CIC framework.
References
1. Serlin DC, Heidelbaugh JJ, Stoffel JT. "Urinary retention in adults: evaluation and initial management." Am Fam Physician. 2018;98(8):496–503. PMID 30277739
2. Emberton M, Fitzpatrick JM. "The Reten-World survey of the management of acute urinary retention: preliminary results." BJU Int. 2008;101(Suppl 3):27–32. doi:10.1111/j.1464-410X.2008.07491.x
3. Nyman MA, Schwenk NM, Silverstein MD. "Management of urinary retention: rapid versus gradual decompression and risk of complications." Mayo Clin Proc. 1997;72(10):951–956. doi:10.1016/S0025-6196(11)63368-5
4. Andrada AO, De Vicente JM, Cidre MA. "Pelvic plexus compression due to a uterine leiomyoma in a woman with acute urinary retention: a new hypothesis." Int Urogynecol J. 2014;25(3):429–431. doi:10.1007/s00192-013-2158-z
5. Fitzpatrick JM, Desgrandchamps F, Adjali K, et al. "Management of acute urinary retention: a worldwide survey of 6074 men with benign prostatic hyperplasia." BJU Int. 2012;109(1):88–95. doi:10.1111/j.1464-410X.2011.10430.x
6. Cohn JA, Ni S, Kaufman MR, et al. "Urinary retention and catheter use among U.S. female Medicare beneficiaries: prevalence and risk factors." Neurourol Urodyn. 2017;36(8):2101–2108. doi:10.1002/nau.23248
7. Selius BA, Subedi R. "Urinary retention in adults: diagnosis and initial management." Am Fam Physician. 2008;77(5):643–650. PMID 18350762
8. Wu CQ, Lefebvre G, Frecker H, Husslein H. "Urinary retention and uterine leiomyomas: a case series and systematic review of the literature." Int Urogynecol J. 2015;26(9):1277–1284. doi:10.1007/s00192-015-2665-1
9. Borgert BJ, Wallen EM, Pham MN. "Prostatitis." JAMA. 2025;334(11):1003–1013. doi:10.1001/jama.2025.11499
10. Szymański JK, Słabuszewska-Jóźwiak A, Jakiel G. "Fowler's syndrome — the cause of urinary retention in young women, often forgotten, but significant and challenging to treat." Int J Environ Res Public Health. 2021;18(6):3310. doi:10.3390/ijerph18063310
11. Panicker JN, Anding R, Arlandis S, et al. "Do we understand voiding dysfunction in women? Current understanding and future perspectives: ICI-RS 2017." Neurourol Urodyn. 2018;37(S4):S75–S85. doi:10.1002/nau.23709
12. Madersbacher H, Cardozo L, Chapple C, et al. "What are the causes and consequences of bladder overdistension? ICI-RS 2011." Neurourol Urodyn. 2012;31(3):317–321. doi:10.1002/nau.22224
13. Chrouser K, Fowler KE, Mann JD, et al. "Urinary retention evaluation and catheterization algorithm for adult inpatients." JAMA Netw Open. 2024;7(7):e2422281. doi:10.1001/jamanetworkopen.2024.22281
14. Johnsen N, Wessells H, Archer-Arroyo K, et al. Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons; 2025.
15. Miller D, Pelzman D, Bonfili J, et al. "Implementation of a standardized process of coudé catheter insertion decreases traumatic catheterizations." Urology. 2024;194:253–259. doi:10.1016/j.urology.2024.10.016
16. Willette PA, Coffield S. "Current trends in the management of difficult urinary catheterizations." West J Emerg Med. 2012;13(6):472–478. doi:10.5811/westjem.2011.11.6810
17. Beaghler M, Grasso M, Loisides P. "Inability to pass a urethral catheter: the bedside role of the flexible cystoscope." Urology. 1994;44(2):268–270. doi:10.1016/s0090-4295(94)80148-7
18. Bugeja S, Mistry K, Yim IHW, et al. "A new urethral catheterisation device (UCD) to manage difficult urethral catheterisation." World J Urol. 2019;37(4):595–600. doi:10.1007/s00345-018-2499-9
19. Kim SW, Nam IC, Kim DR, et al. "Safety and efficacy of fluoroscopy-guided urethral catheterization in case of failed blind or cystoscopy-assisted urethral catheterization." Sci Rep. 2024;14(1):9406. doi:10.1038/s41598-024-60224-1
20. Fletke KJ, Jeong DH, Herrera AV. "Urinary catheter management." Am Fam Physician. 2024;110(3):251–258. PMID 39283848
21. Goyal NK, Goel A, Sankhwar SN. "Safe percutaneous suprapubic catheterisation." Ann R Coll Surg Engl. 2012;94(8):597–600. doi:10.1308/003588412X13373405385412
22. Aguilera PA, Choi T, Durham BA. "Ultrasound-guided suprapubic cystostomy catheter placement in the emergency department." J Emerg Med. 2004;26(3):319–321. doi:10.1016/j.jemermed.2003.11.016
23. Yoon PD, Chalasani V, Woo HH. "Systematic review and meta-analysis on management of acute urinary retention." Prostate Cancer Prostatic Dis. 2015;18(4):297–302. doi:10.1038/pcan.2015.15
24. Kidd EA, Stewart F, Kassis NC, Hom E, Omar MI. "Urethral (indwelling or intermittent) or suprapubic routes for short-term catheterisation in hospitalised adults." Cochrane Database Syst Rev. 2015;(12):CD004203. doi:10.1002/14651858.CD004203.pub3
25. Finger E, Moses A. "As the river flows: a case report of post-obstructive diuresis." BMC Nephrol. 2025;26(1):341. doi:10.1186/s12882-025-04215-y
26. Halbgewachs C, Domes T. "Postobstructive diuresis: pay close attention to urinary retention." Can Fam Physician. 2015;61(2):137–142. PMID 25821871
27. Peterson LJ, Yarger WE, Schocken DD, Glenn JF. "Post-obstructive diuresis: a varied syndrome." J Urol. 1975;113(2):190–194. doi:10.1016/s0022-5347(17)59440-9
28. Baum N, Anhalt M, Carlton CE, Scott R. "Post-obstructive diuresis." J Urol. 1975;114(1):53–56. doi:10.1016/s0022-5347(17)66942-8
29. Karavitakis M, Kyriazis I, Omar MI, et al. "Management of urinary retention in patients with benign prostatic obstruction: a systematic review and meta-analysis." Eur Urol. 2019;75(5):788–798. doi:10.1016/j.eururo.2019.01.046
30. Fisher E, Subramonian K, Omar MI. "The role of alpha blockers prior to removal of urethral catheter for acute urinary retention in men." Cochrane Database Syst Rev. 2014;(6):CD006744. doi:10.1002/14651858.CD006744.pub3
31. Fitzpatrick JM, Kirby RS. "Management of acute urinary retention." BJU Int. 2006;97(Suppl 2):16–22. doi:10.1111/j.1464-410X.2006.06100.x
32. Boettcher S, Brandt AS, Roth S, Mathers MJ, Lazica DA. Urinary retention: benefit of gradual bladder decompression—myth or truth? A randomized controlled trial. Urol Int. 2013;91:140–144. doi:10.1159/000350943.
33. Wu MY, Chang JR, Lee YK, et al. The Effect and Safety of Rapid and Gradual Urinary Decompression in Urine Retention: A Systematic Review and Meta-Analysis. Medicina. 2022;58(10):1441. PubMed. doi:10.3390/medicina58101441
34. Odeyemi PO, Idowu NA. Comparison of post-decompressive haematuria in rapid versus gradual bladder decompression in patients with chronic urinary retention. J West Afr Coll Surg. 2024;14(3):249–254. doi:10.4103/jwas.jwas_5_24.
35. European Association of Urology Nurses. Indwelling catheterisation in adults—urethral and suprapubic. 2024. Indications and contraindications.
36. Centers for Disease Control and Prevention. Indwelling urinary catheter culture stewardship: overview. Guidance.
37. European Association of Urology. Non-neurogenic Female LUTS Guidelines: underactive bladder and functional obstruction. 2026. Guideline.
38. Jacobsen SJ, Jacobson DJ, Girman CJ, et al. "Natural history of prostatism: risk factors for acute urinary retention." J Urol. 1997;158(2):481–487. doi:10.1016/s0022-5347(01)64508-7
39. Hall S, Ahmed S, Reid S, et al. "A national UK audit of suprapubic catheter insertion practice and rate of bowel injury with comparison to a systematic review and meta-analysis of available research." Neurourol Urodyn. 2019;38(8):2194–2199. doi:10.1002/nau.24114
40. Villanueva C, Hemstreet GP 3rd. "Difficult male urethral catheterization: a review of different approaches." Int Braz J Urol. 2008;34(4):401–411. doi:10.1590/s1677-55382008000400002
41. Voinescu GC, Shoemaker M, Moore H, et al. "The relationship between urine osmolality and specific gravity." Am J Med Sci. 2002;323(1):39–42. doi:10.1097/00000441-200201000-00007
42. Echeverry G, Hortin GL, Rai AJ. "Introduction to urinalysis: historical perspectives and clinical application." Methods Mol Biol. 2010;641:1–12. doi:10.1007/978-1-60761-711-2_1
43. Mulder FE, Oude Rengerink K, van der Post JA, et al. "Delivery-related risk factors for covert postpartum urinary retention after vaginal delivery." Int Urogynecol J. 2016;27(1):55–60. doi:10.1007/s00192-015-2768-8
44. Li L, Chen Q, Li H, et al. "Risk factors for postpartum urinary retention: an updated systematic review and meta-analysis." Int J Gynaecol Obstet. 2025;168(1):10–24. doi:10.1002/ijgo.15802
45. Mulder FEM, Hakvoort RA, de Bruin JP, et al. "Long-term micturition problems of asymptomatic postpartum urinary retention: a prospective case-control study." Int Urogynecol J. 2018;29(4):481–488. doi:10.1007/s00192-017-3457-6
46. Buckenmayer A, Siebler N, Haas CS. "Evaluation of simple diagnostic parameters in acute kidney injury in hospitalized patients—diagnostic recommendations for non-nephrologists." Intern Emerg Med. 2023;18(6):1769–1776. doi:10.1007/s11739-023-03365-x
47. Rigonalli U, Sigg S, Moos SV, et al. "Prevalence and clinical implications of post-obstruction hyperdiuresis among patients with urinary retention: a mini review." Eur Urol Open Sci. 2025;73:68–70. doi:10.1016/j.euros.2025.01.017
48. Mulder FEM, Hakvoort RA, de Bruin JP, van der Post JAM, Roovers JWR. "Comparison of clean intermittent and transurethral indwelling catheterization for the treatment of overt urinary retention after vaginal delivery: a multicentre randomized controlled clinical trial." Int Urogynecol J. 2018;29(9):1281–1287. doi:10.1007/s00192-017-3452-y
49. Stoffel JT, Peterson AC, Sandhu JS, Suskind AM, Wei JT, Lightner DJ. "AUA white paper on nonneurogenic chronic urinary retention: consensus definition, treatment algorithm, and outcome end points." J Urol. 2017;198(1):153-160. doi:10.1016/j.juro.2017.01.075
50. International Continence Society. "Urinary Retention." ICS Terminology Discussions. Updated June 2018. https://www.ics.org/committees/standardisation/terminologydiscussions/urinaryretention
51. Hennessy O, Devitt AT, Synnott K, Timlin M. "Assessment and early investigation of cauda equina syndrome- a systematic review of existing international guidelines and summary of the current evidence." Eur Spine J. 2025;34(4):1545-1551. doi:10.1007/s00586-025-08732-0
52. Christensen VS, Skow M, Flottorp SA, et al. "Immediate or delayed trial without catheter in acute urinary retention in males: a systematic review." BJUI Compass. 2024;5(8):846-861. doi:10.1002/bco2.369
53. Bachar G, Siegler Y, Kabakov E, et al. "Intermittent vs continuous catheterization for postpartum urinary retention: a multicenter randomized controlled trial." Am J Obstet Gynecol MFM. 2023;5(10):101084. doi:10.1016/j.ajogmf.2023.101084
54. Selai C, Lee CH, Simeoni S, et al. "High prevalence of psychological comorbidities and functional neurological symptoms in women with urinary retention." J Urol. 2024;212(1):136-144. doi:10.1097/JU.0000000000003983
55. Bianchi A, Leslie SW, Chesnut GT. "Difficult Foley Catheterization." StatPearls [Internet]. StatPearls Publishing; updated July 15, 2026. NCBI Bookshelf. PMID:33232074.
56. Bianchi A, Leslie SW, Chesnut GT. "Difficult Foley Catheterization." StatPearls [Internet]. StatPearls Publishing; updated July 15, 2026. NCBI Bookshelf. PMID:33232074.
57. Bianchi A, Leslie SW, Chesnut GT. "Difficult Foley Catheterization." StatPearls [Internet]. StatPearls Publishing; updated July 15, 2026. NCBI Bookshelf. PMID:33232074.
58. DailyMed. GLYDO (lidocaine hydrochloride jelly USP, 2%) prescribing information. Revised May 2025. Product label.
59. Yaxley J, Yaxley W. "Obstructive uropathy – acute and chronic medical management." World J Nephrol. 2023;12(1):1–9. doi:10.5527/wjn.v12.i1.1.
60. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026. Disease management.
61. Flynn KJ, Schlaepfer CH, Khawaja F, Erickson BA. "Nephrostomy balloon and sheath suprapubic tube placement—a minimally invasive approach to large caliber suprapubic tube placement." Urology. 2022;164:e302. doi:10.1016/j.urology.2022.03.013
62. Ahluwalia RS, Johal N, Kouriefs C, Kooiman G, Montgomery BSI, Plail RO. "The surgical risk of suprapubic catheter insertion and long-term sequelae." Ann R Coll Surg Engl. 2006;88(2):210–213. doi:10.1308/003588406X95101
63. Tikkinen KAO, Cartwright R, Jensen AG, Violette PD. "European guidelines on peri-operative venous thromboembolism prophylaxis: first update. Chapter 12: Urology." Eur J Anaesthesiol. 2024;41(8):618–621. doi:10.1097/EJA.0000000000002012
64. Armitage JN, Sibanda N, Cathcart PJ, Emberton M, van der Meulen JHP. "Mortality in men admitted to hospital with acute urinary retention: database analysis." BMJ. 2007;335(7631):1199–1202. doi:10.1136/bmj.39377.617269.55
65. Nutaitis AC, Meckes NA, Madsen AM, et al. "Postpartum urinary retention: an expert review." Am J Obstet Gynecol. 2023;228(1):14–21. doi:10.1016/j.ajog.2022.07.060
66. Centers for Disease Control and Prevention. "Summary of Recommendations: Guideline for Prevention of Catheter-Associated Urinary Tract Infections (2009)." Updated March 25, 2024. Guideline.
67. Goueli R, Badlani GH, Welliver C, et al. "Management of Lower Urinary Tract Symptoms Attributed to Benign Prostatic Hyperplasia: AUA Guideline (2026) Part III: Procedural/Surgical Management." J Urol. 2026;216(2):161–170. doi:10.1097/JU.0000000000005099