Necrotizing Fasciitis / Fournier's Gangrene
Fournier's gangrene (FG) is a necrotizing soft tissue infection (NSTI) of the perineal, genital or perianal region and is a surgical emergency. Treatment is prompt recognition, resuscitation, broad-spectrum antibiotics and urgent, often repeated debridement.[13][8] Infection is often polymicrobial but may be monomicrobial. Skin preservation is appropriate only when it preserves viable tissue without compromising source control.
Epidemiology
- A US National Inpatient Sample analysis for 2016–2020 identified 9,326 unweighted admissions: 2,875 women (31%) and 6,451 men (69%). In-hospital mortality was 7.1% versus 5.7%, respectively. Median annual incidence estimates were 1.7 per 100,000 women and 4.0 per 100,000 men.[2]
- Mortality is higher in many referral cohorts; case mix, shock, comorbidity and delayed source control affect outcomes.[1]
- An older population study of 1,641 men at 593 hospitals found lower adjusted mortality at hospitals treating more FG cases.[7]
Pathophysiology
FG often arises from polymicrobial infection that spreads rapidly along fascial planes.[1] Common source sites include:
- Anorectal: anorectal abscess, anal fistula, rectal perforation
- Urogenital: urethral stricture, periurethral abscess, catheter trauma, urinary extravasation
- Cutaneous: trauma, pressure ulcer, surgical wound
The hallmark is obliterative endarteritis of subcutaneous vessels causing ischemic fascial necrosis with gas production, spreading rapidly along Colles', Scarpa's, and Dartos fascial planes. The rich and redundant vasculature of the skin means cutaneous manifestations may appear much later than deep tissue necrosis: intact overlying skin may overlie extensively necrotic subcutaneous tissue, yet remain histologically viable and salvageable.[1][3] This underpins the modern skin-sparing surgical approach.
Infection can spread along Dartos fascia. The testes are commonly spared because their arterial supply arises separately through the spermatic cords, rather than from the scrotal skin circulation.
Microbiology
FG is polymicrobial in approximately 58% of cases; monomicrobial infection is documented in approximately 30%.[1] Mixed aerobic-anaerobic synergism is common.
| Category | Common Organisms |
|---|---|
| Aerobic gram-positive | Staphylococcus aureus (including MRSA), Streptococcus spp. (Group A), Enterococcus faecium |
| Aerobic gram-negative | Escherichia coli (most frequent overall), Klebsiella pneumoniae, Pseudomonas aeruginosa, Proteus spp. |
| Anaerobic | Bacteroides fragilis, Fusobacterium spp., Clostridium spp., Peptostreptococcus spp. |
Less Common Isolates.
MRSA and Acinetobacter have been reported among FG isolates.[1] Culture results should prompt early de-escalation or targeted therapy as sensitivities return.[1]
Risk Factors
| Category | Risk Factors |
|---|---|
| Metabolic | Diabetes mellitus (most common; 40–70% of cases in the literature reviewed by Inácio et al.[25]), obesity, malnutrition |
| Immunosuppression | HIV/AIDS, malignancy, corticosteroids, chemotherapy, organ transplant |
| Vascular | Peripheral vascular disease, chronic venous insufficiency |
| Local predisposing | Urethral stricture, perianal abscess, anorectal fistula, urinary instrumentation, trauma |
| Behavioral | Alcohol use disorder, intravenous drug use |
| Novel | In one retrospective cohort of 185 operated FG patients, CT-defined sarcopenia was independently associated with one-year postoperative mortality.[1][27] |
| Medication | SGLT-2 inhibitors carry a regulatory warning for rare FG. A nonsignificant association in studies with few events does not eliminate the warning; suspected FG requires prompt treatment and discontinuation of the SGLT-2 inhibitor[1][4] |
Clinical Presentation and Diagnosis
Clinical Features
Early FG may be mistaken for cellulitis or scrotal abscess. Progression to frank necrosis can occur within hours.
Early: Perineal/scrotal erythema, pain, and edema out of proportion to visible skin changes; induration; fever, tachycardia
Late: Gray/bronze/violaceous skin discoloration with blistering; crepitus on palpation; foul-smelling discharge; cutaneous gangrene; septic shock
Prodromal Period — A Missed-Diagnosis Window
A population-based longitudinal study of 8,098 patients found that 50% had a symptomatically similar diagnosis at a healthcare visit within the 21 days before their Fournier's gangrene diagnosis, and only 16% of those earlier visits involved a urologist. The claims-based model estimated that 63% of symptomatically similar visits represented diagnostic delay; progressive genital or perineal findings at a return visit warrant renewed assessment for FG.[17]
Operate on Clinical Diagnosis — Do Not Wait for Imaging.
The clinical diagnosis of FG is made at the bedside. Do not delay operative debridement in a patient with systemic sepsis and perineal crepitus or necrosis. CT or MRI delineates extent, including pararectal involvement, and helps in equivocal cases, but must not delay surgery in an obvious presentation.[13][11]
Imaging
| Modality | Performance | Notes |
|---|---|---|
| CT abdomen/pelvis with IV contrast | For fascial gas alone in a broader adult NSTI meta-analysis: sensitivity 88.5%, specificity 93.3%[11] | Assesses extent/source; gas supports concern but is neither required nor independently diagnostic |
| Point-of-care ultrasound | Real-time; operator-dependent | Fluid along a fascial plane is the most sensitive finding and subcutaneous emphysema the most specific, per a systematic review of ultrasound for necrotizing fasciitis;[18] POCUS can detect fascial fluid even where formal deep fascial characterization is limited compared with CT/MRI. Intrascrotal air confined to the bowel lumen, rather than subcutaneous or fascial gas, points to an incarcerated inguinal hernia instead of NSTI |
| MRI | Superior soft tissue characterization | Slow acquisition limits emergency use; impractical in unstable patients |
| Plain radiograph | Low sensitivity | May detect gross subcutaneous gas; insufficient for planning |
Severity Scoring
Fournier's Gangrene Severity Index (FGSI)
Developed by Laor et al. (1995);[5] uses 9 physiological parameters scored 0–4 based on deviation from normal. The table shows only the values that score the maximum 4 points in Laor's original Table 1:[5][15]
| Variable | Abnormal Deviation | Max Points |
|---|---|---|
| Temperature (°C) | >41 or <29.9 | 4 |
| Heart rate (bpm) | >180 or <39 | 4 |
| Respiratory rate | >50 or <5 | 4 |
| Serum sodium (mEq/L) | >180 or <110 | 4 |
| Serum creatinine (mg/dL; Laor's table marks it ×2 for acute renal failure) | >3.5 | 4 |
| Serum potassium (mEq/L) | >7 or <2.5 | 4 |
| Hematocrit (%) | >60 or <20 | 4 |
| WBC (×1,000/mm³) | >40 or <1 | 4 |
| Serum bicarbonate, venous (mEq/L) | >52 or <15 | 4 |
In the original 30-patient series, FGSI ≤9 corresponded to 78% survival and >9 to 75% mortality.[5]
Other prognostic scores
The Uludag FGSI adds age and disease extent. The simplified FGSI uses potassium, creatinine and hematocrit.[1] Performance varies across derivation and validation cohorts.[1]
CRP Ratio as Mortality Predictor
A retrospective 52-patient study defined the ratio as preoperative CRP divided by CRP 48 hours after surgery. A ratio ≤1.78 was associated with mortality (sensitivity 86%, specificity 82% within this cohort).[12] Source-control decisions depend on the whole clinical course and repeated wound assessment.[12]
LRINEC Score
The Laboratory Risk Indicator for Necrotizing Fasciitis (LRINEC) incorporates WBC, CRP, hemoglobin, sodium, creatinine, and glucose.[6] In a meta-analysis of adults evaluated for NSTI, score ≥6 had sensitivity 68.2% and specificity 84.8%.[11] A negative LRINEC does not exclude NSTI.
The FGSI and similar scores provide prognostic information and can guide ICU communication and family counseling. LRINEC is a diagnostic aid. No score should delay or defer operative intervention in a clinically apparent or deteriorating patient.
Surgical Management
Timing
Arrange urgent surgical debridement. Delayed source control is associated with worse outcomes. Begin resuscitation, antibiotics and anesthetic/operative preparation in parallel; avoid unnecessary delays while addressing immediate physiologic threats.[2][8]
Skin-Sparing Debridement — Modern Paradigm
AUA advises exploration with limited debridement of nonviable tissue in extensive genital skin loss from infection, shearing injury or burns (Statement 31; Standard, Grade B). Its discussion emphasizes preserving potentially viable genital skin.[22]
Historical radical debridement excised all tissue through to healthy, non-cellulitic margins, often sacrificing viable skin and creating large defects requiring complex reconstruction. Contemporary evidence supports a skin-sparing approach: because the rich cutaneous vasculature may preserve skin viability even over necrotic subcutaneous tissue, the emphasis is on excising only dead or severely compromised tissue.[1][3]
Tom et al. studied 487 patients with NSTI at one institution, comparing an earlier traditional-debridement cohort (230) with a later skin-sparing cohort (257). Mortality did not differ significantly. Median proportion of wound area closed primarily was 0% versus 50%, and skin-grafted area 90% versus 20%.[3] The reported closure percentages describe wound area; the comparison was temporal and nonrandomized.[3]
Counter incisions are a named technique some high-volume NSTI centers use to achieve exposure and source control while sparing overlying skin, without obviating the need for complete debridement of all necrotic tissue.[19]
Operative Technique
Positioning: Lithotomy for wide perineal, scrotal, and genital exposure
Incision strategy: Tailor exposure to the involved fascial compartments. Remove necrotic tissue fully and reassess doubtful tissue; preserving viable skin must not limit adequate exposure or source control.
Blunt dissection distinguishes healthy from necrotic planes. Healthy tissue bleeds briskly; necrotic tissue does not. The finger test (finger dissection proceeds through normally adherent fascial planes without resistance) supports the diagnosis of NSTI in the appropriate clinical context.
Wound left open after debridement; never close at initial operation.
Extent of debridement:
- All visibly necrotic skin, subcutaneous tissue, and fascia
- Extend along fascial planes to bleeding margins
- Scrotum: Orchiectomy rarely required; testicular blood supply is preserved through spermatic cord
- Penis: Debride necrotic Dartos and Buck's fascia; penectomy very rarely required
- Perineum/perirectal: Disease may extend to the ischiorectal fossa. Assess rectal or sphincter injury and wound contamination with the colorectal team. Consider noninvasive fecal management when feasible; perirectal extent, sphincter injury or uncontrolled stool contamination may warrant colostomy for source control or wound care.[13] A retrospective cohort of 149 patients did not find lower mortality with fecal diversion.[24]
- Urinary diversion: SPT recommended when extensive perineal involvement is present or urethral injury has occurred
Re-Look Operations.
IDSA advises that most patients with necrotizing fasciitis return to the OR 24–36 hours after initial debridement and daily thereafter until no further debridement is needed.[8] Areas appearing viable at initial debridement may become ischemic within 24–72 hours post-mobilization. Inadequate single-operation approaches are associated with increased mortality; re-look reflects the evolving biology of the disease.
Venous Thromboembolism Prophylaxis
These patients are frequently septic or critically ill, immobile pending source control, and scheduled for repeated general anesthetics with open wounds, all of which raise baseline VTE risk. The Surviving Sepsis Campaign 2021 guideline recommends pharmacologic VTE prophylaxis over no prophylaxis in adults with sepsis or septic shock, absent a contraindication such as active bleeding.[14] The 2026 Surviving Sepsis Campaign strongly recommends pharmacologic VTE prophylaxis for adults with sepsis or septic shock unless contraindicated and strongly recommends low-molecular-weight heparin over unfractionated heparin.[23] Reassess bleeding and VTE risk around each debridement using the VTE Prophylaxis hub; repeated debridement alone does not establish a contraindication.
Antimicrobial Therapy
Broad-spectrum empiric antibiotics must be initiated immediately upon diagnosis:[8]
Standard polymicrobial coverage options (IDSA-based):
| Regimen | Components |
|---|---|
| Option 1 | Linezolid + Piperacillin-tazobactam |
| Option 2 | Vancomycin + Clindamycin + Piperacillin-tazobactam |
| Alternative broad regimens | Linezolid + Meropenem; or Linezolid + Cefepime/Ceftriaxone + Metronidazole |
| Critically ill (broad) | Vancomycin or linezolid plus a carbapenem (meropenem or imipenem-cilastatin); carbapenem alone does not cover MRSA |
Select agents and doses by renal function, local resistance and penicillin-allergy phenotype; the listed alternatives are not universal penicillin-allergy regimens. For documented group A streptococcal necrotizing fasciitis, IDSA recommends penicillin plus clindamycin.[8]
Antifungal coverage and local antibiogram. A single tertiary-center series of 143 patients with Fournier’s gangrene (2011–2018) had wound cultures available for 131; reported isolates included Staphylococcus (66/143, 46%), Streptococcus (53/143, 37%), Bacteroides (34/143, 24%), Candida (31/143, 22%), E. coli (28/143, 20%) and Prevotella (26/143, 18%). The investigators also reported vancomycin resistance in Streptococcus anginosus and Enterococcus faecalis isolates.[16]
De-escalate antibiotics based on intraoperative wound cultures (obtain at initial debridement). IDSA advises continuing until further debridement is unnecessary, clinical improvement is evident, and fever has been absent for 48–72 hours.[8]
Adjunct and Investigational Therapies
| Therapy | Evidence | Recommendation |
|---|---|---|
| Hyperbaric oxygen (HBO) | Retrospective series show inconsistent benefit; randomized evidence is lacking | The EAU 2026 guideline weakly recommends against adjunctive treatment outside clinical trials. HBO must not delay debridement.[13] |
| IVIG | Benefit in streptococcal toxic shock remains uncertain; routine benefit in FG is not established[8] | Not recommended routinely |
| Reltecimod | 2020 trial showed trends toward benefit but no significant benefit in modified intent-to-treat analysis; FDA unapproved[1] | Investigational; not standard of care |
The EAU 2026 infections guideline gives a strong recommendation to start broad-spectrum antibiotics on presentation and to begin repeated surgical debridement within 24 hours, and a weak recommendation not to use adjunctive treatments outside clinical trials. It found no consistent evidence of benefit for hyperbaric oxygen (retrospective series, mostly before 2000), no evidence of benefit for negative-pressure wound therapy, and low-quality evidence that honey-soaked dressings shortened hospital stay (28 versus 32 days) compared with EUSOL in a 30-patient trial. It reports United States registry mortality of 5% to 10% and that a review of 16 case series (425 men) favored primary or secondary closure for scrotal defects of 50% or less, and flaps or grafts for larger defects.[13] The guideline's suggested regimens include piperacillin-tazobactam with vancomycin, a carbapenem, or cefotaxime with metronidazole or clindamycin.[13]
Wound Management
Choose wound care after adequate debridement according to tissue viability, anatomy and contamination:
- Saline or appropriately diluted antiseptic dressings may be used; antiseptics can be cytotoxic at higher concentrations.
- Negative-pressure wound therapy can assist exudate control and wound preparation. The 35-patient Czymek comparison had selection/survivor bias.[9]
- Temporary testicular thigh pouches are an option in selected extensive scrotal defects, with later functional and reconstructive counseling.
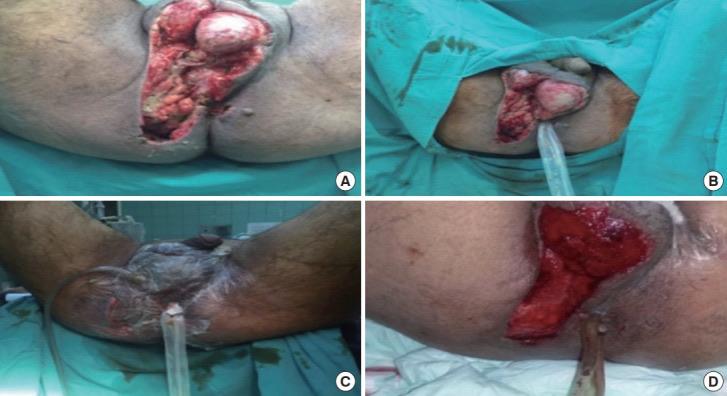
Fournier gangrene managed with vacuum-assisted closure and a bowel management catheter together. (A) Wound after debridement. (B) Bowel management catheter in place. (C) Vacuum-assisted closure applied after placement of the bowel management catheter. (D) Granulation tissue after vacuum-assisted closure therapy. From Eray IC, et al. Ann Coloproctol. 2023;39(3):223-230, Fig. 1 (CC BY-NC).[12]
Reconstruction
Reconstruction follows control of infection and a clean wound.[1] A 2025 review favors early genital reconstruction.[1] A retrospective cohort of 84 patients found that early, same-admission primary closure was associated with a 64% shorter wound convalescence time than healing by secondary intention, after adjustment for wound anatomic extent.[20]
A 2024 review included 38 studies, mainly small observational series. Direct closure, secondary healing, grafts and local flaps were commonly reported; no included study reported a free flap.[10]
A single-center retrospective review of 16 selected adult men undergoing delayed closure of large defects (mean 119 cm², range 44–346 cm²) reported four Clavien–Dindo grade III complication events among the 16 patients: two partial flap necroses, one dehiscence and one bleeding event. Median hospital stay was 13 days (IQR 9–16.3); the study had no comparator group. Most patients were discharged directly home.[21] Half the patients were closed with scrotal flaps alone and the rest with advancement flaps from the inner thigh, lower abdomen or perineum.[21]
| Wound Extent | Preferred Option |
|---|---|
| Small defects | Secondary intention or delayed primary closure (modern preference) |
| Moderate scrotal defects | Split-thickness skin graft (STSG) — preferred over FTSG for take rate |
| Large scrotal / perineal defects | STSG over vascularized tissue; a local or regional flap for deep defects or exposed bone or tendon, including a gracilis myocutaneous flap for deep perineal floor defects.[10] |
| Complex loco-regional needs | Anterolateral thigh, superomedial thigh, groin, SCIP, or Limberg transposition flap |
| Extensive scrotal loss with exteriorized testicles | Thigh pouch; eventual flap reconstruction when conditions allow |
| Penile shaft skin loss | STSG over corporal bodies |
Delayed primary closure is useful when viable tissue can be approximated without tension after infection control. In selected NSTI patients in Tom et al.'s skin-sparing cohort, median primary wound-area closure was 50%.[3]
Tissue expanders require residual scrotal skin and are not an option after complete scrotal loss.[26] Testicular thigh pouches, while simple to perform, carry concerns about temperature regulation and testicular function; patient preference for reconstruction approach should be elicited.
In a retrospective FG cohort of 149 patients, 10 of 33 who had a colostomy during admission underwent restoration of intestinal continuity after the acute episode.[24]
Patient-reported outcomes: comparative functional, sexual and body-image outcomes remain limited in the reconstructive literature.[10]
Podcasts
References
1. Kopechek KJ, Patel HV, Koch GE. Modern Management of Fournier's Gangrene. Curr Urol Rep. 2025;26(1):47. PMID 40455358 doi:10.1007/s11934-025-01275-3
2. Abbasi B, Hacker E, Ghaffar U, et al. Higher Morbidity and Mortality in Females With Fournier Gangrene Compared With Males: Insights From National Inpatient Sample Data. J Urol. 2025;213(1):99–109. doi:10.1097/JU.0000000000004264.
3. Tom LK, Maine RG, Wang CS, Parent BA, Bulger EM, Keys KA. Comparison of Traditional and Skin-Sparing Approaches for Surgical Treatment of Necrotizing Soft-Tissue Infections. Surg Infect. 2020. doi:10.1089/sur.2019.263.
4. US Food and Drug Administration. FDA warns about rare occurrences of a serious infection of the genital area with SGLT2 inhibitors for diabetes. FDA Drug Safety Communication. August 29, 2018. See also Health Sciences Authority safety communication.
5. Laor E, Palmer LS, Tolia BM, Reid RE, Winter HI. Outcome prediction in patients with Fournier's gangrene. J Urol. 1995;154(1):89–92. doi:10.1016/s0022-5347(01)67236-7. PMID 7776464
6. Wong CH, Khin LW, Heng KS, Tan KC, Low CO. The LRINEC (Laboratory Risk Indicator for Necrotizing Fasciitis) score: A tool for distinguishing necrotizing fasciitis from other soft tissue infections. Crit Care Med. 2004;32(7):1535–1541. doi:10.1097/01.ccm.0000129486.35458.7d. PMID 15241098
7. Sorensen MD, Krieger JN, Rivara FP, et al. Fournier's Gangrene: Management and mortality predictors in a population based study. J Urol. 2009;182(6):2742–2747. doi:10.1016/j.juro.2009.08.050. PMID 19837424
8. Stevens DL, Bisno AL, Chambers HF, et al. Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the IDSA. Clin Infect Dis. 2014;59(2):e10–52. doi:10.1093/cid/ciu444. PMID 24973422
9. Czymek R, Schmidt A, Eckmann C, et al. Fournier's gangrene: Vacuum-assisted closure versus conventional dressings. Am J Surg. 2009;197(2):168–176. doi:10.1016/j.amjsurg.2008.07.053. PMID 19185110
10. Susini P, Marcaccini G, Efica J, et al. Fournier's Gangrene Surgical Reconstruction: A Systematic Review. J Clin Med. 2024;13(14):4085. doi:10.3390/jcm13144085.
11. Fernando SM, Tran A, Cheng W, et al. Necrotizing Soft Tissue Infection: Diagnostic Accuracy of Physical Examination, Imaging, and LRINEC Score: A Systematic Review and Meta-Analysis. Ann Surg. 2019;269(1):58–65. doi:10.1097/SLA.0000000000002774.
12. Eray IC, Dalci K, Gumus S, et al. The role of C-reactive protein ratio in predicting mortality in patients with Fournier gangrene. Ann Coloproctol. 2023;39(3):223–230. doi:10.3393/ac.2021.00843.0120.
13. European Association of Urology. EAU Guidelines on Urological Infections (section 3.13, Fournier's gangrene). 2026 limited update, March 2026. Full guideline.
14. Evans L, Rhodes A, Alhazzani W, et al. Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2021. Crit Care Med. 2021;49(11):e1063–e1143. PMID 34605781 doi:10.1097/CCM.0000000000005337.
15. Tufano A, Dipinto P, Passaro F, et al. "The Value of Fournier's Gangrene Scoring Systems on Admission to Predict Mortality: A Systematic Review and Meta-Analysis." J Pers Med. 2023;13(9):1283. doi:10.3390/jpm13091283
16. Castillejo Becerra CM, Jaeger CD, Rose JR, et al. Microorganisms and Antibiogram Patterns in Fournier's Gangrene: Contemporary Experience from a Single Tertiary Care Center. J Urol. 2020;204(6):1249–1255. doi:10.1097/JU.0000000000001194
17. Erickson BA, Miller AC, Warner HL, et al. Understanding the Prodromal Period of Necrotizing Soft Tissue Infections of the Genitalia (Fournier's Gangrene) and the Incidence, Duration, and Risk Factors Associated With Potential Missed Opportunities for an Earlier Diagnosis: A Population-based Longitudinal Study. J Urol. 2022;208(6):1259–1267. doi:10.1097/JU.0000000000002920
18. Marks A, Patel D, Sundaram T, Johnson J, Gottlieb M. Ultrasound for the diagnosis of necrotizing fasciitis: A systematic review of the literature. Am J Emerg Med. 2023;65:31–35. doi:10.1016/j.ajem.2022.12.037
19. Koch GE, Amighi A, Skokan AJ, Hagedorn JC. Skin-Sparing Debridement in Fournier's Gangrene. J Urol. 2024;212(6):912–914. doi:10.1097/JU.0000000000004216
20. Sandberg JM, Warner HL, Flynn KJ, et al. Favorable Outcomes With Early Component Separation, Primary Closure of Necrotizing Soft Tissue Infections of the Genitalia (Fournier's Gangrene) Debridement Wound Defects. Urology. 2022;166:250–256. doi:10.1016/j.urology.2022.03.042
21. Kumar SS, Sun HH, Tay K, et al. Favorable Safety Outcomes of Delayed Primary Closure of Large Fournier's Gangrene Skin Defects. Urology. 2023;180:270–277. doi:10.1016/j.urology.2023.07.028
22. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
23. Prescott HC, Antonelli M, Alhazzani W, et al. "Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2026." Crit Care Med. 2026;54(4):725–812. doi:10.1097/CCM.0000000000007075
24. Ortega Ferrete A, López E, Juez Sáez LD, et al. "Fournier’s gangrene and fecal diversion. When, in which patients, and what type should I perform?" Langenbecks Arch Surg. 2023;408(1):428. doi:10.1007/s00423-023-03137-3
25. Inácio MF, Lima RP, Rizzo Neto S, Lopes FA, Pantaroto M, de Sousa AV. "Epidemiological study on Fournier syndrome in a tertiary hospital in Jundiaí-SP from October 2016 to October 2018." J Coloproctol. 2020;40(1):37–42. doi:10.1016/j.jcol.2019.10.005
26. Suda S, Hayashida K. "Crafting Contours: A Comprehensive Guide to Scrotal Reconstruction." Life (Basel). 2024;14(2):223. doi:10.3390/life14020223
27. Tazeoglu D, Benli S, Esmer AC, Colak T, Apaydin FD. "Effect of Sarcopenia on Mortality and Morbidity in Patients With Fournier's Gangrene." Am Surg. 2023;89(12):5527–5534. doi:10.1177/00031348231160840