Penile Fracture
Penile fracture is a urological emergency: a traumatic tear of the tunica albuginea, the dense fibrous sheath encasing the corpora cavernosa, caused by excessive bending force applied to an erect penis. The diagnosis is primarily clinical. Prompt surgical repair is advised, and a retrospective comparison found worse erectile and curvature outcomes with conservative treatment.[1] The ACS estimates that about 15% of penile fractures involve a urethral injury, which is identified and repaired at the same operation.[2]
Mechanism and Anatomy
Penile fracture occurs when the erect penis bends excessively during sexual activity or is forcibly deflected against the perineum, partner's body, or bedding. The classic injury mechanism involves aggressive manual manipulation or atypical coital positioning.[4][17] Sudden bending can raise intracavernosal pressure enough to tear the thinned tunica albuginea; the often-cited 1,500-mmHg figure comes from cadaveric infusion experiments.[4][17]
The tunica albuginea is thinnest on the ventral and lateral surfaces of the penile shaft, distal to the suspensory ligament; these are the most frequent sites of rupture.[2] Fractures may be unilateral or bilateral, involving one or both corpora cavernosa. The penile and bulbar urethra belong to the anterior urethra. They run within the corpus spongiosum, ventral to the corpora cavernosa; the bulbospongiosus muscle overlies the urethral bulb. Associated spongiosal and urethral injury must be assessed.
Clinical Presentation and Diagnosis
The diagnosis of penile fracture is made by history and physical examination in the majority of cases; imaging is not required when the clinical picture is unambiguous.[2]
Classic triad:
- Audible popping or cracking sound at the time of injury
- Immediate detumescence with rapid deflation of the erection
- Severe penile pain, ecchymosis, and swelling
Physical examination findings:
- Penile ecchymosis and hematoma (may involve the scrotum and perineum if Buck's fascia is disrupted)
- Penile deviation or deformity ("eggplant" or "rolled sausage" deformity depending on hematoma extent)
- Palpable defect in the tunica albuginea (present in some cases)
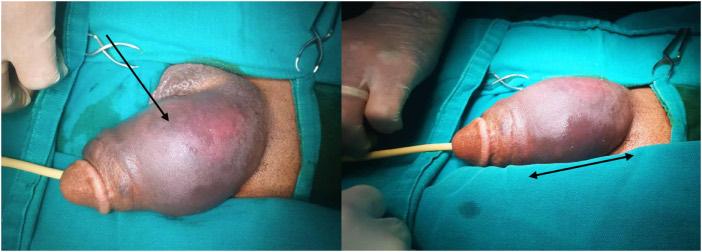
Preoperative appearance of a penile fracture with penile deformity, ecchymosis and swelling; a urethral Foley catheter was placed before surgery. From Ibrahim F, et al. Int J Surg Case Rep. 2026;138(7):2491-2494, Figure 1 (CC BY 4.0).[12]
When Imaging Is Indicated. For patients with indeterminate history or physical examination (atypical mechanism, delayed presentation, obesity preventing palpation, or complex anatomy), penile ultrasound or MRI may be used to evaluate for fracture. Ultrasound is operator-dependent; MRI can clarify an inconclusive examination or ultrasound when promptly available. Imaging must not delay repair of a clinically clear fracture.[2] AUA permits ultrasound for equivocal cases , considers MRI when ultrasound is equivocal or unavailable, and advises exploration if diagnostic doubt persists.[11] The EAU lists ultrasound, contrast-enhanced MRI and cavernosography as options for unclear cases, and reports MRI to be superior to ultrasound.[4][16] The EAU lists an absent cracking sound, slow detumescence, deviation and shaft ecchymosis as clues to possible false fracture.[4][16] In equivocal cases, imaging can assess tunical integrity; exploration remains appropriate if doubt persists.[4][11]
Associated Urethral Injury
The ACS and EAU guidelines both cite urethral injury in about 15% of penile fractures (EAU range 1 to 38% depending on aetiology).[2][4] A 2023 systematic review included 15 studies of penile fracture with associated urethral injury.[5] In a retrospective Brazilian series of 175 patients, 27 (15.4%) had an associated urethral injury.[15] Evaluate for urethral involvement when any of the following is present:[2]
- Blood at the urethral meatus
- Gross hematuria
- Difficulty urinating, weak urinary stream, or acute urinary retention
- Inability to pass a urethral catheter
AUA requires urethral evaluation with penile fracture or penetrating trauma when meatal blood, gross hematuria or inability to void is present (Statement 29; Standard, Grade B). Bilateral corporal fracture is an additional risk factor for urethral injury.[11]
When urethral injury is suspected, perform RUG or cystourethroscopy before or at the time of surgical exploration. AUA regards both as acceptable; neither has demonstrated diagnostic superiority, and availability and procedure timing guide selection.[11] Visible hematuria in a man with genital trauma calls for RUG, and the EAU describes flexible cystoscopy at the start of exploration to localize a urethral injury.[4] Avoid forceful or repeated blind catheter attempts. Direct urethral inspection during surgical exploration is recommended regardless of preoperative imaging; one series reported 2 false negatives among 7 retrograde urethrograms for complex penile fracture, and many surgeons now forgo routine urethrography because intraoperative recognition of urethral disruption is generally straightforward once the corpora are exposed.[7] The urethra may be involved in up to 50% of penile penetrating (ballistic) injuries as well.[2]
Operative Management
Timing
AUA recommends prompt surgical exploration and repair (Statement 27; Standard, Grade B), with repair at presentation in its discussion.[11] The ACS guideline advises exploration within 7 days of injury and notes that earlier repair may improve long-term outcomes, including less pain, faster convalescence and a lower risk of curvature.[2] The 2026 ICSM recommends tunical closure ideally within 24–48 hours of injury .[14] The EAU gives a strong recommendation to treat penile fracture surgically with closure of the tunica albuginea and to exclude urethral injury, and states that immediate urethral repair is indicated when the urethra is injured.[4] The EAU cites a systematic review concluding that repair should be immediate, within 24 hours of presentation, but adds that delayed presentation should not prevent exploration.[4] Delayed presentation should not prevent consideration of exploration; when a penile fracture is diagnosed at presentation, repair is prompt.[2][3][4][11]
The el-Assmy retrospective study included 180 operated patients: 149 presented within 24 hours and 31 presented 30 hours to seven days after injury. It found no significant difference in complications between groups. This supports offering repair to late presenters.[3]
Conservative (non-operative) management is associated with higher complication rates, including abscess, penile fibrosis, Peyronie's disease-like plaques and chronic erectile dysfunction. In the retrospective Gamal series (77 patients, median follow-up 20.8 months), 49 of 51 followed surgical patients (96%) and 9 of 18 followed conservative patients (50%) reported erections adequate for intercourse, no voiding dysfunction, and no penile curvature.[1] Surgical repair is the standard of care.
For patients presenting to a lower-level trauma center without urology coverage, consider early transfer to a center with urology expertise once the patient is stabilized.
Surgical Approach
The ACS guideline names two options, a circumcising incision or a ventral midline penile incision, chosen by the suspected location of injury.[2]
| Incision | Practical use |
|---|---|
| Circumcising degloving | Allows complete bilateral corporal exposure; the EAU's usual approach[4] |
| Ventral midline penile | Direct access along the ventral shaft; the EAU notes local or ventral longitudinal incisions are used increasingly[4] |
Technique:
- Exposure: With a circumcising incision, mobilize penile skin for full bilateral corporal exposure; local or ventral longitudinal incisions are also described.[4] Evacuate the hematoma, identify the tunical tear and irrigate the field. Avoid excessive debridement of viable corporal tissue.[14] In one case report, intraoperative ultrasound localized the tear for a small transverse incision.[13]
- Artificial erection (optional): Inject saline (with or without dilute methylene blue) directly into the corporal body to identify the exact location and extent of the tunica tear when the fracture site is not immediately apparent
- Tunica repair: Close the tunica albuginea disruption with absorbable sutures (typically 2-0 polyglycolic acid or PDS); horizontal mattress or interrupted sutures depending on tear configuration; ensure a watertight closure. Repeating the intracorporeal saline injection and artificial erection (the Gittes test) after closure can confirm tunical integrity and expose a small residual tear previously covered by clot.[7]
- Concomitant urethral repair: Close a partial urethral laceration with interrupted absorbable sutures over a urethral catheter. For complete disruption without extensive tissue loss, perform a tension-free end-to-end anastomosis. Leave a urethral catheter in place whether or not suprapubic drainage is also used.[4][15]
- Drain: Closed-suction drain placement is at surgeon discretion; typically not required for isolated fracture repair
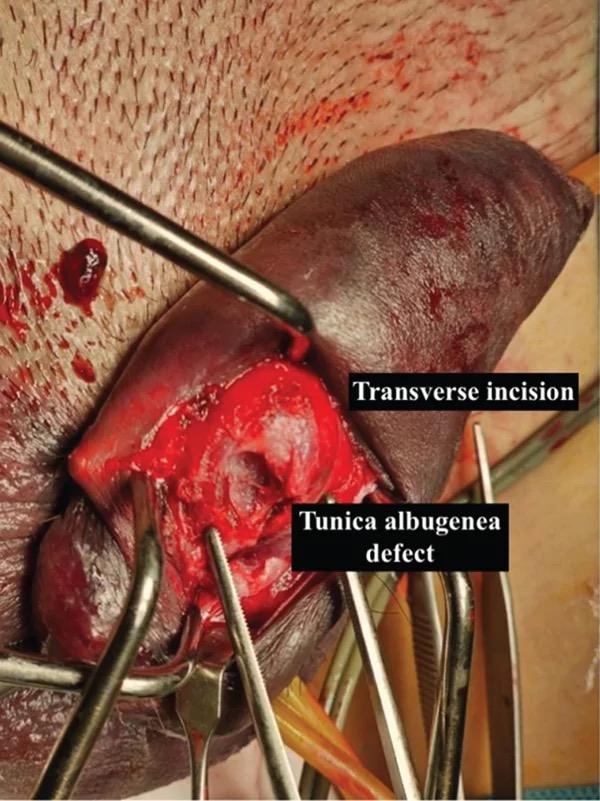
Intraoperative ultrasound-guided repair: a small transverse incision over the site localized by ultrasound exposes the tunica albuginea defect, which was then closed with suture. From Wong HL, et al. Case Rep Urol. 2026;2026:3418235, Figure 3 (CC BY 4.0).[13]
Post-Operative Care
- After urethral repair, catheter duration is tailored to the injury and repair; a 2023 systematic review reported a 21-day median across the eight included studies that provided catheter-duration medians (study medians 12–28 days).[5]
- A 68-patient surgical series advised sexual abstinence for 6 weeks after repair.[18]
- Counsel about possible penile length loss, deformity, altered sensation and sexual dysfunction .[14] Follow-up assesses curvature, erectile function and voiding (if urethral repair was performed); after urethral injury, AUA recommends monitoring for stricture, erectile dysfunction and incontinence for at least one year (Statement 23; Recommendation, Grade C).[11]
- Neither the ACS nor the EAU guideline gives a penile-fracture-specific VTE recommendation.[2][4] This is a short operation without prolonged immobility in most patients; the EAU trauma guideline's general chapter notes trauma patients overall are at high DVT risk, favors compression stockings and LMWH, and notes that strict bed rest after isolated renal trauma has waned in patients able to mobilize.[4] Apply the individual risk-based approach on the VTE Prophylaxis hub rather than a fixed regimen
Outcomes and Complications
| Outcome | Notes |
|---|---|
| Erectile dysfunction | Rare after surgery (1.9% in the EAU summary); more frequent above age 50 and with bilateral corporal involvement; higher with conservative management (up to 62%)[4] |
| Penile curvature | 2.8% after surgery in the EAU summary; more common with delayed repair; may require Nesbit procedure or grafting if symptomatic. Plaques or nodules occur in 13.9% after surgery, while fibrosis or angulation occurs in 35% after conservative management.[4] A matched claims-database cohort found a PD diagnosis in 5.8% of men after penile fracture versus 0% of matched controls (p < 0.0001); immediate repair was associated with fewer coded PD diagnoses (RR 0.20, 95% CI 0.10–0.41), while coded PD diagnoses were more frequent in men over 45 at the time of fracture (RR 3.72, 95% CI 1.94–7.16 versus under 45) within 5 years[6] |
| Urethral stricture | Risk increases with concurrent urethral injury; follow-up should assess for stricture if urethroplasty was performed. The EAU cites a 2% stricture rate after immediate urethral reconstruction,[4] and a 2023 review described five postoperative strictures among its included reports.[5] |
| Wound complications | Uncommon; hematoma and wound dehiscence are the most frequent early complications |
Suspected Fracture After Collagenase (CCH) Injection
A popping sensation or rapid detumescence during or after collagenase clostridium histolyticum (CCH) injection for Peyronie's disease raises concern for a fracture-like tunical injury, but management of this CCH-associated event has been treated separately from the usual traumatic tunical rupture above. A survey of clinicians in the Sexual Medicine Society of North America found varied practice for suspected CCH-associated fracture.[9] In Sharma’s survey, 45 of 158 contacted men who completed four CCH injection series provided complete responses. Seven of these 45 respondents (16%) reported popping or rapid detumescence within 6 weeks and were classified as suspected fractures; tunical rupture was not confirmed, and all seven were observed without surgery.[10] Erectile function (IIEF erectile-function domain) did not worsen compared with men without a suspected fracture (median change +2 vs +1, p = 0.16), and the suspected-fracture group had a larger median primary-curve reduction (30° versus 15°, p = 0.04); the composite-curvature comparison was not statistically significant (p = 0.15).[10] The 2026 ICSM consensus distinguishes mechanism: suspected tunical rupture after coital axial loading follows the traumatic-fracture pathway, whereas observation may be considered for a possible CCH-associated rupture after a spontaneous erection without axial loading or expanding hematoma.[14] The Sharma survey does not compare observation with surgical repair.[10][14]
Penetrating Penile Injury
Penile penetrating injuries are most commonly caused by gunshot wounds and are frequently associated with abdominal, pelvic, and lower extremity injuries.[2] The urethra is involved in up to 50% of penile ballistic injuries.[2]
Management:
- Explore significant penetrating injuries promptly, with irrigation, conservative debridement, removal of foreign bodies and repair.[2] The EAU recommends nonoperative management for small superficial injuries with intact Buck’s fascia; for larger injuries it advises debridement of necrotic tissue only, preserving viable tissue, closing tunica defects after irrigation and grafting when tissue loss is too great.[4]
- Corporal body involvement: repair as for penile fracture (absorbable suture closure of corporotomy or tunica defect)
- For uncomplicated penetrating anterior urethral injury, AUA advises prompt primary repair after staging . Primary repair is deferred with instability, insufficient urethral expertise or extensive tissue destruction or loss.[11] When feasible, use a tension-free, watertight closure over a urethral catheter.[8] When a defect is too long or the tissue too friable to hold suture for primary anastomosis, marsupialization of the urethra with proximal urinary diversion, followed by deferred staged reconstruction after 3–6 months, is a described salvage option for penetrating anterior urethral injury.[8]
- For patients with suspected penile fracture at lower-level trauma centers: consider early transfer to a center with urology expertise once stabilized.[2]
References
1. Gamal WM, Osman MM, Hammady A, Aldahshoury MZ, Hussein MM, Saleem M. Penile fracture: Long-term results of surgical and conservative management. J Trauma. 2011;71(2):491–493. doi:10.1097/TA.0b013e3182093113.
2. American College of Surgeons Trauma Quality Programs. ACS TQP Best Practices Guidelines: Management of Genitourinary Injuries. Chicago, IL; August 2025. Full guideline.
3. el-Assmy A, el-Tholoth HS, Mohsen T, Ibrahiem el-HI. Does timing of presentation of penile fracture affect outcome of surgical intervention? Urology. 2011;77(6):1388–1391. doi:10.1016/j.urology.2010.12.070.
4. European Association of Urology. EAU Guidelines on Urological Trauma, sections 3.3.5 (thromboprophylaxis and bed rest), 4.4.2 and 4.5 (urethral and genital trauma; limited update March 2026). Guideline.
5. Shebl SE. The presentation and outcomes of penile fracture with associated urethral injury: A systematic literature review. Arch Ital Urol Androl. 2023;95(2):11082. doi:10.4081/aiua.2023.11082
6. Maremanda AP, Du Comb W, Able C, Kohn TP, Unal S, Burnett AL. Erectile dysfunction and Peyronie's disease diagnosis rates after penile fracture — a retrospective claims database cohort analysis. Int J Impot Res. 2024;36(2):125–128. doi:10.1038/s41443-023-00746-w
7. Mydlo JH, Doumanian LR. Penile Fracture. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:625–640. doi:10.1007/978-1-4614-7708-2_44
8. Buckley JC, McAninch JW. Management of Acute Urethral Trauma. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:433–441.
9. Yafi FA, Anaissie J, Zurawin J, et al. Results of SMSNA survey regarding complications following intralesional injection therapy with collagenase clostridium histolyticum for Peyronie's disease. J Sex Med. 2016;13(4):684–689. doi:10.1016/j.jsxm.2016.02.105
10. Sharma KL, Bole R, Yang D, et al. Conservative management of suspected fractures in men undergoing collagenase clostridium histolyticum for Peyronie's disease is not associated with worsening of erectile function. Int J Impot Res. 2022;34(1):100–107. doi:10.1038/s41443-020-00383-7
11. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
12. Ibrahim F, Ahmed AT, Abd Alrhman A, et al. Penile fracture following masturbation: a case report. Int J Surg Case Rep. 2026;138(7):2491–2494. doi:10.1097/rc9.0000000000000557
13. Wong HL, Tsui OWK, Ho BSH, Ng ATL. Intraoperative ultrasound-guided repair of penile fracture: a case report. Case Rep Urol. 2026;2026:3418235. doi:10.1155/criu/3418235
14. Chung E, Morey A, Seyam R, et al. "Male genitalia trauma. Recommendations from 5th International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf058. doi:10.1093/sxmrev/qeaf058
15. Barros R, Silva MIS, Antonucci V, Schulze L, Koifman L, Favorito LA. "Primary urethral reconstruction results in penile fracture." Ann R Coll Surg Engl. 2018;100(1):21–25. doi:10.1308/rcsann.2017.0098
16. Agostini E, Vinci A, Bardhi D, Ingravalle F, Muselli M, Milanese G. "Improving clinical diagnostic accuracy and management of False penile fractures characterizing typical clinical presentation: a systematic review and meta-analysis." World J Urol. 2023;41(7):1785–1791. doi:10.1007/s00345-023-04456-2
17. Bitsch M, Kromann-Andersen B, Schou J, Sjøntoft E. "The elasticity and the tensile strength of tunica albuginea of the corpora cavernosa." J Urol. 1990;143(3):642–645. doi:10.1016/S0022-5347(17)40047-4
18. Sharma G, Mandal S, Bhowmik P, Gupta P, Bahal B, Sharma PK. "Sexual function outcomes and risk factors of erectile dysfunction after surgical repair of penile fracture." Turk J Urol. 2021;47(2):106–112. doi:10.5152/tud.2020.20311