Pelvic Fracture Urethral Injury (PFUI)
Pelvic fracture urethral injury (PFUI) is disruption of urethral continuity near the bulbomembranous junction after high-energy pelvic ring trauma; in a 10-cadaver autopsy series, 7 disruptions were distal to the external sphincter.[69] The ACS guideline cites urethral injury in up to 5% of men with anterior pelvic ring fractures; the EAU reports that falls from height account for 6–25% of PFUIs in cited series.[1][37] The injury results from distraction of the membranous urethra away from the bulbar urethra as the pelvic ring disrupts. For most men with complete posterior disruption, the standard initial management is suprapubic tube (SPT) placement, followed by delayed anastomotic urethroplasty (typically 3–6 months later).[1][2][3][4][5]
For obliterative post-traumatic posterior stenosis, the 2026 EAU Urethral Strictures guideline weakly recommends open reconstruction only in high-volume centers, strongly recommends progressive perineal excision and primary anastomosis, and strongly recommends against endoscopic treatment; cut-to-the-light risks a false passage toward the bladder base or rectum. For short (<1.5 cm) nonobliterative stenosis, it weakly recommends one endoluminal attempt.[64] See the limitations of Core-Through Urethrotomy. For short bulbar EPA, see Excision and Primary Anastomosis.
Epidemiology and Mechanism
PFUI predominantly affects males involved in motor vehicle collisions, falls from height, or crush injuries; mean age at urethroplasty was 41.6 years in the cited 122-patient multicenter PFUI cohort.[1][2][4] The mechanism involves disruption of the pelvic ring (most commonly fractures of the sacroiliac joint, anterior arch with displacement, and/or diastasis of the pubic symphysis), producing shearing forces at the relatively fixed membranous urethra.[1][6]
Each millimeter of symphysis pubis diastasis or inferomedial pubic bone fracture displacement is associated with an estimated 10% relative increased risk of urethral injury.[1][6] Complete injuries (approximately 65%) result in a gap between the two urethral stumps filled with fibrotic tissue; incomplete injuries (approximately 35%) maintain some degree of urethral continuity.[6]
Classification
Goldman classification (1997), expanding Colapinto and McCallum
The original 1977 scheme comprised types I–III; Goldman and colleagues added IV, IVa and V.[38]
- Type I. Posterior urethra stretched but intact
- Type II. Partial or complete pure posterior injury of the membranous urethra above an intact urogenital diaphragm[38]
- Type III. Disruption of the membranous urethra extending below the urogenital diaphragm, involving the anterior urethra
- Type IV. Bladder neck injury with extension into the proximal urethra
- Type IVa. Injury to the base of the bladder with periurethral extravasation simulating Type IV
- Type V. Partial or complete isolated anterior urethral injury[38]
AAST Organ Injury Scale
| Grade | Description |
|---|---|
| I | Contusion (blood at meatus, normal urethrography) |
| II | Stretch injury (elongation without extravasation) |
| III | Partial disruption (extravasation with contrast reaching bladder) |
| IV | Complete disruption with extravasation but no bladder filling (<2 cm separation) |
| V | Complete disruption >2 cm separation, or extension into prostate / vagina |
Clinical Presentation and Diagnosis
Clinical signs
High suspicion is warranted with any of:[1]
- Blood at the urethral meatus. Most classic sign
- Suprapubic fullness
- Perineal laceration or butterfly hematoma
- Scrotal hematoma
- Difficulty or inability to pass a Foley catheter
- Inability to void
A high-riding prostate on rectal examination has low sensitivity and specificity for urethral injury. Rectal examination remains relevant to assess associated rectal injury.[1]
Initial imaging — urethrography
- Retrograde urethrography (RUG) is the preferred initial modality. Extravasation without bladder filling suggests complete disruption, but RUG does not always distinguish complete from partial rupture; flexible cystourethroscopy can help.[1][6] The EAU strongly recommends evaluating male urethral injury with flexible cystourethroscopy and/or RUG.[37] It advises injecting 20 to 30 mL of contrast with the meatus occluded, tilting the X-ray beam to 30° rather than moving a patient with a pelvic fracture, and delaying RUG in an unstable patient until stabilised.[37]
- Combined antegrade and retrograde urethrography (via SPT tract) is the fundamental preoperative evaluation before delayed urethroplasty, assessing gap length and alignment.[7]
- Sequencing: if the patient has a pelvic fracture and CT will assess for arterial extravasation, perform CT first and RUG second; contrast extravasation from urethral injection can produce significant artifact on CT.[1]
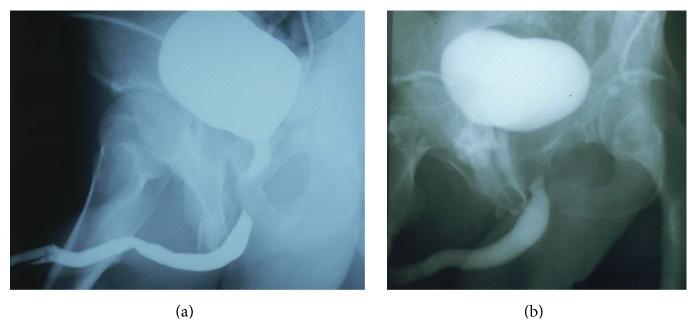
Combined antegrade and retrograde imaging before delayed posterior urethroplasty. (a) With the bladder filled through the suprapubic tube, a retrograde urethrogram is taken while the patient attempts to void; when the bladder neck opens, contrast fills the prostatic urethra and the membranous urethral defect is seen. (b) When the bladder neck does not open, the length of the defect cannot be determined accurately. From Gelman J, Wisenbaugh ES. Adv Urol. 2015;2015:628107, Figure 2 (CC BY).[61]
MRI in Preoperative Planning
Pelvic MRI is an adjunct for complex PFUI, particularly when urethrography does not define the proximal stump, displacement, scar or false passages adequately.[7][8][21][37] Combined antegrade/retrograde urethrography remains the basic reconstruction study.[7][8][21][37]
Protocol
Published PFUI MRI protocols use several combinations of the following sequences and measurements:[7][20]
- T2-weighted sagittal images. A central sequence for identifying the proximal and distal urethral stumps and measuring gap length. Horiguchi et al. measured the pubourethral stump angle (PUA) and pubourethral stump length (PUL) on sagittal T2 in a retrospective 74-man PFUI cohort.[9]
- T2-weighted coronal images. Lateral prostatic displacement and the relationship of the urethra to the corpora cavernosa.
- T1- and T2-weighted axial images. Corpora cavernosa integrity, dorsal venous complex, periurethral scar tissue, and false passages.
- The original PUA study obtained MRI at least 3 months after injury.[9]
- T2-weighted sequences depict urethral and periurethral anatomy; contrast-enhanced T1 images can help assess stenosis, fistulas, abscesses and urinomas.[7]
- A described protocol variant (the "Joshi" protocol) fills the bladder with saline, uses a pre-study alpha-1 blocker to facilitate bladder-neck opening, introduces saline or jelly through the meatus, and acquires a T2 sagittal image with a full bladder while the patient attempts to void; in a 40-patient prospective comparison, this protocol measured urethral gaps 0.3–1.1 cm shorter, with better image-quality scores, than conventional MRI.[53]
Additional MRI information
Accuracy estimates below come from small, selected cohorts (21–27 patients).
| Parameter | Urethrography | MRI | Clinical Significance |
|---|---|---|---|
| Urethral gap length | Estimates; often inaccurate | Matched operative length within 0.5 cm in 23/27 (85%); correctly determined in 18/21 (86%) | Determines need for ancillary maneuvers[7][21][22] |
| Prostatic displacement (direction + degree) | May incompletely depict displacement[20] | Correctly determined in 16/18 (89%)[21] and 19/21 (90%)[22] patients with displacement | In a 121-patient retrospective PFUI cohort, prostatic displacement was associated with an elaborate repair[25]; in a 27-patient MRI cohort, superior/lateral displacement was associated with persistent ED at 12 months.[22] |
| Scar tissue extent and density | Not visualized | Precisely delineated | Guides scar excision planning[21] |
| Paraurethral false tracks | May be missed | Found in 3/21 patients (14%) | May inform operative planning[21] |
| Cavernous body integrity | Not assessed | Avulsion and separation clearly shown | Predicts ED[20][22] |
| Dorsal venous complex patency | Not assessed | Assessed on axial / sagittal | Anticipates bleeding during pubectomy |
| Pubourethral stump angle (PUA) | Not measurable | Measured on sagittal T2 | Independent predictor of elaborate approach[9][23] |
| Relationship to rectum | Not assessed | Clearly delineated | Critical for avoiding rectal injury during dissection |
The Pubourethral Stump Angle (PUA)
The PUA was first described by Horiguchi et al. (2018) and tested in an independent retrospective cohort of 184 men (online 2025; issue 2026).[9][23]
- Pubourethral stump length (PUL). The distance between the distal end of the proximal urethral stump and the lower border of the inferior pubic ramus, measured on sagittal T2.
- Pubourethral stump angle (PUA). The angle between the long axis of the pubis and the line connecting the distal end of the proximal urethral stump to the lower border of the inferior pubic ramus, measured on sagittal T2.
A smaller (lower) PUA indicates the proximal urethral stump has been displaced superiorly and posteriorly behind the pubic symphysis, meaning the prostatic apex is hidden behind the bone, inaccessible from a simple perineal approach without pubectomy. A larger PUA indicates the proximal stump remains relatively accessible below the pubic ramus, amenable to simple perineal mobilization ± corporal splitting.
Original study (Horiguchi 2018, n = 74):[9] 28 patients required a simple perineal approach (mobilization ± corporal splitting); 46 required an elaborate approach (inferior pubectomy or abdominoperineal with rerouting). On univariate analysis, disruption at the prostate apex, greater urethral gap length, longer PUL, and lower PUA were all significantly associated with an elaborate approach. On multivariate analysis, only low PUA was an independent predictor. Overall urethroscopic success (no recurrent stricture) was 94.6%.
Validation study (Horiguchi 2026, n = 184):[23] An elaborate approach (step 3 or higher) was required in 70 patients (38.0%). On multivariate analysis, two independent predictors emerged:
- Smaller PUA. OR 0.95 per degree (95% CI 0.94–0.98, p < 0.0001)[23]
- Prior transurethral treatment. OR 2.77 (95% CI 1.16–6.65, p = 0.02).[23] The combined model, incorporating both predictors, had AUC 0.782; prior treatment was associated with complexity.
MRI prediction of erectile dysfunction
Narumi 1993 (n = 27), an early MRI–ED correlation study, identified three significant MRI variables predicting permanent impotence:[22]
- Avulsion of the corpus cavernosum
- Superior and/or lateral prostatic displacement
- Separation of the corporeal body
The study estimated a 95% probability of persistent ED with cavernous avulsion plus superior/lateral displacement, and 83% probability of normal potency without those findings at 12 months.[22]
Koraitim 2013 (n = 90) identified three independent multivariate predictors of post-PFUI ED:[24]
- Diastasis of pubic symphysis. OR 15.9 (the strongest predictor)[24]
- Lateral displacement of prostate. OR 6.9[24]
- Long urethral gap. OR 2.0[24]
Dixon 1992 (n = 18) further demonstrated that MRI reveals injuries at multiple locations along the erectile pathway, including sacral and ischial fractures (which may damage the pudendal nerve) and cavernous body avulsions, which is additional information beyond conventional urethrography.[20]
MRI impact on surgical planning
Narumi 1993 demonstrated that MRI findings prompted a change in the clinically planned surgical approach from perineal to combined perineal and transpubic in 7 of 27 patients (26%).[22]
Koraitim and Reda 2007 (n = 21) confirmed that MRI:[21]
- Correctly estimated the length of the urethral defect in 86%[21]
- Correctly demonstrated the type and degree of prostatic displacement in 89%[21]
- Precisely delineated the site and density of scar tissue
- Revealed paraurethral false tracks in 3 of 21 patients (14%)[21]
- Demonstrated cavernous avulsion and lateral prostatic displacement in all 6 patients with posttraumatic impotence
Radiographic predictors of surgical complexity
| Prediction System | Modality | Key Parameter | Cutoff | Predictive Value |
|---|---|---|---|---|
| Horiguchi PUA[9][23] | MRI (sagittal T2) | Pubourethral stump angle | Lower PUA → elaborate | AUC 0.782 for PUA + prior treatment (184 men) |
| Koraitim Gapometry / Urethrometry Index[25] | Urethrography | Gap length / bulbar urethral length | >0.35 → elaborate | AUC 0.979; 91% specificity, 95% PPV |
| Wang PUVD[54] | MRI urethrography | Gap distance + pubourethral vertical distance (PUVD) | Longer gap, shorter PUVD → pubectomy | Independent predictors on multivariate analysis; ROC accuracy 83.7% (gap) and 67.4% (PUVD) in 43 men |
| Yepes PUS Position[26] | Urethrography (RGU/VCUG) | Proximal stump above vs. below inferior pubic symphysis | Above → elaborate | OR 66 (p < 0.001) |
| Scherñuk 2026[27] | Urethrography | Any of the tested radiographic predictors | Any positive criterion | 100% sensitivity, 42.3% specificity (36 evaluable men) |
The 2026 external validation by Scherñuk et al. excluded 45/81 patients (often because the bladder neck did not open), leaving 36 evaluable cases. It found that radiological predictors from urethrography alone show limited reliability and accuracy, though the Yepes PUS position correlated with complexity. The absence of any radiological criteria may help identify straightforward cases (100% of patients without predictors underwent non-complex repairs).[27]
Koraitim's 2008 analysis of 120 patients defined the index as urethral gap length divided by bulbar urethral length; mean ratios were 0.21 for simple and 0.64 for elaborate repairs, with simple perineal repair usually used for gaps below one-third of bulbar length.[52] His 2009 analysis of 121 patients used the same denominator and identified a 0.35 cutoff for predicting simple versus elaborate or transpubic repair (91% specificity, 95% positive predictive value).[25]
Acute Management
For suprapubic drainage in the unstable polytrauma patient and the other organs' temporizing options at a damage-control laparotomy, see Damage Control in Genitourinary Trauma.
Suprapubic Tube (SPT) — Preferred
AUA recommends SPT placement as preferred initial management for most PFUI (Statement 20b; Recommendation, Grade C); ACS 2025 also favors initial SPT for complete injury:[1][3]
- SPT is the usual initial drainage strategy for complete male PFUI; selected stable patients may undergo endoscopic realignment. A bladder-neck or prostatic-urethral laceration requires prompt injury-specific repair rather than routine deferral.[37]
- Incomplete injuries may be managed with SPT or urethral catheterization (single gentle attempt by experienced personnel; stop immediately if resistance or new bleeding).
- A ≥14 Fr Foley SPT is preferred for durable drainage and exchange; a small pigtail catheter may need upsizing if used initially.[1][3]
- Pelvic hematoma or concomitant bladder injury may displace or underfill the bladder. Use image guidance and, when needed, needle aspiration for percutaneous SPT; choose open placement under direct vision if percutaneous access is unsafe.[1][37]
- When realignment is selected, an endoscopic approach is preferred over open realignment because of operative burden and blood loss.[37]
Primary Endoscopic Realignment (PER)
PER places a catheter across the acute urethral injury under endoscopic guidance. Approaches include retrograde cystoscopy alone or simultaneous antegrade and retrograde cystoscopy when additional access is needed.[3][37] The evidence is conflicting: the EAU gives a weak recommendation to perform early endoscopic realignment in male PFUI when feasible,[37] whereas ACS favors SPT for complete injury and AUA prefers SPT for most PFUI. AUA permits primary realignment in stable patients (Statement 22; Option, Grade C) and advises against prolonged endoscopic attempts .[3] The EAU advises catheterization for 3 weeks after realignment of a partial injury and 6 weeks after a complete injury, with voiding urethrography at removal; avoid balloon traction to protect the remaining bladder-neck sphincter. It strongly recommends against repeating endoscopic treatment after failed realignment.[37] For the full atlas treatment (dual endoscopic, fluoroscopic IR, and magnetic-catheter variants, technique steps, catheter protocols, and comparative outcomes), see Primary Endoscopic Realignment (PER).
In the 26-center prospective TURNS cohort, 69 of 106 patients had complete PFUI and a failed retrograde cystoscopic catheter attempt; 37 underwent PER and 32 received SPT. Obstruction developed in 36/37 (97%) versus 30/32 (94%; p = 0.471). Urethroplasty was reported for 31 PER patients and 29/32 SPT patients (91%; p = 0.784).[10]
A 2025 meta-analysis (Owen et al., 11 nonrandomized comparative studies, 769 patients) found no statistically significant differences between primary realignment and SPT with delayed urethroplasty: stricture OR 1.23 (95% CI 0.24–6.37), incontinence OR 1.02 (0.59–1.79), and ED OR 0.97 (0.64–1.46). Wide confidence intervals and treatment-selection bias preclude a conclusion of equivalence.[11]
The ACS Best Practices Guidelines (2025) state: "No strong evidence exists to indicate that PER significantly impacts stenosis rates or complexity of future urethral reconstruction following complete PFUI." However, for partial injuries, successful PER may lower the stenosis rate. The guideline advises that any PER attempt be made by a urologist within a few days of injury in a hemodynamically stable patient, and that open realignment has no role because of substantially increased complications. It reports urethral stenosis rates well over 90% after complete injury from pelvic fracture or straddle trauma, usually manifesting within the first year.[1]
Delayed Definitive Reconstruction
Timing
The AUA Urethral Stricture Disease Guideline recommends that definitive reconstruction be planned only after major injuries stabilize and the patient can be safely positioned for urethroplasty. This is usually 3–6 months after trauma; no optimal time has been established (range 6 weeks to 4 yr).[12]
The EAU (2026) makes three timing recommendations for male PFUI. Do not perform immediate urethroplasty (under 48 hours; strong), because of poor visualization, bleeding of about 3 L on entering the pelvic hematoma, and higher rates of stricture, incontinence and ED. Early urethroplasty (2 days to 6 weeks) may be considered for complete disruption in selected patients: stable, short gap, soft perineum and able to lie in lithotomy . For complete disruption, suprapubic diversion with urethroplasty at least 3 months after injury is the standard ; at that point the hematoma has resolved and the prostate has descended toward its normal position.[37]
Scarberry and Gómez (2018), in a retrospective cohort of 39 patients, reported that early reconstruction at 3–6 weeks (when the perineum is soft, the fracture is stable, and associated injuries permit lithotomy positioning) was feasible; the study did not detect differences from a ≥12-week delay. Overall cohort outcomes were failure 5.1%, incontinence 7.7%, ED 56.4%, with no significant differences between early and delayed groups.[13]
Preoperative preparation
- Imaging. Combined antegrade / retrograde urethrography; add pelvic MRI for complex or inadequately defined anatomy (above)
- Urine culture and prophylaxis. Obtain a urine culture before reconstruction, treat bacteriuria or catheter colonization according to susceptibility, and give intraoperative antimicrobial prophylaxis.[66]
- Cystoscopy. Flexible cystoscopy through the SPT to assess the proximal stump, bladder neck competence, and any periurethral pathology. In revision surgery after a chronically indwelling suprapubic catheter, intraoperative cystoscopy can also identify eggshell calculi that have formed on the catheter balloon and help confirm the prostatic apex as the correct proximal anastomotic site.[46]
- Bowel planning. When a urethrorectal fistula or bowel procedure is anticipated, coordinate preparation and diversion decisions with the colorectal team
- Positioning. Confirm that lithotomy is safe given orthopedic injuries. Exaggerated lithotomy is used for direct perineal exposure and is associated with lower-limb neuropraxia, rhabdomyolysis and acute renal failure; inadequate gel padding and operations longer than five hours increase risk.[65]
The Webster / Ramon Progressive Perineal Approach — Detailed Technique
The technique described by Webster and Ramon (1991) in 74 patients with defects ranging from 1.5 to 7 cm achieved a 96% success rate using sequential ancillary maneuvers as needed.[14]
Step 1 — Exposure and bulbar urethral mobilization
- Midline perineal incision from the posterior scrotal raphe to a point just anterior to the anus.
- The bulbospongiosus muscle is divided in the midline raphe, exposing the corpus spongiosum and bulbar urethra.
- The bulbar urethra is mobilized circumferentially from the perineal body distally to the penoscrotal junction, which provides 2–3 cm of additional urethral length. A gloved finger in the rectum can guide posterior dissection of the urethra off the perineal body and reduce the risk of rectal injury during this step.[51]
- The urethra is transected at the level of the obliterative stricture; the distal end is spatulated ventrally.
- Excise the fibrotic scar toward the prostatic stump. Horiguchi et al. advise preserving the remaining membranous urethra and limiting energy use near the sphincter during this dissection to protect continence.[62]
- The proximal stump is identified, often by palpating a metal sound passed through the SPT into the prostatic urethra.
- The proximal stump is spatulated dorsally to create a wide anastomotic opening.
- If a tension-free anastomosis can be achieved at this point, the spatulated ends are anastomosed over a catheter using interrupted absorbable sutures (typically 4-0 or 5-0 PDS / Vicryl), placed at the 12, 3, 6, and 9 o'clock positions. One described setup uses eight 4-0 PDS sutures (4 cardinal positions plus 4 in between), bending the needle into a J-shaped "ski" configuration for proximal-stump access and securing each suture on a serially numbered mosquito clamp so orientation is preserved for tying in order; a long-armed nasal speculum can aid exposure for this suture placement.[45]
- In Fu et al.'s 301-patient cohort, simple perineal anastomosis was performed in 103 (34.2%); in Webster and Ramon's separate 74-patient cohort, 66 required one or more sequential maneuvers.[14][16]
Step 2 — Corporal body separation (crural splitting)
If mobilization alone is insufficient:
- The intercrural septum is divided sharply.
- The corpora cavernosa are separated laterally.
- The bulbar urethra is routed between the separated corpora, shortening the distance by straightening its course.
- Provides an additional 1–2 cm of effective length.
- Used in 17–36% of cases.[4][15][16] The Fu/Xu series reported an 86.5% success rate with corporal splitting.[16]
Step 3 — Inferior pubectomy
If Steps 1–2 are insufficient. A described sub-classification splits this step into 3a (periosteal elevation only) and 3b (bone removal if 3a proves insufficient); reassessing after 3a alone can avoid an unnecessary bone wedge.[55]
- The inferior margin of the pubic symphysis is exposed by dissecting the periosteum. In the described Step 3a, a midline periosteal incision is made with diathermy and the periosteum is elevated bilaterally, for example with the electrocautery tip bent to 45° and slid beneath it; after this exposure the surgeon can reassess whether a bone wedge is still needed.[55]
- A wedge of bone is removed from the inferior border of the symphysis using an oscillating bone saw or rongeur. A described alternative (Step 3b) uses a gouge directed vertically for a standard pubectomy or more horizontally for a deeper resection, with loosened fragments removed by rongeur or forceps; a suprapubic bougie (or a gloved rectal finger to feel its tip at the prostatic apex when it is not palpable perineally) helps confirm the target before bone removal.[55]
- The periosteum on the pelvic (deep) surface is carefully preserved to protect the dorsal venous complex and avoid catastrophic hemorrhage.
- Provides direct access to the prostatic apex, which may be displaced superiorly behind the pubic bone.
- Effectively shortens the distance between the urethral stumps by removing the bony obstacle.
- Used in 10–32% of cases.[4][15][16] Success rate 84.2% in Fu/Xu.[16]
- Pratap et al. observed no pubic-resection complication or bowel herniation in 21 selected transpubic repairs at a mean 28-month follow-up.[29]
Step 4 — Supracrural urethral rerouting
Reserved for the most complex, long-gap defects:
- The urethra is mobilized extensively and rerouted around one side of the corpora cavernosa (supracrurally) rather than between them.
- Provides the maximum possible urethral length gain.
- Used in only 2–5% of cases.[4][15][16]
- Kizer / Brandes reported recurrence in 3 of only 4 rerouted cases.[15]
- However, Li et al. 2025 (n = 37) reported 91.2% success (31/34 with follow-up) using one-sided rerouting via a perineal approach with inferior pubectomy, particularly advocating this technique for young patients and children to minimize secondary trauma to the corpora cavernosa.[17]
The Sa / Xu Progressive Transperineal Strategy — the largest series
Sa et al. 2021 (n = 1,637), a large single-center PFUI series, reported a 92.4% success rate (1,363/1,475 with follow-up) using a progressive transperineal anastomotic strategy:[28]
- After full mobilization of the distal bulbomembranous urethra, the stenotic urethra is transected directly at the proximal margin of the stenotic segment to expose the proximal disrupted end.
- If the stenosis location is too deep to fully mobilize (complex cases), urethral transection is selected at the distal margin of the stenotic urethra instead.
- Distal and proximal disrupted urethras are then trimmed and anastomosed without tension.
- Among 112 failed patients: 10 received endoscopic urethrotomy, 99 underwent secondary / third anastomotic urethroplasty, 3 perineal skin flap urethroplasty.
- Incontinence. 8.5% (125/1,475 patients with follow-up after final successful urethroplasty).[28]
- De novo ED. Reported in 15 patients. The abstract reports 1.6% without the eligible erectile-function denominator; 15/1,637 cannot quantify de novo ED or exclude surgery-related ED.[28]
Abdominoperineal (Transpubic) Approach
Indications[29][30][31]
- Distraction defects >5 cm (some authors use >3 cm)
- Significant lateral or superior prostatic displacement not accessible perineally
- Failed prior perineal urethroplasty
- Associated urethrorectal fistula requiring tissue interposition
- Periurethral cavities, false passages, or open bladder neck
- Pediatric cases with complex anatomy
Technique (Pratap 2006)[29][30]
- Abdominal phase. Lower midline or Pfannenstiel incision; bladder mobilized; retropubic space entered.
- Pubic resection. Partial or complete pubectomy has been used in transpubic repairs to expose the prostatic urethra from above.[4][29] The 2026 EAU Urethral Strictures guideline strongly recommends against total pubectomy during abdominoperineal reconstruction because it has more bleeding, pelvic instability and dead space without added exposure.[64]
- Scar excision. Fibrotic tissue between urethral stumps excised under direct vision from both above and below.
- Perineal phase. Simultaneous perineal dissection mobilizes the bulbar urethra.
- Anastomosis. Spatulated urethral ends anastomosed through the subpubic route or, if needed, via supracrural rerouting.
- Tissue interposition. In cases with urethrorectal fistula, a gracilis muscle flap or rectus abdominis muscle flap is interposed between the repaired rectum and urethra.[31][32]
- Bladder neck repair. Performed when indicated by the actual injury. In this selected 25-patient cohort, 20 (80%) had bladder-neck laceration and underwent simultaneous repair.[30]
Outcomes
- Pratap 2006 (11 adults, 10 prepubescent boys): 20/21 (95%) had a wide anastomosis on postoperative cystourethrography, 2/21 (9.5%) developed postoperative incontinence, and 3/14 not classified as impotent after injury were reported impotent postoperatively. Mean stricture length was 5.2 cm and mean follow-up 28 months; sexual outcome assessment in this mixed-age cohort limits attribution.[29]
- Pratap 2006 (n = 25): 92% overall success; incontinence 4%; potency status unchanged by surgery.[30]
- Koraitim 1995 (n = 32 transpubic): 97% success.[5]
Management of Associated Urethrorectal Fistula (URF)
Associated URF is an uncommon, complex reconstructive problem.Associated URF is a complex reconstructive problem.[31][32]
Xu 2010 (n = 31) reported outcomes by approach:[31]
- Simple perineal. 4/4 (100%) success[31]
- Transperineal with inferior pubectomy. 16/18 (88.9%); the authors concluded it may be appropriate as a first-line procedure[31]
- Combined transpubic-perineal. 7/9 (77.8%) in Xu’s 31-patient series[31]
Guo 2017 (n = 32) specifically evaluated gracilis muscle interposition for PFUI with URF:[32]
- Overall success 91% (29/32)[32]
- One-stage repair with perineal anastomosis and corporal splitting: 17/18 (94%)[32]
- Perineal anastomosis, inferior pubectomy and corporal splitting: 12/14 (86%)[32]
- All 22 patients without any previous repair were successfully treated (100%)[32]
- Only 7/10 (70%) with prior failed urethroplasty and URF repair were cured[32]
- In Guo’s 32-patient single-arm series, a vascularized gracilis flap was interposed as a tissue barrier between the repaired urethra and rectum.[32]
For broader fistula context, see the Rectourethral Fistula article.
Robotic-Assisted Posterior Urethroplasty (RPU)
Robotic approaches have emerged as a viable option, particularly for radiation-induced posterior urethral stenosis and complex cases requiring abdominal access.[18][33][34]
Zhang / Zhao 2023 (n = 105), the largest RPU cohort:[33]
- Mean follow-up 18.7 mo
- 57.1% had prior pelvic radiation (predominantly post-prostate cancer treatment, not PFUI)[33]
- Techniques included EPA, bladder-neck resitting, Y-V plasty and BMG urethroplasty
- 39% required a combined abdominoperineal approach[33]
- ≥Clavien-Dindo grade 3 complications within 30 days: 6.7%[33]
- Incontinence requiring AUS 28.6%[33]
- Reintervention rate 24.8%[33]
Cavallo / Vanni 2021 (n = 12), combined robotic transabdominal and open transperineal:[18] mean age 65.9 yr (predominantly post-radiation, not PFUI); 66.7% required prostatectomy as part of the procedure; stenosis recurrence 16.7%; 75% required subsequent AUS.
Liu / Zhao 2022 (n = 9) was a single-port BMG feasibility series: eight patients had prostate-cancer treatment and one had trauma; median follow-up was 11.7 months.[34]
Most RPU series are dominated by radiation-induced posterior urethral stenosis rather than PFUI. For traumatic PFUI, the open perineal approach remains the standard; robotic assistance is reserved for complex cases requiring abdominal access.[18][33]
Outcomes of Posterior Urethroplasty
| Study | Year | n | Approach | Success | Follow-up | Key Findings |
|---|---|---|---|---|---|---|
| Koraitim[5] | 1995 | 78 (perineal) / 32 (transpubic) | Perineal + transpubic | 95% / 97% | Not reported in abstract (17 yr accrual period) | Author called anastomotic urethroplasty the gold standard; optical urethrotomy succeeded in 58%, in mild strictures with a persistent lumen |
| Webster / Ramon[14] | 1991 | 74 | Elaborated perineal | 96% | — | Sequential ancillary maneuvers |
| Johnsen / TURNS[4] | 2020 | 122 | 95% perineal, 5% abdominoperineal | 91% (no repeat intervention) | median 7.0 mo (IQR 3.2–18.7) | Angioembolization (p = 0.03) and defect length (p = 0.01) predict failure |
| Sa / Xu[28] | 2021 | 1,637 | Progressive transperineal | 92.4% (1,363/1,475) | — | 1,475 followed; 15 de novo ED events (eligible denominator unclear in abstract); incontinence after final successful urethroplasty 8.5% |
| Plamadeala / Lumen[19] | 2025 | 70 | Transecting (75.7%) + non-transecting EPA | 83.8% (10-yr RFS) | median 130 mo | Postop complications (HR 4.85) and extravasation (HR 6.36) predict recurrence |
| Fu / Xu[16] | 2009 | 301 | Perineal with sequential ancillary maneuvers | 87.4% overall | — | Simple perineal 89.3%; with pubectomy 84.2%; with rerouting 85.7% |
| Kizer / Brandes[15] | 2007 | 142 | Simplified perineal | 92% | >1 yr | Rerouting recurrence 3/4; corporal splitting 17%; pubectomy 10% |
| Pratap[29] | 2006 | 21 | Abdominoperineal transpubic | 95% patency | — | Mean stricture 5.2 cm; incontinence 9.5% |
| Pratap[30] | 2006 | 25 | Abdominoperineal transpubic | 92% | — | Incontinence 4%; potency unchanged |
| Scarberry / Gómez[13] | 2018 | 39 | Perineal (early ≤6 wk vs delayed ≥12 wk) | 94.9% | median 64 mo | No statistically detected difference in this small retrospective comparison; ED 56.4% overall |
| Zhang / Zhao[33] | 2023 | 105 | Robotic (mostly post-radiation) | — | 18.7 mo | 39% combined abdominoperineal; incontinence-AUS 28.6% |
| Horiguchi[62] | 2022 | 211 | Delayed anastomotic | 95.3% | median 48 mo | Greater blood loss independently predicted failure; patient-reported outcomes collected |
In the Horiguchi series from a Japanese referral center, success meant a lumen that admitted a flexible cystoscope without further treatment. Of the 80.1% of men assessed by questionnaire at a median 13 postoperative months, mean LUTS-related quality-of-life score improved from 2.8 to 0.9 (0 to 3 scale), EQ-5D from 0.63 to 0.81 and EQ-VAS from 54.4 to 76.6 (p < 0.0001 for each), and 94.7% were satisfied or very satisfied.[62]
Functional Outcomes and Complications
Erectile dysfunction
ED is a major long-term morbidity. The original pelvic trauma often causes impairment before reconstruction; urethroplasty can still cause new or worsened dysfunction, so document baseline function:[1][2][5][19][28]
- ED rates after PFUI. The EAU cites approximately 34% erectile dysfunction following PFUI unrelated to urethroplasty[37]
- New ED after reconstruction. Koraitim (1995) reported 2.5%; Sa 2021 reported 15 events, with an incompletely specified denominator in the abstract[5][28]
- Plamadeala 2025 assessed erectile function in 49 of 70 men; 97.9% of that assessed subgroup had impairment after trauma. Its results section reports 16.3% improving after repair and its abstract reports 12.2%; the discrepancy limits inference beyond the assessed subgroup[19]
- The ACS Best Practices Guidelines (2025) report ED rates of 20–35% after severe urethral injury[1]
In a 27-patient PFUI MRI cohort, cavernous injury and superior/lateral prostatic displacement were associated with persistent ED at 12 months; a separate 90-man retrospective series also associated lateral prostatic displacement with ED.[22][24] In a 92-man multicenter PFUI reconstruction cohort with median 5.6-month follow-up, 19/44 postoperative questionnaire respondents (43%) reported ejaculatory difficulty.[71]
Urinary incontinence
- Postoperative incontinence estimates have different definitions: ACS guidance cites 15–20% after severe urethral injury.[1] Scarberry reported incontinence in 3/39 patients (7.7%) after delayed repair.[13] Plamadeala reported de novo incontinence in 6.6% of the 61 men assessed for urinary continence within a 70-man primary-repair cohort.[19] Sa reported incontinence after final successful repair in 125/1,475 followed patients (8.5%), without an incident-incontinence denominator.[28]
- In Horiguchi's 211-man delayed-repair series, 101/169 questionnaire respondents (59.8%) reported no pad use at a median 13 postoperative months.[62]
- In Cavallo’s selected 12-patient robotic/open reconstruction series, 4/12 (33.3%) developed new SUI, while 9/12 (75%) ultimately received an AUS; these are different outcomes[18]
- In a small retrospective series of 15 men with a cystoscopically or radiographically open bladder neck before posterior urethroplasty, 6 were continent and 8 incontinent afterward (1 received simultaneous AUS placement); mean bladder-neck/prostatic-urethral opening length was 0.9 cm in the continent group versus 1.68 cm in the incontinent group.[58]
Stricture recurrence
- Outcomes after posterior urethroplasty differ by endpoint: Johnsen found 111/122 (91%) without repeat intervention[4]; Koraitim reported 95% perineal and 97% transpubic anastomotic success[5]; Scarberry found 2/39 (5.1%) stricture failures[13]; Fu reported 38/301 (12.6%) failures defined by postoperative instrumentation[16]; and Plamadeala found 11/70 (15.8%) symptomatic recurrences requiring intervention[19].
- Among the 11 men with recurrence in a 70-man primary-repair cohort, median time to recurrence was 3 months (IQR 2–5 mo).[19]
- 10-year recurrence-free survival: 83.8%[19]
- Salvage of a recurrent post-anastomotic stricture. For a short (<1 cm), nonobliterative adult recurrence after EPA, the 2026 EAU guideline weakly recommends no more than two DVIU or dilation attempts if durable patency is intended; it weakly recommends repeat urethroplasty for patients who prefer reconstruction over palliative endoluminal treatment or diversion.[64] In a pediatric perineal anastomotic series (n = 65), recurrence developed in 7 (10.8%), always at the anastomosis and within the first postoperative year; 5 of the 7 were salvaged endoscopically and the other 2 by repeat perineal anastomotic repair.[41] In a related pediatric series, visual internal urethrotomy for a short (<1 cm) recurrence after perineal anastomotic urethroplasty succeeded in 20 of 22 (90%), with a mean 98-month follow-up; strictures not responsive to urethrotomy require repeat urethroplasty, with or without buccal mucosal grafting.[42]
Ischemic Stenosis vs. Technical Restenosis
Ischemic stenosis of the mobilized corpus spongiosum is one described mechanism of posterior urethroplasty failure: after extensive mobilization, the spongiosum may depend on retrograde flow from the glans dorsal-artery arborization.[43] One center's experience describes a selective workup to identify patients at risk for this ischemic pattern — dorsal penile nerve injury, a prior failed reconstruction elsewhere, a lateral-impact pelvic fracture, or a "wind-swept" fracture pattern — with pudendal duplex ultrasonography, reserving pudendal angiography for abnormal duplex parameters. In that experience, reliable reconstruction was possible whenever at least one internal pudendal artery was patent or reconstituted; the group at risk for ischemic stenosis was bilateral complete internal-pudendal obstruction, for whom the center performed penile arterial revascularization before urethral reconstruction.[43] SeePenile Arterial Revascularization for technique and a 2012 outcomes series in post-PFUI arteriogenic ED.[44]
A related distinction is drawn between bulbar urethral ischemic stenosis (a long, near-obliterated ischemic stricture with the bulbar urethra's length preserved but narrowed) and bulbar urethral ischemic necrosis (BUIN), loss of a long segment or the entire bulbar urethra from vascular insufficiency, most often after a failed prior PFUI repair. After anastomotic urethroplasty, the urethra depends on retrograde flow from the dorsal penile arteries once the lateral circumflex and bulbourethral vessels are sacrificed by mobilization and transection; over-mobilization, prior hypospadias repair, multiple prior operations, and injury to the dorsal penile arteries during crural separation or pubectomy are described contributors. One imaging heuristic holds that penile and bulbar urethral lengths should be roughly equal, with the penoscrotal junction as their midpoint; a bulbar segment that appears substantially shorter than the penile urethra on imaging may suggest necrosis rather than simple stenosis.[57]
Predictors of recurrence and operative complexity
- Postoperative complications within 90 days were associated with stenosis recurrence (HR 4.85, p = 0.007)[19]
- Persistent urinary extravasation at the second RUG was associated with stenosis recurrence (HR 6.36, p = 0.006)[19]
- Pelvic artery angioembolization (p = 0.03). Likely a marker of more severe pelvic vascular injury[4]
- Longer distraction defects (p = 0.01)[4]
- Prior transurethral treatment. OR 2.77 for elaborate approach[23]
- Prior failed endoscopic procedures may complicate subsequent urethroplasty[5]
MRI Findings to Inform Surgical Planning
| MRI Finding | Surgical Implication | Predicted Approach |
|---|---|---|
| Large PUA, short gap, no lateral displacement | Simple perineal repair may be feasible | Steps 1–2[9][23] |
| Small PUA, moderate gap, proximal stump behind pubis | Inferior pubectomy likely required | Step 3[9][23] |
| Very small PUA, long gap, significant lateral / superior prostatic displacement | Abdominoperineal approach may be needed | Step 4 or transpubic[9][23][24] |
| Cavernous avulsion + lateral prostatic displacement | Structural injury associated with ED in a small historical cohort; assess function and counsel with uncertainty | Any approach; ED counseling[22] |
| No cavernous avulsion, no lateral displacement | — | Any approach; favorable prognosis[22] |
| Periurethral false passages or cavitation | Anticipate complex dissection; consider tissue interposition | Elaborate perineal or transpubic[21] |
| Prior transurethral treatment | 2.77× increased odds of elaborate approach | Prepare for Steps 3–4[23] |
Special Considerations
Pediatric PFUI
Children with PFUI require attention to pelvic growth and corporal development during reconstruction.[17][35][36] For posterior injury, the EAU Paediatric Urology guideline (2026) weakly recommends either initial SPT with delayed repair or primary transurethral realignment.[67] In one randomized trial of 40 boys with complete PFUI, 14/20 initially voided after realignment but all 14 later required urethroplasty; realignment led to more procedures and longer time to normal voiding than SPT alone, without a detected difference in later reconstructive complexity or outcomes.[68]
- Zhang / Xu 2006 (n = 24 boys, age 7–14). Transperineal-inferior pubic approach yielded the best results (90% success) compared to simple perineal (60%) or transpubic-perineal (77.8%). However, 3 of 9 patients treated with the transpubic-perineal approach walked with an abnormal gait postoperatively.[35]
- Wang / Guo 2020 (n = 22 boys, age 2–14). 90.9% overall success (20/22). The transperineal inferior pubic approach or simpler procedures were used in 20/22 boys without completely removing or incising the pubis; the combined transpubic-perineal approach was used in 2/22 boys with very long defects, and both succeeded.[36]
- Li 2025. In a retrospective 37-patient series of long-segment, complex posterior strictures, the authors proposed one-sided urethral rerouting for young patients, especially children, to limit additional corporal trauma.[17]
- Anterior sagittal trans-anorectal approach (ASTRA). Described as an alternative exposure for pelvic fracture with severe urethral dislocation and longer (2–3 cm) defects, as an alternative to pubectomy/symphysiotomy; outcome data are limited to a single small series.[39]
- Sreeranga 2022 (n = 192, the largest pediatric PFUI series), from the same center as the adult Sa/Xu series above: 181 boys and 11 girls, ages ≤18 (primary vs redo cases 47% vs 53% in boys). Transperineal anastomotic urethroplasty was used in 88.4% of boys and transpubic urethroplasty in 9.4%; overall TPAU success was 81.2% in boys (88.3% for primary cases) and TPU success 64.7%, while girls treated with TPU had 100% success. Follow-up was unavailable for 74 boys and four girls. Secondary procedures (endoscopic urethrotomy or redo surgery) were needed in 39 boys and 1 girl.[59]
- General pediatric technique and management principles have been summarized as follows: as in adults, delayed repair after several months allows the scar to mature and the pelvic hematoma to resolve, letting the bladder descend and often converting an apparently large acute defect into a smaller one; reevaluating gap length with imaging and cystourethroscopy closer to the repair date is recommended. Excision with primary anastomosis is described as typically feasible even for severe defects without tension concerns; additional length can be obtained first by partial pubectomy, then by mobilizing the bladder through an abdominal incision if needed. A suprapubic tube is placed when urethral drainage cannot be achieved acutely, and the perineal-repair catheter is left about 2–3 weeks. Postoperative complications (urinary retention, incontinence, penile shortening, ED) occur at lower rates than in adults with the same injury pattern; in one pediatric cohort, stricture recurred in about 10%, incontinence occurred in up to 20%, and ED occurred in up to half, with figures varying by series.[60]
- Erectile dysfunction risk. Among 60 responding participants assessed a median of 13 years after trauma, 28 (47%) had erectile dysfunction at puberty (1 in 2 children, by the authors’ framing); urethral gap length 2.5 cm or greater and lateral prostatic displacement were the independent predictors on multivariate analysis, and the cause was arteriogenic in most affected boys on duplex ultrasound. These findings support counseling about ED risk in relation to gap length and lateral prostatic displacement, while keeping the 47% estimate specific to this follow-up cohort.[40]
Female PFUI
Female injuries follow a different pathway: evaluate with cystourethroscopy and vaginoscopy. The EAU strongly recommends repair of female PFUI within seven days once the patient is hemodynamically stable, whereas complete male PFUI usually follows suprapubic diversion and deferred urethroplasty. In the EAU's summary of published female PFUI reports, incontinence occurred in 9% after early repair and 31% after delayed repair; vaginal stenosis occurred in 0% and 4%, respectively.[37] Bladder-neck/prostatic lacerations in males also require prompt injury-specific repair, rather than routine deferral.[1][6][37]
A high index of suspicion is needed: female urethral injury is easily missed because catheterization of the short, straight female urethra is often possible despite the injury. Suspect urethral injury with unstable or multiple pelvic fractures, pelvic-ring or sacral injury, vaginal laceration, blood at the introitus, urethrorrhagia, labial swelling, retention, or difficulty passing a catheter. A 25-patient series found the injury could be missed on initial assessment, and vaginal laceration has been reported in most cases.[47] In a systematic review of 158 women with pelvic-fracture urethral injury, radiologic studies (RUG/VCUG) diagnosed only 29% of reported cases, and physical examination with or without attempted catheterization diagnosed 21%.[48]
When vaginal cicatrization from the original injury restricts surgical access, a deep posterolateral episiotomy extending across the bulbospongiosus and transverse perineal muscles (and, if needed, the levator muscle) has been described to improve working space, with layered repair of the divided muscles and vaginoplasty when needed to restore usable vaginal caliber.[49][50] Reported adjuncts for severe introital contracture include a thigh flap similar to the Singapore fasciocutaneous flap and, in another case, leaving a deep vaginal incision open under a glass vaginal mold for four weeks followed by frequent self-dilation.[49][50]
For selected female PFUI, an abdominal route has been described: enter the retropubic space extraperitoneally, use posterior/superior pubectomy for exposure, open the bladder neck under suprapubic-nephroscope guidance, and identify the distal urethral end over a dilator passed from the meatus, with a tension-free bladder-neck-to-urethral-mucosa anastomosis over a 14 Fr silicone catheter using six 5-0 polydioxanone sutures (posterior sutures tied before the catheter is passed across the join). For an associated urethrovaginal fistula, a transvaginal guidewire localizes the tract, the fistula is closed, and an omental flap is interposed between the urethra and anterior vaginal wall. These are the source authors' operative steps, without a comparative female outcome series.[56]
Associated injuries
PFUI rarely occurs in isolation:[1][6]
- Bladder injury. Concomitant bladder injury is reported in 15% of posterior urethral injuries[3]
- Rectal injury. Up to 5% of cases in the EAU text (requires rectal and vaginal examination)[37]
- Vascular injury. 13% required pelvic artery embolization in the TURNS series[4]
- Orthopedic injuries. Multiple fractures, acetabular fractures and lower-extremity injuries may delay positioning for urethroplasty. AUA permits SPT placement during pelvic ORIF ; its discussion finds no demonstrated increase in hardware infection, with gross fecal contamination or open fractures as possible exceptions.[3] Pelvic-fixation hardware placed near the urethra or bladder can also complicate later reconstructive surgery and, rarely, erode into the urinary tract years afterward (see Bladder Trauma — Complications)
Impact of prior endoscopic interventions
The AUA Urethral Stricture Disease Guideline (2023) explicitly cautions against repeated endoscopic maneuvers: "Repeated endoscopic maneuvers including intermittent catheterization and blind 'cut to the light' procedures should be avoided since they are rarely successful." Koraitim warned that repeated urethrotomy of a long fibrous segment between a widely distracted prostatic and bulbar urethra "would not only have a poor result but, by jeopardizing the elasticity of the anterior urethra, it also may undermine the chance for subsequent anastomotic urethroplasty."[5][12]
The Horiguchi 2026 PUA validation study found an association: prior transurethral treatment was associated with an elaborate approach (OR 2.77, p = 0.02).[23]
However, Kizer et al. found that early urethral realignment was associated with successful subsequent reconstruction in 100% (17/17) of patients in whom it was achieved, and the subsequent repair tended to be more straightforward.[15]
Management Algorithm — Male Posterior PFUI
Resuscitation takes priority; the female and bladder-neck injury exceptions above require separate planning.
| Phase | Action | Key Points |
|---|---|---|
| Acute (minutes–hours) | Establish urinary drainage | SPT preferred for complete PFUI; gentle single catheter attempt for incomplete; RUG before instrumentation when clinically feasible; do not delay life-saving care[1][2][3] |
| Acute (days) | Consider PER | Only if patient hemodynamically stable; no proven benefit over SPT for complete injuries; may benefit partial injuries[1][10][11] |
| Subacute (weeks–months) | Stabilize associated injuries | Orthopedic fixation, soft-tissue healing; urology follow-up for ED / incontinence assessment[1] |
| Preoperative (3–6 mo)[12] | Imaging and planning | Combined antegrade / retrograde urethrography; selective MRI for complex anatomy[7][9][21][23] |
| Definitive repair | Delayed perineal anastomotic urethroplasty | Sequential ancillary maneuvers as needed; abdominoperineal approach for complex cases[14][15][18][28][29] |
| Postoperative | Check the anastomosis before catheter removal, then follow long term | In one 70-man primary-repair cohort, pericatheter RUG was obtained at about 14 days and repeated weekly if extravasation persisted.[19] Monitor for recurrence (median time to recurrence 3 months among the 11 recurrent cases), erectile dysfunction and incontinence; consider AUS after incontinence is stable.[13][19] |
AUA recommends monitoring for urethral stricture, erectile dysfunction and incontinence for at least one year after urethral injury (Statement 23; Recommendation, Grade C). Uroflowmetry, RUG and cystoscopy are used as indicated.[3]
Key Takeaways
- Most complete male PFUI injuries are initially diverted with SPT and reconstructed after stabilization; selected patients may have earlier repair or endoscopic realignment. Female PFUI and bladder-neck lacerations require different timing.[1][37]
- MRI supplements urethrography in complex cases.[23] The PUA/prior-treatment model had AUC 0.782 in a retrospective validation cohort.[23]
- Sequential perineal maneuvers aim for a tension-free anastomosis; selected complex cases need abdominal access. Success definitions, follow-up and injury severity vary across series.[4][14][28]
- Contemporary realignment evidence conflicts: Owen’s 2025 meta-analysis found no stricture difference, whereas Wen and Jiang’s 2025 meta-analysis favored primary realignment. Both pooled heterogeneous nonrandomized cohorts; the prospective TURNS complete-PFUI cohort found no lower obstruction rate with realignment.[11][63][10]
- Record baseline erectile and continence function and discuss both trauma-related morbidity and new dysfunction after reconstruction.[19]
Videos
References
-
Johnsen N, Wessells H, Archer-Arroyo K, et al. ACS TQP Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons; 2025.
-
Horiguchi A. Management of male pelvic fracture urethral injuries: review and current topics. Int J Urol. 2019;26(6):596-607. doi:10.1111/iju.13947.
-
Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
-
Johnsen NV, Moses RA, Elliott SP, et al. Multicenter analysis of posterior urethroplasty complexity and outcomes following pelvic fracture urethral injury. World J Urol. 2020;38(4):1073-1079. doi:10.1007/s00345-019-02824-5.
-
Koraitim MM. The lessons of 145 posttraumatic posterior urethral strictures treated in 17 years. J Urol. 1995;153(1):63-6. doi:10.1097/00005392-199501000-00024.
-
Coccolini F, Moore EE, Kluger Y, et al. Kidney and uro-trauma: WSES-AAST guidelines. World J Emerg Surg. 2019;14:54. doi:10.1186/s13017-019-0274-x.
-
Horiguchi A, Edo H, Shinchi M, et al. Role of magnetic resonance imaging in the management of male pelvic fracture urethral injury. Int J Urol. 2022;29(9):919-929. doi:10.1111/iju.14779.
-
da Silva Gaspar SR, Ferreira ND, Oliveira T, et al. Magnetic resonance imaging and pelvic fracture urethral injuries. Urology. 2017;110:9-15. doi:10.1016/j.urology.2017.06.041.
-
Horiguchi A, Edo H, Soga S, et al. Pubourethral stump angle measured on preoperative magnetic resonance imaging predicts urethroplasty type for pelvic fracture urethral injury repair. Urology. 2018;112:198-204. doi:10.1016/j.urology.2017.09.038.
-
McCormick BJ, Keihani S, Hagedorn J, et al. A multicenter prospective cohort study of endoscopic urethral realignment versus suprapubic cystostomy after complete pelvic fracture urethral injury. J Trauma Acute Care Surg. 2023;94(2):344-349. doi:10.1097/TA.0000000000003774.
-
Owen K, Joe W, Palgunadi IN, Soebhali B. A systematic review and meta-analysis of surgical approaches in pelvic fracture-associated urethral injury: primary endoscopic realignment versus delayed urethroplasty. World J Urol. 2025;43(1):603. doi:10.1007/s00345-025-05994-7.
-
Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
-
Scarberry K, Bonomo J, Gómez RG. Delayed posterior urethroplasty following pelvic fracture urethral injury: do we have to wait 3 months? Urology. 2018;116:193-197. doi:10.1016/j.urology.2018.01.018.
-
Webster GD, Ramon J. Repair of pelvic fracture posterior urethral defects using an elaborated perineal approach: experience with 74 cases. J Urol. 1991;145(4):744-8. doi:10.1016/s0022-5347(17)38442-2.
-
Kizer WS, Armenakas NA, Brandes SB, et al. Simplified reconstruction of posterior urethral disruption defects: limited role of supracrural rerouting. J Urol. 2007;177(4):1378-81; discussion 1381-2. doi:10.1016/j.juro.2006.11.036.
-
Fu Q, Zhang J, Sa YL, Jin SB, Xu YM. Transperineal bulboprostatic anastomosis in patients with simple traumatic posterior urethral strictures: a retrospective study from a referral urethral center. Urology. 2009;74(5):1132-6. doi:10.1016/j.urology.2009.05.078.
-
Li H, Jin C, Li S, et al. Urethral rerouting around one side of corpora cavernosus via a perineal approach for treating long-segment, complex posterior urethral strictures. World J Urol. 2025;43(1):485. doi:10.1007/s00345-025-05825-9.
-
Cavallo JA, Vanni AJ, Dy GW, et al. Clinical outcomes of a combined robotic, transabdominal, and open transperineal approach for anastomotic posterior urethroplasty. J Endourol. 2021;35(9):1372-1377. doi:10.1089/end.2020.0973.
-
Plamadeala N, Waterloos M, Waterschoot M, Lumen N. Posterior urethroplasty for pelvic fracture urethral injuries: risk factors for recurrence and complications. World J Urol. 2025;43(1):469. doi:10.1007/s00345-025-05839-3.
-
Dixon CM, Hricak H, McAninch JW. Magnetic resonance imaging of traumatic posterior urethral defects and pelvic crush injuries. J Urol. 1992;148(4):1162-5. doi:10.1016/s0022-5347(17)36849-0.
-
Koraitim MM, Reda IS. Role of magnetic resonance imaging in assessment of posterior urethral distraction defects. Urology. 2007;70(3):403-6. doi:10.1016/j.urology.2007.04.039.
-
Narumi Y, Hricak H, Armenakas NA, Dixon CM, McAninch JW. MR imaging of traumatic posterior urethral injury. Radiology. 1993;188(2):439-43. doi:10.1148/radiology.188.2.8327694.
-
Horiguchi A, Edo H, Shinchi M, et al. Validation of the pubourethral stump angle as a predictive parameter for elaborate anastomotic urethroplasty in pelvic fracture urethral injury. Int J Urol. 2026;33(1):e70307 (online 2025). doi:10.1111/iju.70307.
-
Koraitim MM. Predictors of erectile dysfunction post pelvic fracture urethral injuries: a multivariate analysis. Urology. 2013;81(5):1081-5. doi:10.1016/j.urology.2012.12.040.
-
Koraitim MM. Predictors of surgical approach to repair pelvic fracture urethral distraction defects. J Urol. 2009;182(4):1435-9. doi:10.1016/j.juro.2009.06.022.
-
Yepes C, Oszczudlowski M, Joshi PM, et al. Predictors of elaborated perineal or a combined abdominoperineal approach during repair for pelvic fracture urethral injury. World J Urol. 2024;42(1):40. doi:10.1007/s00345-023-04733-0.
-
Scherñuk J, Dorsemaine MG, Tirapegui F, et al. Old discussion, the same challenge: revisiting radiological predictors for urethroplasty complexity in male pelvic-fracture urethral injuries. World J Urol. 2026;44(1):132. doi:10.1007/s00345-026-06227-1.
-
Sa Y, Wang L, Lv R, et al. Transperineal anastomotic urethroplasty for the treatment of pelvic fracture urethral distraction defects: a progressive surgical strategy. World J Urol. 2021;39(12):4435-4441. doi:10.1007/s00345-021-03789-0.
-
Pratap A, Agrawal CS, Tiwari A, et al. Complex posterior urethral disruptions: management by combined abdominal transpubic perineal urethroplasty. J Urol. 2006;175(5):1751-4; discussion 1754. doi:10.1016/S0022-5347(05)00974-2.
-
Pratap A, Agrawal CS, Pandit RK, Sapkota G, Anchal N. Factors contributing to a successful outcome of combined abdominal transpubic perineal urethroplasty for complex posterior urethral disruptions. J Urol. 2006;176(6 Pt 1):2514-7; discussion 2517. doi:10.1016/j.juro.2006.08.016.
-
Xu YM, Sa YL, Fu Q, Zhang J, Jin SB. Surgical treatment of 31 complex traumatic posterior urethral strictures associated with urethrorectal fistulas. Eur Urol. 2010;57(3):514-20. doi:10.1016/j.eururo.2009.02.035.
-
Guo H, Sa Y, Fu Q, Jin C, Wang L. Experience with 32 pelvic fracture urethral defects associated with urethrorectal fistulas: transperineal urethroplasty with gracilis muscle interposition. J Urol. 2017;198(1):141-147. doi:10.1016/j.juro.2017.01.071.
-
Zhang TR, Alford A, Wang A, Zhao LC. Robotic-assisted posterior urethroplasty: outcomes from 105 men in a single-center experience. Urology. 2023;181:167-173. doi:10.1016/j.urology.2023.05.062.
-
Liu W, Shakir N, Zhao LC. Single-port robotic posterior urethroplasty using buccal mucosa grafts: technique and outcomes. Urology. 2022;159:214-221. doi:10.1016/j.urology.2021.07.049.
-
Zhang J, Xu YM, Qiao Y, et al. An evaluation of surgical approaches for posterior urethral distraction defects in boys. J Urol. 2006;176(1):292-5; discussion 295. doi:10.1016/S0022-5347(06)00518-0.
-
Wang L, Guo HL, Shu HQ, et al. Surgical treatment of pelvic fracture urethral distraction defects in boys: which approach is suitable? Asian J Androl. 2020 May-Jun;22(3):292-295. doi:10.4103/aja.aja_64_19.
-
European Association of Urology. EAU Guidelines on Urological Trauma, section 4.4 (urethral trauma; limited update March 2026).
-
Goldman SM, Sandler CM, Corriere JN Jr, McGuire EJ. Blunt urethral trauma: a unified, anatomical mechanical classification. J Urol. 1997;157(1):85–89. doi:10.1016/S0022-5347(01)65291-1.
-
Onofre LS, Leão JQ, Gomes AL, et al. Pelvic fracture urethral distraction defects in children managed by anterior sagittal trans anorectal approach: a facilitating and safe access. J Pediatr Urol. 2011;7(3):349-55. doi:10.1016/j.jpurol.2011.03.005.
-
Koraitim MM. Predicting risk of erectile dysfunction after pelvic fracture urethral injury in children. J Urol. 2014;192(2):519-23. doi:10.1016/j.juro.2014.02.094.
-
Helmy TE, Sarhan O, Hafez AT, Dawaba M, Ghoneim MA. Perineal anastomotic urethroplasty in a pediatric cohort with posterior urethral strictures: critical analysis of outcomes in a contemporary series. Urology. 2014;83(5):1145-8. doi:10.1016/j.urology.2013.11.028.
-
Helmy TE, Hafez AT. Internal urethrotomy for recurrence after perineal anastomotic urethroplasty for posttraumatic pediatric posterior urethral stricture: could it be sufficient? J Endourol. 2013;27(6):693-6. doi:10.1089/end.2012.0592.
-
Zuckerman JM, McCammon KA. Urethral Stricture Disease. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:1794–1816.
-
Zuckerman JM, McCammon KA, Tisdale BE, et al. Outcome of penile revascularization for arteriogenic erectile dysfunction after pelvic fracture urethral injuries. Urology. 2012;80(6):1369-1373. doi:10.1016/j.urology.2012.07.059.
-
Mundy AR, Andrich DE. Posterior Urethral Strictures. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:273–288. doi:10.1007/978-1-4614-7708-2_19
-
Hudak SJ, Morey AF. Reconstruction of Failed Urethroplasty. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:373–386. doi:10.1007/978-1-4614-7708-2_25
-
Black PC, Miller EA, Porter JR, Wessells H. Urethral and bladder neck injury associated with pelvic fracture in 25 female patients. J Urol. 2006;175(6):2140-2144. doi:10.1016/S0022-5347(06)00309-0.
-
Patel DN, Fok CS, Webster GD, Anger JT. Female urethral injuries associated with pelvic fracture: a systematic review of the literature. BJU Int. 2017;120(6):766-773. doi:10.1111/bju.13989.
-
Nayyar R, Bansal D, Uppal Nayyar B. Female Pelvic Fracture Associated Urethral Injury and Stricture: Principles of Management. In: Khattar N, Nayyar R, Panda A, eds. Female Bladder Outlet Obstruction and Urethral Reconstruction. Springer; 2021:201–209. doi:10.1007/978-981-15-8521-0_19
-
Clifton MM, Gurunluoglu R, Pizarro-Berdichevsky J, Baker T, Vasavada SP. Treatment of vaginal stenosis with fasciocutaneous Singapore flap. Int Urogynecol J. 2017;28(3):493-495. doi:10.1007/s00192-016-3156-8.
-
Moshokoa E. Anastomotic Urethroplasty in Pelvic Fracture Urethral Injuries (PFUIs). In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:277–282. doi:10.1007/978-981-97-5196-9_27
-
Koraitim MM. Gapometry and anterior urethrometry in the repair of posterior urethral defects. J Urol. 2008;179(5):1879-1881. doi:10.1016/j.juro.2008.01.041.
-
Joshi PM, Desai DJ, Shah D, Joshi DP, Kulkarni SB. Magnetic resonance imaging procedure for pelvic fracture urethral injuries and recto urethral fistulas: a simplified protocol. Turk J Urol. 2021;47(1):35-42. doi:10.5152/tud.2020.20472.
-
Wang Z, Song G, Xiao Y, et al. The value of magnetic resonance imaging geometric parameters in pre-assessing the surgical approaches of pelvic fracture urethral injury. Transl Androl Urol. 2020;9(6):2596-2605. doi:10.21037/tau-20-1064.
-
Kulkarni SB, Anand A, Barot P, Navarro J. Mastering Pubectomy. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:291–299. doi:10.1007/978-981-97-5196-9_29
-
Joshi PM, Ocampo MA, Desai D, Kulkarni SB. Trans-Abdominal Approach for Pelvic Fracture Urethral Injuries. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:301–316. doi:10.1007/978-981-97-5196-9_30
-
Joshi PM, Armenta H, Aubé-Peterkin M. Penile Flaps for Bulbar Urethral Necrosis. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:331–342. doi:10.1007/978-981-97-5196-9_33
-
Iselin CE, Webster GD. The significance of the open bladder neck associated with pelvic fracture urethral distraction defects. J Urol. 1999;162(2):347-351. doi:10.1016/s0022-5347(05)68557-6. PMID 10411036.
-
Sreeranga YL, Joshi PM, Bandini M, Kulkarni SB. Comprehensive analysis of paediatric pelvic fracture urethral injury: a reconstructive centre experience. BJU Int. 2022;130(1):114-125. doi:10.1111/bju.15686.
-
Schlomer BJ, Jacobs MA. Pediatric Genitourinary Trauma. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:1289–1310.
-
Gelman J, Wisenbaugh ES. Posterior urethral strictures. Adv Urol. 2015;2015:628107. doi:10.1155/2015/628107.
-
Horiguchi A, Shinchi M, Ojima K, Hirano Y, Ito K, Azuma R. "Surgical and Patient-Reported Outcomes of Delayed Anastomotic Urethroplasty for Male Pelvic Fracture Urethral Injury at a Japanese Referral Center." J Clin Med. 2022;11(5):1225. doi:10.3390/jcm11051225
-
Wen JH, Jiang SJ. "Update on Suprapubic Cystostomy Diversion vs. Primary Realignment for the Management of Blunt Posterior Urethral Injuries: A Systematic Review and Meta-Analysis." Urol J. 2025;22(4):169-175. doi:10.22037/uj.v22i.8061
-
European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Males, section 6.3.5.b. 2026.
-
Gomez RG, Scarberry K. "Anatomy and techniques in posterior urethroplasty." Transl Androl Urol. 2018;7(4):567-579. doi:10.21037/tau.2018.03.05
-
European Association of Urology. EAU Guidelines on Urethral Strictures: Perioperative Care of Urethral Surgery, section 10.2. 2026.
-
European Association of Urology. EAU Guidelines on Paediatric Urology: Paediatric Urological Trauma, section 24.4. 2026.
-
Taha MT, Ali MO, Shahat AA, Abdalla MA, Hammouda HM, Behnsawy HM. "Does primary urethral realignment improve the outcome of pediatric pelvic fracture urethral injury? A randomized controlled trial." Int J Urol. 2023;30(10):922-928. doi:10.1111/iju.15237
-
Mouraviev VB, Santucci RA. "Cadaveric anatomy of pelvic fracture urethral distraction injury: most injuries are distal to the external urinary sphincter." J Urol. 2005;173(3):869-872. doi:10.1097/01.ju.0000152252.48176.69
-
Moore EE, Cogbill TH, Jurkovich GJ, et al. "Organ injury scaling. III: Chest wall, abdominal vascular, ureter, bladder, and urethra." J Trauma. 1992;33(3):337-339. PMID 1404499
-
Mazzone A, Anderson R, Voelzke BB, et al. "Sexual function following pelvic fracture urethral injury and posterior urethroplasty." Transl Androl Urol. 2021;10(5):2043-2050. doi:10.21037/tau-20-1287