Testicular Torsion
Testicular torsion is a urological emergency in which twisting of the spermatic cord compromises testicular blood flow. Ischemia progresses rapidly. Salvage is best when detorsion occurs within the first 4 to 6 hours, but a longer symptom duration does not justify withholding urgent surgery. Surgical exploration and detorsion are definitive treatment for confirmed torsion: fix the affected and contralateral testes if the affected testis is viable, or perform orchiectomy of a nonviable affected testis with contralateral orchiopexy.[21] The clinical diagnosis takes priority over imaging: a patient with a high pretest probability goes to the operating room, not the ultrasound suite.[1][2][3]
Epidemiology
- Incidence: 3.8 per 100,000 males younger than 18 annually in a U.S. pediatric inpatient analysis.[3]
- Accounts for 10–15% of acute scrotal disease in children[3]
- Bimodal age distribution:
- Neonatal period (first 28 days of life). Often extravaginal torsion, frequently missed on initial evaluation
- 12–18 years. The peak adolescent incidence; typically intravaginal torsion on bell-clapper anatomy
- Can occur at any age, including adult life[1][4]
Risk Factors
| Risk factor | Mechanism |
|---|---|
| Bell-clapper deformity | Abnormal high investment of the tunica vaginalis → testis hangs freely like a clapper in a bell → excessive mobility enables intravaginal torsion. Autopsy studies put the rate in the scrotal testis at 4.9–16%[23] |
| Prior similar episodes | Up to 50% report previous similar episodes[7] |
| Family history of torsion | Familial cases have been reported; ask about torsion in relatives.[24] |
| Cold weather | Hyperactive cremasteric reflex |
| Rapid pubertal growth | Testicular enlargement in an already loose investment |
| Antecedent trauma | Minor scrotal trauma can precipitate torsion in predisposed anatomy |
| History of testicular surgery or undescended testis (cryptorchidism) | Predisposes to torsion; ask about it when taking the history. An undescended testis accounted for 8.9% (8/90) and 9.7% (11/107) of all pediatric torsion cases in two single/two-center retrospective series. Presentation is often atypical (groin mass, abdominal pain, restlessness in infants) and can mimic an incarcerated inguinal hernia; four Kargl patients were initially suspected of having a hernia; final salvage rates were 3/8 (37.5%) and 2/11 (18%) respectively, lower than typical intravaginal torsion in a normally descended testis[32][33] |
Pathophysiology
The spermatic cord twists around its longitudinal axis within (or outside of) the tunica vaginalis:
- Venous outflow is obstructed first (the low-pressure venous system yields to the twist before arterial inflow)
- Progressive venous congestion leading to edema and increasing intratesticular pressure
- Eventually arterial inflow is compromised, leading to global ischemia
- Damage depends on duration and degree of twisting; no fixed time threshold determines nonviability
Ischemia-reperfusion injury is a second pathophysiologic hit: detorsion restores flow to injured tissue, driving oxidative stress, neutrophil activation, cytokine release, endothelial dysfunction, and further germ cell loss. This contributes to testicular atrophy after apparently successful detorsion; long-term semen findings vary across cohorts.[5][6][20]
Clinical Presentation
Classic symptoms
- Severe, acute, unilateral scrotal pain. The defining presentation
- Onset typically <24 hours
- Nausea and vomiting. Can accompany torsion as a vagal response, but occurred in 12/64 (18.8%) confirmed cases in one surgical series.[20][36]
- Scrotal swelling, erythema
- Can be associated with lower abdominal or inguinal pain, which may mislead toward non-testicular etiologies in adolescent males
Physical examination
| Sign | Significance |
|---|---|
| High-riding testis with transverse lie | Classic; caused by cord shortening from twist |
| Absent cremasteric reflex | The EAU cites 100% sensitivity and 66% specificity for absence of the reflex in torsion. A preserved reflex should not delay exploration when the presentation is otherwise concerning[20] |
| Tender, swollen, firm testicle | Common; neonatal and atypical presentations may differ |
| Abnormal testicular lie | Transverse or elevated position |
Prior episodes
Up to one-half of patients with testicular torsion report previous similar episodes of pain.[7] For a patient with a history suggesting intermittent torsion who is pain-free at the time of evaluation, urgent exploration is not required, but bilateral scrotal exploration and orchiopexy should still be performed as soon as reasonably possible rather than deferred indefinitely.
Diagnosis
Clinical diagnosis first
Testicular torsion is primarily a clinical diagnosis. When history and exam are consistent with torsion, immediate surgical exploration is indicated and should not be delayed for imaging. When the diagnosis is equivocal, Doppler ultrasound can aid assessment if it does not delay exploration.[3][20]
TWIST Score
In children and young people with acute scrotal pain, the TWIST score (Testicular Workup for Ischemia and Suspected Torsion) is a 7-point triage tool.[4][8][34]
| Finding | Points |
|---|---|
| Testicular swelling | 2 |
| Hard testis | 2 |
| Absent cremasteric reflex | 1 |
| Nausea / vomiting | 1 |
| High-riding testis | 1 |
Risk stratification (Barbosa):
| Risk | TWIST | Pooled performance in the meta-analysis | Action |
|---|---|---|---|
| Low | 0–2 | Sensitivity 0.984; 65.2% of patients classified low risk; missed torsion remains possible[8] | Reassess clinical probability; persistent or concerning symptoms still require urgent assessment ± ultrasound |
| Intermediate | 3–4 | Sensitivity 0.922, specificity 0.682; 19.9% of patients classified intermediate risk[8] | Color Doppler US |
| High | 5–7 | Specificity 0.975; 14.9% of patients classified high risk[8] | Urgent surgical exploration |
- The meta-analysis reported AUC 0.924 for the Barbosa cut-offs in five pediatric studies (1,060 patients; 199 torsions).[8]
- TWIST supports triage.[20] A 2026 meta-analysis of patients younger than 25 reported sensitivity 94.2% (95% CI 72.8–99%) and specificity 98% (95% CI 91.5–99.5%) when comparing high-risk scores 5–7 with low-risk scores 0–2.[34]
Imaging — color Doppler ultrasound
When imaging is chosen for intermediate-risk patients:
- Color Doppler ultrasonography is a useful imaging adjunct when it will not delay exploration, as EAU recommends.[20] A 2026 diagnostic meta-analysis reported sensitivity 95.3% and specificity 98.3% across 42 studies (4,422 participants), with patient selection the main risk-of-bias and applicability concern.[35]
- Performance varies with operator, age and timing. EAU cites sensitivity 63.6–100% and specificity 97–100%; preserved or increased arterial flow can occur in torsion (24% of 208 boys with torsion in one multicenter study), and high-resolution ultrasound visualization of the twisted cord had 97.3% sensitivity and 99% specificity. EAU gives a strong recommendation that Doppler use should not delay intervention[20]
- Findings:
- Absent or decreased intratesticular blood flow on the affected side
- Whirlpool sign. Twisted spermatic cord visible on gray-scale or color Doppler (most specific finding); a systematic review and meta-analysis pooling studies across pediatric and adult patients reported sensitivity 73% and specificity 99%, with sensitivity rising to 92% once neonates (in whom the sign performs poorly) were excluded[31]
- Hypoechoic / heterogeneous parenchyma in late/progressed torsion
A normal ultrasound cannot exclude the diagnosis. Clinical suspicion drives management.[2]
Laboratory findings
If history and physical examination are highly suspicious for torsion, laboratory work is not always necessary and should not delay surgical intervention. On urinalysis, pyuria or bacteriuria suggests epididymo-orchitis, but pyuria can also occur with torsion and is not definitive; leukocytosis can occur with other infectious causes and does not rule out torsion. Obtain a CBC and coagulation profile when a bleeding risk is present, in anticipation of urgent surgery.[24]
Management
Emergent surgical exploration
Any high-risk or clinically convincing case goes to the operating room without delay.
Manual detorsion (bridge therapy)
Can be attempted in the ED while awaiting surgical transfer.[2][9] In a 2026 meta-analysis of eight retrospective comparative studies (844 patients), attempted manual detorsion was associated with fewer orchiectomies (17/406 [4.2%] versus 127/438 [29.0%] without an attempt; OR 0.13, 95% CI 0.07–0.24).[37] All studies had serious risk of bias; the maneuver must not delay urgent exploration and fixation.[37]
- Outward (medial-to-lateral) rotation ("opening a book"); do not delay surgical exploration[20]
- If pain worsens with that direction, rotate the opposite way (atypical torsion direction). In a retrospective review of 104 scrotal explorations for torsion (rotation direction recorded in 81), the testis was rotated laterally, the atypical direction, in 46% (38/81); attempting the standard medial-to-lateral maneuver on these can worsen the torsion[22]
- Ultrasound guidance has been described for manual detorsion; a 2026 systematic review found no direct comparison of guided with unguided attempts. EAU notes that Doppler may be used for guidance without delaying surgical exploration.[9][20][37]
- Pain relief does not prove complete detorsion; residual torsion can remain. Urgent exploration and fixation are still required after apparent manual success
Timing and salvage rates
| Time from symptom onset | Salvage (approximate, from surgical series) |
|---|---|
| 0–6 hours | 97.2% testicular survival (retention irrespective of later atrophy) in the six-hour-interval subset[26] |
| 6–8 hours | Testicle usually salvageable |
| 8–12 hours | Variable; salvage becomes less reliable |
| >12 hours | Risk of permanent damage / orchiectomy increases significantly |
| >24 hours | Testis retention is less frequent; EAU reports severe atrophy or absence with a twist above 360 degrees beyond 24 hours, describes semielective exploration after 24 hours in its chapter prose, and recommends urgent exploration in all cases as soon as possible in its recommendation table[26][20] |
A systematic review of 30 studies included 2,116 torsion patients overall. Among the 1,283 patients reported in six-hour time intervals, testicular survival was 97.2% at 0–6 hours, 79.3% at 7–12 hours, 61.3% at 13–18 hours, 42.5% at 19–24 hours, 24.4% at 25–48 hours, and 7.4% beyond 48 hours. Survival meant retention of the testis, irrespective of later atrophy or impaired function; these data support exploration even after prolonged symptoms.[26]
In a national database analysis of 2,876 pediatric torsion operations, 31.9% ended in orchiectomy, and the rate was highest at ages 1 to 9 years (49.9%).[10] The EAU 2026 guideline gives a critical window of about 4 to 6 hours and notes that the degree of twist also determines salvage: severe atrophy occurred after as little as 4 hours with a twist above 360 degrees, no atrophy was seen with 180 to 360 degrees and up to 12 hours of symptoms, and an absent or severely atrophic testis was found in every case above 360 degrees with symptoms beyond 24 hours. It recommends immediate treatment for torsion (strong) and urgent exploration within 24 hours of onset, with semi-elective exploration beyond that, and reports that up to half of patients develop testicular atrophy despite timely detorsion.[20]
Operative Technique — Scrotal Exploration and Orchiopexy
Incision
- Midline raphe incision. Allows bilateral access through a single incision. FIX-IT consensus also accepts a transverse incision over the affected testis and does not identify a preferred approach.[21]
- Bilateral hemiscrotal incisions. An alternative that provides separate access to each testis.
- Carry through dartos into each hemiscrotum
Delivery and detorsion
- Deliver the affected testis through the dartos pouch
- Detorse the testis by rotating opposite to the direction of twist; palpate the spermatic cord to appreciate the direction
- Wrap in warm saline-soaked gauze while fixing the contralateral testis, then reassess its appearance.[21] A handheld Doppler probe can be used intraoperatively to confirm restored blood flow, as an adjunct or prior step before deciding whether a tunica albuginea incision (bleeding test) is needed
- Deliver and inspect the contralateral testis (usually normal but confirm absence of bell-clapper and synchronous torsion). FIX-IT expert consensus calls for routine removal of healthy testicular appendages from the explored testes in children to prevent later appendage torsion.[21]
Viability assessment
After observation:
- Pink, viable testis: orchiopexy
- Dusky testis with uncertain viability: retain and fix the testis after detorsion and reassessment. FIX-IT expert consensus reserves tunica albuginea incision and flap coverage for selected cases in the hands of surgeons familiar with the technique.[21]
- Black, clearly necrotic testis: orchiectomy
- Exception — solitary testis. If the affected testicle is the patient's solitary testicle, pexy it even if viability is questionable, rather than remove it
Orchiopexy — fixation techniques
For confirmed torsion, fix the viable affected testis and the contralateral testis; if the affected testis requires orchiectomy, fix the contralateral side. If exploration finds neither torsion nor bell-clapper anatomy, FIX-IT consensus advises against routine fixation.[11][21] When bell-clapper anatomy is found without torsion, fix the symptomatic testis, explore the contralateral side, and fix it if the deformity is present there; if epididymo-orchitis is also found, avoid contralateral exploration because of infection risk.[21]
Comparative evidence for fixation techniques is limited and largely observational. FIX-IT is expert consensus: a dartos pouch or sutured fixation is acceptable in children; in adults, it recommends sutured fixation with tunica vaginalis eversion (Jaboulay repair).[12][13][14][21]
Sutureless dartos pouch (scrotal pouch) orchiopexy
- Create a subdartos pouch below the dartos layer
- Obliterate the partial tunica vaginalis sac
- Place testis in the pouch in an extravaginal position
- Tissue adherence secures the testis, with no transparenchymal sutures
- Preserves tunica albuginea and seminiferous tubule integrity
- Kozminski series: 1,104 procedures, including 949 for undescended testes and 155 for torsion; the 98.7% overall success (1,090/1,104 with normal postoperative testicular position and size).[14]
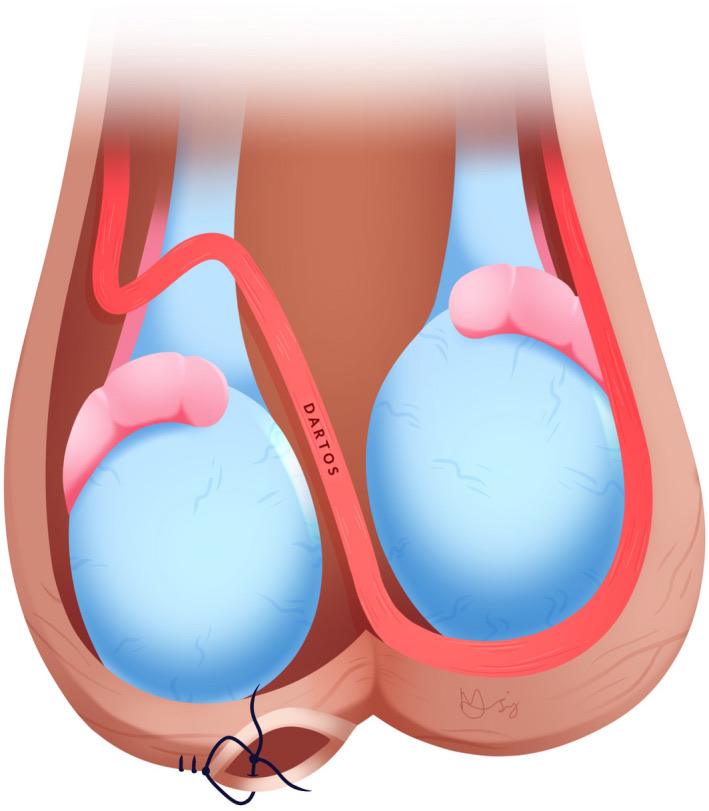
Sutureless fixation of the right testis within a dartos pouch. From Clement KD, et al. BJU Int. 2022;130(5):662-670, Fig. 4 (CC BY-NC).[21]
Sutured point-fixation (traditional)
- FIX-IT accepts three- or four-point fixation, preferring three points
- Nonabsorbable suture preferred; prolonged-absorption polydioxanone is a consensus alternative
- Avoid fixing the testes to each other across the scrotal septum.[21]
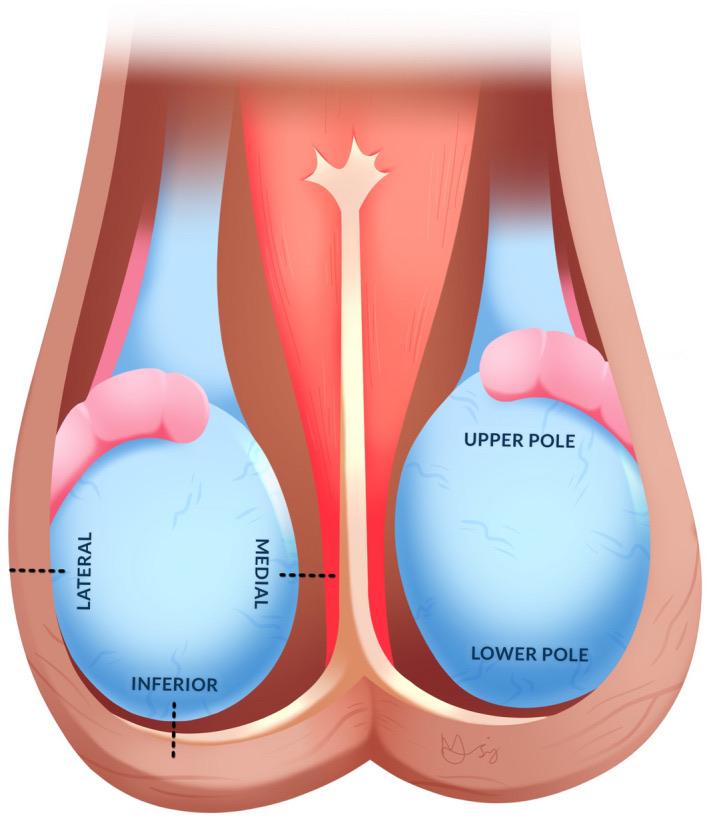
Three-point suture fixation of the right testis; dashed lines mark the lateral, medial and inferior fixation points. From Clement KD, et al. BJU Int. 2022;130(5):662-670, Fig. 5 (CC BY-NC).[21]
Jaboulay fixation (tunica plication)
- Plication of the tunica vaginalis around the testis without transparenchymal sutures
- A retrospective pediatric comparison found no significant difference in reported outcomes[12]
Eversion of tunica vaginalis
- Evert the tunica vaginalis to create extensive serosal-scrotal adherence
- Lent 1993 series (46 procedures in 35 patients): reported 87.5% salvage and no recurrences in this small series[15]
Advanced Salvage — Tunica Albuginea Decompression + Tunica Vaginalis Flap (TVF)
For selected testes that remain ischemic after detorsion, including after prolonged ischemia, tunica albuginea incision with tunica vaginalis flap (TVF) coverage has been described as a salvage maneuver; whether it improves long-term testicular viability over detorsion and fixation alone remains uncertain.[16][17][20] The technique addresses testicular compartment syndrome, which is elevated intratesticular pressure from ischemia-induced edema that impairs reperfusion even after untwisting the cord.[16][17][18]
Rationale
- In a three-boy report, pressure was measured in one 11-year-old: 34 mm Hg after detorsion, falling to 5 mm Hg after incision.[18]
- The tunica albuginea behaves like a non-compliant compartment; decompression allows the swollen parenchyma room to expand and reperfuse
Technique
- Detorse the testis; observe 10–20 min
- If still dusky with questionable viability, make a longitudinal incision in the tunica albuginea on the anterior or lateral surface
- The testis often blushes pink dramatically within minutes as the compartment decompresses
- Harvest a tunica vaginalis flap raised from the hemiscrotum
- Cover the exposed seminiferous tubules with the TVF, sewing its edges to the remaining tunica albuginea with fine absorbable suture (5-0 or 6-0)
- Proceed with orchiopexy
Outcomes
- In Figueroa’s retrospective 59-boy before/after series, orchiectomy occurred in 14/39 (35.9%) before TVF was available and 3/20 (15%) afterward; 6/11 (54.6%) testes treated with TVF met the study’s salvage definition at mean follow-up beyond six months.[16]
- Kim 2025 systematic review (eight studies, 293 patients): most studies had high risk of bias, and three comparative studies did not establish a significant salvage advantage.[17] In a 2026 single-center pediatric cohort, 36% of 39 TVF recipients met a follow-up salvage definition of at least half the contralateral testicular volume with blood flow; matched TVF and standard orchiopexy groups had 38% versus 59% salvage (p = 0.133).[38]
- In Chu's retrospective cohort (182 patients; median follow-up 2.7 months), 32 TVF recipients were matched to 32 orchiectomy cases by age and ischemia time. Among matched TVF recipients, palpable viability occurred in 19/20 (95%) after ischemia of 24 hours or less and 8/12 (67%) after longer ischemia; palpable atrophy occurred in 12/18 (67%) and 10/12 (83%), respectively.[28]
- Animal studies show mixed histopathologic results.
TVF is not routine; in selected cases with persistent dusky appearance and uncertain viability after detorsion and reassessment, surgeons familiar with the technique may use it as a salvage maneuver.[21]
Outcomes and Complications
Testicular atrophy
- In a single-center retrospective cohort of 145 children, 60/106 (56.6%) testes treated with salvage orchiopexy were atrophic at a median 4.5-month follow-up; median volume loss was 57.4%.[19]
- A systematic review and meta-analysis of 12 pediatric studies found a mean early (intraoperative) testicular loss rate of 39%, while long-term (>12 months) loss approached 50% in the studies that followed patients that far, meaning a testis called "salvaged" at the index operation still carries a substantial chance of later loss[27]
- Risk factors: age <6, delayed surgery, intraoperative evidence of poor perfusion
- In one retrospective pediatric cohort, most atrophy was detected within 3–6 months, and the authors suggested first testicular monitoring at 3 months. FIX-IT expert consensus advises outpatient clinical review after fixation and limits Doppler to symptomatic patients whose testis had uncertain viability.[19][21]
Compensatory contralateral hypertrophy
The unaffected testis undergoes compensatory enlargement in both orchiopexy and orchiectomy groups, a normal physiologic response.
Fertility
- Semen and hormonal outcomes after unilateral torsion vary across cohorts. Earlier series reported impaired semen measures.[20] In a 2023 cross-sectional sample of 7,876 young Danish men, 57 reported prior torsion surgery (five orchiectomies); semen parameters did not differ from controls, while FSH was higher and inhibin B lower, mainly after orchiectomy.[39] In a 2026 meta-analysis of 11 studies (538 patients: 197 orchiectomy, 341 orchiopexy), orchiectomy was associated with higher FSH and LH and lower sperm concentration than orchiopexy.[40]
- Mechanism: ischemia-reperfusion injury, germ cell apoptosis, antisperm antibody formation, hypothalamic-pituitary-gonadal axis disruption[5]
- Discuss possible subfertility during follow-up and offer individualized fertility assessment when appropriate. Do not delay emergency detorsion for sperm banking
- Paternity after unilateral torsion. Of 122 men screened, 72 met fertility-analysis criteria, including a stable female partner and unprotected intercourse aimed at conception for at least two years. In this selected cohort, first pregnancies culminating in live birth occurred in 41/49 (83.7%) after orchiectomy and 21/23 (91.3%) after orchiopexy.[25]
Recurrent torsion — even after fixation
Mor et al. found eight recurrent torsions after prior fixation among 179 patients explored for suspected unilateral torsion between 1991 and 2003; fixation methods among the recurrent cases varied.[13]
- Can occur 0.5 to 23 years after initial fixation (mean approximately 7 years)
- Both ipsilateral and contralateral testes are at risk of recurrent torsion
- Occurs even with nonabsorbable polypropylene sutures
- Patients should be counseled that orchiopexy reduces but does not eliminate risk; any new acute scrotal pain warrants immediate evaluation
Neonatal torsion — a special case
Neonatal torsion occurs in the first 28 days and is usually extravaginal. Distinguish established prenatal torsion from new acute postnatal torsion, which requires urgent exploration. EAU 2026 gives a weak recommendation for contralateral orchiopexy in neonatal torsion. For prenatal torsion, operative timing depends on clinical findings and requires early pediatric-urology assessment.[20] Because metachronous contralateral torsion can follow perinatal torsion, the guideline advises early but not acute exploration of both testes with fixation.[20] Salvage rates in this age group are far lower than in older children: a systematic review of 18 case series (268 operated neonates) found an overall salvage rate of 8.96%, rising to about 21.7% when surgery was performed emergently, and a separate meta-analysis of 196 neonates from 9 studies found bilateral exploration salvaged about 7% of ipsilateral testes while preventing asynchronous (contralateral) torsion in about 4%.[29][30]
Counseling
Preoperative and discharge elements:
- Contralateral fixation is recommended when torsion is confirmed; affected-side fixation depends on viability
- Salvage is time-dependent. Revisit the timeline with the patient and family
- Possibility of orchiectomy if the testis is non-viable; consent for this preoperatively
- Atrophy is common even after initial salvage; counsel about this risk and arrange outpatient clinical review. FIX-IT expert consensus reserves Doppler ultrasound for symptoms after fixation of a testis with uncertain viability.[19][21]
- Fertility implications. Discuss risk and subsequent assessment without delaying emergency surgery
- Recurrence remains possible. Any future acute scrotal pain prompts immediate re-evaluation
Post-operative management
Watch for scrotal hematoma or wound infection. Most patients are discharged the same day. Recommend scrotal support for the first few weeks and avoidance of heavy lifting or vigorous activity, and counsel on an athletic cup for future contact sports. After fixation of a testis with uncertain viability, obtain Doppler ultrasound if the patient has persistent or unexpected pain.[21] After orchiectomy, delayed placement of a testicular prosthesis can be discussed. FIX-IT expert consensus favors placement after puberty in children to permit sizing against the adult testis.[21]
Differential Diagnosis — Acute Scrotum
| Diagnosis | Key distinguishing features |
|---|---|
| Testicular torsion | Severe acute pain, absent cremasteric reflex, high-riding testis, TWIST ≥5 |
| Torsion of the appendix testis | Blue dot sign at superior testis pole (present in only about 10–23% of confirmed cases[20]); normal cremasteric reflex; localized tenderness at upper pole |
| Epididymitis / epididymo-orchitis | Often gradual pain, dysuria or fever; pain relief with elevation cannot exclude torsion |
| Incarcerated inguinal hernia | Groin mass extending into scrotum; GI symptoms |
| Hydrocele with acute rupture/bleed | Transillumination + ultrasound differentiates |
| Fournier's gangrene | Systemic toxicity, crepitus, necrotizing skin signs |
| Henoch-Schönlein purpura | Purpuric skin lesions; may have scrotal involvement mimicking torsion |
See Also
References
1. Langan RC, Puente MEE. Scrotal masses. Am Fam Physician. 2022;106(2):184–189. PMID 35977130
2. Lacy A, Smith A, Koyfman A, Long B. High risk and low prevalence diseases: testicular torsion. Am J Emerg Med. 2023;66:98–104. doi:10.1016/j.ajem.2023.01.031
3. Sharp VJ, Kieran K, Arlen AM. Testicular torsion: diagnosis, evaluation, and management. Am Fam Physician. 2013;88(12):835–40. PMID 24364548
4. Ebell MH. Clinical diagnosis of testicular torsion. Am Fam Physician. 2022;106(6):712–713. PMID 36521475
5. Elsayed Abouzed DE, Bafail DA, Refaie SM, et al. Pathophysiology and impact of testicular torsion/detorsion on male reproduction: therapeutic approach with some phytochemicals. Fitoterapia. 2025;185:106722. doi:10.1016/j.fitote.2025.106722
6. Karaguzel E, Kadihasanoglu M, Kutlu O. Mechanisms of testicular torsion and potential protective agents. Nat Rev Urol. 2014;11(7):391–9. doi:10.1038/nrurol.2014.135
7. Prater JM, Overdorf BS. Testicular torsion: a surgical emergency. Am Fam Physician. 1991;44(3):834–40. PMID 1877426
8. Qin KR, Qu LG. Diagnosing with a TWIST: systematic review and meta-analysis of a testicular torsion risk score. J Urol. 2022;208(1):62–70. doi:10.1097/JU.0000000000002496
9. Hsu CT, Chiu PW. Successful outcome of manual testicular detorsion using point-of-care ultrasound guidance: a clinical experience. Pediatr Emerg Care. 2023;39(10):813–815. doi:10.1097/PEC.0000000000003048
10. Cost NG, Bush NC, Barber TD, Huang R, Baker LA. Pediatric testicular torsion: demographics of national orchiopexy versus orchiectomy rates. J Urol. 2011;185(6 Suppl):2459–63. doi:10.1016/j.juro.2011.01.016
11. Bowlin PR, Gatti JM, Murphy JP. Pediatric testicular torsion. Surg Clin North Am. 2017;97(1):161–172. doi:10.1016/j.suc.2016.08.012
12. Koh YH, Granger J, Cundy TP, Boucaut HA, Goh DW. Sutured point-fixation versus Jaboulay fixation for salvaged testicular torsion in children. J Pediatr Surg. 2019;54(12):2631–2635. doi:10.1016/j.jpedsurg.2019.08.018
13. Mor Y, Pinthus JH, Nadu A, et al. Testicular fixation following torsion of the spermatic cord — does it guarantee prevention of recurrent torsion events? J Urol. 2006;175(1):171–3. doi:10.1016/S0022-5347(05)00060-1
14. Kozminski DJ, Kraft KH, Bloom DA. Orchiopexy without transparenchymal fixation suturing: a 29-year experience. J Urol. 2015;194(6):1743–7. doi:10.1016/j.juro.2015.06.089
15. Lent V, Stephani A. Eversion of the tunica vaginalis for prophylaxis of testicular torsion recurrences. J Urol. 1993;150(5 Pt 1):1419–21. doi:10.1016/s0022-5347(17)35795-6
16. Figueroa V, Pippi Salle JL, Braga LH, et al. Comparative analysis of detorsion alone versus detorsion and tunica albuginea decompression (fasciotomy) with tunica vaginalis flap coverage in the surgical management of prolonged testicular ischemia. J Urol. 2012;188(4 Suppl):1417–22. doi:10.1016/j.juro.2012.02.017
17. Kim J, Lorenzo A, Rivera KC, et al. Effectiveness of tunica albuginea incision and tunica vaginalis flap for testicular torsion: a systematic review. World J Urol. 2025;43(1):246. doi:10.1007/s00345-025-05638-w
18. Kutikov A, Casale P, White MA, et al. Testicular compartment syndrome: a new approach to conceptualizing and managing testicular torsion. Urology. 2008;72(4):786–9. doi:10.1016/j.urology.2008.03.031
19. Yu CJ, Zhao J, Luo J, et al. Long-term follow-up results of testicular torsion in children. Asian J Androl. 2022;24(6):653–659. doi:10.4103/aja2021127
20. European Association of Urology. Paediatric Urology Guidelines: Acute Scrotum. 2026. Guideline.
21. Clement KD, Light A, Asif A, et al. A BURST-BAUS consensus document for best practice in the conduct of scrotal exploration for suspected testicular torsion: the Finding Consensus for Orchidopexy in Torsion (FIX-IT) study. BJU Int. 2022;130(5):662–670. doi:10.1111/bju.15818.
22. Yecies T, Bandari J, Schneck F, Cannon G. Direction of rotation in testicular torsion and identification of predictors of testicular salvage. Urology. 2018;114:163–166. doi:10.1016/j.urology.2017.11.034
23. Taghavi K, Dumble C, Hutson JM, Mushtaq I, Mirjalili SA. The bell-clapper deformity of the testis: the definitive pathological anatomy. J Pediatr Surg. 2021;56(8):1405–1410. doi:10.1016/j.jpedsurg.2020.06.023
24. Laher A, Ragavan S, Mehta P, Adam A. Testicular torsion in the emergency room: a review of detection and management strategies. Open Access Emerg Med. 2020;12:237–246. doi:10.2147/OAEM.S236767
25. Zhang X, Zhang J, Cai Z, Wang X, Lu W, Li H. Effect of unilateral testicular torsion at different ages on male fertility. J Int Med Res. 2020;48(4):300060520918792. doi:10.1177/0300060520918792
26. Mellick LB, Sinex JE, Gibson RW, Mears K. A systematic review of testicle survival time after a torsion event. Pediatr Emerg Care. 2019;35(12):821-825. doi:10.1097/PEC.0000000000001287
27. MacDonald C, Kronfli R, Carachi R, O'Toole S. A systematic review and meta-analysis revealing realistic outcomes following paediatric torsion of testes. J Pediatr Urol. 2018;14(6):503-509. doi:10.1016/j.jpurol.2018.09.017
28. Chu DI, Gupta K, Kawal T, et al. Tunica vaginalis flap for salvaging testicular torsion: a matched cohort analysis. J Pediatr Urol. 2018;14(4):329.e1-329.e7. doi:10.1016/j.jpurol.2018.01.010
29. Nandi B, Murphy FL. Neonatal testicular torsion: a systematic literature review. Pediatr Surg Int. 2011;27(10):1037-1040. doi:10.1007/s00383-011-2945-x
30. Monteilh C, Calixte R, Burjonrappa S. Controversies in the management of neonatal testicular torsion: a meta-analysis. J Pediatr Surg. 2019;54(4):815-819. doi:10.1016/j.jpedsurg.2018.07.006
31. McDowall J, Adam A, Gerber L, et al. The ultrasonographic "whirlpool sign" in testicular torsion: valuable tool or waste of valuable time? A systematic review and meta-analysis. Emerg Radiol. 2018;25(3):281-292. doi:10.1007/s10140-018-1579-x
32. Zvizdic Z, Jonuzi A, Glamoclija U, Zvizdic D, Vranic S. Clinical characteristics and outcome of children with acute cryptorchid testicular torsion: a single-center, retrospective case series study. Am J Emerg Med. 2024;82:4-7. doi:10.1016/j.ajem.2024.05.010
33. Kargl S, Haid B. Torsion of an undescended testis - a surgical pediatric emergency. J Pediatr Surg. 2020;55(4):660-664. doi:10.1016/j.jpedsurg.2019.06.018
34. Lewis S, Peeraully R, Ghazy E, et al. "A systematic review and meta-analysis to inform the management of children and young people with acute testicular pain." BJU Int. 2026;137(3):417-429. doi:10.1111/bju.70080
35. Alexander CE, Warren H, Light A, et al. "Ultrasound for the diagnosis of testicular torsion: a systematic review and meta-analysis of diagnostic accuracy." Eur Urol Focus. 2026;12(1):96-108. doi:10.1016/j.euf.2025.04.026
36. Murali TV, Jaya KV, Kumar R. "Testicular torsion - symptomatology and outcomes of 101 scrotal explorations." Urol Ann. 2022;14(2):167-171. doi:10.4103/UA.UA_142_20
37. Wu ZJ, Long JX, Wang B, Yang ZL. "Manual detorsion and orchiectomy risk in testicular torsion: an updated systematic review and attempt-based meta-analysis." Pediatr Surg Int. 2026;42(1):368. doi:10.1007/s00383-026-06602-4
38. Ahmad I, Khondker A, Rickard M, et al. "The tunica vaginalis flap as a rescue procedure in testicular torsion: Quantifying salvage rates with matched cohorts." J Pediatr Urol. 2026;22(5):106004. doi:10.1016/j.jpurol.2026.106004
39. Hansen AH, Priskorn L, Hansen LS, et al. "Testicular torsion and subsequent testicular function in young men from the general population." Hum Reprod. 2023;38(2):216-224. doi:10.1093/humrep/deac271
40. Nasr AM, Zamlout A, Alghzawi HM, Youssef YA, Altell AN, Abdullah I. "Gonadal function and fertility outcomes after orchiopexy versus orchiectomy for testicular torsion: A systematic review and meta-analysis." J Pediatr Surg. 2026;61(10):163348. doi:10.1016/j.jpedsurg.2026.163348