Masculinizing Procedures
Masculinizing gender-affirming procedures span the chest, genitalia, reproductive organs, and (rarely) face / voice, each with distinct techniques, outcomes, and considerations. For overview principles see GAS Overview; for revisions see Revision & Salvage GAS.
Chest Masculinization (Top Surgery)
Top surgery is the most commonly performed masculinizing procedure. One U.S. primary-care survey reported that 95.9% of transgender men who had undergone any GAS had had chest surgery.1 It consists of subcutaneous mastectomy, reduction and repositioning of the nipple-areola complex, and chest contouring with liposuction when needed.2
Surgical Techniques
- Double incision with free nipple grafting (DIFNG). The most common technique in a 3,055-patient review (2,053/3,055; 67.2%)3 and a 73-patient series (130/146 breasts; 89.0%)4, used for larger breasts. Bilateral inframammary incisions, removal of breast parenchyma, and free nipple-areola grafting to a masculinized position.43
- Periareolar / semicircular technique (PAT). Used for smaller breasts with good skin elasticity. Preserves the nipple on a pedicle, resulting in less visible scarring. A meta-analysis found more complications with this technique than with DIFNG or PNT.3
- Pedicled nipple techniques (PNT). An intermediate option preserving nipple vascularity and sensation on a pedicle.3
A systematic review of 3,055 patients associated DIFNG with fewer complications and PAT with higher reported satisfaction. Technique selection depends on anatomy, and heterogeneous outcome reporting limits causal comparisons.3
Outcomes
- In a retrospective series of 73 patients (146 breasts; mean follow-up 7.9 months), the authors reported 2.7% major complications and 8/146 revisions (5.4%). Concomitant liposuction was associated with fewer revisions in that series.4
- In the NSQIP database (755 cases), overall complication rates were 4.7% for mastectomy and 3.7% for reduction, with no significant difference between techniques.5
- Satisfaction and mental health. Among 58 of 81 invitees responding to a postoperative survey, 86% reported improvement in gender-dysphoria-related mental health conditions; quality of life and sexual confidence improved significantly (p < 0.001).6
- A nonrandomized adolescent / young-adult cohort had 36 surgical and 34 control participants completing three-month outcomes. Chest dysphoria and body-image measures improved in the surgical group, but residual baseline differences and short follow-up limit causal inference.7
Adult eligibility. SOC8 recommends breast-cancer risk assessment before mastectomy; prior hormone therapy is not universally required for chest surgery.8 Use the individualized SOC8 assessment framework; adolescent assessment has separate criteria and cannot be inferred from the adult pathway.798
Metoidioplasty
Metoidioplasty involves construction of a microphallus from the hormonally hypertrophied clitoris, offering a simpler one-stage option for patients who do not require penetrative sexual function.1011
Procedure components may include clitoral release, urethral lengthening when voiding from the tip is desired, vaginal closure / excision, and scrotoplasty with or without testicular implants. These components are selected around the patient's goals and are not a fixed package.1112
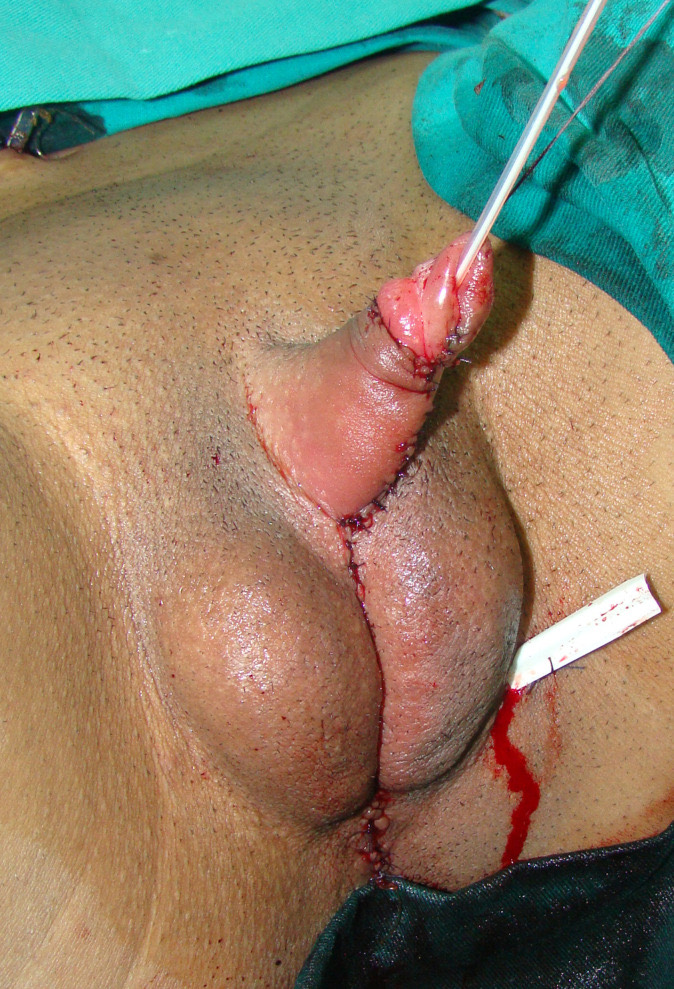
Appearance at the end of a metoidioplasty with urethral lengthening: the neophallus with a catheter at its tip, and a scrotum created from the labia majora with testicular prostheses inserted. From Bordas N, et al. Front Endocrinol (Lausanne). 2021;12:760284, Figure 8 (CC BY).13
Outcomes in a 938-patient specialist series11
- Neophallus length ranged from 4–10 cm. An earlier 813-patient series from the same center, with overlapping accrual years, reported a mean of 5.6 cm.13
- Standing micturition was reported in 99% of 938 patients; 143/938 (15.2%) had urethral complications.11
- Preservation of erogenous sensation is a principal goal. A separate community survey of 129 postoperative patients reported mean erogenous sensation of 4.8/5 after metoidioplasty versus 3.4/5 after phalloplasty; this was not a randomized comparison.14
- In a 2026 review of 23 metoidioplasty studies, reported ability for penetrative intercourse ranged from 0–24% in most series, with one outlier at 70%.15
- 12.5% of patients subsequently requested phalloplasty.
Complications
- At the 12-month checkup in the earlier 813-patient series, 727/813 (89.5%) were classified as successful urethroplasties; 72/813 (8.85%) had fistula and 14/813 (1.7%) had stricture.13
- In a Belgian retrospective cohort with median 44-month follow-up, 42/74 patients (56.8%) had a urethral complication. Additional urethral lengthening was associated with all urethral complications (OR 15.5), and smoking with fistula (OR 6.54).16
- Testicular implant rejection occurred in 2% and displacement in 3.2%.13
Satisfaction. Among 655 questionnaire respondents in the 813-patient series, 79% were totally and 20% mainly satisfied.13
Phalloplasty
Phalloplasty creates a neophallus using a tissue flap. When the flap will form a neourethra, preoperative depilation of hair-bearing donor skin is considered because intraurethral hair can predispose to infection, fistula, and stones.17 Goals may include appearance, sensation, voiding from the tip after urethral lengthening, and rigidity for penetration; the desired combination varies by patient.210
Flap Options
| Flap Type | Key Advantages | Key Disadvantages | Flap Failure Rate |
|---|---|---|---|
| Radial forearm free flap (RFFF) | Thin, pliable flap that can accommodate a tube-in-tube urethra | Visible forearm donor site; urethral complications; requires microsurgery | ~1.9% total flap loss18 |
| Anterolateral thigh (ALT) pedicled | Concealed donor site; pedicled transfer can avoid microsurgical anastomosis | Bulkier flap; may require thinning | ~0.6% total flap loss18 |
| Musculocutaneous latissimus dorsi (MLD) | Can provide substantial length / girth; donor-site function requires counseling | Technically complex; requires microsurgery | — |
| Pedicled abdominal flap | No microsurgical transfer; concealed donor site | Sensation, urethral reconstruction, and contour depend on the design | — |
| Fibula osteocutaneous | Bone can provide intrinsic rigidity | Significant donor-site morbidity | — |
A 2025 systematic review of 769 patients (614 RFFF, 155 pALT) found no statistically significant difference in flap failure or satisfaction. Evidence was rated low certainty with serious selection bias; the table's pooled flap-loss estimates are not individualized predictions or proof of equivalence.18
Urethral Reconstruction — The Most Challenging Aspect
Three main staging strategies exist: (1) single-stage phalloplasty with full-length urethroplasty, (2) metoidioplasty-first two-stage approach, and (3) phalloplasty-first "Big Ben method."22
- Overall urethral complication rates are high. A meta-analysis of 1,566 patients found a pooled fistula / stenosis rate of 48.9% across all techniques.23 A multicenter patient-reported survey of 129 patients who underwent phalloplasty, metoidioplasty, or both found urethrocutaneous fistula in 51/129 (40%) and urethral stricture in 41/129 (32%).1423
- In a single-surgeon retrospective series of 73 patients with at least six months' follow-up, the Big Ben method had a 27% urologic complication rate, with 96% achieving standing urination. Among survey respondents (67% response rate), 96% would undergo it again.24
- A 57-patient retrospective study reported fistula rates of 48% with RFFF, 20% with ALT, and 9.1% with abdominal flaps. The same study reported a 60% overall urologic-complication rate for RFFF.19
- The meta-analysis pooled standing micturition at 91.5% and tactile or erogenous sensation at 88%, with heterogeneous techniques and outcome definitions.23
Survey-reported dimensions. Mean erect length was 14.1 cm after phalloplasty versus 5.5 cm after metoidioplasty in the community survey, subject to recall and selection bias.14
Penile Prosthesis Implantation
A soft-tissue flap lacks native corporal erectile bodies. A technical review describes neophallus pocket creation, cylinder wrapping and fixation to pubic bone as the major implant steps.25 A penile prosthesis is commonly used to provide rigidity for penetration, usually after staged healing; alternatives and the need for an implant depend on flap design and patient goals.2
Types and Outcomes
- Inflatable prostheses. Overall complication rate 38%; most common complications infection (14.5%), dysfunction (12.9%), dislocation (5.7%), and leakage (5.4%). Explantation rate 19%.26
- Malleable (semirigid) prostheses. Overall complication rate 37%; most common complications dislocation (14.9%), infection (11.2%), dysfunction (9.1%), and extrusion (7.6%). Explantation rate 13%.26
- The meta-analysis found no statistically significant difference between implant types, with wide confidence intervals.26
- Five-year inflatable-prosthesis retention rates in flap phalloplasty range from 42–78%, lower than in an anatomic phallus, and complication and mechanical failure rates are higher; satisfaction remains high.25
- A 2025 retrospective cohort of 50 patients and 85 ZSI implant procedures reported three-year explantation-free survival of 39% for hydraulic and 31% for malleable devices. In this ZSI cohort, secondary implantation was associated with higher odds of complications (OR 3.5), and urethral lengthening with shorter time to late complications (HR 2.6, 95% CI 1.3–5.0).27
- Surgical experience matters: infection probability decreased significantly with increasing case number at one center.28
- In a 2026 retrospective cohort of 694 first-time three-piece inflatable implants, estimated 15-year mechanical-failure incidence was 30.6%; overall revision incidence reached 65.1%.29
Hysterectomy With or Without Bilateral Salpingo-Oophorectomy (HBSO When Combined)
Hysterectomy with or without BSO is considered medically necessary for patients with gender dysphoria who desire it, per ACOG.30 In an ACS NSQIP cohort of benign hysterectomies from 2013–2016, 521 of 159,736 procedures (0.3%) were performed in transgender men.3132
Key Considerations
- Route. A laparoscopic approach was used in 137 of 142 patients (96.5%) in one series.33 Vaginal hysterectomy is possible but may be technically difficult due to lack of uterine descent and severe vaginal atrophy from testosterone.3033
- Oophorectomy decision. It should be individualized based on fertility desires, long-term hormone plans, and patient preference. In cisgender women, oophorectomy is associated with increased cardiovascular events and all-cause mortality due to estrogen loss; whether this applies to transgender men on testosterone is unknown.34
- Combined surgery. HBSO and chest surgery can be combined in selected patients. In a 142-patient cohort, 123 underwent combined surgery; 13/123 (10.5%) had an intra- or postoperative complication. Thoracic hematoma occurred in 9/118 (7.6%) laparoscopic combined cases. Among 63 combined-surgery questionnaire respondents, mean satisfaction with performing both procedures in one session was 9.8/10.33
- Fertility preservation. Discuss oocyte / embryo preservation before gonadectomy. Hysterectomy removes the ability to carry a pregnancy, while retained ovaries may still permit later oocyte retrieval; bilateral oophorectomy removes that source of future oocytes. Fertility counseling should not assume a lack of interest in genetic parenthood.35
- Bone health. Plan adequate sex-steroid replacement and individualized bone-health follow-up after oophorectomy. Testosterone treatment does not guarantee protection from every cause of bone loss.308
Vaginectomy
In Chen et al.'s full metoidioplasty technique with urethral lengthening, vaginal mucosa is excised or ablated before colpocleisis closes the canal.36 Vaginal preservation is an option to discuss. Complete vaginectomy requires prior or concomitant hysterectomy.37 When urethral lengthening is also planned, counsel that a systematic review of high-bias case series found more urethral complications with vaginal preservation in both metoidioplasty and phalloplasty.38239 In an 813-patient complete-metoidioplasty series that included vaginectomy, 78 patients (9.6%) had a perineal cyst and/or discharge attributed to residual vaginal mucosa; persistent vaginal remnant is a recognized urologic complication requiring evaluation.1340
Stress Incontinence Surgery Before Urethral Lengthening
Mishra and Ferrando describe the same surgical options for stress urinary incontinence in transgender men who have not had genital surgery as in cisgender women: tension-free midurethral sling with mesh, Burch colposuspension, or pubovaginal sling with an autologous fascial graft (fascia lata or rectus fascia). When metoidioplasty or phalloplasty with urethral lengthening is a near-term goal, they note that suburethral scarring from mesh or graft placement can interfere with the suburethral dissection and flap creation used for urethral lengthening, depending on the technique, and recommend discussing this interaction with the patient and the gender-affirming reconstructive surgeon before continence surgery. They report that morbidity from the continence procedure itself is higher when an autologous graft is harvested and placed at the bladder neck or proximal urethra than with a midurethral sling.41
Voice and Facial Surgery
Unlike transfeminine patients, transmasculine individuals rarely require voice or facial surgery.10 Testosterone therapy deepens the voice and masculinizes facial features (facial-hair growth, fat redistribution, jawline changes). Voice deepening from testosterone is generally permanent.
Perioperative Testosterone Management
In a 2026 meta-analysis of 15 chest masculinization studies (3,036 testosterone-treated and 726 untreated patients), testosterone use was associated with hematoma (OR 1.99, 95% CI 1.19–3.34); among testosterone users, hematoma rates were 8.73% with continuation and 7.80% with cessation (p = 0.54).42 See also the Gender-Affirming Hormone Therapy hub.
- In a study of 490 patients undergoing top surgery, there was no difference in rates of hematoma (2.9% vs 2.8%), seroma, VTE, or overall complications in the groups that held versus continued testosterone (175 versus 211 patients); another 104 had never received it.43
- A systematic review in JAMA Surgery found, on limited data (one study of testosterone), that exogenous testosterone was not associated with increased VTE risk or other surgical complications. It found no evidence to support routine discontinuation.44
Long-Term Satisfaction and Regret
Reported satisfaction is often high, but outcome definitions, follow-up, and participation vary:
- Regret rate. One systematic review estimated 0.8% in transmasculine and 4.0% in transfeminine cohorts.4546
- Satisfaction. Among 946 primary-care survey participants who reported prior GAS, 776 (82.0%) reported high surgical satisfaction; reproductive surgeries were rated most satisfactory (mean 4.6/5).1 Younger transmasculine patients had higher odds of high satisfaction.1
- 40-year follow-up. 15 of 97 identified patients participated. Respondents reported favorable body congruency and mental health with no regret.47
- Genital self-image. In an online survey, postoperative respondents had a higher mean genital self-image score than preoperative respondents (20.29 versus 13.04, p < 0.00001).14
Regret ascertainment, loss to follow-up and surgeon- versus patient-reported complication rates are compared in Outcome Data Sources and Registries.
Eligibility and Timing Summary
For adults, use SOC8 assessment and consent principles, ordinarily with one competent assessment opinion if documentation is required. Hormones are not universally mandatory; metoidioplasty planning depends on achieved clitoral growth, whereas phalloplasty and hysterectomy do not inherently require a fixed year of testosterone. A 2026 international Delphi panel considered a Charlson Comorbidity Index ≥3 a relative contraindication to phalloplasty.48 Gonadectomy requires discussion of hormone goals and long-term endocrine care. The 2017 Endocrine Society guideline advised at least one year of hormone therapy before genital surgery unless hormones were undesired or medically contraindicated.49 For eligible adults, SOC8 suggests considering gonadectomy after six months of tolerated hormones when appropriate to the person's goals, and genital reconstruction after stability on the current regimen, which may include at least six months of hormones or longer for the desired result.2930498
Prosthesis placement follows sufficient flap and urethral healing with no active infection; timing is individualized with the reconstructive team.50
Lifelong Follow-Up Considerations
Patients who have undergone masculinizing genital surgery require ongoing urologic follow-up, particularly after phalloplasty, given the high rate of delayed urethral complications. Acute urinary retention after neophalloplasty requires urgent assessment; suprapubic drainage is first-line when a stricture causes retention.51 The 2026 EAU guideline strongly recommends against endoscopic incision or urethroplasty within six months of neophalloplasty.51 Systemic infection or threatened flap or device complications also require urgent assessment. Persistent dribbling, pelvic pain, and recurrent infections warrant timely reconstructive review. Donor-site complications (nerve injury, decreased strength / sensation) may benefit from occupational therapy. Patients with metoidioplasty without vaginectomy who have receptive vaginal sex should continue STI screening with vaginal swabs.39