Abdominoperineal (Transpubic) Urethroplasty
Abdominoperineal urethroplasty is a combined surgical approach for complex posterior urethral distraction defects, most commonly after pelvic fracture urethral injury (PFUI). It is the most extensive step in the reconstructive ladder for posterior urethral strictures and is reserved for cases in which a perineal-only approach cannot achieve a tension-free anastomosis. Synonymous terms include combined abdominal transpubic perineal urethroplasty, perineo-abdominal urethroplasty, and transpubic urethroplasty.[1][2][3] For the 1973 Waterhouse description, see the History of Urethral Surgery.
For the canonical PFUI clinical workflow (epidemiology, MRI, Webster steps, surveillance), see Pelvic Fracture Urethral Injury (PFUI). For the standard perineal anastomotic technique, see Excision and Primary Anastomosis. For the robotic alternative for VUAS / BNC, see Robotic Posterior Urethroplasty. For the post-prostatectomy VUAS-context abdominoperineal approach, see Combined Abdominoperineal Approach (BNC / VUAS).
Indications
The abdominoperineal approach is reserved for cases in which suitable perineal maneuvers are insufficient or in which intra-abdominal pathology requires direct abdominal access:[1][2][4][5][6][7]
- Defects that cannot be bridged without tension through an appropriate perineal approach.
- Previous failed perineal urethroplasty when repeat perineal exposure and length-gaining maneuvers cannot achieve a tension-free anastomosis.[18]
- Associated complex pathology. Rectourethral fistulas, periurethral cavities or abscesses, false passages, and bladder-neck laceration may complicate repair.[6][15] Perineal repair has been described, with approach selected by fistula location, etiology, stricture length, and prior repair.[6][15]
- Pediatric cases in which a small pelvis limits perineal exposure.
- Proximal urethral stump above the inferior pubic margin on imaging, associated with step 3 or higher (pubectomy, rerouting or abdominal access; OR 66) in a retrospective study analyzing 102/114 patients.[7]
The abdominoperineal approach was used in 6/122 (5%) PFUI repairs in the TURNS multicenter series[8] and in 5.6% of 737 repairs in a large single-center series.[9] It is reserved for the most complex defects.[8][9]
Webster Step-Based Classification
The procedure fits within the Webster classification of progressive perineal maneuvers for posterior urethroplasty:[7][9]
| Step | Maneuver |
|---|---|
| 1 | Bulbar urethral mobilization alone |
| 2 | Corporal splitting (separation of the crura) |
| 3 | Inferior pubectomy |
| 4 | Supracrural urethral rerouting |
| Combined | Abdominoperineal approach when steps 1–4 are insufficient or intra-abdominal pathology (bladder-neck repair, fistula closure) requires direct abdominal access |
Kizer reported recurrence in 3/4 rerouted repairs and success in 4/5 abdominoperineal repairs.[4] A larger later series found no significant recurrence-free survival difference among step-4, abdominal and substitution groups.[4][9]
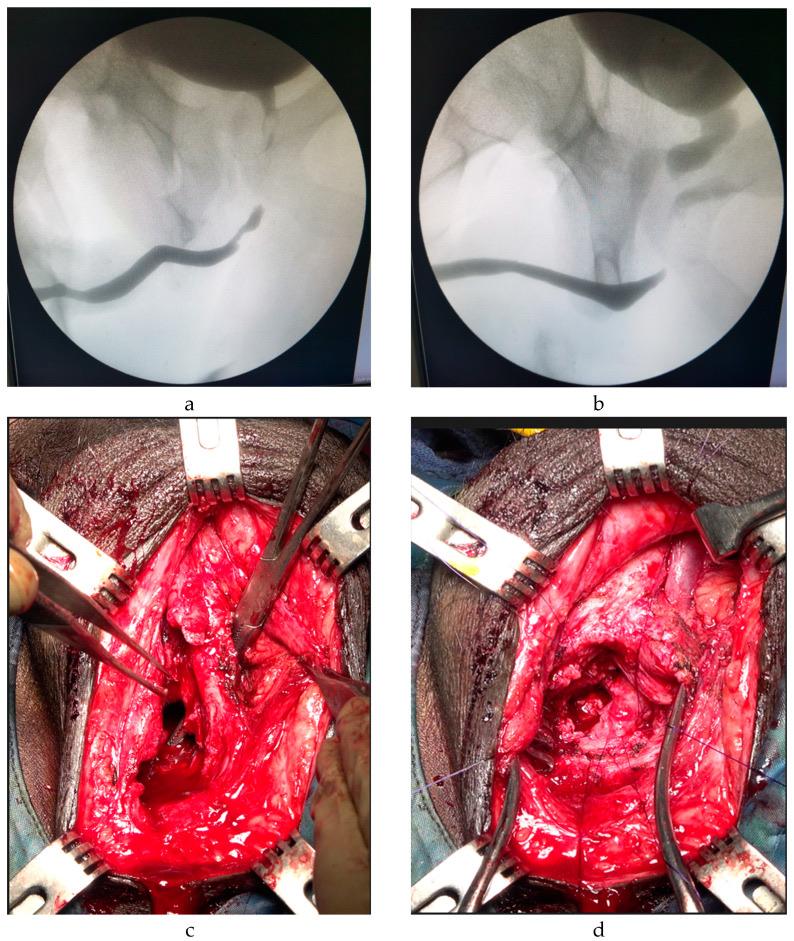
Supracrural urethral rerouting (step 4). (a, b) Retrograde urethrogram and voiding cystourethrogram showing a normal anterior urethra, a long gap and an open bladder neck. (c, d) The urethra is routed around the lateral side of the left corporal body at the penobulbar junction, straightening the natural bulbar curve and shortening the distance to the anastomosis, then passed through the bony defect created by the earlier inferior pubectomy; a small furrow is gouged in the pubis along the urethral course to avoid compression between corpus and bone. From Yepes C, et al. J Clin Med. 2023;12(6):2427, Figure 2 (CC BY).[9]
Preoperative Evaluation
- Urine culture and infection control. Obtain a preoperative urine culture, treat bacteriuria or infection before urethroplasty, and give intraoperative antimicrobial prophylaxis guided by local susceptibility patterns.[16]
- RGU and VCUG define distraction-defect length and stump position relative to the pubic symphysis.[2][7]
- Cystourethroscopy assesses bladder-neck competence and the proximal urethral stump.[2][5]
- Pelvic MRI. In the original 74-man series, a smaller sagittal T2 pubourethral stump angle (PUA) independently predicted step 3 or higher. In an independent 184-man retrospective validation, smaller PUA and prior transurethral treatment independently predicted inferior pubectomy or greater perineal elaboration (AUC 0.782 for the combined model); neither study isolates the need for abdominal access.[10][17]
- Erectile function is assessed as a predictor of surgical complexity and as a baseline for counseling.[7]
- Timing. Definitive reconstruction is planned after major injuries stabilize and the patient can be positioned safely for urethroplasty .[11]
- Associated rectourethral fistula. Assess the need and timing of fecal diversion before definitive repair; all 40 patients in Wang's perineal fistula-repair series had fecal diversion before urethroplasty.[15]
Surgical Technique
| Step | Detail |
|---|---|
| 1. Positioning | Lithotomy adapted to orthopedic injuries, pressure protection and simultaneous access to perineum and lower abdomen[1][2] |
| 2. Perineal phase | Bulbar urethra mobilized through midline perineal incision; all scar excised until healthy mucosa is identified distally |
| 3. Abdominal phase | Lower midline or Pfannenstiel incision provides retropubic access; bladder opened to identify the proximal urethral stump from above |
| 4. Partial pubectomy | A wedge is resected subperiosteally from the medial pubic bones with an osteotome to widen the subpubic tunnel. Partial superior or inferior resection is chosen according to the exposure required; total pubectomy adds morbidity without greater exposure.[3][12] |
| 5. Anastomosis | When the mobilized distal bulbar urethra is viable and reaches without tension, pass it through the subpubic tunnel (or reroute around one penile crus when needed), then spatulate and anastomose it to the prostatic apex under direct vision. In bulbar necrosis, consider substitution with a pedicled preputial tube instead of forcing an end-to-end repair.[1][3][9] |
| 6. Ancillary procedures | Bladder-neck repair when injured (20/25 in one highly selected series), rectourethral fistula closure with gracilis or rectus abdominis interposition in Xu’s 9 combined repairs (bulbospongiosus/dartos flaps in the other 22 repairs), omental wrapping of the anastomosis in Koraitim’s series, and drainage of periurethral cavities[5][6][3] |
| 7. Catheter management | Xu used suprapubic drainage and a urethral silicone stent for approximately 4 weeks. Assess for extravasation with validated urethrography before catheter removal; continue drainage and repeat assessment when a significant leak persists.[6][16] |
A long-nose speculum to open the prostatic apex in the deep operative field has been described to allow 10-12 single sutures to be placed under direct vision, with a curved needle passed from outside through the apex (including mucosa) into the bladder and back out, avoiding traction on the urethral tissue.[13]
Koraitim's "gold triad"
Koraitim's three principles for successful anastomotic urethroplasty:[1]
- Complete excision of scarred tissue.
- Fixation of healthy mucosa at both urethral ends.
- Creation of a tension-free anastomosis.
Localizing the Proximal Urethra in Complete Obliteration or Very Long Defects
For complete obliteration or very long defects, a synchronous abdominoperineal "double block" localization has been described: a guidewire passed through the suprapubic tract identifies the bladder neck, the proximal prostatic urethra is exposed and cannulated, an intraprostatic 6 Fr ureteroscope visualizes the verumontanum and membranous urethra, and a needle passed from the perineum under endoscopic view localizes the membranous urethral apex (the Hosseini technique). A dilator then identifies the proximal urethral end from below before a tension-free anastomosis, with concurrent bladder-neck-to-prostate anastomosis and, when needed, omental interposition.[14]
Outcomes
| Series | n | Stricture Length | Success | Incontinence | New-Onset Impotence |
|---|---|---|---|---|---|
| Koraitim 2005[1] | 40 | — | 39/40 (98%) | No new incontinence in the full 155-patient cohort | Two potency losses in the full cohort; not a 40-patient subgroup rate |
| Pratap 2006a[2] | 21 (11 adults, 10 prepubescent boys) | 5.2 cm mean | 20/21 (95%) radiographic patency; mean follow-up 28 months (range 9–40) | 2/21 | 3/14 without impotence after the initial injury (authors' denominator; mixed adult/pediatric cohort) |
| Pratap 2006b[5] | 25 | 6.5 cm mean | 24/25 radiographic patency; 92% overall success at mean 24 months (range 11–39) | 1/25 (4%) | No change in potency; 15/25 were initially potent |
| Koraitim 2010[3] | 64 | 4.2 cm | 98.4% | 0% | 3.1% |
| Yepes 2023[9] | 41 | — | 30/41 (73.2% calculated; article prints 74.4%); Qmax >10 mL/s and no further instrumentation | — | — |
| Kizer 2007[4] | 5 | — | 80% | — | — |
Different populations, follow-up and endpoints limit comparison. Koraitim's full 2005 cohort was followed 1–22 years, and his 2010 transpubic cohort 1–24 years.[1][3] Yepes reported median follow-up of 48 months (range 6–108) and 147/737 (19.9%) lost to follow-up for the full 737-patient cohort; abdominal-subgroup follow-up was not reported.[9] Koraitim’s 98% abdominal versus 90% perineal results are observational; the 2005 and 2010 reports may include overlapping patients.[1][3]
Complications
- Rectal injury. Rectal injury is a recognized complication of posterior urethral scar dissection.[19]
- Urinary incontinence. Baseline bladder-neck and sphincter injury contribute. Preoperative function and the injury pattern determine counseling.[1][2]
- Erectile dysfunction. Pelvic trauma commonly causes preoperative ED, and additional postoperative impairment is possible. Pratap reported new impotence in 3/14 initially potent men[2], whereas Koraitim reported two direct potency losses among 66 initially potent men in a 155-patient series[1] and two direct losses in a 64-patient transpubic series.[3] Estimates of surgical risk vary by series.[2]
- Pubectomy-related complications. Pratap observed no pubic-resection complication or bowel herniation in 21 combined repairs followed a mean 28 months[2]; Koraitim observed no abnormal gait or pelvic girdle pain in 64 partial transpubic repairs followed 1–24 years.[3] In Golimbu's mixed 287-case series, total pubectomy had higher morbidity, including bleeding, pelvic instability, incontinence and anastomotic stricture, and the authors abandoned it.[2][3][12]
- Recurrent stricture. Koraitim reported 63/64 successes; the remaining patient was lost early to follow-up and counted as a failure.[3] Yepes reported 11/41 recurrences (26.8% calculated; article prints 25.6%) in a separate complex subgroup, defined by abnormal Qmax and/or further instrumentation.[3][9]
- Bladder stones were a late complication in some series (2/64 at 6 and 14 years after surgery).[3]
Comparison With Alternative Approaches
Abdominal access and supracrural rerouting are selective options, and comparative trials have not established a fixed hierarchy.[4][9] The 2026 EAU guideline strongly recommends progressive perineal EPA for obliterative post-traumatic posterior stenosis and avoiding total pubectomy.[20] It weakly recommends reserving abdominoperineal reconstruction for complicated situations, performing open reconstruction in high-volume centers, and using a local tissue flap for excessive dead space or after rectourethral-fistula repair.[20] The AUA states that anastomotic reconstruction is performed through a perineal approach, that transabdominal or transpubic techniques are rarely required, and that clinicians should refer patients to tertiary care centers when necessary.[11]
For VUAS / BNC after radical prostatectomy or radiation, the contemporary alternative is robotic transabdominal reconstruction; see Robotic Posterior Urethroplasty and Bladder Neck Reconstruction & VUAS.
Key Takeaways
Abdominoperineal access can enable a tension-free reconstruction when a perineal route is inadequate or associated pathology requires abdominal exposure. In different selected cohorts, Yepes reported 30/41 meeting a Qmax >10 mL/s and no-further-urethral-instrumentation endpoint, whereas Koraitim reported 39/40 successful perineo-abdominal repairs; continence and potency also reflect the original injury.[1][2][9]
Videos
References
1. Koraitim MM. On the art of anastomotic posterior urethroplasty: a 27-year experience. J Urol. 2005;173(1):135-139. doi:10.1097/01.ju.0000146683.31101.ff.
2. Pratap A, Agrawal CS, Tiwari A, et al. Complex posterior urethral disruptions: management by combined abdominal transpubic perineal urethroplasty. J Urol. 2006;175(5):1751-1754. doi:10.1016/S0022-5347(05)00974-2.
3. Koraitim MM. Transpubic urethroplasty revisited: total, superior, or inferior pubectomy? Urology. 2010;75(3):691-694. doi:10.1016/j.urology.2009.09.026.
4. Kizer WS, Armenakas NA, Brandes SB, et al. Simplified reconstruction of posterior urethral disruption defects: limited role of supracrural rerouting. J Urol. 2007;177(4):1378-1381. doi:10.1016/j.juro.2006.11.036.
5. Pratap A, Agrawal CS, Pandit RK, Sapkota G, Anchal N. Factors contributing to a successful outcome of combined abdominal transpubic perineal urethroplasty for complex posterior urethral disruptions. J Urol. 2006;176(6 Pt 1):2514-2517. doi:10.1016/j.juro.2006.08.016.
6. Xu YM, Sa YL, Fu Q, Zhang J, Jin SB. Surgical treatment of 31 complex traumatic posterior urethral strictures associated with urethrorectal fistulas. Eur Urol. 2010;57(3):514-520. doi:10.1016/j.eururo.2009.02.035.
7. Yepes C, Oszczudlowski M, Joshi PM, et al. Predictors of elaborated perineal or a combined abdominoperineal approach during repair for pelvic fracture urethral injury. World J Urol. 2024;42(1):40. doi:10.1007/s00345-023-04733-0.
8. Johnsen NV, Moses RA, Elliott SP, et al. Multicenter analysis of posterior urethroplasty complexity and outcomes following pelvic fracture urethral injury. World J Urol. 2020;38(4):1073-1079. doi:10.1007/s00345-019-02824-5.
9. Yepes C, Oszczudlowski M, Bandini M, et al. Management of pelvic fracture urethral injury: is supracrural urethral rerouting (step 4) becoming anecdotical or does it remain in force? J Clin Med. 2023;12(6):2427. doi:10.3390/jcm12062427.
10. Horiguchi A, Edo H, Soga S, et al. Pubourethral stump angle measured on preoperative magnetic resonance imaging predicts urethroplasty type for pelvic fracture urethral injury repair. Urology. 2018;112:198-204. doi:10.1016/j.urology.2017.09.038.
11. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
12. Golimbu M, Al-Askari S, Morales P. Transpubic approach for lower urinary tract surgery: a 15-year experience. J Urol. 1990;143(1):72-76. doi:10.1016/s0022-5347(17)39869-5.
13. Schreiter F, Schönberger B, Olianas R. Reconstruction of the Bulbar and Membranous Urethra. In: Schreiter F, Jordan GH, eds. Urethral Reconstructive Surgery. Springer; 2006:115-117.
14. Joshi PM, Ocampo MA, Desai D, Kulkarni SB. Trans-abdominal Approach for Pelvic Fracture Urethral Injuries. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:305-309.
15. Wang L, Song W, Lv R, et al. "Precise treatment of pelvic fracture urethral injury associated with urethrorectal fistula." BJU Int. 2024;134(4):589-595. doi:10.1111/bju.16401
16. European Association of Urology. "Perioperative Care of Urethral Surgery." EAU Guidelines on Urethral Strictures. 2026. Official guideline.
17. Horiguchi A, Edo H, Shinchi M, et al. "Validation of the Pubourethral Stump Angle as a Predictive Parameter for Elaborate Anastomotic Urethroplasty in Pelvic Fracture Urethral Injury." Int J Urol. 2026;33(1):e70307. doi:10.1111/iju.70307
18. Kulkarni SB, Joshi PM, Hunter C, Surana S, Shahrour W, Alhajeri F. "Complex posterior urethral injury." Arab J Urol. 2015;13(1):43-52. doi:10.1016/j.aju.2014.11.008.
19. Plamadeala N, Waterloos M, Waterschoot M, Lumen N. "Posterior urethroplasty for pelvic fracture urethral injuries: risk factors for recurrence and complications." World J Urol. 2025;43(1):469. doi:10.1007/s00345-025-05839-3.
20. European Association of Urology. "Disease Management in Males." EAU Guidelines on Urethral Strictures. 2026. Official guideline.