Augmented Anastomotic Urethroplasty
Augmented anastomotic urethroplasty (AAU) is a hybrid technique that combines excision of the most fibrotic or obliterative segment of a stricture with an onlay graft to reconstruct longer bulbar urethral strictures that are too long for simple excision and primary anastomosis (EPA) alone. Originally described by Guralnick and Webster in 2001, AAU yielded 27/29 (93%) stricture-free at mean 28 months in their retrospective series and 62/69 (90%) without recurrence or reintervention at median 34 months in a retrospective series of recurrent strictures.[1][4] A prospective dorsal-onlay AAU cohort reported 157/163 without recurrence at median 31 months.[3] In a retrospective comparison of 221 transecting AAU repairs and 286 non-transecting dorsal onlays, AAU was associated with more cystoscopic recurrence (adjusted HR 4.8).[2]
For the buccal graft itself, see Buccal Mucosa Graft. For vessel-sparing variants, see Non-Transecting Bulbar Urethroplasty and Jordan Vessel-Sparing EPA.
Definition and Concept
The core principle of AAU is to address strictures that contain a focal segment of dense fibrosis or obliteration within a longer area of narrowing. Rather than excising the entire stricture (which may create excessive tension) or relying solely on a graft over heavily scarred tissue (a poor graft bed), AAU excises a selected dense segment, performs a partial roof- or floor-strip anastomosis, and augments the remaining defect with an onlay graft.[1][4] Mean excised lengths were 1.2 cm in the original series and 2.8 cm in the augmented Russell series.[1][6]
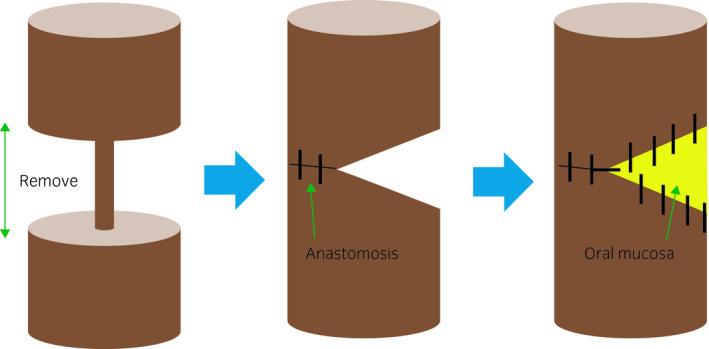
Schematic of augmented anastomotic urethroplasty: the obliterated segment is removed, the urethral ends are partially anastomosed, and the remaining defect is augmented with oral mucosa. From Tabei T, Horiguchi A, Kobayashi K. IJU Case Rep. 2019;2(5):292-295, Figure 3 (CC BY-NC 4.0).[16]
As Guralnick and Webster originally described it: a short bulbar stricture ≤1 cm is best managed by EPA, but when total stricture length is too great for excision and anastomosis, the surgeon can perform "stricture excision with roof or floor strip anastomosis augmented by an onlay."[1]
In an editorial comment on this technique, Brandes describes his own intraoperative threshold for the excision-versus-graft decision: when the residual nonobliterative bulbar plate measures more than 5 mm after urethrotomy, he generally selects graft augmentation; below 5 mm he considers double overlapping buccal grafts or focal excision plus graft, making the final choice from the operative appearance. This is a single surgeon's attributed practice, not a validated cutoff.[14]
Indications
- Bulbar urethral strictures >2 cm with a focal obliterative or densely fibrotic segment not amenable to EPA alone[1][6]
- Strictures with a 1–2 cm particularly narrow or fibrotic segment within a longer area of narrowing[1][6][4]
- Recurrent strictures after prior endoscopic treatment or urethroplasty[4]
- Strictures where a pure onlay graft would otherwise be placed over heavily scarred, poorly vascularized tissue (the anastomotic component removes that segment)[4]
- The AUA Urethral Stricture Disease Guideline (2023) recommends that surgeons offer urethroplasty as the initial treatment for long (≥2 cm) bulbar strictures ; it does not specify the urethroplasty technique[7]
Surgical Technique
Two main configurations exist, defined by which urethral wall is preserved for the anastomosis and which side receives the graft.
Configuration 1 — Roof Strip (Dorsal) Anastomosis + Ventral Onlay
- The strictured segment is exposed via a perineal approach.
- The corpus spongiosum is fully transected through the most fibrotic segment.
- The most diseased portion is excised.
- The dorsal (roof) urethral plate is preserved and anastomosed end-to-end, creating a "roof strip" anastomosis.
- This leaves an oval ventral defect that is augmented with an onlay buccal mucosa graft or pedicled skin flap.
- The graft is sutured to the edges of the ventral defect.[1][6]
Configuration 2 — Floor Strip (Ventral) Anastomosis + Dorsal Onlay
- Same exposure and excision of the most fibrotic segment.
- The ventral (floor) urethral wall is preserved and anastomosed.
- The resulting dorsal defect is augmented with a dorsal onlay graft (typically buccal mucosa placed on the tunica albuginea of the corpora cavernosa, per the Barbagli technique).
- Dorsal onlay was used in 20/29 original AAU cases and all 163 repairs in Hoy's dorsal-onlay AAU cohort.[1][3]
In the original Guralnick / Webster series, 20 of 29 patients received a floor strip anastomosis with dorsal onlay, and 9 received a roof strip anastomosis with ventral onlay. Mean excised length was 1.2 cm and mean onlay length was 4.5 cm.[1]
After grafted urethroplasty, catheter drainage commonly lasts two to three weeks. The EAU 2026 guideline strongly recommends validated urethrography to assess for extravasation before removal; persistent significant leakage warrants continued drainage and reassessment after one week.[17]
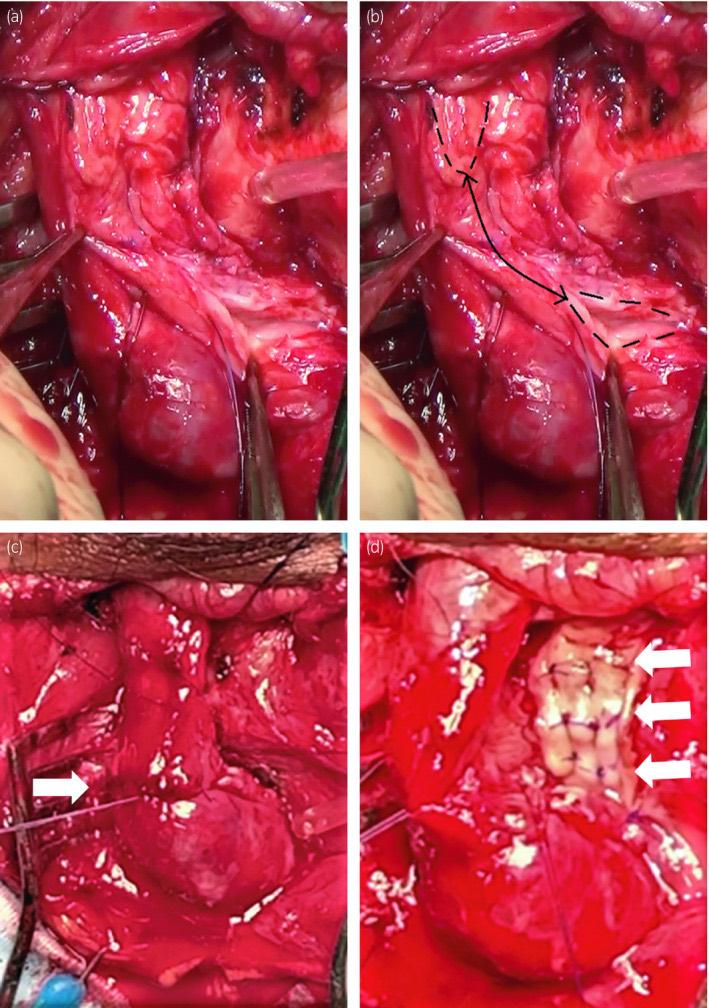
Augmented anastomotic urethroplasty for a complicated bulbar stricture: (a) complete 30-mm obliteration; (b) proximal and distal edges of the urethral mucosa traced, with the obliterated segment between them (arrow); (c) ventral anastomosis between the healthy proximal and distal urethral mucosa (arrow); (d) oral mucosa graft from the left inner cheek spread and fixed to the corpora cavernosa (arrows). From Tabei T, Horiguchi A, Kobayashi K. IJU Case Rep. 2019;2(5):292-295, Figure 2 (CC BY-NC 4.0).[16]
The Augmented Russell Technique (El-Kassaby)
A specific variant in 234 patients with long bulbar strictures (mean 4.2 cm): excision of most of the diseased segment (mean 2.8 cm) with dorsal strip anastomosis, augmented by a ventral buccal mucosal patch (mean 4.7 cm). The success rate was 93.7% (223 patients completed the follow-up protocol) at mean 36 months.[6]
A Five-Seam Closure Sequence (De Win)
For his augmented repair, De Win dorsally spatulates both urethral ends by at least 1.5 cm and bridges the gap with a dorsal buccal graft quilted to the corporal bed, then completes five seams in sequence: proximal graft-to-urethra, distal graft-to-urethra, right lateral graft-to-mucosa, ventral urethra-to-urethra, and left lateral graft-to-mucosa, closing the ventral spongiosum before the final left lateral seam.[15]
Key Outcomes by Series
| Study | n | Technique | Mean Stricture Length | Success | Follow-up |
|---|---|---|---|---|---|
| Guralnick / Webster 2001[1] | 29 | Transecting AAU (dorsal or ventral onlay) | 1.5 cm (RUG) | 27/29 stricture-free (93%) | Mean 28 mo |
| Abouassaly / Angermeier 2007[4] | 69 | Transecting AAU | — | 62/69 without recurrence or further intervention (90%) | Median 34 mo |
| El-Kassaby 2008[6] | 234 treated; 223 completed follow-up | Augmented Russell (dorsal strip + ventral BMG) | 4.2 cm | 209/223 stricture-free (93.7%) | Mean 36 mo |
| Hoy / Rourke 2013[3] | 163 | Dorsal onlay augmented anastomotic + BMG | long segment | 157/163 without recurrence | Median 31 mo |
| Welk / Kodama 2012 (ANTA)[8] | 21 | Non-transecting ANTA + BMG | — | 20/21 without further treatment (95.2%) | 2.3 yr (whole cohort median) |
| Redmond / Rourke 2020[2] | 221 (AAU) vs 286 (DO) | Transecting AAU vs non-transecting DO | 4.4 cm (overall mean) | 476/507 cystoscopic success (93.9% overall) | Mean 78.9 mo |
| Baudry 2025 (ntAAU)[5] | 42 | Non-transecting AAU + dorsal BMG | long bulbar stricture with a critical segment | 90.5% anatomical | Median 18 mo |
| Marks 2023 (MANTA)[9] | 54 | Ventral non-transecting + dorsal mucomucosal anastomosis | Not separately reported (mean graft length 4.5 cm; eligible ≥2 cm, obliterative core ≤1.5 cm) | 50/54 functional success (93%) | Median 41 mo |
The Critical Controversy — AAU vs. Pure Dorsal Onlay
A large retrospective comparison by Redmond and Rourke (2020; 507 patients, mean follow-up 78.9 months) questioned the role of transecting AAU:[2]
- Transecting AAU was independently associated with stricture recurrence on multivariate analysis (HR 4.8, p = 0.002)
- Other independent predictors of failure: increasing stricture length (HR 1.2, p = 0.002) and iatrogenic etiology (HR 3.2, p = 0.03)
- No statistically significant difference in 90-day Clavien ≥2 complications (3.6% versus 4.2%, p = 0.74) or de novo ED at six months (5.9% versus 5.6%, p = 0.89)[2]
- The institution shifted from routinely performing transecting AAU to non-transecting dorsal onlay around 2011
The institutional shift around 2011 creates potential era and selection confounding.
Complications
In Guralnick and Webster’s 29 AAU repairs, postvoid dribbling occurred in 13 patients, pseudodiverticulum in two, subjective shortening in five and new erectile dysfunction in one.[1] The accompanying chapter attributes this dribbling to impaired emptying of the reconstructed bulbar spongiosum and adjacent musculature and describes teaching patients to manually milk the urethra from the perineum toward the meatus after voiding as a practical counseling step.[14] In Hoy’s 163-patient dorsal-onlay augmented anastomotic series, the reported rates were 41.7% dribbling, 3.7% UTI, 3.1% ED, 10.4% orchalgia and 4.3% donor-site morbidity.[3]
The direct Redmond comparison reported Clavien ≥2 events in 3.6% versus 4.2% and de novo ED at six months in 5.9% versus 5.6% (AAU versus dorsal onlay), without significant differences.[2]
Evolution — Non-Transecting Augmented Techniques
Several vessel-sparing augmented modifications have been described subsequently.
1. ANTA (Augmented Non-Transected Anastomotic), Welk / Kodama 2012. ANTA was described as the first non-transecting augmented technique. It involves complete stricture excision (mucosectomy) without transecting the spongiosum, combined with dorsal onlay BMG. In the ANTA subgroup, 20/21 required no further treatment (95.2%; 93% was the combined 44-patient ANTA and onlay cohort). The median buccal graft was modestly shorter (4.5 cm versus 5.0 cm, p = 0.047).[8]
2. MsANTA (Mucosal-Sparing ANTA), Joshi / Kulkarni 2022. MsANTA has been described as a refinement in which the native urethral mucosa is neither transected nor resected but reconstructed with a direct mucosa-to-mucosa anastomosis, preserving the communicant vessels from the corpus spongiosum to the urethral mucosa.[10]
3. MANTA (Mucomucosal Anastomotic Non-Transecting Augmentation), Marks 2023. Marks and colleagues selected MANTA for strictures ≥2 cm with an obliterative segment ≤1.5 cm, a dorsal urethral bed <0.5 cm, and fibrotic changes confined to the mucosa. The scar is superficially excised dorsally while the spongiosum is left intact. Dorsal mucomucosal anastomosis is complemented by a ventral onlay graft. Among 54 MANTA patients (38 bulbar, 16 penobulbar), the series reported functional success in 50/54 (93%), defined by no symptomatic need for instrumentation, at a cohort median follow-up of 41 months; four patients were lost to follow-up before three months. Median IIEF-EF scores in sexually active respondents were 27 before and 24 after surgery (p = 0.4), and 45/45 satisfaction respondents were satisfied or very satisfied. Incomplete invasive surveillance may have missed anatomical recurrences.[9]
4. ntAAU (Non-Transecting Augmented Anastomotic), Baudry 2025. Non-transecting AAU with dorsal onlay BMG for selected long bulbar strictures with a short critical segment. In 42 patients: 90.5% anatomical success, 83.3% functional success at median 18 months. Complication rate 14.2%. Median postoperative IIEF-5 was 22 in 31 respondents.[5]
Graft Placement — Dorsal vs. Ventral Onlay
A 2025 meta-analysis of 8 studies and 655 patients comparing dorsal versus ventral onlay BMG urethroplasty found:[11]
- Success rates. No significant difference (RR 1.00, 95% CI 0.94–1.06, p = 0.97)
- Qmax. Comparable at 3 and 12 months
- Transient ED. Significantly lower with ventral technique (RR 0.24, 95% CI 0.08–0.67, p = 0.006)
- Permanent ED. No statistically significant difference (RR 0.57, 95% CI 0.03–12.20, p = 0.72)[11]
Among 134 responding GURS members (of 350 invited), dorsal graft placement was preferred (66%) over ventral (34%) for bulbar urethroplasty with BMG.[12] Choose the graft position according to anatomy, tissue quality and surgeon experience; EAU states that the best location remains to be determined.[13]
The permanent-ED estimate was imprecise (95% CI 0.03–12.20).[11]
Predictors of Failure
- Transecting AAU versus dorsal onlay in the Redmond cohort (adjusted HR 4.8, p = 0.002)[2]
- Increasing stricture length (HR 1.2, p = 0.002); strictures ≥5 cm are particularly prone to recurrence (p = 0.010)[2][3]
- Iatrogenic etiology (HR 3.2, p = 0.03)[2]
- Older age (mean 52 versus 39 yr in failures versus successes, p = 0.02)[4]
- Postoperative UTI (28% in failures versus 3.2% in successes, p = 0.05)[4]
- Lichen sclerosus requires a specific oral-mucosa reconstruction plan; one-stage repair is not uniformly contraindicated.[13]
Choosing the Reconstruction
| Stricture pattern | Reconstruction to consider |
|---|---|
| Short, traumatic bulbar stricture with nearly complete obliteration and full-thickness fibrosis | Transecting EPA |
| Short bulbar stricture without straddle injury | Non-transecting EPA or a free graft |
| Longer bulbar narrowing with a viable plate | Free-graft augmentation; dorsal, dorsolateral or ventral according to anatomy |
| Longer narrowing with a short nearly obliterative focus | Selected augmented non-transecting repair if viable tissue and a tension-free partial anastomosis are achievable |
| Extensive obliteration or adverse local tissues | Individualized complex or staged reconstruction |
These selections follow the EAU framework.[19] When a later artificial urinary sphincter is likely, a 2026 meta-analysis of observational studies associated prior transecting versus non-transecting urethroplasty with more AUS erosion (RR 2.34, 95% CI 1.30–4.21) and explantation (RR 2.38, 95% CI 1.59–3.57).[19] The augmented non-transecting recommendation is weak, reflecting limited comparative evidence. Total stricture length and length of the obliterative core are different measurements.[13]
Postoperative Surveillance
The EAU 2026 guideline strongly recommends routine follow-up for at least one year after urethroplasty. For graft repairs, its proposed standard-risk schedule lists symptom and sexual-function PROMs and uroflowmetry at 3, 12, and 24 months and five years, with cystoscopy or urethrography at 3, 12, and 24 months; later anatomical evaluation is performed as indicated.[18]
Key Takeaways
- AAU bridges the gap between EPA (short strictures) and pure onlay grafting (longer strictures) by addressing the focal obliterative component that limits graft take.
- Two retrospective AAU series reported 27/29 (93%) stricture-free at mean 28 months and 62/69 (90%) without recurrence or reintervention at median 34 months; in a retrospective comparison of 221 AAU and 286 non-transecting dorsal onlay repairs, AAU was associated with higher cystoscopic recurrence (adjusted HR 4.8).[1][4][2]
- Non-transecting augmented variants preserve spongiosal continuity and use onlay grafting, but handle mucosa differently: ANTA excises the focal scarred segment, MsANTA preserves native mucosa, and MANTA uses superficial dorsal scar excision; ntAAU is another described augmented variant.[5][8][9][10]
- Discuss dribbling, sexual and penile symptoms as well as patency; rates depend on technique, baseline symptoms and measurement method.
- For longer strictures without a focal obliterative segment, EAU recommends free graft urethroplasty for strictures not amenable to EPA, and the Redmond cohort associated transecting AAU with more recurrence than dorsal onlay.[2][13]
- Longer strictures were associated with recurrence in Redmond's AAU-versus-dorsal-onlay cohort, while Hoy's AAU cohort had lower patency at ≥5 cm.[2][3]
Videos
References
-
Guralnick ML, Webster GD. The augmented anastomotic urethroplasty: indications and outcome in 29 patients. J Urol. 2001;165(5):1496-501. doi:10.1016/s0022-5347(05)66335-5
-
Redmond EJ, Hoare DT, Rourke KF. Augmented anastomotic urethroplasty is independently associated with failure after reconstruction for long bulbar urethral strictures. J Urol. 2020;204(5):989-995. doi:10.1097/JU.0000000000001177.
-
Hoy NY, Kinnaird A, Rourke KF. Expanded use of a dorsal onlay augmented anastomotic urethroplasty with buccal mucosa for long segment bulbar urethral strictures: analysis of outcomes and complications. Urology. 2013;81(6):1357-61. doi:10.1016/j.urology.2013.02.012.
-
Abouassaly R, Angermeier KW. Augmented anastomotic urethroplasty. J Urol. 2007;177(6):2211-5; discussion 2215-6. doi:10.1016/j.juro.2007.01.140.
-
Baudry A, Schirmann A, Guillot-Tantay C, et al. Non-transecting anastomotic augmented urethroplasty with dorsal onlay buccal graft for the treatment of bulbous urethral strictures: results and complications. World J Urol. 2025;43(1):238. doi:10.1007/s00345-025-05633-1.
-
El-Kassaby AW, El-Zayat TM, Azazy S, Osman T. One-stage repair of long bulbar urethral strictures using augmented Russell dorsal strip anastomosis: outcome of 234 cases. Eur Urol. 2008;53(2):420-4. doi:10.1016/j.eururo.2007.06.002.
-
Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
-
Welk BK, Kodama RT. The augmented nontransected anastomotic urethroplasty for the treatment of bulbar urethral strictures. Urology. 2012;79(4):917-21. doi:10.1016/j.urology.2011.12.008.
-
Marks P, Dahlem R, Janisch F, et al. Mucomucosal anastomotic non-transecting augmentation (MANTA) urethroplasty: a ventral modification for obliterative strictures. BJU Int. 2023;132(4):444-451. doi:10.1111/bju.16112.
-
Joshi P, Bandini M, Kulkarni SB. Mucosal-sparing augmented non-transected anastomotic (MsANTA) urethroplasty: a step forward in ANTA urethroplasty. BJU Int. 2022;130(1):133-136. doi:10.1111/bju.15734.
-
Hassan AA, Soliman AM, Shouman HA, et al. Dorsal- vs ventral-onlay buccal mucosal graft urethroplasty for urethral strictures: a meta-analysis. BJU Int. 2025. doi:10.1111/bju.16811.
-
Berg C, Singh A, Hu P, et al. Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons. Urology. 2024;191:139-143. doi:10.1016/j.urology.2024.06.019.
-
European Association of Urology. EAU Guidelines on Urethral Strictures: disease management in males. 2026. Current guideline.
-
Guralnick ML, O'Connor RC. The Augmented Anastomotic Urethroplasty. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:214-216 (includes an editorial comment by Steven B. Brandes).
-
De Win G. Anastomotic and Augmented Anastomotic Urethroplasty. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:55-57.
-
Tabei T, Horiguchi A, Kobayashi K. Complicated bulbar urethral stricture successfully treated using augmented anastomotic urethroplasty: a case report. IJU Case Rep. 2019;2(5):292-295. doi:10.1002/iju5.12113
-
European Association of Urology. EAU Guidelines on Urethral Strictures: Perioperative Care of Urethral Surgery. 2026. Current guideline.
-
Lumen N, Campos Juanatey F, Dimitropoulos K, et al. EAU Guidelines on Urethral Strictures: Follow Up. EAU Guidelines Office, Arnhem, the Netherlands; 2026. ISBN 978-94-92761-32-5. Guideline chapter.
-
Deameh MG, Mohamed H, Abdelshafi A, Mohamed T, Ramez M. "Association of prior urethroplasty and technique with outcomes after artificial urinary sphincter implantation: a systematic review and meta-analysis." Urology. 2026;214:135-142. doi:10.1016/j.urology.2026.05.024