Blandy Perineal Urethrostomy
The Blandy perineal urethrostomy (PU) is one of the classical techniques for creating a permanent perineal stoma. It derives from the first stage of the two-stage scrotal-flap urethroplasty that Blandy, Singh and Tresidder described in 1968 for long strictures.[1] It uses an inverted U-shaped, posteriorly based perineal or scrotal skin flap that is advanced and sutured to the opened (marsupialized) bulbar urethra. In the Johanson technique reported by Lumen, scrotal skin is invaginated toward the opened urethra and sutured to its mucosa without a formal posteriorly based flap. The original laterally based 7-flap instead advanced skin to a transected urethral stump.[2][14]
For the modern midline algorithmic approach, see Midline Perineal Urethrostomy (loop or 7-flap). The inverted-U incision described here can also carry a dorsal buccal-mucosa onlay to widen the stoma (see Augmented Perineal Urethrostomy). For dorsal-plate-preservation PU, see Myers / McAninch principles. For salvage of a failed PU when local perineal tissue is depleted, see Propeller Flap PU Revision.
Historical Background and Concept
Blandy's 1968 paper, titled for the scrotal flap (see the History of Urethral Surgery), described a two-stage urethroplasty: the stricture was laid open as far as the verumontanum, and an inverted U-shaped scrotal skin flap was sutured into the floor of the opened urethra, with its apex anchored by sutures placed first in the prostatic urethra; the skin was retubularized three months later. Seventeen patients completed both stages; of four awaiting the second stage, one man with recurrent bladder stones preferred to keep the first-stage opening.[1][2] This was a deliberate departure from the earlier Johanson technique (1953), which relied on simple marsupialization of the opened urethra to perineal skin edges without a formal flap.[2][3]
Indications
The Blandy technique shares the general indications for definitive PU:
- Complex, long-segment, or panurethral strictures. 62.6% of patients in the largest dedicated Blandy series had panurethral disease.[4]
- Recurrent strictures after failed urethroplasty or endoscopic management.
- Lichen sclerosus. It accounted for 30.4% of Ponce de León's PU cases.[4] In LS-related cases, assess the planned flap for involved genital skin; the EAU guideline describes oral-mucosa-augmented Gil-Vernet-Blandy PU for LS-related strictures.[14]
- Iatrogenic (27%) and idiopathic (25.7%) strictures.[4]
- Older or comorbid patients. Poor candidates for complex multi-stage reconstruction; definitive PU is preferentially performed in older patients with worse cardiovascular comorbidity and longer strictures.[5]
- Post-urethrectomy / post-penectomy as the definitive voiding outlet after oncologic resection.[2]
- Patient preference. Nearly half of patients undergoing Stage 1 of an intended multi-stage urethroplasty refuse closure and elect to remain with PU, supporting offering PU as a primary option from the outset.[5]
The AUA 2023 amendment says surgeons may offer long-term PU as an alternative to urethroplasty and should offer it to patients at high risk of reconstruction failure .[6]
Surgical Technique
Positioning and preparation
- Obtain a preoperative urine culture and treat infection or bacteriuria before surgery. Give intraoperative antibiotic prophylaxis according to local resistance patterns .[13]
- Dorsal lithotomy with stirrups; perineum, genitalia, and inner thighs prepped and draped.
- Plan drainage using the existing suprapubic catheter where appropriate. In one retrospective cohort, suprapubic catheter use was associated with failure, potentially reflecting disease severity.[4]
Step 1 — Inverted U-shaped perineal incision
- The inverted U is the defining feature of the Blandy technique.
- The rounded apex of the U is directed anteriorly (toward the scrotum); the open base or pedicle is directed posteriorly (toward the anus); that is, the flap is posteriorly based.
- The two limbs of the U run roughly parallel on either side of the midline raphe, originating from the posterior base and joined anteriorly by the curved apex near the scrotal junction.
- Tailor flap length and base to the measured urethra-to-skin distance, preserving a broad vascular base and tension-free reach.
Step 2 — Flap elevation
- Elevate the inverted U as a full-thickness skin flap with subcutaneous tissue intact, developed off the underlying bulbocavernosus muscle (the flap contracts substantially once released).
- The flap is posteriorly based: blood supply enters from the posterior perineal vasculature at the base (the open end of the U, toward the anus).
- Reflect the flap to expose the bulbospongiosus and corpus spongiosum.
Step 3 — Urethral exposure and ventral urethrotomy
- Divide the bulbospongiosus to expose the corpus spongiosum and bulbar urethra.
- Open the urethra ventrally along the strictured segment. The urethra is laid open (marsupialized) rather than transected. This is the central technical distinction from the 7-flap.
- Extend the urethrotomy proximally until healthy, well-vascularized mucosa is encountered.
- Spatulate widely to a broad fish-mouth opening. In Lumen's Blandy technique, the edges of the opened corpus spongiosum were sutured for hemostasis.[2]
Step 4 — Flap advancement and anastomosis
- Bring the flap apex to the proximal end of the opened urethra without tension.[2]
- Parachute the apex of the flap (the rounded anterior tip) to the proximal edge of the spatulated urethra using pre-placed absorbable apical sutures (polyglactin or polyglycolic acid).
- Suture the flap edges to urethral mucosa while checking reach. In Lumen's technique, tension prompted a midline posterior scrotal incision and mobilization of two scrotal flaps to complete the stoma; both Blandy failures in that 16-patient cohort followed anastomotic tension and dehiscence.[2]
- Suture the remaining perineal and scrotal skin edges to the distal urethral opening to complete the stoma.
- The flap fills the ventral urethrotomy, with its apex at the proximal opening and its sides sutured to mucosa. Select skin that will not introduce hair into the outlet; perineal skin is not inherently hairless.[2]
- For the stoma created after total penectomy, a rosebud configuration similar to an ileostomy has been described as intended to reduce the risk of stenosis; this has not been directly compared with a standard flap-to-mucosa stoma.[16]
Step 5 — Catheter and closure
- 16–18 Fr Foley through the urethrostomy into the bladder.
- Layered wound closure.
- Catheter duration depends on the reconstruction. EAU guidance permits removal after 3–5 days following an uncomplicated perineostomy; graft augmentation, leakage or wound problems require an individualized plan.[13]
- In Lumen's cohort, regular follow-up used history, clinical examination and uroflowmetry; suspected stenosis led to urethrography and endoscopic assessment.[2]
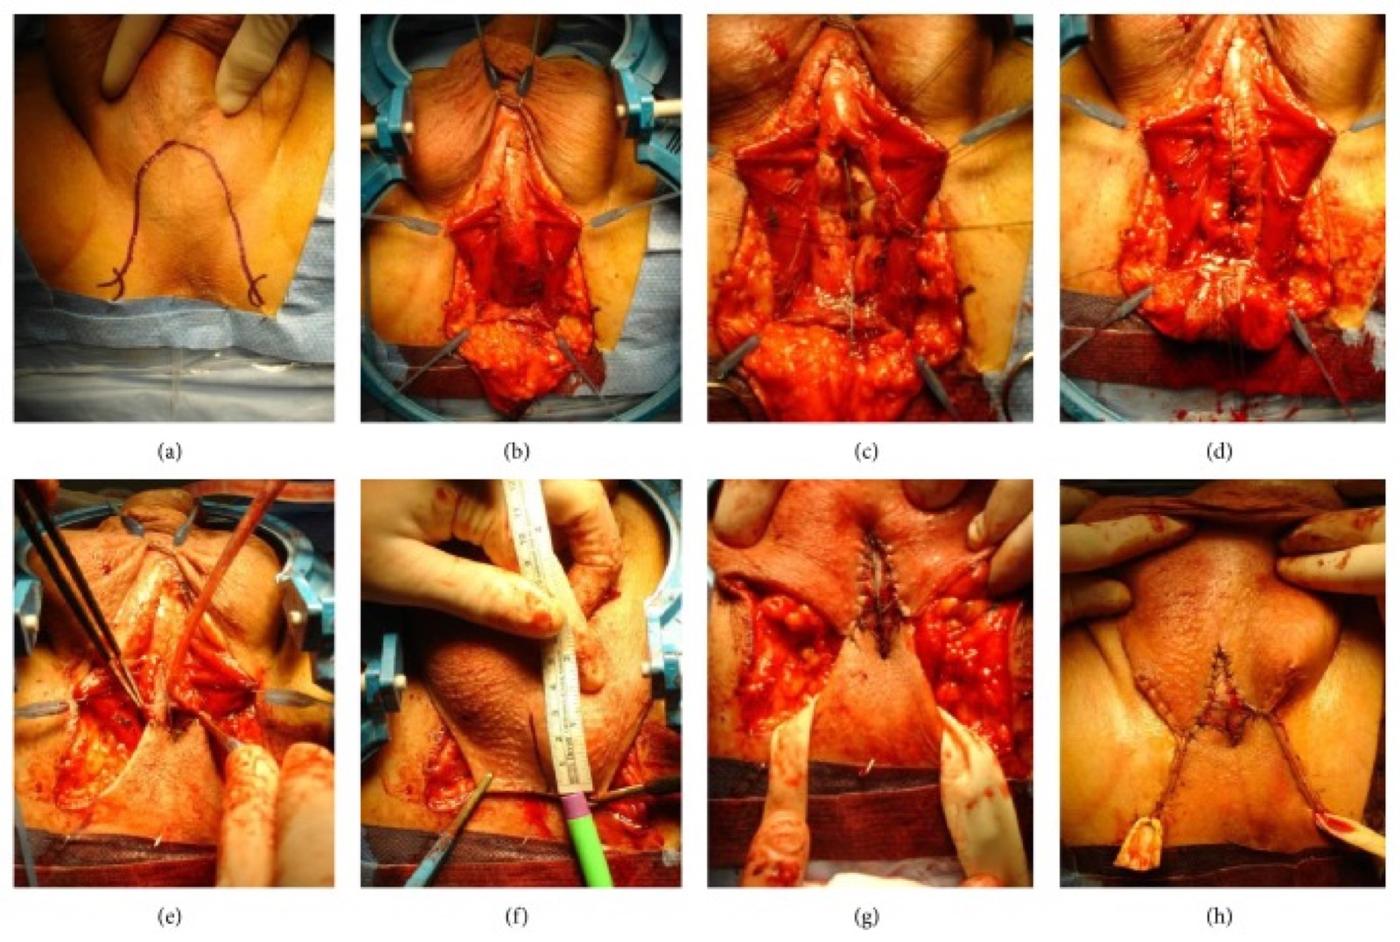
Blandy perineal urethrostomy: (a) inverted-U perineal incision; (b) exposure of the bulbar urethra; (c) opening of the bulbar urethra; (d) hemostatic sutures on the corpus spongiosum and the flap apex sutured to the proximal urethral opening; (e) inverted-U flap sutured to the urethral edges; (f) scrotal flaps created and (g) advanced to the urethral mucosa; (h) wound closure and final result. From Lumen N, et al. Biomed Res Int. 2015;2015:365715, Figure 2 (CC BY 3.0).
How Blandy Differs From Other PU Techniques
| Technique | Skin flap | Urethral handling |
|---|---|---|
| Blandy (1968) | Inverted U-shaped, posteriorly based, advanced to opened urethra | Laid open (marsupialized) |
| Johanson (1953) | None — simple marsupialization to skin edges | Laid open (marsupialized) |
| 7-Flap (Morey 2011) | Laterally based 7-shaped flap, advanced to amputated stump | Transected and amputated (the later loop modification does not transect) |
| Myers / McAninch (2011) | Inverted-U advancement flap; dorsal urethral plate and longitudinal blood supply preserved[18] | Opened ventrally; dorsal plate intact |
Anatomic Cost of the Inverted-U Incision
In the anatomy experiments reported by Lin, the inverted-U incision involved 1.6 to 2.0 times more vessels and nerves than a vertical midline incision, with similar visual operative fields.[7] In a matched retrospective bulbar or posterior urethroplasty cohort, the authors also reported:
| Endpoint | Inverted U | Midline vertical |
|---|---|---|
| Surgical site infection | 16.4–18.6% | 1.9–3.1% (p < 0.05) |
| Hospital stay | 15.8 ± 9.0 days | 12.7 ± 3.8 days (p < 0.05) |
Outcomes
| Series | n | Technique | Success | Follow-up | Notable |
|---|---|---|---|---|---|
| Ponce de León 2023[4] | 115 | Inverted-U PU: Blandy with dorsal-plate preservation and incomplete Blandy without it | 51.3% overall; 75% in last 8 yr (freedom from any postoperative instrumentation) | Median 71 mo overall | Age, BMI, SPC and era predicted failure; 88.7% voiding satisfaction |
| Lumen 2015[2] | 16 (Blandy) / 35 (Johanson) | Blandy vs Johanson | 14/16 (87.5%) / 26/35 (74.3%) without further instrumentation (p = 0.248); one-year failure-free survival 84.8% / 87.3% (log-rank p = 0.904) | Median 9 / 36 mo (mean 11.1 / 47.9 mo) | Unequal follow-up limits comparison; Qmax improved in both |
| Myers / McAninch 2011[8] | 40 followed of 45 enrolled | Inverted-U advancement flap with dorsal-plate preservation[18] | 83% primary / 93% secondary | Median 31 mo | Radiation OR 11.2 (95% CI 1.4–87.2) |
| Joshi / Morey 2024[9] | 103 | Midline (7-flap / loop) | 98/103 (95.1%) free from re-intervention | Median 61 mo at survey in 49 respondents | 42/49 satisfied; 6/103 complications |
| Fuchs / Morey 2018[10] | 77 | Midline PU | 94.8% | PU-specific follow-up not reported (full 403-patient cohort: median 50.7 mo) | Nonrandomized comparisons with different reconstruction groups |
| Klemm 2024[11] | 76 | Definitive PU | 84% retreatment-free survival; 16% recurrent stomal stenosis | Median 55 mo | Retrospective referral-center cohort |
In the Ponce de León Blandy series, success improved from 51.3% across the full cohort to 75% in the most recent 8 years.[4] In a retrospective series of 173 men who had a flap perineostomy (Barbagli, 1978 to 2007), 70% (121/173) were successful at a median follow-up of 62 months, 97% (168/173) were satisfied or very satisfied, and 127 (73.4%) declined the planned second stage.[15] The EAU guideline reports PU patency failure of 36.7-67% at a median of 62 months for lichen sclerosus, trauma and infection strictures.[14]
Prognostic Factors for Failure
Ponce de León's multivariate analysis (n = 115, 71 mo follow-up) identified four independent predictors:[4]
- Age (p = 0.01). Older patients had higher failure.
- BMI (p = 0.01). Higher BMI predicted failure (possibly reflecting urethra-to-skin distance and wound-healing burden).
- Date of surgery (p = 0.01). More recent operations had better outcomes.
- Suprapubic catheter (p = 0.003). It may be a marker of more severe disease or prior failed interventions.
Diabetes, stricture etiology, stricture type, and prior surgeries were not significant in this analysis.[4]
In the Myers / McAninch dorsal-plate-preservation series, prior radiation was associated with stomal stenosis (OR 11.2; 95% CI 1.4–87.2), with considerable uncertainty in a small cohort.[8]
Complications
The Blandy technique is a low-morbidity procedure overall:[4]
| Clavien grade | Rate |
|---|---|
| None | 73% |
| I (minor deviations from usual recovery) | 25.2% |
| II (pharmacologic) | 0.9% |
| IVa (life-threatening / ICU) | 0.9% |
Primary failure mode is stomal stenosis. In Lumen's 51-patient mixed-technique cohort, postoperative complications included wound dehiscence (6/51), urosepsis (1/51), and bleeding requiring exploration (1/51).[2]
Functional Outcomes and Quality of Life
- Voiding satisfaction. 88.7% in Ponce de León.[4]
- Qmax. Significant improvement in both Blandy and Johanson cohorts.[2]
- Postvoid dribbling. Among Lumen's questionnaire respondents, 4/13 (30.8%) after Blandy PU and 4/18 (22.2%) after Johanson PU reported it; follow-up differed between the groups.[2]
- QoL. Lumen's categorized IPSS quality-of-life responses did not differ significantly between 19 Johanson and 13 Blandy respondents (p = 0.635).[2]
- Among questionnaire respondents in Klemm's 76-patient PU cohort, the median ICIQ-UI short-form score was 0; median cohort follow-up was 55 months.[11] In Joshi's separate midline-PU survey, 31/41 respondents (76%) were unbothered by sitting to void.[9]
Choosing the PU Technique
Blandy, dorsal-plate-preserving, loop and 7-flap reconstructions remain options. In a nine-center observational cohort of selected LS-related penile strictures, five-year stricture-free estimates were 82% after single-stage oral-mucosal urethroplasty (n = 127), 76% after staged repair (n = 44) and 75% after PU (n = 60; technique unspecified).[17] The cohort excluded meatal strictures under 2 cm, bulbar involvement and panurethral strictures over 10 cm.[17] Flap reach, proximal disease, body habitus, prior operations and surgeon experience determine selection. A midline incision permits an intraoperative loop-versus-flap decision, while a 7-flap can bridge a deeper outlet in selected obese patients.[12] The 2026 EAU guideline recommends offering PU for complex anterior strictures , considering augmented Gil-Vernet-Blandy or 7-flap PU for proximal bulbar or membranous disease , and choosing the PU type by surgeon experience and patient characteristics .[14]
Videos
References
1. Blandy JP, Singh M, Tresidder GC. Urethroplasty by scrotal flap for long urethral strictures. Br J Urol. 1968;40(3):261-267. doi:10.1111/j.1464-410X.1968.tb09886.x.
2. Lumen N, Beysens M, Van Praet C, et al. Perineal urethrostomy: surgical and functional evaluation of two techniques. Biomed Res Int. 2015;2015:365715. doi:10.1155/2015/365715.
3. Al-Ali M, Al-Hajaj R. Johanson's staged urethroplasty revisited in the salvage treatment of 68 complex urethral stricture patients: presentation of total urethroplasty. Eur Urol. 2001;39(3):268-271. doi:10.1159/000052451.
4. Ponce de León J, Salas D, Calderón J, Montlleó M, Palou J. Analysis of prognostic factors of failure in perineal urethrostomy. World J Urol. 2023;41(4):1109-1115. doi:10.1007/s00345-023-04343-w.
5. Verla W, Oosterlinck W, Waterloos M, Spinoit AF, Lumen N. Perineal urethrostomy for complicated anterior urethral strictures: indications and patient's choice. An analysis at a single institution. Urology. 2020;138:160-165. doi:10.1016/j.urology.2019.11.064.
6. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
7. Lin Y, Luo D, Liao B, et al. Perineal midline vertical incision versus inverted-U incision in urethroplasty: which is better? World J Urol. 2018;36(8):1267-1274. doi:10.1007/s00345-018-2267-x.
8. Myers JB, Porten SP, McAninch JW. The outcomes of perineal urethrostomy with preservation of the dorsal urethral plate and urethral blood supply. Urology. 2011;77(5):1223-1227. doi:10.1016/j.urology.2010.10.041.
9. Joshi EG, VanDyke ME, Langford BT, Franzen BP, Morey AF. Algorithmic midline approach to perineal urethrostomy is associated with long-term success and high patient satisfaction. Urology. 2024;190:133-139. doi:10.1016/j.urology.2024.03.016.
10. Fuchs JS, Shakir N, McKibben MJ, et al. Changing trends in reconstruction of complex anterior urethral strictures: from skin flap to perineal urethrostomy. Urology. 2018;122:169-173. doi:10.1016/j.urology.2018.08.009.
11. Klemm J, Dahlem R, Schulz RJ, et al. Perineal urethrostomy for complex urethral strictures: long-term patient-reported outcomes from a reconstructive referral center and a scoping literature review. J Urol. 2024;212(5):738-748. doi:10.1097/JU.0000000000004169.
12. McKibben MJ, Rozanski AT, Fuchs JS, Sundaram V, Morey AF. Versatile algorithmic midline approach to perineal urethrostomy for complex urethral strictures. World J Urol. 2019;37(7):1403-1408. doi:10.1007/s00345-018-2522-1.
13. EAU Guidelines on Urethral Strictures: perioperative care. https://uroweb.org/guidelines/urethral-strictures/chapter/perioperative-care-of-urethral-surgery. Accessed September 12, 2026.
14. EAU Guidelines on Urethral Strictures: perineal urethrostomy. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males. Accessed September 12, 2026.
15. Barbagli G, De Angelis M, Romano G, Lazzeri M. Clinical outcome and quality of life assessment in patients treated with perineal urethrostomy for anterior urethral stricture disease. J Urol. 2009;182(2):548-557. doi:10.1016/j.juro.2009.04.012.
16. Horenblas S, Malone PR, Muneer A. Surgical treatment of penile cancer. In: Muneer A, Arya M, Jordan GH, eds. Atlas of Male Genitourethral Surgery: The Illustrated Guide. Wiley-Blackwell; 2014:134-150. doi:10.1002/9781118651292.ch11
17. Hengel R, Vanni A, Erickson B, et al. "Multi-Institutional Analysis of Surgery for Lichen Sclerosus-Induced Penile Urethral Stricture: Establishing Single-Stage Urethroplasty as a Primary Treatment Option." J Urol. 2025;213(5):628-637. doi:10.1097/JU.0000000000004434
18. Myers JB, McAninch JW. "Perineal urethrostomy." BJU Int. 2011;107(5):856-865. doi:10.1111/j.1464-410X.2011.10139.x