Distal Urethrectomy with Advancement Meatoplasty (Female)
Distal urethrectomy with advancement meatoplasty is a single-stage repair for a very short meatal female urethral stricture. The diseased segment is excised, and healthy proximal urethral mucosa is advanced to the surrounding vaginal epithelium to form a neomeatus. A mobilized anterior vaginal-wall flap is a separate reconstruction described after oncologic distal urethral resection. No graft or oral-mucosa harvest is required.[1][2][23][6]
For the broader female-stricture treatment ladder and endoscopic alternatives, see Female DVIU and Urethral Dilation. For longer or more proximal strictures requiring augmentation, see Female Dorsal Onlay BMG, Ventral Onlay BMG, and Blandy U-Flap.
Indications
- A short distal female urethral stricture selected for excision and advancement after its proximal extent is defined.[1] For isolated short meatal stenosis, the EAU 2026 guideline gives a weak recommendation for meatoplasty as an initial treatment; prior endoscopic failure is not required.[21]
- For a stricture in the distal third,[2][3] consider excision and mucosal advancement only when disease is confined to a very short meatal segment with healthy proximal mucosa and the planned resection avoids continence structures.[9][23]
- Meatal stenosis refractory to conservative management.
- LS-associated meatal stricture (some authors prefer BMG in this setting given LS recurrence risk in local tissue).[4][5]
- Oncologic context. Distal urethral resection during vulvectomy for vulvar cancer involving the distal urethra; the same advancement principle is used to construct the neomeatus.[6][7]
Contraindications / Relative Limitations
- Strictures extending into the mid or proximal urethra require augmentation urethroplasty (vaginal flap or BMG) rather than simple excision and advancement.[1][3]
- LS or atrophy compromising the anterior vaginal wall flap quality.[1][4]
- Resection that would injure the rhabdosphincter or its support; sphincter fibers extend through the middle and distal urethra.[8][9]
Surgical Anatomy — the Sphincter Limit
The female urethral sphincter (rhabdosphincter) is concentrated in the middle and distal thirds of the urethra; the compressor urethrae lies in the distal third. Resection must preserve the individual continence mechanism and adequate functional urethral length.[9][10] The often-cited 1–1.5 cm range derives partly from selected vulvar-cancer series.[9][10]
- Reid 1990. Of 21 women evaluated prospectively around vulvectomy, all 4 in whom a portion of the urethra was excised developed stress or total incontinence, with significant decreases in functional urethral length and distal pressure-transmission ratios.[8]
- Hampl 2011. After partial distal-urethral resection of up to 1.5 cm in 19 women with anterior vulvar cancer, 5 (26%) reported urinary disturbances and underwent urodynamics. The authors classified 18 of 19 (95%) as continent, although only the symptomatic women were tested and one measurement was unreliable.[10]
- de Mooij 2007. In a retrospective comparison, 4 of 18 women (22%) who underwent radical vulvectomy plus partial urethrectomy (1–1.5 cm) reported incontinence, versus 2 of 17 (12%) treated by vulvectomy alone (p = 0.86), a nonsignificant difference in this small cohort.[16]
- Dimarco 2004.[17] In a 26-patient cohort undergoing partial urethrectomy for primary female urethral carcinoma — a different population from the vulvar-cancer resections above — stress urinary incontinence was reported in 11 (42%), urinary retention in 2 (8%), and urge incontinence in 1 (4%); the follow-up interval for these outcomes was not stated.[17]
Prior surgery, tissue loss and baseline continence alter risk; these small oncologic series provide no stricture-specific safe resection limit.
Technique
Dorsal lithotomy under regional or general anesthesia.[2][5][6][7]
- Define extent and baseline function. Before selecting excision, assess pelvic findings, continence, flow and post-void residual; use VCUG or videourodynamics to delineate the proximal limit in women with refractory LUTS . Cystourethroscopy identifies the distal edge, but a tight meatus may require preliminary dilation before the proximal urethra can be examined.[21]
- Circumferential meatal incision just proximal to the diseased segment; circumferential mobilization of the distal urethra off the periurethral tissue and anterior vaginal wall. Some authors place stay sutures in healthy urethral mucosa proximal to the stricture before excision to limit retraction: Meilika and Sandhu describe circumferential stay sutures placed in identified healthy proximal tissue[18]; Volkin and Nitti describe interrupted absorbable sutures at least 2 mm proximal to the stricture at 6 and 12 o'clock[19]; and Lec and Nitti describe two- or four-quadrant stay sutures (four in their figure), with a nasal speculum and, occasionally, a ventral urethrotomy used to define the proximal stricture limit.[20]
- Distal urethrectomy. Sharply excise the fibrotic distal segment while preserving healthy proximal urethral mucosa for advancement and subsequent neomeatal anastomosis.[18] Minimize resection and preserve the sphincter and support complex; do not treat 1.5 cm as a guarantee of continence. Send the specimen for pathology to rule out malignancy and confirm spongiofibrosis.[5]
- Spatulation of the proximal healthy urethral stump, usually ventrally, to widen the new meatus and limit circular contracture. Avoid carrying the ventral incision too far toward the vagina, which can cause vaginal voiding.[24]
- Urethral mucosal advancement. Advance healthy proximal urethral mucosa to the vaginal epithelium bordering the excised meatus without tension. Separately mobilized anterior vaginal-wall flaps have been described for neomeatus reconstruction after more extensive oncologic resection.[18][23][6][14]
- Neomeatus creation. Use interrupted absorbable mucosa-to-mucosa sutures (4-0 or 5-0, for example polyglactin) for the described advancement repair.[24] In a separate post-vulvectomy repair, Lange et al. inset a triangular anterior vaginal flap into a posterior longitudinal urethrotomy with interrupted 5-0 polyglactin sutures.[6] The illustrated Ceccaroni oncologic tunnel-flap variant instead uses an X-shaped vaginal opening and six radial everting 3-0 polyglactin sutures; its proposed mechanical benefit comes from one case.[14]
- Catheter. Select catheter caliber and drainage duration according to the repair and wound condition. Ceccaroni’s oncologic tunnel-flap case used an 18 Fr Foley initially and added suprapubic diversion after wound dehiscence.[14]
Technical pearls. For short-stricture advancement, join healthy proximal urethral mucosa to adjacent vaginal epithelium with interrupted absorbable sutures and avoid tension.[23][18] Lange et al. describe a noncircular V-Y inset for the separate post-vulvectomy vaginal-flap repair.[6] Send the urethrectomy specimen for pathology.[5]
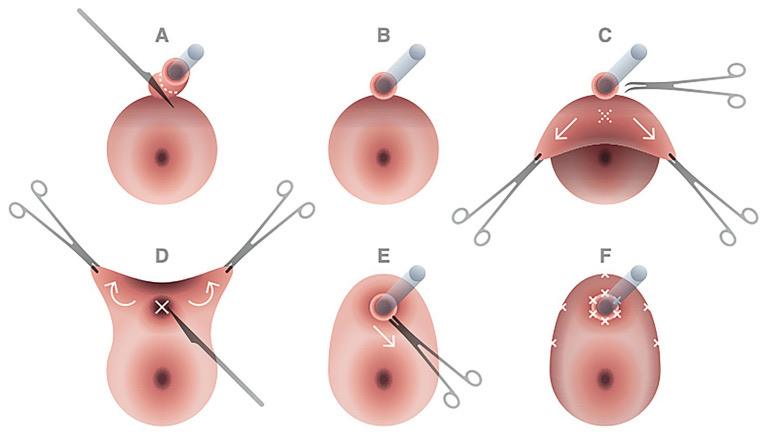
Neomeatus reconstruction after distal urethrectomy for advanced vulvar cancer ("tunnel flap" variant). (A, B) Cold-knife incision of the urethral wall about 2 cm from the meatus. (C) The ventral vaginal wall edges are held in Allis clamps under caudal traction and the urethrovaginal septum is dissected cranially for about 4 cm, creating an advancement vaginal flap that covers the resected urethral stump without excess tension. (D, E) An X-shaped incision about 1 cm cranially on the vaginal wall is aligned with the urethral neomeatus. (F) The urethral-vaginostomy is completed with six everting radial interrupted 3-0 polyglactin sutures, and the flap is anchored to the vulvar flap skin, forming a tunnel of vaginal mucosa along the re-anastomosed urethra. From Ceccaroni M, et al. Front Med (Lausanne). 2025;12:1695521, Figure 3 (CC BY).[14]
Outcomes
Outcome data isolating distal urethrectomy with advancement meatoplasty in FUS are limited; most series pool it with other urethroplasty techniques or report it in the post-vulvectomy oncologic setting.
| Setting | Series | n | Result |
|---|---|---|---|
| FUS — reviews of urethroplasty techniques and dilation | Osman 2013 SR / Sarin 2021 meta[11][12] | 221 / 554 across all interventions, including dilation | Urethroplasty success 80–94% vs dilation 47% (Osman; no further intervention); urethroplasty 86–93% vs dilation 49% (Sarin; symptom improvement and no further instrumentation); mean follow-up varied by technique |
| FUS — vaginal flap (9) and BMG (1) urethroplasty, retrospective | Blaivas 2012[13] | 17 women with stricture; 10 underwent urethroplasty | Urethroplasty: 100% at 1 yr and 78% at 5 yr; initial dilation in 17 women: 6% success |
| FUS — vaginal flap vs DOBMGU head-to-head | Higuchi 2026[3] | 7 vs 8 | Cystoscopic absence of re-stricture without secondary intervention: VFU 57.1% (4 / 7) vs DOBMGU 87.5% (7 / 8); median follow-up 12 mo for the whole 15-patient cohort; spraying 2 / 7 in VFU only. Small sample. |
| Post-vulvectomy neomeatus reconstruction | Lange 2022[6] | 42 vaginal-flap advancements / 41 women | 1 neomeatal stenosis, 1 neomeatal dehiscence with occlusion, and 1 partial flap necrosis; 6 meatus-related self-reported urinary incontinence events (1/17 limited, 5/25 extended, with one extended-group value missing) and 2/25 spraying events after extended repair. Mean follow-up among survivors was 56 months. The authors judged the stenosis and dehiscence preventable. |
| Post-vulvectomy neomeatus reconstruction | de Lorenzi 2015[7] | 47; 32 (68.1%) evaluated long term | Among those evaluated long term: no urethral stenosis; 6/32 (18.7%) had urinary incontinence |
Complications
Stress urinary incontinence (SUI) is an important functional concern if resection approaches continence structures, but its incidence after limited distal advancement for female stricture has not been established.[8][9][23] A 2026 review discusses incontinence as a functional concern after female urethroplasty.[5] A 2022 review of FUS interventions reported mild-to-moderate de novo incontinence after surgery in 9.43%, without specifying the stress subtype; most recovered with pelvic floor exercises.[22] Across 221 women in dilation and mixed urethroplasty series, the Osman review found no reported de novo SUI.[11]
Other reported complications:
- Neomeatal stenosis or re-stricture. Reported after both vulvectomy reconstruction and stricture surgery; noncircular insets are used to avoid it.[6]
- Urinary spraying. Reported with vaginal flap reconstruction of distal strictures (2 / 7 in Higuchi 2026; absent in DOBMGU).[3]
- Wound dehiscence. In de Lorenzi's 47-patient oncologic series, 11/47 (23.4%) had wound breakdown and 2/47 (4.3%) had dehiscence at the neomeatal reconstruction site.[7][14]
- Partial vaginal flap necrosis. 2.1% in the de Lorenzi series.[7]
- Narrowed introitus. Reported in 25% of women evaluated long-term after oncologic vulvectomy.[7]
- UTI. Perioperative, related to catheterization.
Comparison with Alternative Distal-Stricture Techniques
| Technique | Best for | Reported success | Key advantage | Key limitation |
|---|---|---|---|---|
| Distal urethrectomy + advancement meatoplasty | Very short meatal stricture | — | Local tissue; no graft donor site; excises diseased segment | SUI risk depends on resection, anatomy and baseline function; spraying risk for this exact repair is unquantified |
| Vaginal flap urethroplasty (Blandy / lateral-based) | Distal-to-mid strictures | Historical Osman review: 50/55 (91%) vaginal-flap repairs were reported successful at mean 32 months, but 12 of these women were instructed to perform daily intermittent self-catheterization. EAU 2026 synthesis: 81.4% patency among 161 women in 9 ventral vaginal-flap studies at mean/median follow-up of 10–80.7 months, with 15/161 (9.3%) new urinary incontinence.[2][4][5][11][21] | Well-vascularized, readily available | Atrophy, scarring, or LS may limit suitable vaginal tissue |
| Dorsal onlay BMG urethroplasty | Location and length guide selection | 62.5–100% in small dorsal BMG series[2][4][5] | Versatile; tissue independent of vaginal health | Oral donor-site morbidity; technically more complex |
| Urethral dilation | Initial option for confirmed nonmeatal FUS; see the endoscopic pathway | Limited durability | Office-based in selected patients | DVIU evidence in true FUS is insufficient; isolated meatal disease may be treated with meatoplasty |
Postoperative Management
- Volkin and Nitti, and separately Lec and Nitti, describe urethral drainage for as little as 1–3 days after limited distal reconstruction and note that postoperative swelling can itself cause retention.[19][20] In Ceccaroni’s extensive oncologic reconstruction, wound dehiscence led to suprapubic diversion on postoperative day 8 and removal after healing on day 63.[14] Duration should match repair extent and healing.
- Topical estrogen at the neomeatus in postmenopausal women may support mucosal health.[4]
- Follow-up uroflowmetry and cystoscopy at 3–6 months to confirm patency.
- Long-term surveillance is needed; late recurrences > 5 years have been reported.[13]
Summary
Distal urethrectomy with advancement meatoplasty is an option for short distal or meatal female urethral stricture. Well-vascularized anterior vaginal wall is used to construct the neomeatus.[8][9] The operation aims to preserve functional urethral length and sphincter support while creating a wide neomeatus.[8][9] The success rate of distal excisional advancement for FUS has not been established.[11][6][23] Oral mucosal augmentation is an alternative when the stricture extends beyond the distal urethra or local tissue is unhealthy.[1][3][11][15]
References
1. Bouchard B, Campeau L. Surgery for female urethral stricture. Neurourol Urodyn. 2025;44(1):51-62. doi:10.1002/nau.25358.
2. Faiena I, Koprowski C, Tunuguntla H. Female urethral reconstruction. J Urol. 2016;195(3):557-567. doi:10.1016/j.juro.2015.07.124.
3. Higuchi M, Horiguchi A, Ashiya M, et al. Vaginal flap urethroplasty and dorsal onlay buccal mucosal graft urethroplasty for female urethral stricture: a single-center experience. Int J Urol. 2026;33(5):e70477. doi:10.1111/iju.70477.
4. West C, Lawrence A. Female urethroplasty: contemporary thinking. World J Urol. 2019;37(4):619-629. doi:10.1007/s00345-018-2564-4.
5. Chakraborty JN, Enganti B, Nayak P. Female urethroplasty: a critical review of indications, techniques and concerns. Int Urogynecol J. 2026;37(4):823-833. doi:10.1007/s00192-025-06415-4.
6. Lange M, Hage JJ, Hartveld L, Zijlmans HJMAA, van Beurden M. Reconstruction of the meatus urethrae after oncologic vulvectomy: outcome of 42 vaginal flap advancements in 41 women. Ann Plast Surg. 2022;88(5):538-543. doi:10.1097/SAP.0000000000003048.
7. de Lorenzi F, Loschi P, Rietjens M, et al. Neourethral meatus reconstruction for vulvectomies requiring resection of the distal part of the urethra. Eur J Surg Oncol. 2015;41(12):1664-1670. doi:10.1016/j.ejso.2015.07.017.
8. Reid GC, DeLancey JO, Hopkins MP, Roberts JA, Morley GW. Urinary incontinence following radical vulvectomy. Obstet Gynecol. 1990;75(5):852-858. PMID 2325969
9. Colleselli K, Stenzl A, Eder R, et al. The female urethral sphincter: a morphological and topographical study. J Urol. 1998;160(1):49-54. doi:10.1016/s0022-5347(01)63025-8.
10. Hampl M, Langkamp B, Lux J, et al. The risk of urinary incontinence after partial urethral resection in patients with anterior vulvar cancer. Eur J Obstet Gynecol Reprod Biol. 2011;154(1):108-112. doi:10.1016/j.ejogrb.2010.08.018.
11. Osman NI, Mangera A, Chapple CR. A systematic review of surgical techniques used in the treatment of female urethral stricture. Eur Urol. 2013;64(6):965-973. doi:10.1016/j.eururo.2013.07.038.
12. Sarin I, Narain TA, Panwar VK, et al. Deciphering the enigma of female urethral strictures: a systematic review and meta-analysis of management modalities. Neurourol Urodyn. 2021;40(1):65-79. doi:10.1002/nau.24584.
13. Blaivas JG, Santos JA, Tsui JF, et al. Management of urethral stricture in women. J Urol. 2012;188(5):1778-1782. doi:10.1016/j.juro.2012.07.042.
14. Ceccaroni M, Ferrari FA, Roviglione G, et al. Vaginal "tunnel flap" technique for urethral neomeatus reconstruction after distal urethrectomy in advanced vulvar cancer: a case report with anatomical insights. Front Med. 2025;12:1695521. doi:10.3389/fmed.2025.1695521.
15. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
16. de Mooij Y, Burger MP, Schilthuis MS, Buist M, van der Velden J. Partial urethral resection in the surgical treatment of vulvar cancer does not have a significant impact on urinary continence: a confirmation of an authority-based opinion. Int J Gynecol Cancer. 2007;17(1):294-297. doi:10.1111/j.1525-1438.2007.00788.x.
17. Dimarco DS, Dimarco CS, Zincke H, et al. Surgical treatment for local control of female urethral carcinoma. Urol Oncol. 2004;22(5):404-409. doi:10.1016/S1078-1439(03)00174-1.
18. Meilika KN, Sandhu JS. Segmental or total female urethrectomy. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:106.
19. Volkin D, Nitti VW. Diagnosis and management of female urethral stricture disease. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:1204.
20. Lec P, Nitti VW. Female urethral reconstruction. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:683-684.
21. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females. 2026. Official guideline.
22. Chakraborty JN, Chawla A, Vyas N. "Surgical interventions in female urethral strictures: a comprehensive literature review." Int Urogynecol J. 2022;33(3):459-485. doi:10.1007/s00192-021-04906-8.
23. Peyronnet B, Freton L, Marcelli F, et al. "Female urethral stricture." Fr J Urol. 2024;34(11):102749. doi:10.1016/j.fjurol.2024.102749
24. de Toledo IA, DeLong J. "Female urethral stricture: techniques for reconstruction." Plast Aesthet Res. 2022;9:5. doi:10.20517/2347-9264.2021.103