Combined Dorsal BMG + Ventral Fasciocutaneous Flap (Erickson)
The combined dorsal buccal mucosal graft (BMG) with ventral fasciocutaneous flap is a single-stage tissue-transfer technique for complex, long-segment, or obliterative anterior urethral strictures where neither a graft nor a flap alone provides sufficient tissue for circumferential urethral reconstruction. It was described by Erickson, Breyer, and McAninch in 2012.[1][2] The AUA 2023 urethral stricture guideline amendment permits oral mucosal grafts, penile fasciocutaneous flaps, or their combination for long, multi-segment strictures .[3]
For graft material principles, see Buccal Mucosa Graft. For the ventral pedicled-flap principles, see Penile / Preputial Flap. For the dual-BMG (Palminteri / Gelman) alternative, see Dorsal Onlay BMG and Ventral Onlay BMG. The Karapanos plate-and-spongiosum-preserving modification with the Orandi flap is described in the technique section below.
Concept and Rationale
The technique leverages the complementary strengths of two tissue types:
- BMG (dorsal). The graft is free and requires a well-vascularized recipient bed. It is quilted directly onto the tunica albuginea of the corpora cavernosa, which provides imbibition and inosculation.[2][4]
- Fasciocutaneous flap (ventral). The flap is pedicled penile skin that carries its own dartos-fascia blood supply. Placed ventrally, it does not depend on the recipient bed for survival, which suits strictures where ventral spongiofibrosis has compromised local vascularity.[1][5]
Together they form a circumferential neourethra (dorsal BMG roof and ventral flap floor), enabling complete segmental urethral replacement in a single stage.[1]
Indications and Patient Selection
- Long-segment anterior urethral strictures (mean approximately 9.75 cm in the Erickson / McAninch series).[1]
- Obliterative or near-obliterative strictures not amenable to EPA or simple onlay augmentation.[1][2]
- Panurethral or multi-segment strictures involving both penile and bulbar urethra.[1]
- Selected redo repairs with a damaged urethral plate have been described when healthy penile skin remains available; the cited Q-flap report is a single case with three-month follow-up.[5]
- Prerequisite: healthy, non-hair-bearing penile skin available for the fasciocutaneous flap.[1][3]
In a GURS survey conducted in 2022 and published in 2024 (134 of 350 invited responded), 90% preferred multiple BMGs over a combined graft/flap for panurethral strictures.[6] The combined operation remains an option when single-stage repair is desired and the urethral plate is severely compromised. For patients with penile strictures, EAU 2026 strongly recommends counseling that adverse intraoperative findings may require conversion to staged repair.[15]
In lichen sclerosus-proven urethral stricture, the AUA amendment states that surgeons should not use genital skin flaps or grafts, so these patients are not candidates for this technique.[1][3]
Surgical Technique
The table outlines Erickson's segmental replacement and notes selected variants, including Kojovic and Djordjevic's longitudinal dorsal penile-skin flap.[1][2]
| Step | Detail |
|---|---|
| 1. Exposure and flap harvest | Begin in low lithotomy and harvest a 2 cm-wide distal circumferential penile fasciocutaneous flap. Pass a 22 Fr catheter to identify the distal stricture, then extend a ventral urethrotomy proximally to normal-caliber urethra. Add a scrotal split or perineal incision when the bulbar urethra is involved.[1] |
| 2. Segmental excision and dorsal BMG | Excise unusable urethral plate (in general <0.5 cm wide with significant spongiofibrosis) and surrounding diseased spongiosum, then measure the defect. Secure a 1.5–2 cm-wide cheek graft to the native urethral ends and underlying corporal tunica to form the dorsal wall.[1] |
| 3. Ventral fasciocutaneous flap | The original Erickson operation uses a distal circumferential penile fasciocutaneous flap, opened into a strip. Kojovic uses a longitudinal dorsal penile-skin flap transposed ventrally. Preserve the vascular pedicle and join flap margins to graft/native urethral margins as appropriate |
| 4. Neourethral closure | Approximate the dorsal graft and ventral flap around the catheter; at the grafted segment, anchor flap-to-graft sutures to the underlying corporal tunica to limit contraction[1]; when preserved, the corpus spongiosum is wrapped around the repair for additional support[7]. Guidice recommends overlapping the flap's proximal end and the graft's distal end by about 0.5 cm to reduce the risk of an annular, ring-like restenosis at the junction[12] |
| 5. Catheter and closure | In Erickson's protocol, complete the repair over a 16 Fr Foley catheter, maintain drainage for at least three weeks, and obtain VCUG to exclude extravasation before removal; close the wound in layers.[1] |
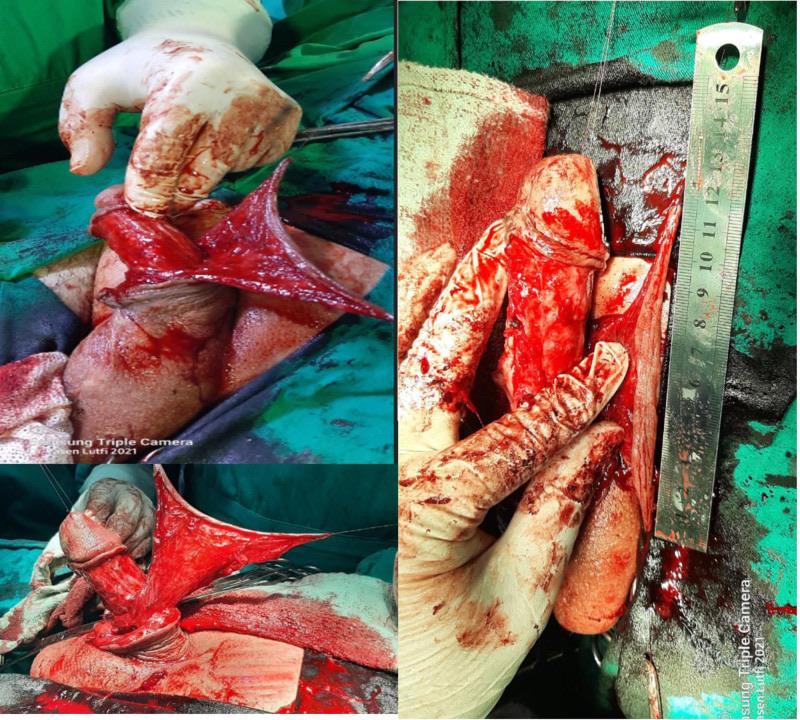
Harvest of a circumferential penile skin flap with a dorsal pedicled extension (Q flap) for the ventral component of a combined repair. From Anadani A, et al. Medicine (Baltimore). 2025;104(12):e41888, Figure 3 (CC BY).[5]
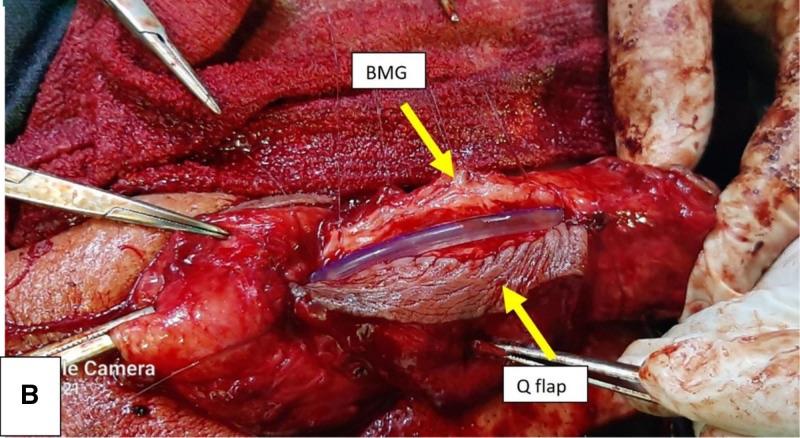
Combined repair in progress: the buccal mucosa graft (BMG) attached dorsally to the damaged urethral plate and the Q flap sutured ventrally. Panel B only; panel A (graft harvest) omitted. From Anadani A, et al. Medicine (Baltimore). 2025;104(12):e41888, Figure 5 (CC BY).[5]
Karapanos modification
Karapanos 2024 preserves the native urethral plate and corpus spongiosum, uses a narrower Orandi-type ventral pedicled penile-skin flap, and wraps the preserved spongiosum ventrally around the flap for reinforcement, yielding a triangular-cross-section neourethra and 91.7% success after a median 38 mo of follow-up for narrow penile strictures, with transient fistulas in 25% (3 / 12) all healing with prolonged catheterization.[7]
Outcomes
| Series | Evaluated n | Stricture length | Reported outcome | Follow-up |
|---|---|---|---|---|
| Erickson 2012[1] | 14 | Mean 9.75 cm; mean circumferential replacement 5.4 cm | 9/14 without further intervention; 11/14 after allowing one endoscopic treatment | Median 2.5 yr |
| Kojovic / Djordjevic 2019[2] | 46 of 51 operated | Mean 5.2 cm | 39/46 patent (84.8%); 36/46 successful voiding (78.3%) when three fistulas also counted | Mean 49 mo |
| Karapanos 2024 (modification)[7] | 12 | Median 5 cm | 11/12 successful (91.7%); three transient fistulas | Median 38 mo |
| Anadani 2025 (case report)[5] | 1 | 5 cm | Early reported success; insufficient for a durability estimate | 3 mo |
Small, uncontrolled series with different operations and endpoints provide no comparison with staged reconstruction. For graft-and-flap substitution repair, EAU 2026 recommends at least one year of follow-up , three-month flexible cystoscopy , and a risk-adjusted protocol ; its standard-risk proposal schedules uroflowmetry and patient-reported outcomes at 3, 12, and 24 months and five years, anatomic assessment at 3, 12, and 24 months (and at five years if indicated), and consideration of longer follow-up after penile or substitution urethroplasty.[16] Erickson reported longer strictures among the five initial failures (12.8 versus 8.7 cm, p = 0.04), an exploratory association in a 14-patient cohort.[1]
Complications
- Stricture recurrence. Recurrence is the primary concern, at 15–36% in the Erickson and Kojovic series (5/14 initial failures and 7/46, respectively).[1][2]
- Urethrocutaneous fistula. Approximately 6.5% in Kojovic; transient fistulas in 25% (3 / 12) in Karapanos, all healing with prolonged catheterization.[2][7]
- Post-void dribbling. Dribbling was reported by 5 of 12 patients (41.7%) in the Karapanos series after spongiosum-preserving repair.[7]
- Sexual outcomes. Reliable technique-specific ED estimates are unavailable from these small series.
- Donor-site morbidity. Buccal graft harvest can cause oral pain, tightness or contracture, sensory changes, and salivary symptoms; severity and duration vary.[4]
In Warner 2015, a retrospective multicenter cohort of 466 strictures at least 8 cm long, flap procedures were associated with 32% complications versus 14% without flaps (p = 0.02).[9]
Comparison With Alternative Approaches
- Dual BMG (Palminteri dorsal and ventral; Gelman / Siegel). Gelman / Siegel reported 94% initial success in 18 patients, with one additional patient successfully treated by DVIU. The ventral graft requires preserved spongiosum; Gelman / Siegel did not compare the technique with a vascularized flap.[10]
- Distal variant (Gelman / Sohn). For obliterative distal strictures with circumferential urethral deficiency, Gelman and Sohn (2011) quilted buccal mucosa to the ventral corpora to rebuild the dorsal urethral plate, usually including the glans and fossa navicularis, and completed a single-stage repair with an onlay penile skin flap. All 12 patients were free of disabling chordee or stricture at a mean 39 months (range 7–96); one urethrocutaneous fistula, and one fistula with medium-caliber fossa narrowing and chordee, were repaired.[14]
- Two-stage repair (Bracka, Johanson). An option when the plate or local tissues cannot support a single-stage repair. Comparable success of the combined operation has not been established in a controlled trial. Genital skin flaps should not be used for LS-related reconstruction.[1][11]
- BMG alone (dorsal or ventral onlay). Suited to non-obliterative strictures. Hassan 2025 meta found no difference in success between dorsal and ventral onlay BMG (RR 1.00, 95% CI 0.94–1.06), though ventral onlay may reduce transient ED.[8]
- Location-based proximal graft, distal flap (Angermeier). For a panurethral stricture with disease-free penile skin available but too short to bridge the whole defect, Angermeier describes a proximal bulbar ventral BMG onlay combined with a distal penile or penoscrotal island flap based on lateral dartos, starting in exaggerated lithotomy for the perineal graft stage and repositioning to low lithotomy before the distal flap work to limit time with the legs elevated.[13]
Key Considerations
- The flap requires healthy, hairless penile skin. Avoid genital skin for LS-related strictures or if available skin is diseased or hair-bearing. Circumcision alone is not an absolute contraindication; assess the remaining skin and its vascularity.[1][3]
- Hair-bearing skin should not be used for substitution urethroplasty because of the risk of urethral calculi, recurrent UTI and lumen obstruction by hair. The exception is a rare case with no alternative.[3]
- The operation is best performed by reconstructive urologists proficient in both graft and flap techniques.[5][11]
Videos
References
1. Erickson BA, Breyer BN, McAninch JW. Single-stage segmental urethral replacement using combined ventral onlay fasciocutaneous flap with dorsal onlay buccal grafting for long-segment strictures. BJU Int. 2012;109(9):1392-1396. doi:10.1111/j.1464-410X.2011.10483.x.
2. Kojovic V, Djordjevic ML, Vuksanovic A. Single-stage repair of obliterated anterior urethral strictures using buccal mucosa graft and dorsal penile skin flap. Int J Urol. 2019;26(1):90-95. doi:10.1111/iju.13816.
3. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
4. Horiguchi A. Substitution urethroplasty using oral mucosa graft for male anterior urethral stricture disease: current topics and reviews. Int J Urol. 2017;24(7):493-503. doi:10.1111/iju.13356.
5. Anadani A, Obaidin A, Badawi B, Lutfi MY. One-stage urethroplasty using a combination of buccal mucosa graft and Q penile skin flap for a complicated urethral stricture: a challenging case report. Medicine. 2025;104(12):e41888. doi:10.1097/MD.0000000000041888.
6. Berg C, Singh A, Hu P, et al. Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons. Urology. 2024;191:139-143. doi:10.1016/j.urology.2024.06.019.
7. Karapanos L, Halbe L, Storz E, et al. Preservation of the native urethral plate and corpus spongiosum combined with buccal mucosa graft plus Orandi's penile skin flap as an alternative to staged urethroplasty for narrow penile strictures. Int J Urol. 2024;31(10):1095-1101. doi:10.1111/iju.15521.
8. Hassan AA, Soliman AM, Shouman HA, et al. Dorsal- vs ventral-onlay buccal mucosal graft urethroplasty for urethral strictures: a meta-analysis. BJU Int. 2025. doi:10.1111/bju.16811.
9. Warner JN, Malkawi I, Dhradkeh M, et al. A multi-institutional evaluation of the management and outcomes of long-segment urethral strictures. Urology. 2015;85(6):1483-1487. doi:10.1016/j.urology.2015.01.041.
10. Gelman J, Siegel JA. Ventral and dorsal buccal grafting for 1-stage repair of complex anterior urethral strictures. Urology. 2014;83(6):1418-1422. doi:10.1016/j.urology.2014.01.024.
11. Patterson JM, Chapple CR. Surgical techniques in substitution urethroplasty using buccal mucosa for the treatment of anterior urethral strictures. Eur Urol. 2008;53(6):1162-1171. doi:10.1016/j.eururo.2007.10.011.
12. Guidice C. Panurethral strictures. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:231-248.
13. Angermeier KW. Anterior urethral reconstruction: ventral grafts. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:464.
14. Gelman J, Sohn W. "1-Stage Repair of Obliterative Distal Urethral Strictures With Buccal Graft Urethral Plate Reconstruction and Simultaneous Onlay Penile Skin Flap." J Urol. 2011;186(3):935-938. doi:10.1016/j.juro.2011.04.056
15. European Association of Urology. "EAU Guidelines on Urethral Strictures: Disease Management in Males." 2026. Guideline
16. European Association of Urology. "EAU Guidelines on Urethral Strictures: Follow Up." 2026. Guideline