Female Dorsal Onlay Urethroplasty
Female dorsal onlay urethroplasty places a tissue graft (buccal, lingual, vaginal, or labial mucosa) on the dorsal (12 o'clock) surface of the urethra to augment a strictured segment. It is an established reconstructive option for female urethral stricture (FUS). Reported outcomes vary by graft, population and follow-up, and current guidance does not establish superiority over ventral reconstruction.[1][2][3]
For the broader female-stricture treatment ladder, see Female DVIU and Urethral Dilation, Distal Urethrectomy with Advancement Meatoplasty, Blandy U-Flap, Lateral-Based Anterior Vaginal Wall Flap, and Female Ventral Onlay BMG. For graft tissue principles, see the Buccal Mucosa Graft (foundations) article.
Epidemiology and Etiology of FUS
FUS accounts for approximately 1% of women presenting with LUTS and is frequently underdiagnosed.[4][5] Most common etiologies:
- Iatrogenic. Repeated dilations, traumatic catheterization, transurethral procedures.[6][7]
- Idiopathic. 53.48% of cases in a 35-study review (488 patients) were presumably idiopathic.[3]
- Obstetric. Particularly cephalopelvic disproportion.[6]
- Lichen sclerosus / lichen planus.[6]
- Pelvic trauma, radiation, urethral / vaginal atrophy, recurrent infection.[6][8]
In Khawaja’s 25-patient series, the largest location category was mid-proximal (40%); mean stricture length was 1.8 cm (range 0.7–2.1 cm).[9]
Diagnosis
The AUA 2023 guideline includes urethral stricture in the differential for women with decreased stream, incomplete emptying, dysuria, recurrent UTI, or rising PVR.[6] Workup:
- Pelvic examination for meatal stenosis, prolapse, vulvar dermatoses and local tissue quality; uroflowmetry (reduced Qmax), PVR, urethral calibration (failure to pass a 14 Fr catheter strongly suggests stricture), cystourethroscopy when feasible, VCUG, and video-urodynamics to distinguish anatomic stricture from functional obstruction.[6][10][5]
Indications
- Recurrent or refractory FUS after failed dilation or DVIU.[6]
- Dorsal onlay has been used for distal, mid, proximal and pan-urethral strictures in selected patients. For an isolated short meatal stricture, the EAU recommends meatotomy/meatoplasty .[29] When a proximal stricture involves the bladder neck, assess continence risk individually; one multicenter series avoided urethroplasty in that setting.[9][11][29][32]
- The 2023 AUA amendment states that urethroplasty should be offered to women with stricture because endoscopic treatment has low efficacy.[6]
- Some experts advocate upfront urethroplasty over serial dilation.[9]
Graft Materials
The operative principles of dorsal onlay (urethral mobilization, dorsal urethrotomy, graft fixation, quilting onto the periurethral bed) are the same for each tissue source. Donor choice depends on tissue availability, prior harvests and patient preference.
| Source | Pros | Cons / Cautions | Anchor evidence |
|---|---|---|---|
| Buccal mucosa (most common default) | Hairless, thick epithelium, infection-resistant, well-suited for wet environment | Oral donor-site morbidity; cheek scarring | Richard 2021 (n=19 oral-graft patients, buccal or lingual; 89.5% patient-reported clinical success at median 12-month follow-up);[2] Khawaja 2022 (n=25, > 90%);[9] Savun 2026 (n=38 dorsal arm, 92.1% by 16 Fr cystoscope passage or Qmax >15 mL/s);[12] Higuchi 2026 (7/8, 87.5%, anatomically stricture-free without reintervention; VFU 4/7, 57.1%, used mainly for distal strictures; median follow-up 12 mo)[11] |
| Lingual mucosa | Same biology as buccal; alternative oral source when buccal sites have been previously harvested | Fewer female reports than buccal; donor-site outcomes come from small series | Sharma 2010 (n=15 women; 1 submeatal stenosis at 3 mo; no neurosensory complications at 1 yr);[13] Simonato 2006 (pilot in 8 men; donor-site data)[14] |
| Vaginal mucosa (free graft) | Same operative field; avoids oral harvest; an option when vaginal mucosa is suitable, including when an adequate pedicled flap cannot be mobilized.[8][15] | Avoid in LS, atrophy or a narrow vaginal introitus; vaginal-narrowing risk if harvest site is poorly selected | Borchert 2022 (technique video)[15] |
For mucosa-tissue principles see Buccal Mucosa Graft (foundations), Labial Mucosa Graft, and Lingual Mucosa Graft.
For free vaginal-graft harvest, Nayyar and colleagues prefer the middle anterior or posterior vaginal wall and avoid the thick, rugose anterior distal one-third, which they preserve as a plane for possible future continence surgery. This is the chapter authors' donor-site preference; head-to-head comparison of vaginal- and oral-graft take is lacking.[20]
Surgical Technique
Dorsal lithotomy.[15][2][16][4]
- Setup. Check a preoperative urine culture, usually one to two weeks before surgery, and treat infection or colonization. Give intraoperative antibiotic prophylaxis .[33] Waterloos and Verla advise a three-month interval after dilation or urethrotomy for stricture maturation and passage of a guidewire into the bladder to avoid a false passage during stricturotomy. Use a urethral catheter for identification when feasible, with a suprapubic catheter as needed.[10][33]
- Suprameatal incision. A semilunar incision above the meatus exposes the dorsal urethral plane.
- Dorsal exposure. Develop the plane between the dorsal urethra and clitoral bodies, protecting the sphincter and neurovascular tissues; this is distinct from ventral urethrovaginal dissection. Palpate the pubic bone to identify the proximal dissection limit.[10]
- Dorsal urethrotomy. Make a longitudinal 12 o'clock incision along the guidewire through the entire stricture until healthy proximal urethra is reached.[10]
- Graft harvest. Buccal, lingual, vaginal or labial; defat and remove fibromuscular tissue from the graft.
- Graft placement. Place stay sutures at the opened urethral edges. Suture the onlay to both urethrotomy edges with running or interrupted absorbable sutures without tension, incorporating periurethral tissue for fixation; Waterloos and Verla begin bilateral running sutures proximally and attach the distal graft edge to the suprameatal incision.[10]
- Graft fixation. Secure the graft to the vascular dorsal recipient bed, with mucosa facing the lumen, avoiding folds or dead space. Waterloos and Verla quilt it to the clitoral bodies at the midline with absorbable sutures.[10]
- Catheter. Waterloos and Verla describe a 16–20 Fr urethral catheter for two to three weeks after dorsal onlay graft repair and removal after urethrography shows no contrast extravasation. Kuo et al. also left an SPC, with both catheters in place for three weeks in their supraurethral case.[10][16]
- Surveillance. In Khawaja’s 25-patient series, symptoms, uroflowmetry and PVR were assessed every three months in the first year and twice yearly thereafter; the series also used inability to pass a 17-Fr cystoscope in its recurrence definition.[9]
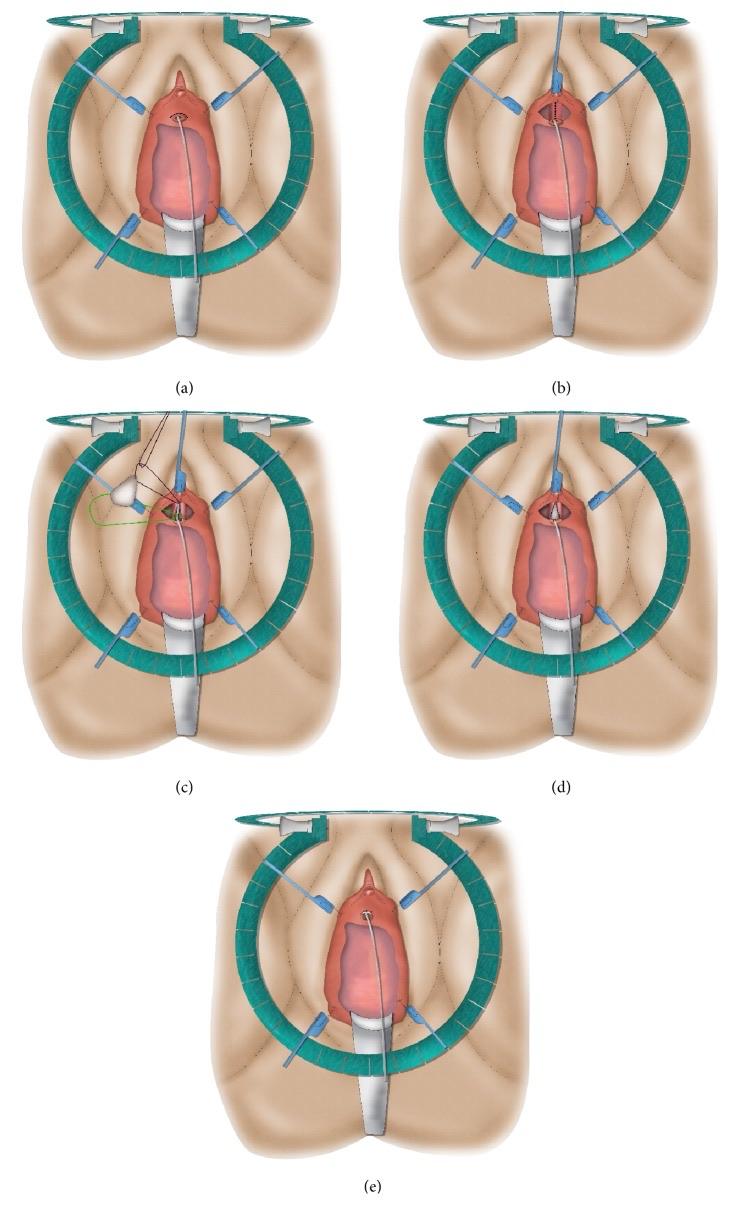
Dorsal onlay free graft urethroplasty: (a) semilunar suprameatal incision; (b) dorsal stricturotomy; (c, d) graft edges sutured to the urethral edges; (e) distal graft edges sutured to the edge of the suprameatal incision. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 8 (CC BY).[10]
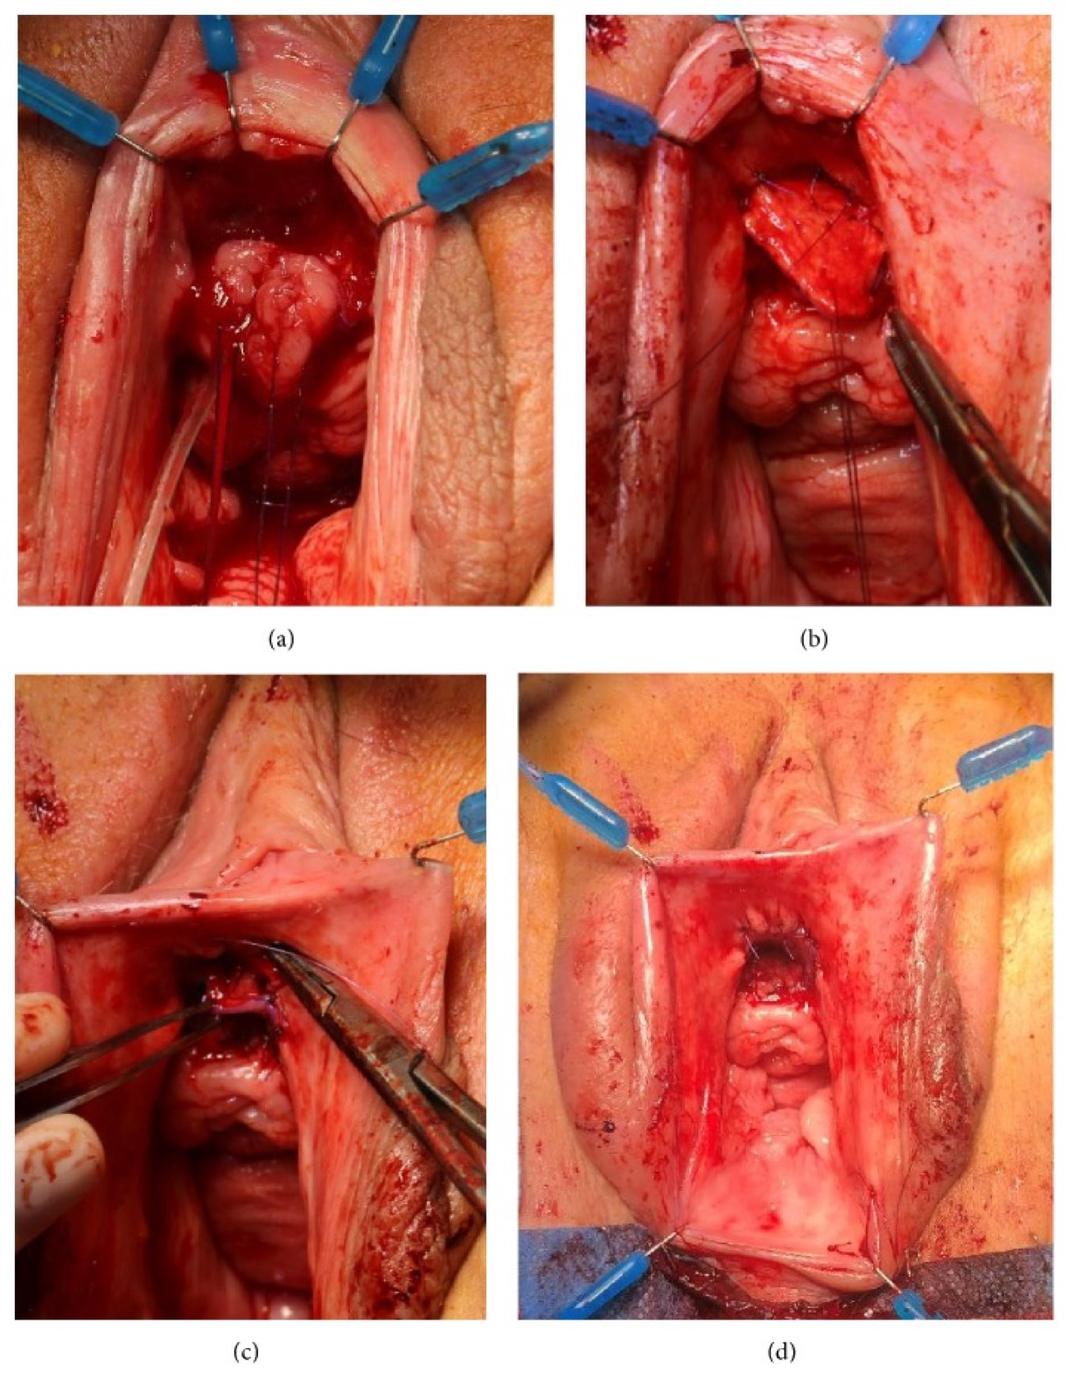
Dorsal onlay buccal mucosa graft urethroplasty: (a) semilunar suprameatal incision and dorsal stricturotomy, with stay sutures on the opened urethra; (b) graft quilted to the surface of the clitoral bodies and its edges sutured to the urethral edges; (c) distal graft edges sutured to the edge of the suprameatal incision; (d) final result. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 9 (CC BY 4.0).
Recipient-bed anatomy. The periurethral and lateral urethropelvic ligaments mark the boundary between the dorsal and ventral dissection planes, and a semicircular perimeatal incision is kept within its intended plane to avoid crossing it; anatomical studies of the female urethral support structures describe them differently.[21][22] The proximal two-thirds of the dorsal urethra has no defined support bed of its own: the recipient bed there is loose areolar or retropubic fibrofatty tissue, while distal clitoral structures provide the bed distally.[23] Nayyar and colleagues describe avoiding division of the endopelvic fascia and superior pubourethral ligament to preserve urethral suspension, avoiding far-lateral urethral mobilization, and avoiding saline hydrodissection, which in their experience makes tissue planes edematous and harder to follow.[20]
Meatal-sparing modification (Mittal 2021). For mid- or proximal strictures, the urethrotomy is centered over the strictured segment, sparing the meatus. The authors proposed this modification to avoid meatal widening and stream spraying; they reported a single case.[17]
Technical tenets. Adequate dorsal dissection and mobilization; full-stricture-length incision; defat the graft; tension-free anastomosis.[15] Some experts advocate extensive grafting of the entire urethra given the difficulty of precisely delineating stricture extent intraoperatively.[9][4]
Graft dimensions. Reported dorsal free-graft sizes vary by author: Alvarez de Toledo harvests and fenestrates a 4 × 2 cm buccal mucosa graft, which he finds generally sufficient even for panurethral stricture given the relatively constant female urethral length, while Lec and Nitti describe a usual dorsal onlay graft of about 2 cm wide by 3–4 cm long. Neither size is a validated standard; the graft is tailored to the individual defect.[24][25]
Outcomes
| Series | n | Graft | Approach | Success | Follow-up |
|---|---|---|---|---|---|
| Richard 2021[2] | 19 | Oral (buccal / lingual) | Dorsal onlay | 89.5% overall; 90.9% at 1 yr | median 12 mo |
| Higuchi 2026[11] | 8 | Buccal mucosa | Dorsal onlay | 87.5% (vs 57.1% VFU same series) | median 12 mo |
| Khawaja 2022[9] | 25 | Buccal mucosa | Dorsal onlay | > 90% | — |
| Savun 2026[12] | 38 (dorsal arm) | Buccal mucosa | Dorsal onlay | 92.1% (16 Fr scope passage or Qmax >15 mL/s) | variable |
| Gomez 2020[4] | pooled review | Buccal mucosa | Dorsal onlay | ~ 86% | mean 21 mo |
| Jena 2025[1] | 204 | Labial mucosa | Dorsal onlay | 93.5% at 2 yr | median 29 mo |
In the 2026 EAU synthesis of 11 dorsal oral-graft studies (319 women), 83% were stricture-free (range 69–95%) at mean or median follow-up of six to 33 months; 2.2% developed new SUI.[29] In the Richard series, Qmax rose from 7.4 to 15.2 mL/s and PVR fell from 161 to 72 mL.[2] Success definitions differ across series: self-assessed LUTS improvement at 1–3 months (Richard), passage of a 16 Fr cystoscope or Qmax >15 mL/s (Savun), and recurrence assessed by symptoms, Qmax/PVR and failure to pass a 17 Fr cystoscope (Khawaja).[2][12][9]
Complications
- De novo SUI was reported in 15.7% at 1–3 months and 9.1% at one year in the Richard dorsal-onlay series.[2] A separate review pooling different female-stricture operations reported that most mild-to-moderate postoperative incontinence improved with pelvic floor exercises.[3]
- Stricture recurrence. Richard reported 1/19 (5.3%) at a median 12 months; Jena reported 6.5% at two years, including four repeat urethroplasties. In a multicenter cohort (n = 165; 33 dorsal grafts), two-year stricture-free survival after dorsal graft was 80% (median follow-up 29 months overall), and prior radiotherapy was independently associated with recurrence across all procedures (p = 0.015).[1][2][31]
- Perioperative complications of Clavien-Dindo grade 2–3 occurred in 2.94% of the Jena series.[1]
- Urinary spraying occurred in 2 of 7 women after vaginal flap urethroplasty and in none after dorsal onlay in the Higuchi series.[11]
- Donor-site morbidity. Buccal harvest can cause oral pain, numbness or mouth tightness; tightness can persist beyond six months in broader urethroplasty donor-site studies. The 2026 EAU guideline recommends counseling about potential complications of oral graft harvest .[30] Free vaginal-graft harvest can narrow the vagina if the donor site is poorly selected.[15][8]
- Bleeding during dorsal dissection. Purohit and Blaivas advise against blind coagulation or suture ligature for troublesome bleeding and instead pack the retropubic space with gauze between the dorsal urethra and pubis for compression; in their experience this has not required retropubic exploration from above.[26]
Dorsal vs Ventral Onlay
The cited studies report success rates of approximately 89–93% across dorsal and ventral approaches, with different success definitions and follow-up periods.[12][18][19] In one single-center randomized trial, 19/20 women analyzed in each dorsal-onlay and ventral-inlay arm met the one-year success endpoint (47 randomized; median follow-up 21 months); the ventral-inlay arm had less blood loss, shorter surgery and less pain at six and 24 hours.[27] A 2025 review found no significant success difference in four comparative cohorts (62/69 dorsal versus 93/103 ventral; OR 0.84, 95% CI 0.30–2.36); 21/25 included studies were level 4 evidence.[28] Practical distinctions:
- Dorsal. The dorsal approach is thought to leave the ventro-lateral urethral support intact, and it is better suited to distal strictures requiring meatal reconstruction.[18][4]
- Ventral. The ventral approach allows easier meatus preservation and a wider operative field, with lower intraoperative bleeding in a small trial. Only specific inlay variants are vaginal-sparing.[12][18][19]
- A multicenter retrospective comparison found no significant difference in de novo SUI, sexual function (FSFI) or patient-reported impression of change between approaches.[12]
Guideline Position
The 2023 AUA Urethral Stricture Disease Guideline Amendment states that surgeons may reconstruct female strictures with oral mucosal grafts, vaginal flaps or a combination. The text adds that urethroplasty should be offered given the low efficacy of endoscopic treatment. It reports success rates of 69–95% across techniques, chosen by surgeon experience.[6] The 2026 EAU guideline recommends initial dilation ; at first recurrence, repeat dilation with weekly intermittent self-dilation using a 16–18 Fr catheter or planned repeat dilation ; and at second recurrence, urethroplasty when self-dilation is unsuitable or definitive treatment is desired .[29]
Summary
Dorsal onlay is one reconstructive option for FUS. Graft and approach are chosen by local anatomy, donor tissue and patient goals. The evidence above ranges from small series to a 204-woman labial-graft cohort, and the AUA guideline does not rank dorsal above ventral reconstruction.[1][2][6] Comparative oral-graft studies have not established superior patency, continence or sexual outcomes for dorsal over ventral repair.[12][27][28]
Videos
References
1. Jena AK, Jena R, Madhavan M, Madhavan K. Dorsal onlay labial mucosal graft urethroplasty in female urethral stricture: outcomes of over 200 cases from a single surgeon. Urology. 2025;204:216-223. doi:10.1016/j.urology.2025.05.040.
2. Richard C, Peyronnet B, Drain A, et al. Dorsal onlay oral mucosa graft urethroplasty for female urethral stricture. Urology. 2021;158:215-221. doi:10.1016/j.urology.2021.09.001.
3. Chakraborty JN, Chawla A, Vyas N. Surgical interventions in female urethral strictures: a comprehensive literature review. Int Urogynecol J. 2022;33(3):459-485. doi:10.1007/s00192-021-04906-8.
4. Gomez RG, Segura FJ, Saavedra A, Campos RA. Female urethral reconstruction: dorsal buccal mucosa graft onlay. World J Urol. 2020;38(12):3047-3054. doi:10.1007/s00345-019-02958-6.
5. Turchi B, Lumen N, Verla W, Waterloos M. Female urethral stricture disease: a narrative review on diagnosis, surgical techniques and outcomes. Int J Impot Res. 2026;38(4):286-295. doi:10.1038/s41443-025-01079-6.
6. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
7. West C, Lawrence A. Female urethroplasty: contemporary thinking. World J Urol. 2019;37(4):619-629. doi:10.1007/s00345-018-2564-4.
8. Bouchard B, Campeau L. Surgery for female urethral stricture. Neurourol Urodyn. 2025;44(1):51-62. doi:10.1002/nau.25358.
9. Khawaja AR, Dar YA, Bashir F, et al. Outcome of dorsal buccal graft urethroplasty in female urethral stricture disease (FUSD): our institutional experience. Int Urogynecol J. 2022;33(3):697-702. doi:10.1007/s00192-021-04840-9.
10. Waterloos M, Verla W. Female urethroplasty: a practical guide emphasizing diagnosis and surgical treatment of female urethral stricture disease. Biomed Res Int. 2019;2019:6715257. doi:10.1155/2019/6715257.
11. Higuchi M, Horiguchi A, Ashiya M, et al. Vaginal flap urethroplasty and dorsal onlay buccal mucosal graft urethroplasty for female urethral stricture: a single-center experience. Int J Urol. 2026;33(5):e70477. doi:10.1111/iju.70477.
12. Savun M, Cubuk A, Colakoglu Y, Aksakal YN, Simsek A. Comparative analysis of dorsal and ventral onlay urethroplasty with buccal mucosal graft in female urethral strictures: a multi-center study. Int Urogynecol J. 2026;37(2):511-516. doi:10.1007/s00192-025-06479-2.
13. Sharma GK, Pandey A, Bansal H, et al. Dorsal onlay lingual mucosal graft urethroplasty for urethral strictures in women. BJU Int. 2010;105(9):1309-1312. doi:10.1111/j.1464-410X.2009.08951.x.
14. Simonato A, Gregori A, Lissiani A, et al. The tongue as an alternative donor site for graft urethroplasty: a pilot study. J Urol. 2006;175(2):589-592. doi:10.1016/S0022-5347(05)00166-7.
15. Borchert A, Jamil M, Perkins S, Raffee S, Atiemo H. Vaginal free graft dorsal onlay urethroplasty. Urology. 2022;159:256. doi:10.1016/j.urology.2021.06.004.
16. Kuo T, Uçar M, Venugopal S, et al. Female urethroplasty with a buccal mucosa graft using a supraurethral approach. Int Urogynecol J. 2024;35(5):1093-1095. doi:10.1007/s00192-024-05737-z.
17. Mittal A, Bahuguna G, Sarin I, et al. Meatal-sparing dorsal onlay vaginal graft urethroplasty: widening the surgical horizons of female urethral stricture. Int Urogynecol J. 2021;32(3):737-739. doi:10.1007/s00192-020-04524-w.
18. Katiyar VK, Sood R, Sharma U, et al. Critical analysis of outcome between ventral and dorsal onlay urethroplasty in female urethral stricture. Urology. 2021;157:79-84. doi:10.1016/j.urology.2021.05.021.
19. Gaur AS, Tarigopula V, Mandal S, et al. Comparison of ventral inlay and dorsal onlay urethroplasty for female urethral stricture. Urology. 2024;193:46-50. doi:10.1016/j.urology.2024.06.046.
20. Nayyar R, Kumar P, Uppal Nayyar B. Dorsal (Anterior) Onlay Urethroplasty for Female Urethral Stricture. In: Khattar N, Nayyar R, Panda A, eds. Female Bladder Outlet Obstruction and Urethral Reconstruction. Springer; 2021:161-168. doi:10.1007/978-981-15-8521-0_14
21. el-Sayed RF, Morsy MM, el-Mashed SM, et al. Anatomy of the urethral supporting ligaments defined by dissection, histology, and MRI of female cadavers and MRI of healthy nulliparous women. AJR Am J Roentgenol. 2007;189(5):1145-1157. doi:10.2214/AJR.07.2215.
22. Fritsch H, Pinggera GM, Lienemann A, et al. What are the supportive structures of the female urethra? Neurourol Urodyn. 2006;25(2):128-134. doi:10.1002/nau.20133.
23. Khattar N, Nayyar R. Applied Anatomy for Female Urethral Reconstruction. In: Khattar N, Nayyar R, Panda A, eds. Female Bladder Outlet Obstruction and Urethral Reconstruction. Springer; 2021:141-160. doi:10.1007/978-981-15-8521-0_13
24. Alvarez de Toledo I. Female Urethral Reconstruction. In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:829-840. doi:10.1007/978-3-031-19598-3_48
25. Lec P, Nitti VW. Female Urethral Reconstruction. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:682-689.
26. Purohit RS, Blaivas JG. Female Urethral Reconstructive Surgery. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:205-220. doi:10.1007/978-3-319-49855-3_19
27. Mandal S, Gaur AS, Singh K, et al. "Comparative efficacy of dorsal-onlay and ventral-1 inlay buccal mucosal graft urethroplasty in female urethral stricture: a randomized clinical trial." Urology. 2025;200:52-58. doi:10.1016/j.urology.2025.01.064
28. Ortac M, Ozervarli MF, Ergul RB, et al. "Comparing ventral and dorsal oral mucosal graft urethroplasty in female urethral stricture: a systematic review and meta-analysis." World J Urol. 2025;43(1):397. doi:10.1007/s00345-025-05773-4
29. European Association of Urology. "EAU Guidelines on Urethral Strictures: Disease Management in Females." 2026, §7.3. Official guideline.
30. European Association of Urology. "EAU Guidelines on Urethral Strictures: Tissue Transfer." 2026, §9.3. Official guideline.
31. Waterloos M, Lumen N, Ockrim JL, et al. "Diagnostics, reconstructive approaches, and outcomes in female urethroplasty patients." BJU Int. 2025;135(6):1025-1030. doi:10.1111/bju.16701
32. Bain M, Gomez Zapata DE, Ravichandran K, et al. "Female urethral stricture: a multi-centre experience and lessons learnt." BJUI Compass. 2025;6(5):e70024. doi:10.1002/bco2.70024.
33. European Association of Urology. "EAU Guidelines on Urethral Strictures: Perioperative Care of Urethral Surgery." 2026, §10.2. Official guideline.