Female Vaginal Flap Urethroplasty (Blandy U-Flap)
The Blandy U-flap vaginal flap urethroplasty is a ventral-inlay vaginal-flap technique for female urethral stricture (FUS) repair. A U-shaped anterior-vaginal-wall flap is mobilized on a proximal pedicle, the strictured urethra is opened ventrally, and the flap is inlaid into the urethrotomy defect to augment the urethral lumen.[1][3] It is the female counterpart of the male ventral-onlay urethroplasty.
For the broader female-stricture treatment ladder, see Female DVIU and Urethral Dilation, Distal Urethrectomy with Advancement Meatoplasty, Lateral-Based Anterior Vaginal Wall Flap, Female Dorsal Onlay BMG, and Ventral Onlay BMG.
Eponym and Concept
Attributed to John Blandy. The U-flap design uses anterior vaginal wall as a pedicled flap (proximal base), preserving the submucosal vascular plexus, and avoids the donor-site morbidity of buccal mucosa.[1][3]
Indications
- Recurrent FUS after dilation or DVIU.[4][5] The EAU 2026 guideline weakly recommends initial dilation and, for first recurrence, repeat dilation with planned weekly 16–18 Fr ISD or planned repeat dilation; it strongly recommends urethroplasty at second recurrence when ISD is unsuitable or the woman wants definitive treatment.[22]
- Distal and mid-urethral disease appears across the cited vaginal-flap and inlay series, which used different repairs.[6][7] For the classic Blandy U-flap, Waterloos and Verla favor meatal or short distal strictures, and Bouchard and Campeau describe best fit within 1 cm of the meatus and for a 1.5–2 cm stricture.[3][23]
- Healthy, well-estrogenized anterior vaginal wall (no LS, no severe atrophy).[4][8]
- Preoperative assessment. Before choosing a vaginal flap, document stricture location and length with VCUG or videourodynamics when feasible; measure flow and PVR, examine vaginal tissue, and obtain a urine culture. Waterloos and Verla advise three months of urethral rest after dilation or urethrotomy.[3][22]
- Selected longer or pan-urethral strictures, which Simonato treated with the lateral-pedicle variant.[9]
Contraindications / Limitations
- Lichen sclerosus or vaginal atrophy compromising the flap.[4][8] Significant vaginal hiatal narrowing is also a reason to avoid Blandy repair in Bouchard and Campeau's chapter.[23]
- Prior pelvic radiation. Assess local tissue quality and counsel about recurrence risk; in a 2025 multicenter urethroplasty cohort, prior radiotherapy was associated with stricture recurrence.[27]
- Prior synthetic midurethral sling. In Önol et al.'s 17-woman series, two women with previous synthetic slings received Martius-reinforced ventral BMG rather than a vaginal flap.[7]
Technique
Dorsal lithotomy under regional or general anesthesia.[2][10]
- Cystourethroscopy. Inspect the stricture and, only if a small scope passes safely, the proximal urethra and bladder; use VCUG or videourodynamics to define stricture length.[3][22]
- Lumen access. When feasible, place a guidewire through the urethra into the bladder before stricturotomy to reduce false-passage risk; use a Foley to identify the lumen only if it passes safely.[2][3]
- Inverted-U vaginal incision. For classic Blandy repair, outline an inverted U on the anterior vaginal wall just below the ventral meatus, preserving the proximal base.[3][23] Hajebrahimi's tubularized variant instead used parallel anterior-vaginal incisions around the meatus.[2]
- Flap elevation. Dissect the vaginal mucosal flap from the ventral urethra while preserving its vascular submucosal layer, then reflect it cephalad to expose the ventral urethra.[2][3]
- Ventral urethrotomy. In the classic Blandy repair, incise at 6 o'clock until healthy proximal mucosa permits passage of a 20 Fr catheter, then place stay sutures on both urethral edges for exposure.[3] Gormley's vaginal-inlay series describes posterior stricture incision, whereas Hajebrahimi's tubularized U-flap variant uses a dorsal incision.[10][2]
- Flap inlay. The distal tip of the vaginal flap is sutured to the proximal end of the urethrotomy with interrupted absorbable sutures. The lateral edges are sutured to the edges of the incised urethral mucosa to augment the ventral circumference.[2][10]
- Distal inset. In the classic Blandy augmentation, continue suturing the flap edges to the urethral edges through the external meatus. Hajebrahimi et al. describe tubularizing the inner flap over a larger Foley catheter in their U-flap variant.[2][3]
- Vaginal closure. In the classic Blandy repair, suture the remaining flap base to the vaginal mucosal borders with interrupted Donati sutures. In Hajebrahimi's tubularized variant, the folded flap's second layer is sutured to native vagina.[2][3]
- Catheter. Waterloos and Verla describe 7–10 days of drainage after an anterior vaginal-wall flap and three weeks after a lateral vaginal-wall flap, with removal after urethrography excludes extravasation.[3]
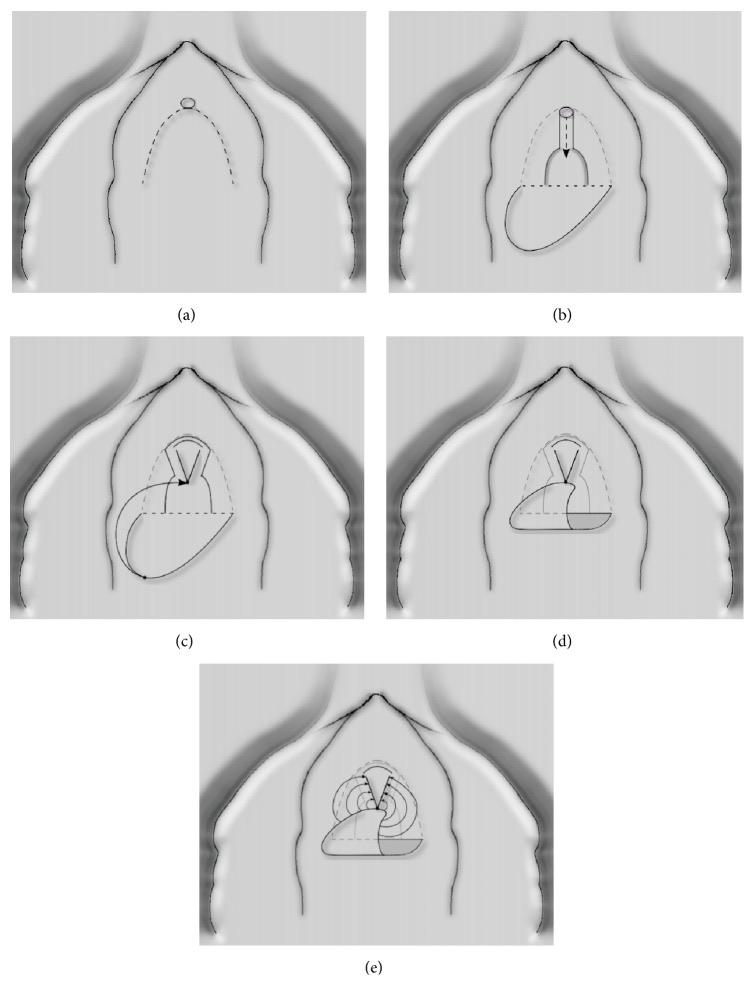
Anterior vaginal wall flap (Blandy flap): (a) inverted-U incision; (b) ventral stricturotomy; (c, d) tip of the U-flap sutured to the proximal end of the opened urethra; (e) remaining flap edges sutured to the urethral edges. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 5 (CC BY).[3]
Hajebrahimi describes the urethral incision as dorsal, so terminology for the urethrotomy orientation differs among reports.[2]
Technical principles. The flap is pedicled, not a free graft. The U must be wide enough to allow tension-free augmentation. The ventral approach leaves the dorsal urethral surface intact.[4][11]
Flap dimensions and calibration. Bouchard and Campeau elevate the anterior vaginal flap over about 3 cm and make it at least 2 cm wide to preserve the submucosal vascular layer and allow for contraction during healing, confirm patency by calibrating to approximately 22 Fr, and use a nasal speculum to check that the proximal stricture has been opened. Their inset places three proximal absorbable sutures with urethral bites out-to-in and flap bites in-to-out so the knots lie on the vaginal side, and the flap is closed with Donati stitches.[23]
Intraoperative bleeding. Purohit and Blaivas control bleeding during vaginal-flap dissection, and during retropubic-space bleeding after vaginal entry, with pressure packing unless an obvious vessel can be coagulated or ligated; for bleeding that seems excessive they avoid exploring through the vaginal wound and instead pack the retropubic space with one or two 4 × 4 sponges or a lap pad through the vagina.[24]
Sling sequencing. When a pubovaginal sling is added for mid- or proximal reconstruction with the inverted-U flap, Lec and Nitti place the sling first and then advance the flap, preferring autologous rectus fascia or fascia lata.[25]
Important Modifications
Lateral-based anterior vaginal wall flap (Romero-Maroto / Simonato)
Romero-Maroto 2018 and Simonato 2010 independently described a lateral-based flap in place of the midline U-flap, and both were inspired by the male Orandi technique. Simonato's lateral pedicle maintains the vascular axis of the flap. His variant also partially de-epithelializes the flap edges to promote cicatrization at the suture line and avoid fistula formation. Romero-Maroto developed the modification because the Blandy technique had produced a retrusive meatus and an inward urinary stream in their patients.[1][9] See Lateral-Based Anterior Vaginal Wall Flap.
Gormley vaginal inlay flap
The Gormley inlay is a simplified variant in which the posterior aspect of the stricture is incised and a vaginal flap is advanced into the defect. In Gormley's 12 women (follow-up 3 months to 9 years), all reported relief of most symptoms and could be catheterized with a 14 Fr catheter, and none had stress incontinence. Urge symptoms and difficulty with catheterization persisted in some women despite a technically good repair.[10]
Blaivas vaginal flap reconstruction (urethral loss / neourethra)
This technique is for urethral loss, not stricture. A vaginal flap is rolled into a tube to create a neourethra and covered with a Martius labial fat-pad flap, usually with a concomitant anti-incontinence procedure. In Blaivas 1989 (10 women), 6 were continent after a single reconstruction.[14] In Blaivas-Heritz 1996 (49 women with urethral or vesical neck damage), a Martius flap was used in 47 and a fascial pubovaginal sling in 41, and 42/49 were continent at 1 to 11 years.[13]
For the Martius flap itself, Purohit and Blaivas make a vertical labia-majora incision through Scarpa's fascia and mobilize the fat pad on its pudendal blood supply, almost always basing it on the internal pudendal artery. To limit bleeding they dissect between Scarpa's fascia and the fat pad; they warn that the more superficial plane between skin and Scarpa's fascia looks easier but contains broad, flat veins that are difficult to control. The flap is tunneled beneath the vaginal epithelium onto the urethral suture line, and a Penrose drain is traditionally left for 24–48 hours.[24]
Dalela W-V vestibular flap (occlusive distal stricture)
Dalela and colleagues reported a W-V vestibular-flap repair in one woman with a totally occlusive distal urethral stricture. A W is marked across the vestibule with its base toward the clitoris, two V-shaped flaps are raised, and the distal urethra is circumferentially mobilized; with a suprapubic antegrade bougie for guidance, the urethral wall is opened posteriorly over its tip and the diseased distal 1.5 cm is excised circumferentially; the medial flap edges are then approximated to convert the W into a V, and the distal urethra is spatulated and joined to the V tip before the remaining flap is tubularized as a neourethra. Each limb descends about 2.5 cm from the meatus. The design keeps a central, forward-facing meatus, though some urinary spraying is still expected.[26]
Outcomes
| Series | n | Technique | Success | Follow-up | Continence outcome / concurrent sling |
|---|---|---|---|---|---|
| Hajebrahimi 2019[2] | 14 | Dorsal-incision, tubularized U-flap variant | 100% (voiding improved) | — | 2/14 postoperative SUI; new onset not specified |
| Gormley 2010[10] | 12 | Vaginal inlay flap | All reported relief of most symptoms | 3 mo–9 yr | 0% |
| Romero-Maroto 2018[1] | 9 | Lateral-based vaginal flap | 100% (no recurrence) | 80.7 mo | 0% |
| Simonato 2010[9] | 6 | Lateral-pedicle vaginal flap | 5/6 needed no additional treatment; 1/6 used CIC for high PVR (recurrence not specified) | 70.8 mo | Not reported |
| Önol 2011[7] | 17 (10 inlay) | Anterior vaginal wall inlay (10) and other techniques | 100% objective (all 17; inlay subgroup not reported separately) | 24 mo (median) | not reported |
| Higuchi 2026[6] | 7 | VFU | 57.1% (4/7) | 12 mo median (whole 15-patient series; VFU-specific follow-up not reported) | 1 in whole series (group not stated) |
| Blaivas 2012[15] | 17 total (9 vaginal flaps; 1 primary BMG) | Vaginal flap in 9 women, including 5 with sling; primary BMG in 1 | 100% at 1 yr; 78% at 5 yr for flap and graft reconstructions combined, not flap-specific | ≥ 1 yr (recurrences at 5.5 and 6 yr) | concurrent sling in 5 flap repairs |
| Flisser-Blaivas 2003[16] | 72 | Vaginal-flap reconstruction for varied urethral pathology; 56 with sling | 93% single-procedure anatomical repair, not stricture-specific patency | 1.5 yr (median) | not isolatable with concurrent slings |
In the Flisser-Blaivas series, 56 of the 72 vaginal-flap patients had a concomitant pubovaginal sling, and of the 62 patients with preoperative incontinence, 54 (87%) considered themselves cured or improved.[16]
The EAU 2026 update pooled 161 women treated with ventral vaginal-flap urethroplasty: 96 inverted-U inlays, 47 lateral C flaps, 17 onlay flaps and one island flap. Patency was 81.4% (range 67–100%) at 10 to 80.7 months, and new-onset urinary incontinence occurred in 15/161 (9.3%).[22] An earlier review of 35 studies (488 patients across all interventions) reported 92.5% success for the local-flap subgroup.[5]
The Retrusive-Meatus / Spraying Problem
Romero-Maroto et al. reported a retrusive meatus and inward urinary stream in their earlier Blandy repairs; the frequency was not quantified.[1] Separately reported events after vaginal-flap urethroplasty include:
- A retrusive (posteriorly displaced) neomeatus.
- An inward urinary stream that sprays the perineum or vagina instead of directing anteriorly.
- Urinary spraying in 2 of 7 (29%) VFU patients in Higuchi 2026, and in none of the BMG patients in the same series.[6]
- Other acute complications in 14 of 161 women (8.7%) in the EAU 2026 pooled data, including UTI and intravaginal direction of the urinary stream.[22]
Romero-Maroto developed the lateral-based flap to preserve meatal position; in their nine-woman observational series, all meatuses remained orthotopic without stream deviation at mean 80.7-month follow-up.[1]
Complications
- Stricture recurrence. Blaivas reported no recurrence at a minimum of 1 year after reconstruction, but two strictures recurred at 5.5 and 6 years; Kowalik reported recurrence requiring dilation in two vaginal-flap patients.[15][17]
- New urinary incontinence, including SUI. Individual vaginal-flap series report postoperative SUI rates of 0–14%; the EAU 2026 vaginal-flap pool reported new urinary incontinence of any type in 15/161 women (9.3%).[2][22] In Hajebrahimi et al., 2/14 developed SUI: one improved by six months and one received a transobturator tape at 12 months.[2] Persistent incontinence requires reassessment of urethral healing, obstruction, tissue quality and continence options.[2][5][22]
- Retrusive meatus and inward stream. These were described with the classic U-flap.[1]
- Urinary spraying. It has been reported in small vaginal-flap cohorts.[6]
- Urgency and urge incontinence. Hajebrahimi et al. reported new urgency and worsening pre-existing urge incontinence; Gormley described persistent urge symptoms despite technically adequate repair.[2][10]
- Urethrovaginal fistula. Flap-edge de-epithelialization (Simonato) and Martius interposition (Blaivas) have been used to lower fistula risk.[9][13]
- Need for CIC. One of 6 women in Simonato's series required CIC.[9]
Comparison with Alternatives
| Feature | Blandy U-Flap | Lateral-Based Flap | Dorsal Onlay BMG | Ventral Onlay BMG |
|---|---|---|---|---|
| Tissue source | Anterior vaginal wall | Anterior vaginal wall | Buccal mucosa | Buccal mucosa |
| Blood supply | Pedicled (proximal base) | Pedicled (lateral base) | Free graft | Free graft |
| Meatal position | Risk of retrusive | Orthotopic | Orthotopic | Orthotopic |
| Urinary spraying | Reported | Not reported | Not reported | Not reported |
| Stricture location | Meatal / short distal (classic U-flap)[3][23] | Distal / mid / pan | Any | Any |
| Reported stricture-free outcome | 10/12 (83%; Gormley U-flap, EAU appraisal)[10][22] | 9/9 (100%; Romero-Maroto lateral flap, mean 80.7 mo)[1][22] | EAU dorsal oral-graft pool (includes 15 LMG; not BMG-only): 83% (69–95%)[22] | EAU ventral oral-graft pool (includes 70 inlays; not onlay-only): 90.7% (86–98%)[22] |
| Donor-site morbidity | No separate harvest site; local vaginal tissue morbidity remains possible[26] | No separate harvest site; local vaginal tissue morbidity remains possible[26] | Oral | Oral |
| Vaginal-tissue health required | Yes | Yes | No | No |
A 2026 meta-analysis of 5 studies (n = 319) found no significant difference between dorsal and ventral onlay BMG in success rate (RR 1.00; 95% CI 0.91–1.10), or in Qmax, PVR or AUA score at 6 months.[20] Katiyar 2021 randomized 24 women to dorsal or ventral onlay and found comparable outcomes, with one recurrence in each arm.[12] The AUA 2023 amendment states that surgeons may reconstruct female strictures with oral mucosal grafts, vaginal flaps or a combination .[21] It cites success rates of 69–95% across techniques and technique choice based on surgeon experience.[21]
When to Choose the Blandy U-Flap
- Stricture is meatal or short (<2 cm) distal, with adequate local vaginal tissue for the classic Blandy U-flap.[4][6][3][23]
- Anterior vaginal wall is healthy and well-estrogenized (no LS).[4][8]
- Surgeon prefers to avoid BMG donor-site morbidity.[19]
- A pedicled (versus free-graft) reconstruction is preferred.
Because of the retrusive-meatus and spraying reports, the lateral-based modification or BMG urethroplasty has been used when the stricture extends beyond the distal urethra.[1][6][18]
Postoperative Management
- Urethral drainage is described for 7–10 days after an anterior vaginal-wall U-flap and for three weeks after a lateral vaginal-wall flap; Waterloos and Verla remove the catheter after urethrography excludes extravasation.[3]
- Voiding trial after catheter removal.
- Uroflowmetry, PVR, and cystoscopy at 3–6 mo.
- Topical estrogen in postmenopausal women.[8]
- Long-term surveillance. Late recurrences ≥ 5 yr documented.[15]
- Catheter fixation. Purohit and Blaivas suture the catheter to the anterior abdominal wall with a gentle loop and check the wound and catheter frequently for pressure on the repair, after one traction episode completely disrupted a repair in an elderly patient; they maintain drainage until voiding at 3 weeks with no extravasation on VCUG.[24]
Summary
The Blandy U-flap is a pedicled vaginal-flap urethroplasty for distal or mid-urethral FUS that avoids a separate oral mucosal harvest; in Gormley’s 12-woman series, 10/12 were stricture-free in the EAU appraisal, while all reported relief of most symptoms at 3 months to 9 years.[3][10][22] Romero-Maroto et al. reported retrusive meatus and inward stream after their earlier Blandy repairs without quantifying frequency; all nine women in their lateral-flap series had an orthotopic meatus and unchanged stream direction at mean 80.7 months.[1] Simonato separately described a lateral-pedicle flap for wide disease.[9] BMG urethroplasty is an alternative when the stricture extends beyond the distal urethra or local tissue is unhealthy.[1][4][5][6]
Videos
References
1. Romero-Maroto J, Verdú-Verdú L, Gómez-Pérez L, et al. Lateral-based anterior vaginal wall flap in the treatment of female urethral stricture: efficacy and safety. Eur Urol. 2018;73(1):123-128. doi:10.1016/j.eururo.2016.09.029.
2. Hajebrahimi S, Maroufi H, Mostafaei H, Salehi-Pourmehr H. Reconstruction of the urethra with an anterior vaginal mucosal flap in female urethral stricture. Int Urogynecol J. 2019;30(12):2055-2060. doi:10.1007/s00192-019-03910-3.
3. Waterloos M, Verla W. Female urethroplasty: a practical guide emphasizing diagnosis and surgical treatment of female urethral stricture disease. Biomed Res Int. 2019;2019:6715257. doi:10.1155/2019/6715257.
4. Bouchard B, Campeau L. Surgery for female urethral stricture. Neurourol Urodyn. 2025;44(1):51-62. doi:10.1002/nau.25358.
5. Chakraborty JN, Chawla A, Vyas N. Surgical interventions in female urethral strictures: a comprehensive literature review. Int Urogynecol J. 2022;33(3):459-485. doi:10.1007/s00192-021-04906-8.
6. Higuchi M, Horiguchi A, Ashiya M, et al. Vaginal flap urethroplasty and dorsal onlay buccal mucosal graft urethroplasty for female urethral stricture: a single-center experience. Int J Urol. 2026;33(5):e70477. doi:10.1111/iju.70477.
7. Önol FF, Antar B, Köse O, Erdem MR, Önol ŞY. Techniques and results of urethroplasty for female urethral strictures: our experience with 17 patients. Urology. 2011;77(6):1318-1324. doi:10.1016/j.urology.2011.01.017.
8. West C, Lawrence A. Female urethroplasty: contemporary thinking. World J Urol. 2019;37(4):619-629. doi:10.1007/s00345-018-2564-4.
9. Simonato A, Varca V, Esposito M, Carmignani G. Vaginal flap urethroplasty for wide female stricture disease. J Urol. 2010;184(4):1381-1385. doi:10.1016/j.juro.2010.06.042.
10. Gormley EA. Vaginal flap urethroplasty for female urethral stricture disease. Neurourol Urodyn. 2010;29 Suppl 1:S42-S45. doi:10.1002/nau.20814.
11. Faiena I, Koprowski C, Tunuguntla H. Female urethral reconstruction. J Urol. 2016;195(3):557-567. doi:10.1016/j.juro.2015.07.124.
12. Katiyar VK, Sood R, Sharma U, et al. Critical analysis of outcome between ventral and dorsal onlay urethroplasty in female urethral stricture. Urology. 2021;157:79-84. doi:10.1016/j.urology.2021.05.021.
13. Blaivas JG, Heritz DM. Vaginal flap reconstruction of the urethra and vesical neck in women: a report of 49 cases. J Urol. 1996;155(3):1014-1017. doi:10.1016/s0022-5347(01)66372-9. PMID: 8583550.
14. Blaivas JG. Vaginal flap urethral reconstruction: an alternative to the bladder flap neourethra. J Urol. 1989;141(3):542-545. doi:10.1016/s0022-5347(17)40887-1.
15. Blaivas JG, Santos JA, Tsui JF, et al. Management of urethral stricture in women. J Urol. 2012;188(5):1778-1782. doi:10.1016/j.juro.2012.07.042.
16. Flisser AJ, Blaivas JG. Outcome of urethral reconstructive surgery in a series of 74 women. J Urol. 2003;169(6):2246-2249. doi:10.1097/01.ju.0000061763.88247.16.
17. Kowalik C, Stoffel JT, Zinman L, Vanni AJ, Buckley JC. Intermediate outcomes after female urethral reconstruction: graft vs flap. Urology. 2014;83(5):1181-1185. doi:10.1016/j.urology.2013.12.052.
18. Savun M, Cubuk A, Colakoglu Y, Aksakal YN, Simsek A. Comparative analysis of dorsal and ventral onlay urethroplasty with buccal mucosal graft in female urethral strictures: a multi-center study. Int Urogynecol J. 2026;37(2):511-516. doi:10.1007/s00192-025-06479-2.
19. Borchert A, Jamil M, Perkins S, Raffee S, Atiemo H. Vaginal free graft dorsal onlay urethroplasty. Urology. 2022;159:256. doi:10.1016/j.urology.2021.06.004.
20. Li X, Zhao X, Li Z, et al. Dorsal versus ventral onlay buccal mucosal graft urethroplasty in female urethral stricture: a meta-analysis. Int Urogynecol J. 2026;37(8):2303-2311. doi:10.1007/s00192-026-06516-8.
21. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
22. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females (limited update 2026), section 7.3.2. Guideline.
23. Bouchard B, Campeau L. Female Blandy Flap Urethroplasty. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:43-47. doi:10.1007/978-981-97-5196-9_6
24. Purohit RS, Blaivas JG. Female Urethral Reconstructive Surgery. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:205-220.
25. Lec P, Nitti VW. Female Urethral Reconstruction. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:682-689.
26. Dalela D, Gupta P, Dalela D, Govil T. W-V flap: a new technique for reconstruction of female distal urethral stricture using vestibular mucosa. BMJ Case Rep. 2016;2016:bcr2016215309. doi:10.1136/bcr-2016-215309.
27. Waterloos M, Lumen N, Ockrim JL, et al. "Diagnostics, reconstructive approaches, and outcomes in female urethroplasty patients." BJU Int. 2025;135(6):1025-1030. doi:10.1111/bju.16701