Female Ventral Inlay BMG Urethroplasty
Ventral inlay buccal mucosal graft urethroplasty is a vaginal-sparing option for female urethral stricture. The stricture is opened through the meatus or transurethrally and augmented with oral mucosa while preserving the anterior vaginal wall. Small female studies report ventral-inlay success from 10/14 (71%) in a two-center retrospective subgroup at mean cohort follow-up of 27 months to 19/20 (95%) in the analyzed arm of a randomized trial at one year.[10][2]
For the related techniques, see Female Ventral Onlay, Female Dorsal Onlay and the Female Dilation / Reconstruction Pathway.
Access and Patient Selection
| Feature | Ventral inlay | Ventral onlay |
|---|---|---|
| Access | Meatal/transurethral | Through an anterior vaginal incision |
| Vaginal wall | Preserved in the vaginal-sparing variant | Opened and closed separately |
| Graft fixation | Secured to urethral margins and recipient bed | Secured to urethral margins with periurethral tissue coverage |
| Selection | Requires adequate exposure and viable recipient tissue | Provides wider open exposure |
Confirm an anatomical stricture and define its length, location and proximity to the continence mechanism before selecting reconstruction. Recurrent disease, patient preference for definitive treatment, donor and recipient tissue quality and surgeon experience guide the choice. In a two-center retrospective cohort, four of 14 ventral-inlay patients required further dilation or surgery (three distal and one mid-distal strictures); two distal patients underwent repeat urethroplasty.[10] The AUA 2023 amendment states that surgeons may reconstruct female strictures with oral mucosal grafts, vaginal flaps or both .[5] The EAU 2026 guideline strongly recommends urethroplasty after a second recurrence when a woman cannot perform intermittent self-dilatation or wants definitive treatment; technique selection depends on tissue quality and surgeon experience.[6] The AUA discussion favors offering urethroplasty once female stricture is diagnosed, whereas the EAU weakly recommends initial dilation.[5][6]
Vaginal sparing may be helpful after prior vaginal surgery or when further vaginal dissection is undesirable. Assess periurethral scarring, support, baseline continence and graft-bed viability.
Operative Principles
The cited female techniques use a ventral urethrotomy through meatal or transurethral access, extending the stricture opening into healthy urethral mucosa. Oral mucosa is harvested and prepared to fit the defect, then secured proximally, along the urethral margins and to the recipient bed. Maintain a tension-free inset, mucosa facing the lumen, and preserve the vaginal wall and periurethral support.[1][2][3]
The steps are:
- Position the patient in dorsal lithotomy. Identify the lumen with a guidewire and expose the stricture under direct vision; place the drainage catheter after graft fixation.[9]
- Work through the meatus, with no vaginal-wall incision.
- Incise the ventral urethral mucosa and underlying fibrosis at 6 o'clock across the stricture without opening the full urethral wall or entering the urethrovaginal plane. Extend proximally to healthy mucosa and distally to the meatus when it is involved.[9][10]
- Harvest buccal mucosa from the inner cheek, remove fibromuscular tissue and trim the graft to the urethrotomy defect.
- Secure the graft proximally, then along both urethral margins, and fix it to the periurethral recipient bed, using quilting sutures if needed for spread fixation.
- Secure the distal end of the graft at the meatus.
- Leave a urethral catheter.
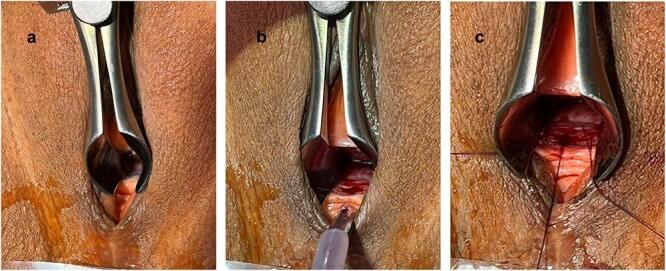
Female ventral inlay buccal mucosal graft urethroplasty: (a) exposure of the urethral stricture with a nasal speculum; (b) after urethrotomy at 6 o'clock; (c) 5-0 PDS sutures placed at 5, 6 and 7 o'clock. From Burkhardt O, et al. J Surg Case Rep. 2023;2023(2):rjad025, Figure 1 (CC BY 4.0).[8]
The graft lies on the native periurethral bed. Inlay repair does not use the periurethral fascial flaps of ventral onlay. Meatal access gives a narrower view than open vaginal exposure.
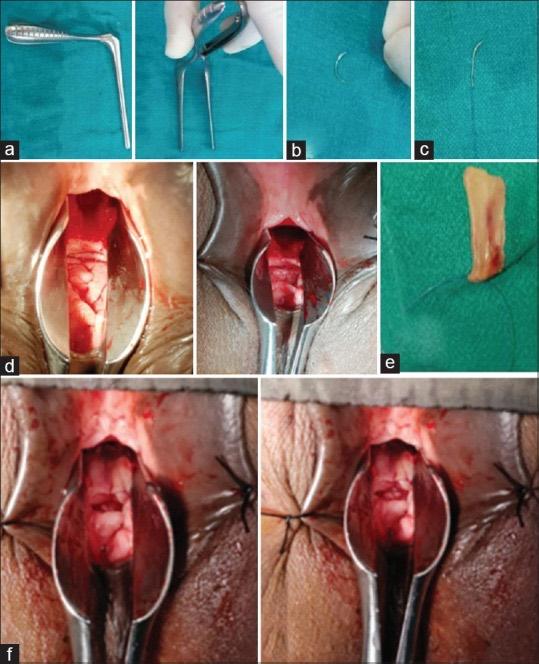
Female ventral inlay urethroplasty: (a) nasal speculum; (b) standard needle; (c) curved needle; (d) after incision of the strictured mucosa and spongiosum; (e) buccal mucosa with suture; (f) after fixation of the buccal mucosa to the bed. From Nayak P, et al. Indian J Urol. 2019;35(4):273-277, Figure 2 (CC BY-NC-SA 4.0).[9]
Catheter size and duration, suture choice and fixation method vary among reports and should follow the actual female technique and intraoperative findings. The Sterling/Nikolavsky transurethral technique for fossa navicularis and distal strictures is a male operation.[7] See the separate male transmeatal technique.
Female Outcome Evidence
| Study | Population / design | Reported outcome | Interpretation |
|---|---|---|---|
| Gaur 2024[1] | Female comparative cohort; 46 ventral-inlay and 27 dorsal-onlay patients | 89.1% success, median follow-up 27.5 months; dorsal-onlay group 88.9% at median 14 months | Follow-up differed between groups |
| Mandal 2025[2] | Single-center randomized trial: 47 randomized, 40 analyzed (20 per arm) | One failure per arm at one year; 95% success in each; median follow-up 21 months | Exclusions after randomization |
| Kumaraswamy 2022[3] | Retrospective analysis of prospectively maintained data, 21 women | 90.5% overall success; life-table estimate 85% at 2–5 years; median follow-up 42 months | Later estimates are based on fewer patients at risk |
| Gülpınar 2021[4] | Small observational comparison; eight vaginal-sparing inlay patients | 87.5% success among the eight inlay patients; median postoperative follow-up of 24.6 months was reported for the full 34-patient, three-technique cohort | Insufficient to rank three techniques |
The Kumaraswamy series reported improved symptoms, flow and residual urine in all but 3 patients, with no urinary incontinence. Median AUA symptom score fell from 27 to 9, median PVR from 138 to 24 mL, and mean Qmax rose from 7.7 to 22.6 mL/s. Recurrence, incontinence, donor-site symptoms, urinary spraying, infection and fistula remain relevant outcomes to monitor.[3]
The EAU 2026 update pooled 247 ventral oral-mucosal graft repairs: 177 onlay BMG and 70 inlay repairs. Combined stricture-free rates were 90.7% (range 86–98%) at 6 to 38.1 months, and eight women (3.2%) developed new-onset SUI; neither pooled percentage is inlay-specific.[6] A randomized 12-per-arm trial compared ventral with dorsal onlay and found one recurrence in each arm at six months; another randomized trial compared ventral inlay with dorsal onlay and found one failure in each of two 20-patient analyzed arms at one year.[11][2]
Long-Term Durability
The Kumaraswamy life-table analysis gives the longest follow-up for inlay repair. Success was 95% at 1 year and 85% at each of 2, 3, 4 and 5 years.[3] The two failures occurred at 6 and 24 months, and the minimum follow-up was 24 months.[3] Gaur 2024 reports median follow-up of 27.5 months (range 11–55) after ventral inlay and 14 months (range 7–17) after dorsal onlay.[1]
What the 2025 Randomized Trial Adds
In the 40 analyzed participants, ventral inlay had shorter median operating time (30 versus 44.5 minutes; p < 0.001), lower median blood loss (10 versus 15 mL; p = 0.012) and lower pain scores at 6 and 24 hours (not at 48 hours), with less analgesia required. Success was 95% in each arm.[2]
The authors list small sample size and single-institution experience as limitations. Most inlay data come from one group, so the results need confirmation elsewhere. Katiyar 2021 is another small randomized female comparison (dorsal versus ventral onlay).[6]
Follow-up and Remaining Uncertainty
Assess voiding symptoms, uroflowmetry, residual urine, continence and sexual function after repair, using cystoscopy or other anatomical evaluation when indicated. Late recurrence can occur. The current evidence supports ventral inlay as one reconstructive option in experienced hands.[3][5][6]
Videos
References
1. Gaur AS, Tarigopula V, Mandal S, et al. Comparison of ventral inlay and dorsal onlay urethroplasty for female urethral stricture. Urology. 2024;193:46-50. doi:10.1016/j.urology.2024.06.046.
2. Mandal S, Gaur AS, Singh K, et al. Comparative efficacy of dorsal-onlay and ventral-inlay buccal mucosal graft urethroplasty in female urethral stricture: a randomized clinical trial. Urology. 2025;200:52-58. doi:10.1016/j.urology.2025.01.064.
3. Kumaraswamy S, Mandal S, Das MK, Nayak P. Long-term follow-up and success rate of ventral inlay buccal mucosal graft urethroplasty for female urethral stricture disease. Urology. 2022;166:146-151. doi:10.1016/j.urology.2022.05.002.
4. Gülpınar Ö, Zumrutbas AE, Sancı A, et al. The outcomes of three buccal mucosal graft urethroplasty techniques in women with urethral stricture disease. Neurourol Urodyn. 2021;40(8):1921-1928. doi:10.1002/nau.24764.
5. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
6. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females (limited update 2026), section 7.3.2. Guideline.
7. Sterling J, Daneshvar M, Nikolavsky D. Transurethral ventral inlay buccal mucosa graft urethroplasty: technique and intermediate outcomes. BJU Int. 2023;132(1):109-111. doi:10.1111/bju.16007.
8. Burkhardt O, Schmid HP, Engeler D, Zumstein V. Ventral-inlay buccal mucosal graft urethroplasty in a 44-year old female patient with recurrent urethral stricture. J Surg Case Rep. 2023;2023(2):rjad025. doi:10.1093/jscr/rjad025.
9. Nayak P, Mandal S, Das M. Ventral-inlay buccal mucosal graft urethroplasty for female urethral stricture. Indian J Urol. 2019;35(4):273-277. doi:10.4103/iju.iju_57_19.
10. Bain M, Gomez Zapata DE, Ravichandran K, et al. "Female urethral stricture: A multi-centre experience and lessons learnt." BJUI Compass. 2025;6(5):e70024. doi:10.1002/bco2.70024
11. Katiyar VK, Sood R, Sharma U, Goel HK, Gahlawat S, Desai DS. "Critical analysis of outcome between ventral and dorsal onlay urethroplasty in female urethral stricture." Urology. 2021;157:79-84. doi:10.1016/j.urology.2021.05.021