Female Ventral Onlay Urethroplasty
Female ventral onlay urethroplasty places a tissue graft (usually buccal mucosa) or pedicled flap on the ventral (6 o'clock) surface of the urethra to augment a strictured segment. In the cited studies, Berdondini reported 41/42 (98%) stricture-free at mean 38.1 months, Katiyar reported one recurrence among 12 ventral-onlay patients, and Savun reported 25/27 (92.6%) composite patency at final follow-up, defined by 16-Fr cystoscope passage or Qmax >15 mL/s.[1][2][3] Compared with dorsal onlay, a small randomized trial found easier meatus preservation and a wider operative field with the ventral approach, and it was associated with less intraoperative bleeding. Conventional ventral onlay still requires vaginal dissection; vaginal sparing refers to specific inlay variants.[1][2][3]
For the dorsal counterpart see Female Dorsal Onlay Urethroplasty. For the inlay variant (graft placed into the urethrotomy without urethral mobilization), see Female Ventral Inlay BMG (Mandal RCT). For pedicled-flap alternatives see the Blandy U-Flap, Lateral-Based Anterior Vaginal Wall Flap, and Önol Anterior Vaginal Wall Mucosal Inlay.
Rationale and Indications
Indications mirror those for dorsal onlay: recurrent or refractory FUS after failed dilation or DVIU. For a first recurrence after dilation, the EAU recommends repeat dilation followed by planned weekly intermittent self-dilation with a 16–18 Fr catheter, or planned repeat dilation ; after a second recurrence, it recommends urethroplasty when self-dilation is not feasible or the patient prefers definitive treatment .[19] The AUA 2023 amendment states that surgeons may reconstruct female strictures with oral mucosal grafts, vaginal flaps or a combination .[4] It cites low efficacy of endoscopic treatment and success of 69–95% across techniques, with technique chosen by surgeon experience.[4]
The ventral approach is particularly favored when:
- Meatus preservation is desired (mid- or proximal strictures).[2]
- Anterior vaginal access is acceptable. Conventional ventral BMG onlay avoids vaginal graft harvest but requires a vaginal incision.[1][19][5] Gaur compared ventral inlay BMG with dorsal onlay BMG.[1][19][5]
- The ventral urethra has suitable tissue quality and the stricture location permits ventral onlay; Savun’s retrospective cohort reported median blood loss of 10 mL with ventral versus 20 mL with dorsal onlay (p = 0.001), but whether this difference changes patient outcomes is unknown.[19][3]
- The surgeon prefers the ventral dissection plane. A step-by-step video demonstrates the operation for female pelvic reconstructive surgeons.[12]
Graft / Flap Options
| Source | Pros | Cons / Cautions |
|---|---|---|
| Buccal mucosa graft (BMG) | Most commonly reported; thick epithelium, hairless, infection-resistant; periurethral fascia provides vascular bed[1][7] | Oral donor-site morbidity; mouth tightness may persist beyond six months after BMG harvest.[22] |
| Vaginal wall pedicled flap | Own blood supply; useful for distal strictures; lateral-based variant preserves orthotopic meatus[8] | Vaginal-flap anatomical success was 4/7 (57.1%) in one 15-patient series (median follow-up 12 months overall), and two-year stricture-free survival was 73% in a separate ventral onlay flap cohort; spraying was reported after vaginal flap urethroplasty[9][10] |
| Vaginal wall free graft (dorsal alternative) | Avoids oral harvest; all 75 vaginal free-graft repairs in the EAU review used a dorsal approach.[19] | Avoid with LS or vaginal atrophy; harvesting may further narrow an already narrow introitus.[21] Kumar 2025 reported pooled success of 86.2% with BMG versus 89.8% with vaginal graft across approaches, using Qmax >15 mL/s at three months, PVR <30 mL and symptom improvement in its success definition.[11] |
Surgical Technique — Ventral Onlay BMG
Dorsal lithotomy.[1][12][7][13]
- Setup. When the stricture permits, pass a guidewire through the urethra into the bladder before opening it to reduce false-passage risk.[21] A urethral catheter identifies the urethra when it passes safely. Passing a Fogarty embolectomy catheter through the stricture into the bladder and withdrawing it with the balloon inflated has been described to palpate and mark the proximal margin of the stricture before the incision is made.[20]
- Anterior vaginal wall incision. Longitudinal, over the urethra.
- Periurethral fascia dissection. Incise the fascia and elevate two lateral fascial flaps, exposing the ventral urethral surface. These flaps are the analog of the male dartos and form the vascular bed for the graft.[1]
- Ventral urethrotomy. Make a longitudinal 6 o'clock incision through the entire stricture into healthy proximal urethra. Extend distally to healthy urethra when present, or through the meatus when distal disease involves it.[1][21] One described technique extends the incision about 0.5 cm beyond each end of the stricture and calibrates the proximal and distal normal urethra to at least 30 Ch before graft sizing.[20]
- BMG harvest. Identify and avoid Stensen's duct. Harvest inner-cheek mucosa while leaving underlying muscle and fat in place, then remove excess submucosal fat from the graft.[13]
- Graft placement. Graft sutured to the urethral mucosal margins on both sides (running or interrupted absorbable); tension-free augmentation. One described sequence places three apical sutures proximally (7, 6 and 5 o'clock) before running the lateral anastomoses from the proximal apex toward the meatus; when the stricturotomy extends through the meatus, the distal graft edge can instead be everted about 0.3–0.5 cm to form the ventral half of the neomeatus, or closed with additional distal apical sutures.[20]
- Fascial flap coverage. Periurethral fascial flaps closed over the graft, providing the vascularized bed and mechanical support.[1]
- Vaginal wall closure. Anterior vaginal wall closed over the repair.
- Catheter. Keep the urethral catheter for approximately 2–3 weeks after ventral onlay graft repair; an SPC may also be present. Waterloos and Verla describe removing the urethral catheter after urethrography shows no contrast extravasation.[21]
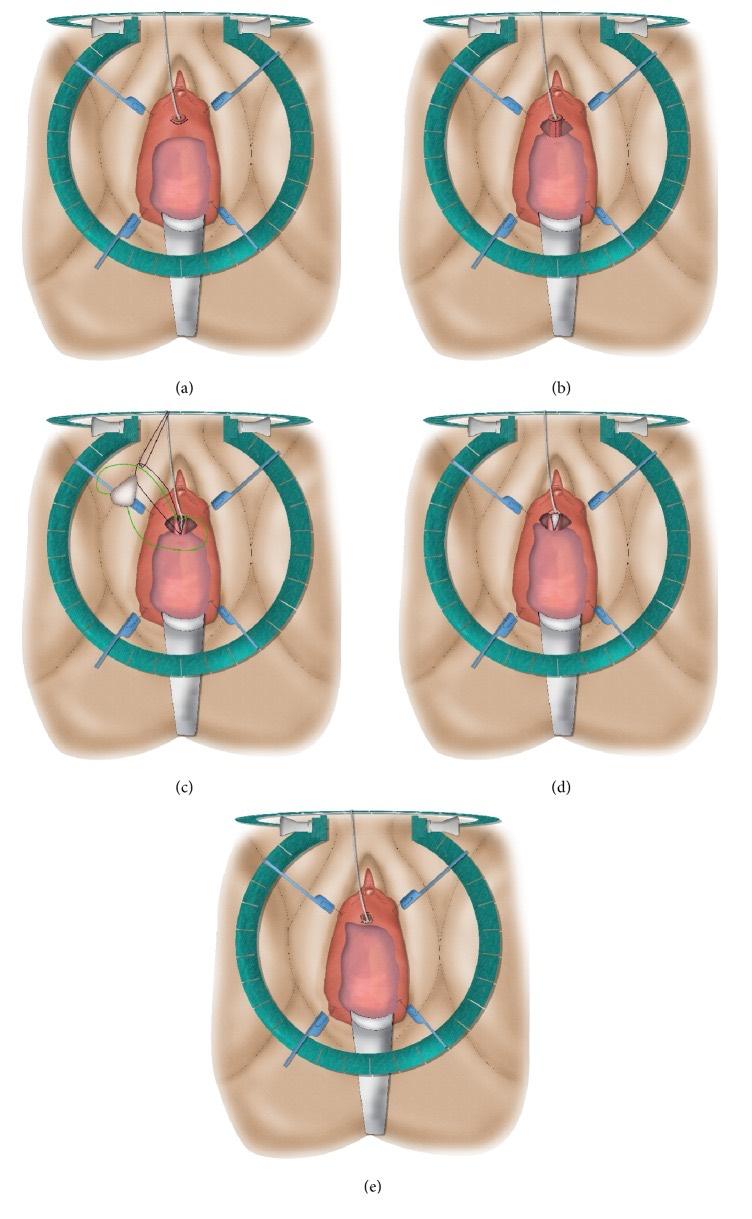
Ventral onlay free graft urethroplasty (a variant with a semilunar inframeatal incision): (a) semilunar inframeatal incision; (b) ventral stricturotomy; (c, d) suturing the graft edges to the urethral edges; (e) suturing the distal graft edges to the edge of the inframeatal incision. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 10 (CC BY 4.0).[21]
Modified "AZ" technique (Ozlulerden 2020)
In Ozlulerden's AZ modification, three proximal graft-to-urethra sutures are left untied while the BMG is quilted to a raised anterior vaginal wall flap. The proximal sutures are tied, the graft-bearing flap is anastomosed to the urethral and vaginal edges, and the remaining vaginal incision is closed.[13] In the first 7 patients (mean follow-up 23 months), Qmax rose from 5.1 to 31.8 mL/s and PVR fell from 84 to 7 mL at 3 months. The authors saw no infection, vaginal erosion, urinary incontinence or oral discomfort, and mean operating time was 64 minutes.[13]
Martius-Reinforced Ventral BMG Onlay
When the periurethral tissue is compromised (typically after synthetic sling or mesh erosion, prior failed urethroplasty, or pelvic radiation), the periurethral fascial bed is unreliable as a vascular supply for the graft. In these cases, a Martius (labial fat-pad) flap is mobilized and interposed between the BMG and the vaginal-wall closure to provide a vascularized second layer. Önol et al. described this Martius-reinforced ventral BMG approach in 2 of 17 women with prior synthetic midurethral slings; the broader 17-patient series achieved 100% objective cure at median 24 months.[17] In a series of 159 women, Martius interposition was used in 12 women having urethroplasty for stricture. Harvest morbidity was low, with labial hematoma in 1.25% and wound infection in 0.6%.[18] A posterior-pedicle modified Martius flap, harvested from the patient's right labium majus for a right-handed surgeon and quilted to the BMG with its distal free edge everted to help form the neomeatus, has also been described.[20]
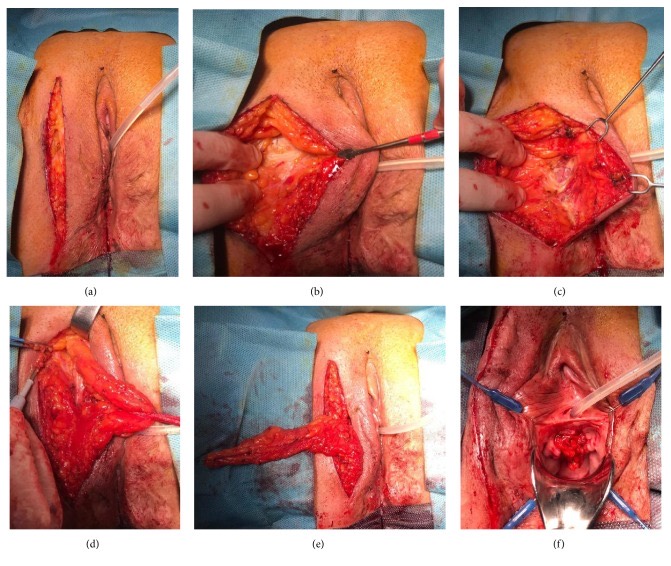
Martius flap after ventral urethral repair. (a) Sagittal labial incision line. (b) Lateral dissection to the labiocrural fold. (c) Medial dissection up to the bulbospongiosus muscle. (d) Mobilization of the flap. (e) Division of the anterior pedicle. (f) The flap transposed over the ventrally reconstructed urethra. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 12 (CC BY 4.0).[21]
Circumstances in which Martius reinforcement has been used or proposed:
- Prior synthetic midurethral sling or vaginal mesh erosion.
- Failed prior urethroplasty with scarred / poorly vascularized periurethral bed.
- Pelvic radiotherapy.
- Adjunctive coverage of a tenuous closure layer.
Technical tenets:
- Urethrotomy must extend through the entire stricture length into healthy tissue.
- Periurethral fascial flaps provide the vascular bed needed for graft take (analog of dartos in male urethroplasty).[1]
- Ventral dissection preserves the dorsal urethral sphincter plane, a proposed anatomical advantage. A lower de novo SUI risk than with dorsal onlay remains theoretical and was not demonstrated in the Savun comparative cohort.[1][3][21]
Surgical Technique — Ventral Vaginal Flap
A pedicled anterior vaginal wall flap rather than a free graft:[8][14]
- Two parallel incisions on the anterior vaginal wall around the meatus.
- Raise a U-shaped (Blandy) or lateral-based vaginal flap with vascular pedicle intact.
- Ventral urethrotomy through the stricture.
- Rotate and suture the flap to the urethral edges.
- Close the remaining vaginal wall.
The lateral-based anterior vaginal wall flap (Romero-Maroto) achieved 100% success in n = 9 at mean 80.7 mo with no recurrence, no de-novo SUI, and orthotopic meatus.[8]
Outcomes
| Series | n | Technique | Success | Follow-up | Key findings |
|---|---|---|---|---|---|
| Berdondini 2024[1] | 42 | Ventral BMG | 98% | mean 38.1 mo | Qmax 7.7 → 25.9 mL/s; 0% incontinence |
| Mukhtar / Greenwell 2017[7] | 22 | Ventral BMG | 95.5% | median 21.5 mo | Qmax 7 → 18 mL/s; 1 mild SUI (resolved) |
| Savun 2026 (multicenter)[3] | 27 (ventral arm) | Ventral BMG | 92.6% | variable | Comparable patency to dorsal (92.1%); less bleeding |
| Coguplugil 2021[15] | 8 | Ventral BMG | 100% | mean 16.4 mo | No SUI; 1 dyspareunia |
| Ozlulerden 2020 ("AZ")[13] | 7 | Modified ventral BMG | Flow and PVR improved in all 7 | mean 23 mo | Qmax 5.1 → 31.8 mL/s (3 mo) |
| Romero-Maroto 2018[8] | 9 | Ventral vaginal flap (lateral-based) | 100% | mean 80.7 mo | Orthotopic meatus; 0% recurrence / SUI |
| Waterloos / Lumen EAU 2025[9] | 165 total: 115 VOGU / 17 VOFU / 33 DOGU | Ventral graft / flap; dorsal graft comparator | 86% / 73% ventral at 2 yr | median 29 mo (all 165) | Prior radiotherapy was independently associated with recurrence in the full mixed-procedure cohort (p = 0.015) |
| Katiyar 2021 RCT[2] | 12 (ventral arm) | Ventral BMG | 92% (11/12) | 6 mo | Comparable to dorsal; easier meatus preservation, less bleeding, wider field |
Functional improvements were consistent across series. Qmax rose from 7.7 to 25.9 mL/s in Berdondini, and in Mukhtar median Qmax rose from 7 to 18 mL/s while median PVR fell from 100 to 15 mL.[1][7] The EAU 2026 update pooled 247 ventral oral mucosal graft repairs, including 177 onlay and 70 inlay procedures.[19] Across this mixed cohort, 90.7% (range 86–98%) were stricture-free at 6 to 38.1 months and eight women (3.2%) developed new-onset SUI.[19]
Meta-Analytic Evidence — Ventral vs Dorsal
Comparative reports show no consistent difference in patency between dorsal and ventral onlay. The Savun report is a retrospective cohort.
- Li 2026. 5 studies, n = 319: no significant difference in success (RR 1.00; 95% CI 0.91–1.10; p = 0.95), or in Qmax, PVR, or AUA score at six months.[6]
- Ortac 2025. Across 25 eligible oral-graft studies, pooled success was 92.1% in 16 dorsal studies and 95.5% in 13 ventral studies; the ventral estimate includes inlay and onlay repairs.[16] The four comparative cohorts, which included ventral-inlay and ventral-onlay repairs, showed no significant difference in success (62/69 dorsal versus 93/103 ventral; OR 0.84; 95% CI 0.30–2.36; p = 0.74).[16] SUI occurred in 4 ventral and 2 dorsal cases. Most studies (21 of 25) were level 4 evidence.[16]
- Savun 2026. This three-center cohort (n = 65), which the authors describe as the largest individual comparative cohort, reported patency of 92.1% dorsal versus 92.6% ventral at final follow-up (p = 1.0), defined as passage of a 16-Fr cystoscope or Qmax >15 mL/s. There was no statistically significant difference in FSFI, PGIC or de novo incontinence. Ventral onlay had less blood loss (10 versus 20 mL, p = 0.001).[3]
Advantages
- Easier meatus preservation in selected strictures. A small randomized trial found meatus preservation easier with ventral onlay, but ventral repairs extending to the meatus can require distal graft or neomeatus reconstruction.[2][20]
- Wider operative field.[2]
- Less intraoperative bleeding. 10 versus 20 mL, Savun.[3]
- Buccal graft option. Ventral BMG onlay avoids vaginal graft harvest but still requires a vaginal incision; dorsal onlay can also use BMG.[1][19][5] Gaur compared ventral inlay BMG with dorsal onlay BMG.[1][19][5]
- Sphincter-plane rationale. Ventral repair avoids dorsal sphincter dissection, but a lower de novo SUI risk than dorsal onlay has not been demonstrated.[1][3]
- Teaching resources. A step-by-step video is available for female pelvic reconstructive surgeons.[12]
Limitations
- Distal strictures requiring meatal reconstruction. In one randomized 24-patient trial, the authors found the dorsal approach technically better for this pattern.[2] Ventral graft extension to the meatus is also described in the technique above.[21]
- Urinary spraying. In Higuchi 2026, spraying occurred only after vaginal flap urethroplasty (2 of 7), not after BMG.[10]
- Graft support depends on the periurethral fascial flaps. The Martius-reinforced variant has been used when this bed is compromised.[1][17]
- Vaginal wound and tissue-quality considerations apply to ventral onlay access even when the graft is buccal.
Complications
-
Urethrovaginal fistula. Sparse ventral muscle and overlapping urethral and vaginal suture lines are potential mechanisms. Waterloos and Verla advise a low threshold for Martius interposition when ventral tissues are poor.[21]
-
De novo SUI. Individual ventral onlay BMG series report rates of 0% to 4.5%.[1][7] The EAU reported eight cases among 247 ventral oral-graft repairs (3.2%), a pool that includes 70 inlay procedures.[19] In Mukhtar’s onlay series, one of 22 women developed mild SUI that resolved with conservative management by six months.[1][7][16][19]
-
Stricture recurrence. Berdondini observed recurrence in 1/42 women (2.4%) at mean 38.1 months.[1] Waterloos estimated 86% two-year stricture-free survival among 115 ventral onlay graft recipients; median follow-up was 29 months across the full 165-woman cohort.[1][9]
-
Dyspareunia. It occurred in 1 of 8 women (12.5%) in one small series.[15]
-
Spraying. It was reported after VFU and not after BMG.[10]
-
Oral donor-site morbidity. Counsel about pain, numbness, difficulty chewing, and mouth tightness after buccal graft harvest; some symptoms may persist beyond six months. The EAU recommends counseling about potential oral-graft complications .[22]
Prognostic Factor
In the Waterloos / Lumen EAU multicenter study (n = 165; median follow-up 29 months), prior radiotherapy was an independent predictor of stricture recurrence after female urethroplasty (p = 0.015). Two-year stricture-free survival was 73%, 86% and 80% after ventral onlay flap, ventral onlay graft and dorsal onlay graft, without a significant difference between groups.[9]
Summary
Waterloos et al. reported 86% two-year stricture-free survival after ventral onlay graft, whereas Berdondini et al. reported 41/42 (98%) stricture-free at mean 38.1 months; comparative studies show no consistent patency difference from dorsal onlay.[9][1][3][6] Reported practical advantages are meatus preservation, less bleeding, avoidance of vaginal graft harvest (with BMG) and preservation of the dorsal sphincter mechanism. Berdondini 2024 is a single-surgeon series (n = 42; 98% stricture-free at mean 38.1 months; Qmax 7.7 to 25.9 mL/s).[1] The Mandal 2025 RCT (covered on the Ventral Inlay BMG page) reported one failure per arm among 40 analyzed participants at one year.[23] Prior radiotherapy was associated with recurrence in one multicenter cohort.[1][3][6][9]
Videos
References
1. Berdondini E, Eissa A, Margara A, et al. Ventral onlay buccal mucosa graft urethroplasty for female urethral stricture: medium-term results in a single surgeon experience. Urology. 2024;193:194-200. doi:10.1016/j.urology.2024.06.045.
2. Katiyar VK, Sood R, Sharma U, et al. Critical analysis of outcome between ventral and dorsal onlay urethroplasty in female urethral stricture. Urology. 2021;157:79-84. doi:10.1016/j.urology.2021.05.021.
3. Savun M, Cubuk A, Colakoglu Y, Aksakal YN, Simsek A. Comparative analysis of dorsal and ventral onlay urethroplasty with buccal mucosal graft in female urethral strictures: a multi-center study. Int Urogynecol J. 2026;37(2):511-516. doi:10.1007/s00192-025-06479-2.
4. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
5. Gaur AS, Tarigopula V, Mandal S, et al. Comparison of ventral inlay and dorsal onlay urethroplasty for female urethral stricture. Urology. 2024;193:46-50. doi:10.1016/j.urology.2024.06.046.
6. Li X, Zhao X, Li Z, et al. Dorsal versus ventral onlay buccal mucosal graft urethroplasty in female urethral stricture: a meta-analysis. Int Urogynecol J. 2026;37(8):2303-2311. doi:10.1007/s00192-026-06516-8.
7. Mukhtar BMB, Spilotros M, Malde S, Greenwell TJ. Ventral-onlay buccal mucosa graft substitution urethroplasty for urethral stricture in women. BJU Int. 2017;120(5):710-716. doi:10.1111/bju.13970.
8. Romero-Maroto J, Verdú-Verdú L, Gómez-Pérez L, et al. Lateral-based anterior vaginal wall flap in the treatment of female urethral stricture: efficacy and safety. Eur Urol. 2018;73(1):123-128. doi:10.1016/j.eururo.2016.09.029.
9. Waterloos M, Lumen N, Ockrim JL, et al. Diagnostics, reconstructive approaches, and outcomes in female urethroplasty patients. BJU Int. 2025;135(6):1025-1030. doi:10.1111/bju.16701.
10. Higuchi M, Horiguchi A, Ashiya M, et al. Vaginal flap urethroplasty and dorsal onlay buccal mucosal graft urethroplasty for female urethral stricture: a single-center experience. Int J Urol. 2026;33(5):e70477. doi:10.1111/iju.70477.
11. Kumar L, Thakur A, Agarwal S, et al. Buccal versus vaginal graft urethroplasty in female urethral stricture: a systematic review and meta-analysis. Int Urogynecol J. 2025;36(11):2121-2132. doi:10.1007/s00192-025-06171-5.
12. Petrikovets A, Sun HH, Kiechle J, et al. Ventral-onlay buccal mucosal graft urethroplasty for the treatment of female urethral stricture: a step-by-step video for female pelvic reconstructive surgeons. Int Urogynecol J. 2019;30(12):2191-2193. doi:10.1007/s00192-019-03987-w.
13. Ozlulerden Y, Celen S, Zumrutbas AE, Aybek Z. Female buccal mucosa graft urethroplasty: a new modified ventral onlay "AZ" technique. Int Urogynecol J. 2020;31(12):2543-2550. doi:10.1007/s00192-020-04354-w.
14. Hajebrahimi S, Maroufi H, Mostafaei H, Salehi-Pourmehr H. Reconstruction of the urethra with an anterior vaginal mucosal flap in female urethral stricture. Int Urogynecol J. 2019;30(12):2055-2060. doi:10.1007/s00192-019-03910-3.
15. Coguplugil AE, Ebiloglu T, Sarikaya S, et al. Ventral onlay buccal mucosa graft urethroplasty for female urethral stricture. Int J Urol. 2021;28(5):538-543. doi:10.1111/iju.14504.
16. Ortac M, Ozervarli MF, Ergul RB, et al. Comparing ventral and dorsal oral mucosal graft urethroplasty in female urethral stricture: a systematic review and meta-analysis. World J Urol. 2025;43(1):397. doi:10.1007/s00345-025-05773-4.
17. Önol FF, Antar B, Köse O, Erdem MR, Önol ŞY. Techniques and results of urethroplasty for female urethral strictures: our experience with 17 patients. Urology. 2011;77(6):1318-1324. doi:10.1016/j.urology.2011.01.017.
18. Malde S, Spilotros M, Wilson A, et al. The uses and outcomes of the Martius fat pad in female urology. World J Urol. 2017;35(3):473-478. doi:10.1007/s00345-016-1887-2.
19. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females (limited update 2026), section 7.3.2. Guideline.
20. Greenwell T. Female Ventral Onlay Substitution Urethroplasty with Oral Mucosal Graft. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:29-34. doi:10.1007/978-981-97-5196-9_4.
21. Waterloos M, Verla W. Female urethroplasty: a practical guide emphasizing diagnosis and surgical treatment of female urethral stricture disease. Biomed Res Int. 2019;2019:6715257. doi:10.1155/2019/6715257.
22. Lumen N, Campos Juanatey F, Dimitropoulos K, et al. EAU Guidelines on Urethral Strictures: Tissue Transfer. EAU Guidelines Office, Arnhem, the Netherlands; 2026. ISBN 978-94-92761-32-5. Guideline chapter.
23. Mandal S, Gaur AS, Singh K, et al. "Comparative Efficacy of Dorsal-Onlay and Ventral-1 Inlay Buccal Mucosal Graft Urethroplasty in Female Urethral Stricture: A Randomized Clinical Trial." Urology. 2025;200:52-58. doi:10.1016/j.urology.2025.01.064