Kulkarni One-Stage Panurethral Urethroplasty
Kulkarni's one-stage panurethral urethroplasty is a single-stage reconstruction for long-segment and panurethral anterior urethral strictures using one-sided urethral dissection, penile invagination through a perineal approach, and dorsal or dorsolateral oral mucosa graft (OMG) onlay. Sanjay Kulkarni and colleagues in India began treating panurethral strictures in 1998 and published the one-sided dissection refinement in 2009.[1][2] The technique reaches the entire urethra from meatus to bulb without a separate penile incision by delivering the penile shaft into the perineal wound. One-sided dissection is intended to preserve the contralateral neurovascular supply. A 2026 review by the originating group reports long-term success of 80–85% in large series.[15]
Indications
- Panurethral strictures involving both the penile and bulbar urethra, typically longer than 8–10 cm (mean 14 cm in Kulkarni's series; more than 8 cm in the multicenter series)[1][3]
- Complex anterior peno-bulbar strictures[4]
- Most common etiologies: lichen sclerosus (especially in South Asia) and iatrogenic causes (instrumentation, catheterization, prior failed repairs)[1][2]
- Primary and redo settings. Success was 86.5% for primary repair and 61.5% after a previously failed urethroplasty[1]
- Pediatric peno-bulbar non-hypospadias strictures (16 of 28 children in a retrospective series received the Kulkarni technique; the 12 with isolated bulbar strictures received Barbagli repair)[5]
Surgical Technique
One-sided urethral dissection combined with penile invagination allows the surgeon to open and graft the entire anterior urethra through a single perineal incision. The one-sided dissection is intended to preserve the contralateral blood supply and the dorsal nerve of the penis.[1][2][6]
The 2009 description of one-sided anterior dorsal oral-mucosa graft urethroplasty reported 24 men (12 bulbar strictures with a mean length of 4.2 cm and 12 panurethral strictures with a mean length of 10 cm; lichen sclerosus in 50% and prior treatment in 83%). The lateral vascular supply on one side, the central tendon of the perineum, the bulbospongiosus muscle and its perineal innervation were preserved. With failure defined as any postoperative instrumentation, including dilation, 22 of 24 (92%) were successful at a mean follow-up of 22 months (range 12–55).[16]
Step-by-Step
1. Positioning and incision
Obtain a preoperative urine culture and treat bacteriuria or infection before urethroplasty; administer intraoperative prophylactic antibiotics according to local resistance patterns.[17] Place the patient in lithotomy. Midline perineal incision to expose the bulbar urethra. (This is the standard access; the penoscrotal, distal-shaft, and circumcoronal-degloving alternatives are compared under Incisions and Access Options below.)
2. One-sided urethral mobilization
The urethra is mobilized from the corpora cavernosa on one side only (typically the left), preserving the contralateral lateral urethral blood supply and the central perineal tendon attachments. This is the distinction from the Barbagli dorsal onlay, which requires circumferential mobilization; the one-sided approach retains contralateral attachments and is intended to reduce vascular disruption.[1][7][2]
3. Penile invagination
The penile shaft is invaginated retrogradely through the perineal incision, delivering the penile urethra into the operative field. This maneuver brings the entire anterior urethra, from the external meatus to the bulbomembranous junction, into the perineal wound and removes the need for a separate penile or penoscrotal incision.[4][3][1]
4. Dorsal urethrotomy
After partial rotation, open the urethra in the dorsal midline through the strictured segment. If the stricture reaches the meatus, Kulkarni's described technique extends a dorsal meatotomy through the glans and anchors the distal oral graft to the meatal edge.[16]
5. Graft harvest and placement
One or two OMGs (buccal or lingual) are harvested and placed as a dorsal onlay on the opened urethral plate. During placement of the penile graft, Kulkarni's original technique applies continuous upward traction to the inverted penis to prevent chordee. The graft is spread-fixed and quilted to the corporal bed; its apices are sutured to the urethrotomy apices and one graft margin to the adjacent margin of the urethral plate. The urethra, with the intact bulbospongiosus, is then rotated back over the graft and its free margin fixed to the corpora cavernosa with interrupted 4-0 polyglactin sutures over a 16 Fr grooved silicone catheter.[16] Kulkarni's series placed two oral mucosa grafts dorsally (mean stricture length 14 cm).[1] Penile skin grafts have been described when oral mucosa is insufficient; Takekawa reported 80.0% success with oral mucosa and 95.8% with penile skin in a mixed, nonrandomized group of 39 at median 12 months.[4] In a 2025 randomized trial, 98 patients with long anterior strictures were assigned to penile skin or buccal mucosa grafts and 92 were analyzed; 12-month success was 41/44 (93.2%) versus 47/48 (97.9%), respectively (p = 0.346).[19] The trial excluded lichen sclerosus and unsalvageable urethral plates.[19] The EAU 2026 guideline gives a strong recommendation against genital skin in men with lichen sclerosus.[14]
6. Closure
The augmented urethra is closed over a urethral catheter. A suprapubic catheter may provide additional bladder drainage; it does not pass through the repaired urethra. The penis is reduced to its anatomic position and the perineal wound closed in layers. An indwelling catheter is commonly left for two to three weeks after urethroplasty; persistent significant extravasation warrants continued or renewed catheterization and repeat urethrography after one week. Before catheter removal, the EAU 2026 guideline strongly recommends validated urethrography to assess for extravasation.[17]
Incisions and Access Options
The standard perineal Kulkarni approach delivers the penis into a perineal wound and applies a one-sided dorsal oral-mucosa onlay without a penile skin incision.[1][13] The distal-shaft Mini-Kulkarni uses a penile skin incision.[11] Warner's penoscrotal inversion avoids a penile skin incision but degloves the ventral penile skin.[10] Warner discusses penile skin necrosis and scarring among complications of fasciocutaneous flap urethroplasty.[10] The same one-sided principle can be delivered through several incisions; the choice is driven chiefly by stricture location.
| Access | Route to the urethra | Best suited for |
|---|---|---|
| Circumcoronal degloving | Subcoronal incision ~0.5 cm below the corona; deglove along Buck's fascia | Isolated penile strictures; when penile delivery into a proximal wound is difficult |
| Perineal + penile invagination (standard Kulkarni) | Midline perineal incision; penis invaginated retrogradely into the wound | Panurethral or peno-bulbar strictures; the whole anterior urethra through one incision |
| Penoscrotal + penile inversion | Penoscrotal incision; penis inverted into the wound (supine) | Penile-urethral strictures; no penile incision; supine positioning |
| "Mini-Kulkarni" (distal-shaft, glans-sparing) | Longitudinal distal penile-shaft incision over the prepuce; distal urethra rotated laterally | Isolated fossa-navicularis / meatal strictures |
Circumcoronal degloving — the traditional penile approach
Classic access to the penile urethra is a circumferential subcoronal incision approximately 0.5 cm below the corona, degloving the penis along Buck's fascia.[13] It gives direct exposure and remains reasonable for isolated penile strictures or when delivering the penis into a proximal wound is difficult.
Penoscrotal inversion (Warner)
Warner and colleagues described a one-sided anterior dorsal oral-mucosa graft urethroplasty performed by inverting the penis into a penoscrotal wound. Like the perineal Kulkarni it requires no penile skin incision. The authors list a single-stage repair in the supine position rather than lithotomy as further advantages.[10] In the initial series of 5 patients (mean stricture 3 cm; etiologies instrumentation, lichen sclerosus and failed hypospadias; mean follow-up 6 months), 4 of 5 (80%) had a successful outcome, defined as no postoperative instrumentation.[10] Mathur described a midline penoscrotal incision to reach the anterior urethra for a repair that uses the tunica albuginea of the corpora cavernosa as the augmentation tissue (79 patients; good-or-fair outcomes in 75/79 [94.9%] at 4 months and 71/79 [89.9%] at 24 months).[12]
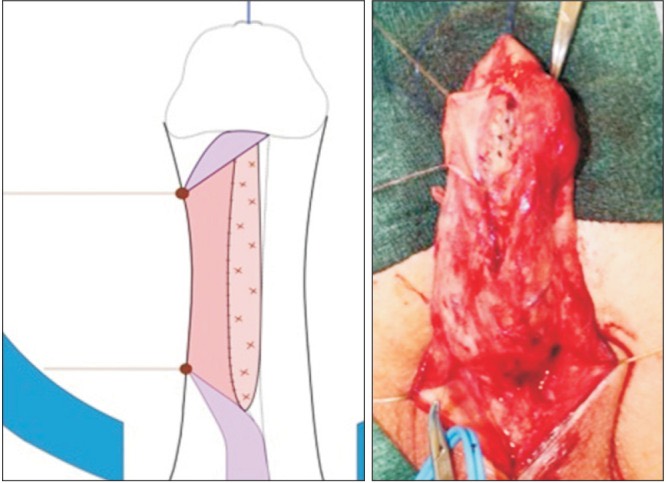
Penoscrotal inversion variant of the one-sided dorsal onlay. The penis is inverted into the penoscrotal wound, the urethra is mobilized off the corpora on one side only, and the oral mucosa graft is quilted down to the corpora before the opened urethral margins are sutured to it. From Warner JN, et al. Investig Clin Urol. 2016;57(2):135-140, Fig. 7 (CC BY-NC 4.0).[10]
The "Mini-Kulkarni" — distal / fossa-navicularis application
The "Mini-Kulkarni" applies the one-sided dissection and dorsal-onlay principle to isolated fossa-navicularis and meatal strictures without splitting the glans. Through a longitudinal incision in the distal third of the penile shaft over the prepuce, the distal urethra is rotated laterally and a dorsal buccal-mucosa graft is laid against the glanular bed. The contralateral blood and nerve supply is preserved.[11] In the initial report (6 patients), mean Qmax was 7.8 mL/s at baseline and 15.2 mL/s at 6 months among five patients with data at each time point (different patients were missing at baseline and follow-up); one recurrence and no fistula or glans dehiscence were reported. Urinary spray was reported in one patient in the abstract and table but in two of six in the results text.[11]
Evidence caveat. The Mini-Kulkarni is described in a 2025 preprint (n = 6, 6-month follow-up, not peer-reviewed in the cited version).[11] For better-validated distal techniques, see the dorsal-inlay and meatal approaches: Asopa dorsal inlay and meatotomy / meatoplasty.
Comparison with Barbagli Dorsal Onlay
Kartal et al. compared one-sided dorsolateral onlay (Kulkarni) versus standard circumferential dorsal onlay (Barbagli) retrospectively in 68 patients with strictures longer than 8 cm (31 Kulkarni, 37 Barbagli):[7]
| Parameter | Kulkarni One-Sided | Barbagli Dorsal Onlay |
|---|---|---|
| Operative time | 180 min | 196 min (p = 0.037) |
| Estimated blood loss | 164 mL | 202 mL (p = 0.033) |
| Hospital stay | 3.5 days | 4.4 days (p = 0.002) |
| Perioperative complications | 16.1% | 37.8% (p = 0.046) |
| Success rate (~5 yr) | 87.1% | 70.3% |
The anatomical rationale is preservation of contralateral attachments.
Outcomes
Case series report success of 83–90%, but populations, endpoints and follow-up differ:[1][7][8][4]
| Series | n | Stricture Length | Follow-up | Success |
|---|---|---|---|---|
| Kulkarni 2012[1] | 117 | Panurethral (mean 14 cm) | Median 59 mo | 83.7% overall; 86.5% primary, 61.5% redo |
| Spencer 2018[3] | 73 | Mean 13.6 cm | Mean 44 mo | 64/73 (88%) without recurrence; 4-institution retrospective review |
| Kartal 2020[7] | 31 | Mean 9.7 cm | Mean 59.8 mo | 27/31 (87.1%) |
| Zumrutbas 2020[8] | 35 | Mean 13.6 cm | Minimum 6 mo | 6 recurrences (29/35 without recurrence) |
| Takekawa 2025[4] | 39 | Median 4.4 cm; complex anterior | Median 12 mo (IQR 6–34) | 89.7% overall; oral and penile-skin grafts mixed |
Most recurrent strictures develop at the proximal graft margin (bulbar end).[1] The EAU 2026 guideline strongly recommends routine follow-up for at least one year after urethroplasty and weakly recommends a risk-adjusted protocol.[18] Its proposed standard-risk schedule includes penile and graft repairs, with uroflowmetry and patient-reported measures at 3, 12 and 24 months and at five years, and anatomic assessment at 3, 12 and 24 months and at five years when indicated; longer follow-up should be considered after penile and substitution repairs.[18] One small cohort found more recurrence above age 65 (5/14 versus 1/21).[8]
Functional and Patient-Reported Outcomes
- Voiding function. Mean Qmax was 25.4 mL/s at the first postoperative visit in one series.[8] Mean IPSS fell from 23 to 10 (p < 0.001) in the multicenter series.[3]
- Erectile function. Takekawa found no overall SHIM change. Spencer reported increased SHIM in 8/42 respondents and decreased SHIM in 6/42.[4][3]
- Ejaculatory function. MSHQ ejaculatory scores improved from 8 to 11 (p = 0.004).[3]
- Patient satisfaction. 88.6% of patients were satisfied and 94.3% would choose the procedure again.[8]
Complications
| Complication | Rate |
|---|---|
| Post-void dribbling | 45%[3] |
| Penile chordee | 18/73 (25%); a systematic review reports resolution by one year in 13/18 affected men and dorsal plication in 2/18.[3][20] |
| Donor-site complications | 2 of 39 patients, both grade 2[4] |
| Stricture recurrence | Varies with primary versus redo repair and follow-up; managed with dilation, DVIU, meatoplasty, or re-urethroplasty[8][1] |
Guideline Context
The AUA 2023 Urethral Stricture Guideline Amendment states that surgeons may reconstruct long multi-segment strictures with one-stage or multi-stage techniques using oral mucosal grafts, penile fasciocutaneous flaps, or a combination . Oral mucosa is the first-choice graft material , and buccal and lingual mucosal grafts are equivalent alternatives .[9] The AUA 2023 guideline discussion describes complex reconstruction of panurethral strictures as best performed at established high-volume reconstructive centers.[9]
Relative Contraindications and Limitations
- LS and local tissue quality. The EAU 2026 guideline recommends oral mucosa for LS and gives a weak recommendation for single-stage oral mucosa graft urethroplasty in the absence of adverse local conditions. When the urethral plate or surrounding tissues cannot support augmentation, staged repair may be needed; the EAU guideline strongly recommends counseling men with penile strictures that a planned single-stage procedure may be converted to staged repair if intraoperative findings are adverse.[14]
- Prior failed urethroplasty. Success was 61.5% versus 86.5% for primary repair.[1]
- Age and health. Fitness, tissue quality and patient priorities are assessed individually.[8]
- Medical comorbidities that preclude extended operative time. Perineal urethrostomy is a long-term alternative to urethroplasty (AUA conditional recommendation; expert opinion in high-risk populations).[9]
See Also
- Johanson Two-Stage Urethroplasty, for panurethral LS when urethral plate is obliterated
- Dorsal Onlay BMG (Barbagli), the circumferential dissection comparator
- Muscle-Sparing Urethroplasty, broader context for one-sided techniques
- History of Urethral Surgery, the one-sided anterior urethroplasty in historical context
Videos
References
1. Kulkarni SB, Joshi PM, Venkatesan K. Management of Panurethral Stricture Disease in India. J Urol. 2012;188(3):824–30. doi:10.1016/j.juro.2012.05.020
2. Kulkarni S, Kulkarni J, Surana S, Joshi PM. Management of Panurethral Stricture. Urol Clin North Am. 2017;44(1):67–75. doi:10.1016/j.ucl.2016.08.011
3. Spencer J, Blakely S, Daugherty M, et al. Clinical and Patient-Reported Outcomes of 1-Sided Anterior Urethroplasty for Long-Segment or Panurethral Strictures. Urology. 2018;111:208–213. doi:10.1016/j.urology.2017.08.029
4. Takekawa K, Horiguchi A, Shinchi M, et al. One-Sided Dorsal Onlay Urethroplasty With Penile Invagination (Kulkarni Urethroplasty) for Complex Anterior Urethral Strictures: A Single-Center Experience. Int J Urol. 2025;32(6):749–755. doi:10.1111/iju.70048
5. Patil N, Javali T. Paediatric Buccal Mucosal Graft Urethroplasty for Non-Hypospadias Urethral Strictures: A Single Centre Experience With Long Term Outcomes. Urology. 2021;158:174–179. doi:10.1016/j.urology.2021.06.029
6. Horiguchi A. Substitution Urethroplasty Using Oral Mucosa Graft for Male Anterior Urethral Stricture Disease: Current Topics and Reviews. Int J Urol. 2017;24(7):493–503. doi:10.1111/iju.13356
7. Kartal I, Çimen S, Kokurcan A, et al. Comparison Between Dorsal Onlay and One-Sided Dorsolateral Onlay Buccal Mucosal Graft Urethroplasty in Long Anterior Urethral Strictures. Int J Urol. 2020;27(9):719–724. doi:10.1111/iju.14286
8. Zumrutbas AE, Ozlulerden Y, Celen S, Kucuker K, Aybek Z. The Outcomes of Kulkarni's One-Stage Oral Mucosa Graft Urethroplasty in Patients With Panurethral Stricture: A Single Centre Experience. World J Urol. 2020;38(1):175–181. doi:10.1007/s00345-019-02758-y
9. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral Stricture Disease Guideline Amendment (2023). J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
10. Warner JN, Tracey JM, Zhumkhawala AA, Chan KG, Lau CS. Penile Inversion Through a Penoscrotal Incision for the Treatment of Penile Urethral Strictures. Investig Clin Urol. 2016;57(2):135–140. doi:10.4111/icu.2016.57.2.135
11. Oliveira DEG, Geminiani JJ, Alvim RG, Reis AB. The "Mini-Kulkarni": A Promising New Technique for the Treatment of Strictures of the Fossa Navicularis and Urethral Meatus. Research Square [Preprint]. 2025. doi:10.21203/rs.3.rs-6805479/v1
12. Mathur RK, Himanshu A, Sudarshan O. Technique of Anterior Urethra Urethroplasty Using Tunica Albuginea of Corpora Cavernosa. Int J Urol. 2007;14(3):209–213. doi:10.1111/j.1442-2042.2007.01683.x
13. Verla W, Oosterlinck W, Spinoit AF, Waterloos M. A Comprehensive Review Emphasizing Anatomy, Etiology, Diagnosis, and Treatment of Male Urethral Stricture Disease. Biomed Res Int. 2019;2019:9046430. doi:10.1155/2019/9046430
14. EAU Guidelines on Urethral Strictures, 2026: disease management in males. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males. Accessed September 12, 2026.
15. Kulkarni SB, Ratanapornsompong W, Thakkar S, et al. Twenty-five Years of Panurethral Stricture Repair Using the Kulkarni Technique. Eur Urol Focus. 2026;12(3):329-332. doi:10.1016/j.euf.2026.04.007
16. Kulkarni S, Barbagli G, Sansalone S, Lazzeri M. One-sided anterior urethroplasty: a new dorsal onlay graft technique. BJU Int. 2009;104(8):1150–1155. doi:10.1111/j.1464-410X.2009.08590.x
17. European Association of Urology. "EAU Guidelines on Urethral Strictures: Perioperative Care of Urethral Surgery." 2026. https://uroweb.org/guidelines/urethral-strictures/chapter/perioperative-care-of-urethral-surgery
18. European Association of Urology. "EAU Guidelines on Urethral Strictures: Follow Up." 2026. https://uroweb.org/guidelines/urethral-strictures/chapter/followup
19. Alrefaey A, Anwar MA, Abdelmagid ME, et al. "Comparative outcomes of penile skin grafts versus buccal mucosal grafts in urethroplasty for the treatment of extensive anterior urethral strictures." Sci Rep. 2025;15(1):29508. doi:10.1038/s41598-025-14191-w
20. Calleja Hermosa P, Campos-Juanatey F, Varea Malo R, Correas Gómez MÁ, Gutiérrez Baños JL; Trauma and Reconstructive Urology Working Party of the European Association of Urology Young Academic Urologists. "Sexual function after anterior urethroplasty: a systematic review." Transl Androl Urol. 2021;10(6):2554-2573. doi:10.21037/tau-20-1307