Lateral-Based Anterior Vaginal Wall Flap (Romero-Maroto / Simonato)
The lateral-based anterior vaginal wall flap urethroplasty is a modification of the classic Blandy U-flap developed specifically to address the retrusive-meatus and inward-stream problem of the proximal-pedicled design. The lateral-based variant was described independently by Romero-Maroto 2018 and Simonato 2010, and both were inspired by the male Orandi technique (1968). The EAU 2026 update classifies these repairs as lateral C flaps.[1][2][3][16]
For the broader female-stricture treatment ladder, see Female DVIU and Urethral Dilation, Distal Urethrectomy with Advancement Meatoplasty, Female Dorsal Onlay BMG, and Ventral Onlay BMG.
Rationale — Why a Lateral Pedicle
The Blandy technique produced a retrusive meatus and an inward urinary stream in the Romero-Maroto patients, and the proximal pedicle is the presumed cause.[1] A lateral pedicle has the following aims:
- It preserves the vascular axis of the anterior vaginal wall along the lateral pedicle.[2]
- It keeps the meatus orthotopic, with normal anterior stream direction.[1]
- Spraying remains unquantified for the lateral-based flap: Romero-Maroto assessed stream direction, while Higuchi reported spraying in 2/7 women with an unspecified vaginal-flap subtype.[1][8]
Indications
- FUS refractory to dilation or DVIU is one indication for reconstruction.[1][4] AUA 2023 statement 26 permits vaginal-flap reconstruction; its discussion advises offering urethroplasty for FUS given low endoscopic efficacy.[7] EAU 2026 recommends initial dilation and urethroplasty at second recurrence if ISD is unsuitable or definitive repair is desired .[7][16]
- Distal, mid, or pan-urethral strictures. Romero-Maroto treated three pan-urethral strictures among nine women; Simonato treated five mid-to-distal strictures and one with proximal extension.[1][2]
- Healthy, well-estrogenized anterior vaginal wall (no LS, no severe atrophy).[4][5]
Contraindications
- LS or vaginal atrophy compromising flap quality.[4][5]
- Prior radiation involving the proposed flap tissue may limit its suitability if the vaginal mucosa is unhealthy or lacks pliability; assess local tissue quality.[5]
- Prior sling-related periurethral scarring may limit local flap mobilization. In Önol's series, two women with prior synthetic midurethral slings received Martius-reinforced ventral BMG instead.[6]
Romero-Maroto Technique (Eur Urol 2018)
Dorsal lithotomy, regional or general anesthesia.[1]
- Map the stricture and secure access. Use VCUG to define site and length; cystourethroscopy can confirm the stricture when urethral caliber exceeds 14 Fr. Before the vaginal incision, pass an 8-Fr Foley catheter or, if it will not pass, a guidewire.[1][17]
- Vaginal exposure and ventral urethrotomy. Make a midline anterior vaginal wall incision and mobilize the wall on the chosen side while preserving vascularity. Then incise the urethra at 6 o'clock from the meatus until the proximal stricture is fully open. When the meatus is not strictured, carry the flap only to the distal stricture limit.[1]
- Lateral flap design. Rectangular or trapezoidal anterior-vaginal-wall flap outlined lateral to the urethra, with the vascular pedicle based laterally (Orandi analog).
- Flap elevation. Select a rectangular segment of anterior vaginal wall matched to stricture length and caliber. Mobilize the outer border while preserving a wide axial vascular pedicle. Waterloos and Verla describe deep medial periurethral and superficial lateral submucosal dissection, sufficient pedicle mobilization, and careful bipolar hemostasis to preserve vascularity; Romero-Maroto's inset does not require tunneling or flap rotation.[1][17] 5.[2] Flap inlay. Suture the inner vaginal-flap edge to the ipsilateral urethrotomy margin with interrupted 3-0 polyglactin. Turn the outer edge around and suture it to the contralateral margin without rotating or tunneling the flap.[1]
- Donor-site closure. Primary; the lateral pedicle keeps the meatus in its orthotopic position without posterior retraction.
- Catheter. Postoperative urethral catheter.
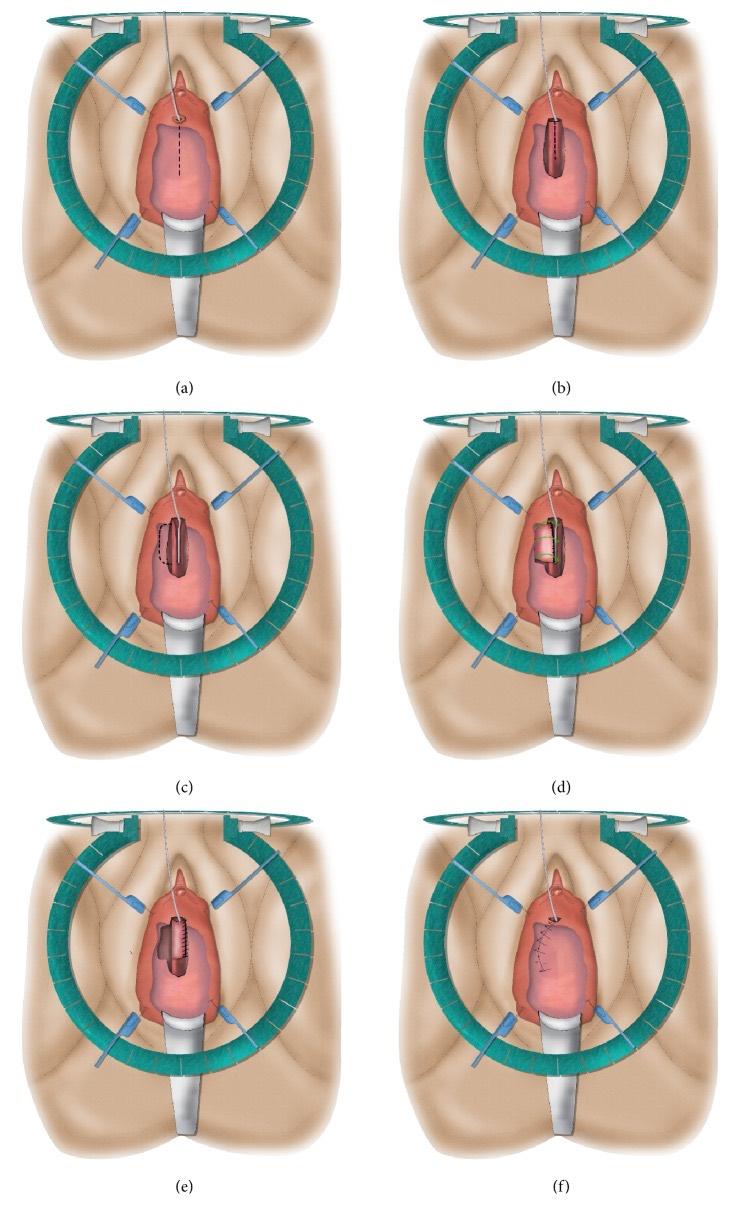
Lateral vaginal wall flap ("Orandi flap") urethroplasty: (a) longitudinal midline incision of the anterior vaginal wall; (b) ventral stricturotomy; (c) mobilization of the lateral vaginal wall flap; (d) suturing the medial surface of the flap to the ipsilateral side of the urethra; (e) turning the mucosal surface of the flap toward the urethral lumen and suturing its lateral side to the contralateral side of the urethra; (f) completed closure. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 7 (CC BY 4.0).[17]
Simonato Technique (J Urol 2010) — De-Epithelialization Refinement
Simonato also used a lateral vascular pedicle, but inverted the flap apex onto itself and partially de-epithelialized the suture-bearing area; Romero-Maroto inset the flap without this inversion.[1][2]
- Partial de-epithelialization of the flap edges where sutures are placed. The exposed submucosal connective tissue promotes scar (cicatrix) formation at the suture line, which Simonato designed to avoid fistula formation.
- Allows reconstruction of long segments including pan-urethral strictures.
Lateral-Based Flap vs Classic Blandy U-Flap
| Feature | Classic Blandy U-Flap | Lateral-Based Flap (Romero-Maroto / Simonato) |
|---|---|---|
| Pedicle orientation | Proximal | Lateral |
| Vascular axis | Proximal pedicle | Preserved along lateral pedicle |
| Meatal position | Risk of retrusive | Orthotopic |
| Urinary stream | Inward / posterior reported | Normal anterior preserved |
| Fistula-related design | Standard suture line | Simonato de-epithelialized the flap near the sutures to favor cicatrix formation; prevention was not compared[2] |
| Stricture length | Distal / mid | Distal / mid / pan-urethral |
| Urinary spraying | No classic U-flap estimate from the cited studies; Higuchi did not specify VFU subtype[8] | No distinct spraying endpoint in Romero-Maroto; not reported in Simonato's abstract[1][2] |
Outcomes
Romero-Maroto 2018 — Eur Urol[1]
- Nine women underwent repair; eight returned for a later medical review, and one died after an earlier review. The cross-sectional study included chart review. Mean age was 56 years (range 41–78), and mean reported follow-up was 80.7 months (range 12–198).[1]
- 100% symptom relief; urethral caliber rose from 10.8 to ≥ 20 Fr; Qmax rose from 6.8 to 21 mL/s (3-fold).[1]
- No recurrence, de novo SUI, or fistula was reported in nine women; all neomeatuses remained orthotopic without a reported change in stream direction. Spraying was not measured separately.[1]
Simonato 2010 — J Urol[2]
- n = 6 with extensive strictures (5 involving the middle and distal urethra, 1 also involving the proximal urethra with bilateral hydronephrosis).[2]
- Mean follow-up 70.8 mo.
- Normal micturition in all after catheter removal; 5/6 (83%) required no further treatment; 1/6 (17%) required CIC for significant residual urine.[2]
Comparative context
| Series | Technique | n | Success | Mean follow-up | De-novo SUI | Spraying |
|---|---|---|---|---|---|---|
| Romero-Maroto 2018[1] | Lateral-based flap | 9 | No recurrence reported | 80.7 mo | 0/9 | Not separately reported |
| Simonato 2010[2] | Lateral-pedicle + de-epithelialization | 6 | 5/6 (83%) needed no further treatment; 6/6 voided normally after catheter removal | 70.8 mo | — | — |
| Hajebrahimi 2019[9] | Tubularized anterior vaginal U-flap with dorsal urethrotomy | 14 | 14/14 voiding LUTS improved or cured | — | 14% (2/14) postoperative SUI; new onset not specified | not reported |
| Higuchi 2026[8] | VFU | 7 | 4/7 (57.1%) cystoscopic absence of re-stricture without secondary intervention | 12 mo (median, whole 15-patient series; VFU-only follow-up not reported) | 1 in whole series (group not stated) | 29% (2/7) |
| Kowalik 2014[10] | VFU vs dorsal BMG | 10 | 2 VFU recurrences; none after BMG | — | not reported | not reported |
| Önol 2011[6] | Anterior vaginal wall inlay (10 of 17) and other techniques | 17 | 100% objective (all 17) | 24 mo (median) | not reported | not reported |
Advantages
- Orthotopic meatus. This is the main reported gain over the Blandy flap.[1]
- Preserved vascular axis along the lateral pedicle.[2]
- Versatility. Simonato extended the technique to long or pan-urethral disease.[2]
- Stream direction. Romero-Maroto reported an orthotopic meatus and unchanged stream direction in nine women; spraying was not assessed separately.[1] 5.[2] De-epithelialization (Simonato). The author partially de-epithelialized the flap at the suture line to encourage cicatrix formation and avoid fistula.[2]
- No oral donor-site morbidity. The vaginal donor site still has wound and scarring risks.[4]
Limitations and Caveats
- Small evidence base. The two primary series total 15 patients (Level 4). The EAU 2026 update lists 47 women treated with a lateral C flap across two studies, and its pooled vaginal flap data (161 women) show 81.4% patency (range 67–100%) and new-onset urinary incontinence in 9.3%.[1][2][16]
- Tissue-quality dependence. Like all VFU techniques, requires healthy vaginal tissue.[4][5]
- Vaginal graft versus flap distinction. Kumar 2025 SR / meta of 18 studies found no significant difference in success between BMG (86.2%) and vaginal-wall graft (89.8%), Qmax, or PVR.[11] Separately, Kowalik 2014 (10 women) reported two recurrences after VFU and none after dorsal BMG, and Higuchi 2026 reported 87.5% (DOBMGU) versus 57.1% (VFU).[10][8] In a 2025 multicenter cohort of 165 women, 2-year stricture-free survival was 73% after ventral onlay flap (17 women), 86% after ventral onlay graft (115), and 80% after dorsal onlay graft (33), without a significant between-group difference; median follow-up was 29 months.[19] Flap subtype was not specified, and prior radiotherapy predicted recurrence in the full cohort.[19]
- Residual urine. One of 6 women in Simonato's series required CIC for significant residual urine.[2]
Martius Adjunct
The Martius labial fat-pad flap can interpose vascularized tissue between the urethral repair and the vaginal closure, particularly when tissue quality is suspect or fistula risk is elevated.[12][13][14]
- Malde 2017 reviewed Martius use in female urology (12 women in the urethroplasty subset).[12]
- Blaivas-Heritz 1996 used Martius in 47 of 49 women with urethral or vesical neck damage, with a pubovaginal sling in 41. Continence was achieved in 87% at 1 to 11 years.[13]
- Flisser-Blaivas 2003 reported 93% anatomic success by a single vaginal flap procedure in 72 women (56 with a concomitant pubovaginal sling), median follow-up 1.5 years.[14]
- Önol 2011 used Martius-reinforced ventral BMG specifically when prior synthetic midurethral sling created periurethral scarring.[6]
When to Choose This Technique
| Scenario | Reconstructive option | Rationale |
|---|---|---|
| Distal / mid stricture, healthy vaginal tissue | Lateral-based flap | Orthotopic meatus and no oral donor site; mean follow-up 6–7 yr in two small series[1][2] |
| Pan-urethral / long-segment | Lateral-based flap or dorsal BMG | Romero-Maroto treated three panurethral strictures with a lateral-based flap; Simonato treated one stricture with proximal extension, and Higuchi treated three panurethral strictures with dorsal BMG.[1][2][8] |
| LS / atrophy | Dorsal onlay BMG | Vaginal tissue unsuitable[4][5] |
| Prior MUS with periurethral scarring | Martius-reinforced ventral BMG | Scarring limits flap mobilization[6] |
| Concern for meatal retraction | Lateral-based flap | Orthotopic meatus in 9/9 Romero-Maroto patients; spraying was not measured separately[1] |
The AUA 2023 amendment states that surgeons may reconstruct female strictures with oral mucosal grafts, vaginal flaps or a combination . It cites success of 69–95% across techniques and selection by surgeon experience.[7]
Postoperative Management
- Catheter and leak check. Romero-Maroto kept a urethral catheter for 3 weeks (4 weeks in one patient), and Simonato reported normal voiding after catheter removal. Waterloos and Verla describe urethrography before removal, with removal when no contrast extravasation is seen.[1][2][17]
- Voiding trial with uroflowmetry and PVR.
- Cystoscopy at 3–6 months.
- Preoperative vaginal-tissue preparation (Romero-Maroto series). Two postmenopausal women received intravaginal estrogen for 3 months before surgery; flap selection depends on tissue quality.[1][5]
- Long-term surveillance — late recurrences ≥ 5 yr have been reported with VFU generally.[15]
Summary
The lateral-based anterior vaginal wall flap is a modification of the Blandy U-flap intended to avoid the retrusive meatus and inward stream of the classic design. Romero-Maroto reported symptom relief in all nine women at a mean of 6.7 yr, while Simonato reported that five of six women required no further treatment at a mean of 5.9 yr (with partial flap de-epithelialization).[1][2] The two original series included 15 women. A 2026 three-center retrospective series reported composite functional success in 23/24 women, with follow-up reported as 9.5 years (range 2–21.8); 4/24 had Clavien-Dindo grade I complications, with no long-term complications or de novo incontinence reported.[18] Its patients may overlap the Romero-Maroto cohort.[18] The technique is an option for women with healthy vaginal tissue who want single-stage repair without an oral-mucosa donor site.[1][2]
References
1. Romero-Maroto J, Verdú-Verdú L, Gómez-Pérez L, et al. Lateral-based anterior vaginal wall flap in the treatment of female urethral stricture: efficacy and safety. Eur Urol. 2018;73(1):123-128. doi:10.1016/j.eururo.2016.09.029.
2. Simonato A, Varca V, Esposito M, Carmignani G. Vaginal flap urethroplasty for wide female stricture disease. J Urol. 2010;184(4):1381-1385. doi:10.1016/j.juro.2010.06.042.
3. Orandi A. One-stage urethroplasty. Br J Urol. 1968;40(6):717-719. doi:10.1111/j.1464-410x.1968.tb11872.x. PMID: 4883846.
4. Bouchard B, Campeau L. Surgery for female urethral stricture. Neurourol Urodyn. 2025;44(1):51-62. doi:10.1002/nau.25358.
5. West C, Lawrence A. Female urethroplasty: contemporary thinking. World J Urol. 2019;37(4):619-629. doi:10.1007/s00345-018-2564-4.
6. Önol FF, Antar B, Köse O, Erdem MR, Önol ŞY. Techniques and results of urethroplasty for female urethral strictures: our experience with 17 patients. Urology. 2011;77(6):1318-1324. doi:10.1016/j.urology.2011.01.017.
7. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
8. Higuchi M, Horiguchi A, Ashiya M, et al. Vaginal flap urethroplasty and dorsal onlay buccal mucosal graft urethroplasty for female urethral stricture: a single-center experience. Int J Urol. 2026;33(5):e70477. doi:10.1111/iju.70477.
9. Hajebrahimi S, Maroufi H, Mostafaei H, Salehi-Pourmehr H. Reconstruction of the urethra with an anterior vaginal mucosal flap in female urethral stricture. Int Urogynecol J. 2019;30(12):2055-2060. doi:10.1007/s00192-019-03910-3.
10. Kowalik C, Stoffel JT, Zinman L, Vanni AJ, Buckley JC. Intermediate outcomes after female urethral reconstruction: graft vs flap. Urology. 2014;83(5):1181-1185. doi:10.1016/j.urology.2013.12.052.
11. Kumar L, Thakur A, Agarwal S, et al. Buccal versus vaginal graft urethroplasty in female urethral stricture: a systematic review and meta-analysis. Int Urogynecol J. 2025;36(11):2121-2132. doi:10.1007/s00192-025-06171-5.
12. Malde S, Spilotros M, Wilson A, et al. The uses and outcomes of the Martius fat pad in female urology. World J Urol. 2017;35(3):473-478. doi:10.1007/s00345-016-1887-2.
13. Blaivas JG, Heritz DM. Vaginal flap reconstruction of the urethra and vesical neck in women: a report of 49 cases. J Urol. 1996;155(3):1014-1017. doi:10.1016/s0022-5347(01)66372-9. PMID: 8583550.
14. Flisser AJ, Blaivas JG. Outcome of urethral reconstructive surgery in a series of 74 women. J Urol. 2003;169(6):2246-2249. doi:10.1097/01.ju.0000061763.88247.16.
15. Blaivas JG, Santos JA, Tsui JF, et al. Management of urethral stricture in women. J Urol. 2012;188(5):1778-1782. doi:10.1016/j.juro.2012.07.042.
16. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females (limited update 2026), section 7.3.2. Guideline.
17. Waterloos M, Verla W. Female urethroplasty: a practical guide emphasizing diagnosis and surgical treatment of female urethral stricture disease. Biomed Res Int. 2019;2019:6715257. doi:10.1155/2019/6715257.
18. Sarrio-Sanz P, Gómez-Perez L, López López AI, et al. "Multicentric evaluation of a lateral-based anterior vaginal wall flap for female urethral stricture repair." Minerva Urol Nephrol. 2026 Mar 16. doi:10.23736/S2724-6051.25.06533-4
19. Waterloos M, Lumen N, Ockrim JL, et al. "Diagnostics, reconstructive approaches, and outcomes in female urethroplasty patients." BJU Int. 2025;135(6):1025-1030. doi:10.1111/bju.16701