Male Urethroplasty — Incisions & Approaches
Male urethroplasty begins with two decisions: how to incise the skin and how to reach the urethra. Outcomes for individual named techniques are on their own pages, cross-linked below.
Decision principles (graft selection, tension, spongiofibrosis) are in Principles of Urethral Reconstruction. The Master Decision Framework covers technique selection.
1. Perineal Skin Incisions
Three principal perineal skin incisions are described for bulbar and posterior urethroplasty:
| Incision | Description | Reported endpoint | Notes |
|---|---|---|---|
| Midline perineal vertical | Longitudinal incision in the perineal raphe | SSI 1.9% in bulbar and 3.1% in posterior repairs | Lin: matched retrospective urethroplasty cohort; lower infection rates than inverted-U in that cohort[1] |
| Inverted-U (curvilinear) | U-shaped incision curving around the perineum | SSI 18.6% in bulbar and 16.4% in posterior repairs | Lin: corresponding inverted-U groups; cadaveric incisions crossed more nerves and vessels[1] |
| Lambda perineal incision (LPI) | Inverted-Y / lambda shape extending laterally from midline | Minor wound complications 23.3% (vs 11.9% midline), not SSI alone | Bascom 2016 (n = 540 bulbar urethroplasties): independently associated with increased 90-day wound complications, primarily superficial wound-edge separation (10.7% vs 0%); six-month urethroplasty failure was 6.2% with lambda versus 0% with midline (P = .0003), with no identifiable urethroplasty-outcome advantage for lambda[2] |

Midline, inverted-U and lambda incisions illustrate different ways to obtain perineal exposure. Choice depends on exposure, prior scars, patient anatomy and reconstruction. (Original WARWIKI schematic; see the figure source record and review limits.)
A midline vertical incision provides bulbar access and permits a loop or 7-flap perineal urethrostomy when selected. EAU 2026 strongly recommends offering perineal urethrostomy to men with complex anterior stricture disease.[24] For PFUI-related posterior urethroplasty, EAU 2026 strongly recommends a midline perineal incision.[24] PU reconstruction remains individualized.[24]
For penile urethral strictures, the three penile-skin incisions are described in the next section.
2. Penile-Stricture Exposure — Three Approaches
For penile urethral strictures specifically, three exposure strategies dominate contemporary practice. In a retrospective 13-institution review of 222 non-hypospadiac penile strictures (median follow-up 49 months, overall success 80.2%), Abramowitz found no significant difference in outcomes by incision approach. Choice is driven by stricture characteristics and surgeon experience.[3]
2a. Degloving / circumcising incision
Subcoronal circumferential incision (identical to a circumcision incision); penile skin retracted proximally to "deglove" the shaft, exposing the entire penile urethra from glans to penoscrotal junction. The ACS trauma guideline names a circumcising incision, or a ventral midline penile incision, as the exposure for penile fracture repair.[4]
- Advantages: circumferential exposure permits simultaneous fasciocutaneous flap harvest for selected repairs (Quartey, Q-flap, McAninch circular) and may be used for staged repairs requiring wide penile exposure.
- Disadvantages: disrupts dartos blood supply circumferentially; risk of penile edema / skin necrosis (especially in redo cases); preputial preservation depends on the incision and reconstruction.
- Best for: isolated penile strictures, staged repair, cases requiring fasciocutaneous flap harvest when suitable non-hair-bearing penile skin is available and LS is absent[24][29], selected cases requiring wide penile exposure; LS alone does not require complete plate excision.
For short distal penile strictures, circumcising degloving has been combined with one-sided dorsal mobilization to the cavernosal midline, intraurethral methylene blue to identify diseased mucosa, and a dorsal meatotomy when the meatus is narrow, tubularizing the urethra over a 14-16 Fr catheter.[27]
2b. Kulkarni penile invagination (perineal-only)
Standard perineal midline incision with the penis invaginated (telescoped) into the perineal wound and no penile incision. One-sided urethral mobilization preserves the contralateral neurovascular bundle and central perineal tendon attachments. The graft is placed as a dorsolateral onlay.[3][5]
- Advantages: avoids a separate penile skin incision and permits long-segment oral-graft reconstruction with one-sided urethral mobilization. See the technique page for study-specific results.[3][5]
- Limitations: distal access can be difficult, and meatal or fossa-navicularis disease may require an additional distal maneuver. LS involving the meatus is not by itself a categorical exclusion; tissue quality determines the reconstruction.[24]
- Technical variation. Some surgeons mobilize the corpus spongiosum circumferentially rather than unilaterally during penile invagination, extending the dorsal urethrotomy approximately 1 cm beyond the distal disease and, when fossa navicularis or meatal disease is present, reversing the inversion to extend the incision through the glans urethral plate. For a residual caliber of 0-4 Fr, excision with a two-sided graft repair, or anastomotic repair only for a selected injury-associated penile stricture <1 cm (the EAU strongly recommends against penile anastomosis for strictures >1 cm because of chordee)[24], has been described; excising two separate segments risks the antegrade and retrograde urethral blood supply, so a staged approach is advised instead in complex cases.[28]
- Best for: long-segment and panurethral strictures (especially > 8 cm), peno-bulbar strictures, and cases where penile-skin preservation is a priority.
- Canonical technique page: Kulkarni One-Sided Dorsolateral BMG.
2c. Midline ventral penile incision
A direct longitudinal incision along the ventral raphe preserves lateral dartos pedicles and avoids circumferential degloving. It is used for modified Orandi dorsal-skin-flap repair, penile fracture repair, and penoscrotal-junction strictures.[3][4]
- Advantages: preserves lateral penile-skin vascularity; avoids circumcision; can be combined with perineal invagination for penoscrotal-junction strictures.
- Disadvantages: limited exposure for long penile strictures; visible ventral scar; the incision must accommodate any planned flap and preserve its dartos pedicle.
- Best for: focal / short penile strictures, modified Orandi dorsal-skin-flap repairs, penoscrotal-junction strictures, penile-fracture repair.
3. Anterior Urethrotomy Approaches
How the urethra itself is opened once exposed drives graft placement, blood-supply preservation, and operative time.
| Approach | Description | Implication |
|---|---|---|
| Ventral urethrotomy | Urethra opened on its ventral surface | Traditional approach; supports ventral onlay BMG and the Asopa dorsal inlay (dorsal wall incised through the ventral opening). Less urethral mobilization required[6][7] |
| Dorsal urethrotomy (Barbagli) | Urethra mobilized circumferentially and rotated 180° to expose the dorsal surface | More extensive dissection; supports dorsal onlay BMG (Barbagli)[6][8] |
| Dorsolateral (Kulkarni) | One-sided urethral dissection; contralateral blood supply preserved | Minimizes urethral devascularization; particularly useful for long penile strictures; the basis of the Kulkarni one-sided dorsolateral BMG technique[6] |
| Non-transecting | Corpus spongiosum is not fully transected, so antegrade blood flow is preserved | Cotter 2019 multi-institutional data: 2,098 anterior urethroplasties (10 surgeons, 2010-2017): bulbar excisional repairs performed without transection rose 430%. Includes Jordan vessel-sparing EPA, non-transecting bulbar, and the entire ANTA / MsANTA / MANTA / ntAAU family[9]. A 151-patient randomized trial of transecting EPA versus buccal-graft urethroplasty for bulbar strictures ≤2 cm reported perceived penile shortening in 26% versus 5.4% and reduced glans stiffness in 19% versus 6.8% at 12 months; recurrence requiring retreatment was 12.2% versus 13.0%.[30] |
4. Posterior Urethroplasty Approaches
For posterior urethral distraction defects (PFUI) and post-prostatectomy or post-radiation membranous-urethral or VUAS strictures:
| Approach | Used in | Indication |
|---|---|---|
| Perineal anastomotic | Usual reconstructive access for PFUI | Obtain healthy ends and a tension-free anastomosis; required maneuvers depend on fibrosis, displacement and urethral elasticity[10][11][24] |
| Elaborated perineal (Webster steps 1–4) | Webster step framework | Bulbar mobilization → corporal splitting → inferior pubectomy → supracrural rerouting. In one 142-patient multicenter series, inferior pubectomy was used in 10% and corporal splitting in 17%; anastomosis after scar excision and mobilization alone sufficed in 67%[11][12] |
| Supracrural rerouting (step 4) | Rare adjunct | Mobilized urethra routed around a crus when other maneuvers do not provide reach. Kizer reported recurrence in 3/4 rerouted cases.[11] |
| Transpubic (abdominoperineal) | Selected complex defects | Consider when adequate exposure or a tension-free repair cannot be obtained perineally, including selected fistulas or cavities. For post-traumatic posterior stenosis, EAU strongly recommends against total pubectomy during abdominoperineal reconstruction because partial pubectomy provides similar exposure with fewer complications.[24] See Abdominoperineal Urethroplasty[12][13][14][24] |
| Modified perineal (Quartey 1988) | Niche | Standard perineal-prostatectomy incision with division of the urogenital diaphragm in the midline; improved membranous-urethra exposure without pubectomy[15] |
| Robotic transabdominal | Contemporary alternative for VUAS / BNC | AUA 2023: surgeons may perform robotic or open reconstruction for recalcitrant bladder neck or VUAS stenosis [16]. In a heterogeneous single-center series of 105 men (57.1% previously irradiated), 41/105 required combined abdominoperineal access, 30/105 later received an artificial urinary sphincter for incontinence, and 26/105 required surgical reintervention at a mean 18.7 months of follow-up.[25] See Robotic Posterior Urethroplasty |
The EAU Urological Trauma guideline (2026) calls perineal anastomotic repair the technique of choice after PFUI. It reserves a combined abdominoperineal approach for rare cases with bladder-neck injury, recto-urethral fistula, multiple prior repairs or a long distance between the stumps.[26]
5. Graft / Tissue Placement Configurations
For substitution urethroplasty, the graft (most commonly buccal mucosa; the AUA guideline names oral mucosa as the first choice, Expert Opinion[16]) can be placed in several configurations:
| Configuration | Eponym | Vascular bed | Indication |
|---|---|---|---|
| Dorsal onlay | Barbagli | Tunica albuginea | Bulbar strictures, ~ 88% success[17][18] |
| Ventral onlay | Morey / McAninch | Corpus spongiosum | Bulbar strictures, about 89% success in a historical pooled review; a later meta-analysis found less transient ED than dorsal onlay, while the permanent-ED estimate was too imprecise to establish comparable risk[17][19][20] |
| Dorsal inlay | Asopa | Tunica albuginea exposed by incising the dorsal plate through a ventral urethrotomy | Shorter operative time and less blood loss than dorsal onlay in a 47-man alternating-allocation study[8]; about 87% success (39/45 evaluated at a mean 42 months, from 58 men treated) in a separate prospective series of recurrent anterior strictures[7] |
| Dorsolateral onlay | Kulkarni | Corporal bed, with contralateral urethral attachments retained | Long penile / panurethral; preserves contralateral NVB[6] |
| Two-sided dorsal + ventral | Palminteri double-face | Tunica + spongiosum | Tight / near-obliterative bulbar strictures; 88% success (64/73 patients with buccal grafts, mean follow-up 48.9 months); none of the 49 preoperatively sexually active men reported postoperative erectile impairment. See Palminteri Double-Face[21][17] |
| Augmented anastomotic | Guralnick / Webster | Hybrid — excise + onlay | Selected focal obliteration within a longer bulbar stricture; avoid unnecessary transection. See the dedicated augmented-anastomotic pages for comparative evidence and tissue-preserving alternatives[6][24] |
The 88.4% dorsal and 88.8% ventral estimates above come from separate pooled cohorts of 934 and 563 men, with mean follow-up of 42.2 and 34.4 months.[17] A later systematic review found no technique superior.[18] Dorsal and ventral onlay had recurrence of 20% or less at medium-term follow-up; evidence for dorsal inlay and dorsolateral onlay was too sparse for recommendations, and recurrence rose with longer follow-up.[18]
For combined graft-and-flap configurations, see Combined Dorsal BMG + Ventral Fasciocutaneous Flap (Erickson) and Ventral BMG + Gracilis Muscle Flap (Vanni / Zinman).
6. Flap-Based Techniques — Declining Role
Penile fasciocutaneous flaps (Orandi, Quartey, Q-flap, McAninch circular) historically dominated long penile and panurethral reconstruction. In the Cotter series of 2,098 anterior urethroplasties from 2010 to 2017, penile-urethral fasciocutaneous flap use declined 86% and single-stage dorsal repairs increased 280%.[9] Among bulbar substitutional repairs in that series, dorsal graft placement increased 95% and ventral placement fell 75%.[9]
In this retrospective 222-man non-hypospadiac penile-stricture series, success (no cystoscopically confirmed recurrence <16 Fr) was 83% with buccal mucosa graft and 52% with fasciocutaneous flap; median follow-up for the full cohort was 49 months.[3] EAU 2026 reports no significant overall patency difference in other graft-versus-flap comparisons (the two small randomized trials excluded LS), with more flap morbidity; it strongly recommends a graft when both options are equally indicated and weakly recommends a flap for a poorly vascularized urethral bed.[29] In a 2022 survey of GURS members (134 respondents, 38% response rate), 90% preferred multiple buccal grafts over combined graft and flap for panurethral strictures.[22] Flap-based techniques remain useful in specific scenarios:
- Circumferential one-stage replacement. In non-LS strictures with suitable penile skin, a vascularized flap can form a tube when a complete urethral segment requires replacement. EAU strongly recommends against a tubularized free graft for single-stage repair.[24][29]
- Compromised graft bed (radiation, severe spongiofibrosis). The flap brings its own blood supply.
- Depleted oral mucosa. A penile or preputial flap can supply vascularized tissue when suitable non-hair-bearing genital skin is available and LS is absent.[24][29] With suitable foreskin, a preputial spiral graft provides a free-graft option.[29]
- Resource-limited settings. No specialized graft material is required.
7. One-Stage vs Staged
| Setting | Preferred |
|---|---|
| Bulbar strictures not amenable to tension-free EPA | One-stage free graft urethroplasty; choose dorsal, dorsolateral or ventral placement by operative findings and expertise. The EAU reports 88–91% patency at short- to medium-term follow-up and strongly recommends free graft in this setting.[24] |
| Penile strictures requiring augmentation, including distal or primary disease | Single-stage or staged repair according to prior interventions and stricture characteristics; counsel that adverse intraoperative findings may require conversion to staged repair .[24] |
| Complex penile strictures with extensive spongiofibrosis | Staged (Bracka or Johanson) repair is often considered when scarring or urethral-plate quality is unfavorable; counsel that adverse intraoperative findings may require conversion from a planned single-stage repair . If the first stage heals satisfactorily, EAU weakly recommends waiting at least four to six months before tubularization.[24] |
| Lichen sclerosus | For LS-related penile strictures, the EAU weakly recommends single-stage oral-mucosa graft repair in the absence of adverse local conditions; consider staged repair when local conditions preclude it. Do not use genital skin for augmentation penile urethroplasty .[24] |
| Failed hypospadias repair | Select single-stage or staged reconstruction by plate, skin, scarring, fistula and chordee; refer patients to a specialist center .[24] |
| Panurethral disease with a usable plate | One-stage Kulkarni dorsolateral oral-graft repair is one option; select the technique by segment, tissue quality and extent, and combine approaches when one cannot treat the full stricture .[24] |
| Panurethral disease with an unusable plate | Consider staged oral-graft reconstruction; a combined graft + flap (Erickson) is an option only when healthy, non-hair-bearing penile skin is available and LS is absent. Offer complex panurethral repair in a specialist center .[24] |
Mangera 2011 reported pooled success of 90.5% for two-stage (n = 129) versus 75.7% for one-stage (n = 432) penile repairs across heterogeneous series, with shorter follow-up for the staged group (22.2 vs 32.8 months).[17] A 2025 nine-center observational cohort studied 231 men with LS-related penile strictures, excluding meatal strictures <2 cm, bulbar involvement and panurethral strictures >10 cm. Five-year stricture-free estimates were 82% after single-stage oral-graft repair (127 men), 76% after staged repair (44 men) and 75% after perineal urethrostomy (60 men; log-rank P = .6).[31]
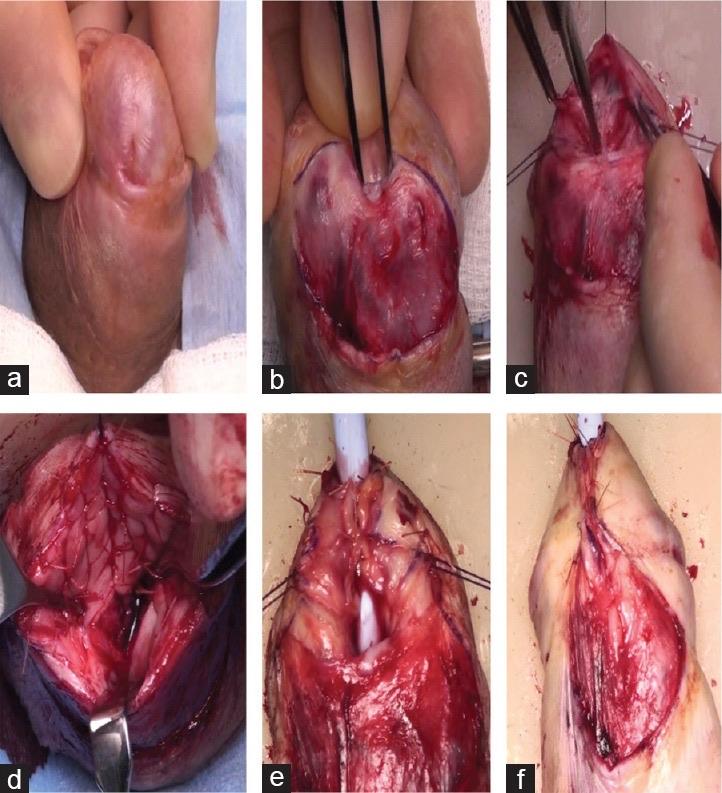
Selected single-stage tubularized buccal mucosa graft (BMG) repair of a fossa navicularis stricture. (a) Preoperative appearance of a severe lichen sclerosus fossa navicularis stricture. (b) Urethral exposure and location of the stricture. (c) Dorsal incision to deepen the glans. (d) Complete resurfacing with BMG. (e) First layer of neourethral retubularization. (f) Second and third layers of closure. From Campos-Juanatey F, et al. Asian J Androl. 2020;22(2):134-139, Figure 2 (CC BY-NC-SA).[23]
Contemporary Trends — Summary
Practice patterns in the TURNS series changed over 2010-2017:[9]
- Single-stage dorsal penile repairs increased 280% and penile fasciocutaneous flap use decreased 86%.[9]
- Bulbar excisional repairs without transection increased 430%.[9]
Retrospective series associate the midline perineal incision with fewer wound complications than the lambda or inverted-U incision.[1][2] The AUA guideline names oral mucosa as the first-choice graft.[16]
References
1. Lin Y, Luo D, Liao B, et al. Perineal midline vertical incision versus inverted-U incision in urethroplasty: which is better? World J Urol. 2018;36(8):1267-1274. doi:10.1007/s00345-018-2267-x.
2. Bascom A, Ghosh S, Fairey AS, Rourke KF. Assessment of wound complications after bulbar urethroplasty: the impact of a lambda perineal incision. Urology. 2016;90:184-188. doi:10.1016/j.urology.2015.12.047.
3. Abramowitz D, Sam AP, Pachorek M, et al. Multi-institutional review of non-hypospadiac penile urethral stricture management and outcomes. Int J Urol. 2022;29(5):376-382. doi:10.1111/iju.14786.
4. Johnsen N, Wessells H, Archer-Arroyo K, et al. Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons; 2025.
5. Takekawa K, Horiguchi A, Shinchi M, et al. One-sided dorsal onlay urethroplasty with penile invagination (Kulkarni urethroplasty) for complex anterior urethral strictures: a single-center experience. Int J Urol. 2025;32(6):749-755. doi:10.1111/iju.70048.
6. Horiguchi A. Substitution urethroplasty using oral mucosa graft for male anterior urethral stricture disease: current topics and reviews. Int J Urol. 2017;24(7):493-503. doi:10.1111/iju.13356.
7. Pisapati VL, Paturi S, Bethu S, et al. Dorsal buccal mucosal graft urethroplasty for anterior urethral stricture by Asopa technique. Eur Urol. 2009;56(1):201-205. doi:10.1016/j.eururo.2008.06.002.
8. Aldaqadossi H, El Gamal S, El-Nadey M, et al. Dorsal onlay (Barbagli technique) versus dorsal inlay (Asopa technique) buccal mucosal graft urethroplasty for anterior urethral stricture: a prospective randomized study. Int J Urol. 2014;21(2):185-188. doi:10.1111/iju.12235.
9. Cotter KJ, Hahn AE, Voelzke BB, et al. Trends in urethral stricture disease etiology and urethroplasty technique from a multi-institutional surgical outcomes research group. Urology. 2019;130:167-174. doi:10.1016/j.urology.2019.01.046.
10. Koraitim MM. On the art of anastomotic posterior urethroplasty: a 27-year experience. J Urol. 2005;173(1):135-139. doi:10.1097/01.ju.0000146683.31101.ff.
11. Kizer WS, Armenakas NA, Brandes SB, et al. Simplified reconstruction of posterior urethral disruption defects: limited role of supracrural rerouting. J Urol. 2007;177(4):1378-1381. doi:10.1016/j.juro.2006.11.036.
12. Koraitim MM. Transpubic urethroplasty revisited: total, superior, or inferior pubectomy? Urology. 2010;75(3):691-694. doi:10.1016/j.urology.2009.09.026.
13. Pratap A, Agrawal CS, Tiwari A, et al. Complex posterior urethral disruptions: management by combined abdominal transpubic perineal urethroplasty. J Urol. 2006;175(5):1751-1754. doi:10.1016/S0022-5347(05)00974-2.
14. Koraitim MM. The lessons of 145 post-traumatic posterior urethral strictures treated in 17 years. J Urol. 1995;153(1):63-66. doi:10.1097/00005392-199501000-00024.
15. Quartey JK. A modified perineal approach to reconstruction of membranous urethra for stricture. J Urol. 1988;139(4):780-783. doi:10.1016/s0022-5347(17)42635-8.
16. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
17. Mangera A, Patterson JM, Chapple CR. A systematic review of graft augmentation urethroplasty techniques for the treatment of anterior urethral strictures. Eur Urol. 2011;59(5):797-814. doi:10.1016/j.eururo.2011.02.010.
18. Barratt R, Chan G, La Rocca R, et al. Free graft augmentation urethroplasty for bulbar urethral strictures: which technique is best? A systematic review. Eur Urol. 2021;80(1):57-68. doi:10.1016/j.eururo.2021.03.026.
19. Hassan AA, Soliman AM, Shouman HA, et al. Dorsal- vs ventral-onlay buccal mucosal graft urethroplasty for urethral strictures: a meta-analysis. BJU Int. 2025. doi:10.1111/bju.16811.
20. Mousa A, Eissa A, Raheem AA, Zoeir A. Ventral versus dorsal onlay buccal mucosal graft urethroplasty for non-traumatic proximal bulbar urethral strictures in sexually active men: erectile and urinary functions. World J Urol. 2025;43(1):87. doi:10.1007/s00345-025-05441-7.
21. Palminteri E, Berdondini E, Shokeir AA, et al. Two-sided bulbar urethroplasty using dorsal plus ventral oral graft: urinary and sexual outcomes of a new technique. J Urol. 2011;185(5):1766-1771. doi:10.1016/j.juro.2010.12.103.
22. Berg C, Singh A, Hu P, et al. Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons. Urology. 2024;191:139-143. doi:10.1016/j.urology.2024.06.019.
23. Campos-Juanatey F, Bugeja S, Dragova M, et al. Single-stage tubular urethral reconstruction using oral grafts is an alternative to classical staged approach for selected penile urethral strictures. Asian J Androl. 2020;22(2):134-139. doi:10.4103/aja.aja_78_19.
24. EAU Guidelines on Urethral Strictures: disease management in males. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-males. Accessed September 12, 2026.
25. Zhang TR, Alford A, Wang A, Zhao LC. Robotic-assisted posterior urethroplasty: outcomes from 105 men in a single-center experience. Urology. 2023;181:167-173. doi:10.1016/j.urology.2023.05.062.
26. European Association of Urology. EAU Guidelines on Urological Trauma, section 4.4.3.c.3 (deferred management of posterior urethral injury; limited update March 2026). Guideline.
27. Kulkarni SB, Badranavar S, Talpallikar A, Ocampo MA. Dorsal circumcision approach for penile strictures. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:119-123. doi:10.1007/978-981-97-5196-9_15
28. Canagasingham A, Chung A. Penile inversion approaches to the penile urethral stricture. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:125-132.
29. European Association of Urology. “Tissue transfer.” In: EAU Guidelines on Urethral Strictures, 2026 limited update. EAU Guidelines Office, Arnhem, the Netherlands; 2026. Official guideline chapter.
30. Holm HV, Ohnesorge SS, Nilsen OJ. "Long-term Outcomes of Transecting Versus Nontransecting Bulbar Urethroplasty: Results from the Scandinavian Urethroplasty Study." Eur Urol Focus. 2026;12(3):316-318. doi:10.1016/j.euf.2026.05.007
31. Hengel R, Vanni A, Erickson B, et al. "Multi-Institutional Analysis of Surgery for Lichen Sclerosus-Induced Penile Urethral Stricture: Establishing Single-Stage Urethroplasty as a Primary Treatment Option." J Urol. 2025;213(5):628-637. doi:10.1097/JU.0000000000004434