Non-Transecting Bulbar Urethroplasty
Non-transecting bulbar urethroplasty comprises repairs that preserve spongiosal continuity while reconstructing the narrowed urethra. Comparative evidence suggests fewer penile complications, with no detected difference in recurrence; an erectile-function benefit is less consistent.[1][2][3] The operation can involve mucosal excision, a limited stricturoplasty or graft augmentation according to the defect.[1][2][3]
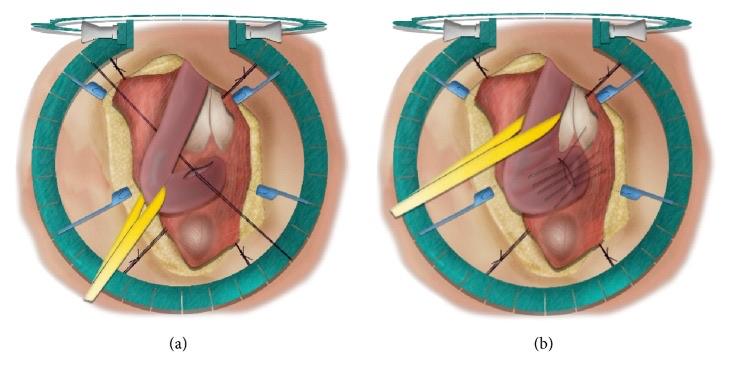
Heineke-Mikulicz stricturoplasty: (a) longitudinal incision across the stricture; (b) transverse closure of the incision. Related: Heineke-Mikulicz principle. From Verla W, et al. Biomed Res Int. 2019;2019:9046430, Figure 7 (CC BY).[23]
Historical Development and Rationale
Spongiosum-preserving anastomotic urethroplasty was introduced by Jordan et al. in 2007 and described in a preliminary series of 22 patients by Andrich and Mundy in 2012 (see the History of Urethral Surgery).[3][4] Preserving viable spongiosum avoids unnecessary disruption of urethral blood supply, which is particularly relevant in non-traumatic strictures with superficial fibrosis. Nearly obliterative short bulbar straddle-injury strictures with full-thickness fibrosis remain an indication for tEPA . [18] Penile shortening and reduced glans filling are reported outcomes.
By preserving the corpus spongiosum and its vasculature, ntBU aims to:
- Maintain bulbar artery blood flow and limit glans ischemia
- Reduce de novo erectile dysfunction
- Preserve a well-vascularized tissue bed for future redo graft surgery; in observational AUS cohorts, prior transecting urethroplasty was associated with higher erosion and explantation risk than prior non-transecting repair, without establishing causation.[26]
- Reduce penile shortening and chordee
These were proposed benefits when the technique was described. In the randomized tEPA-versus-BMG comparison, penile complications were more frequent after tEPA, while IIEF-5 erectile-function scores did not differ at 12 months.[5][9]
Indications
- Short bulbar strictures, usually around 2 cm or less, without full-thickness traumatic obliteration. The EAU 2026 guideline weakly recommends non-transecting excision and primary anastomosis or free graft urethroplasty instead of transecting EPA for short strictures unrelated to straddle injury; longer defects may need a graft.[18]
- Related posterior application: vessel-sparing EPA achieved 88.5% success in a separate 26-patient posterior cohort.[5] Superiority over standard posterior EPA has not been established.[5][18]
- Both primary and recurrent strictures
- Long (>2 cm) bulbar strictures with a short critical segment may be treated with augmented non-transecting repair.[18] In a separate retrospective single-surgeon series of non-transecting anastomotic repair, 30/32 patients with strictures >2 cm and 63/65 with strictures ≤2 cm needed no repeat intervention at a median follow-up of 8.4 months; the abstract reports no graft-augmented arm.[21]
- Can be combined with buccal mucosal grafts for longer strictures (ANTA, MANTA, and ntAAU variants; see below)[11][12][13]
Surgical Technique
The procedure is performed through a perineal incision in lithotomy position. Two main approaches exist, dorsal and ventral, sharing the core principle of spongiosal preservation.
Dorsal Non-Transecting Anastomotic Approach
Jordan’s vessel-sparing repair and subsequent non-transecting modifications share a vascular-preservation aim but differ in dissection. The following steps describe the dorsal non-transecting end-to-end variant illustrated in Figure 6. Jordan's vessel-sparing EPA differs in dissection and spatulation; assess scar depth and tissue viability before deciding whether spongiosal continuity can be preserved.[3][5][23]
- Exposure: Make a midline perineal incision, divide the bulbospongiosus muscle in the midline, and mobilize the spongiosum dorsally off the corpora cavernosa. Leave the proximal bulb attached to the perineal body to preserve bulbar arterial entry.[5]
- Dorsal urethrotomy: Expose the dorsal surface without excessive torsion of the preserved attachments. Make a dorsal midline urethrotomy through the strictured segment and extend it into healthy urethra proximally and distally without transecting the spongiosum. Assess scar length and depth: a membrane-like lesion may need transverse stricturoplasty without excision, superficial scar may permit mucosal anastomosis, and a longer segment may need graft augmentation; for a short traumatic near-obliteration with full-thickness spongiofibrosis, EAU strongly recommends tEPA.[24][18]
- Scar excision: Excise scarred urethral epithelium and adjacent spongiofibrosis to healthy underlying spongiosum without full-thickness division of the corpus spongiosum.[23]
- Spatulation: Spatulate the healthy proximal and distal mucosal ends ventrally so they can meet without tension.[23]
- Anastomosis: Approximate the healthy ventral mucosal edges without tension using 5-0 absorbable sutures (interrupted or running), then close the dorsal urethrotomy transversely.[23]
- Spongioplasty: The corpus spongiosum is re-approximated over the anastomosis with 4-0 absorbable sutures.
- Catheter: Catheter size and duration are tailored to the repair; selected uncomplicated short repairs may allow early removal. EAU strongly recommends validated urethrography to assess for extravasation before catheter removal.[19]
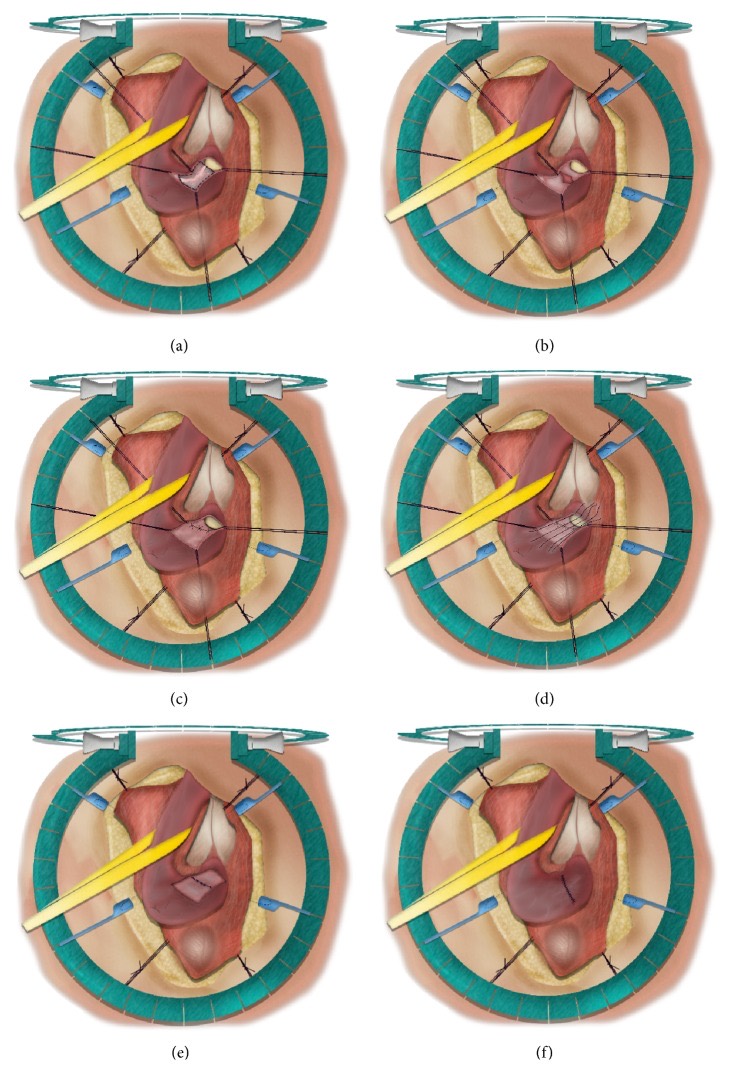
Non-transecting end-to-end urethroplasty. (a) Excision of the stricture and surrounding spongiofibrosis after a dorsal longitudinal incision; (b) ventral spatulation of the proximal and distal urethral ends; (c) transverse closure of the ventral urethral plate; (d, e) transverse closure of the dorsal urethra; (f) spongioplasty. The spongiosum is not divided full-thickness, aiming to preserve the bulbar arteries. From Verla W, et al. Biomed Res Int. 2019;2019:9046430, Figure 6 (CC BY).[23]
Ventral Approach
Morán et al. described a ventral approach for short mid or distal bulbar strictures in ten patients; Bogdanov et al. described a related approach that avoids full dorsal spongiosal mobilization. Selection and operative details vary between these reports.[6][7]
- A ventral midline urethrotomy is made through the stricture.
- Mucosal scar tissue is excised (mucosectomy) while preserving the dorsal spongiosum.
- Healthy mucosal edges are approximated without tension.
- Mucosal closure is performed in a Heineke–Mikulicz fashion using 5-0 absorbable monofilament; spongioplasty with 4-0 absorbable suture.
The ventral approach avoids full dorsal mobilization of the corpus spongiosum.[6][7]
Heineke–Mikulicz Selection and Closure (Wibowo / Satyagraha)
Wibowo and Satyagraha describe direct transverse Heineke–Mikulicz closure for a short, membrane-like 1–2 cm stricture at the junction of the proximal and middle thirds of the bulbar urethra. Their mucosa-to-mucosa closure uses three mirrored suture pairs at the 12/6, 1/5 and 11/7 o'clock positions, followed by a spongiosum-to-spongiosum layer using three 5-0 polyglactin sutures in the same pattern.[22]
Augmented Non-Transecting Techniques
For longer bulbar strictures with a short, nearly obliterative segment and viable residual spongiosum, a non-transecting repair can combine limited scar excision and mucosal anastomosis with buccal graft augmentation . For short, nearly obliterative post-traumatic strictures with full-thickness spongiofibrosis, EAU strongly recommends tEPA.[18]
| Variant | Description | Key Outcome Data |
|---|---|---|
| ANTA (augmented non-transected anastomotic urethroplasty) | Mucosectomy + dorsal onlay BMG; smaller graft than pure onlay BMG | 20/21 without further treatment; 93% was the combined 44-patient ANTA/onlay cohort. Median graft 4.5 versus 5 cm (p = 0.047)[11] |
| MANTA (mucomucosal anastomotic non-transecting augmentation) | Ventral modification selected intraoperatively for strictures ≥2 cm with an obliterative segment ≤1.5 cm, a dorsal bed <0.5 cm, and no severe fibrosis beyond the mucosa.[12] | The cohort included 38 bulbar and 16 penobulbar strictures; 50/54 (93%) reported functional success at median 41 months (four lost to follow-up before 3 months); IIEF-EF 27 → 24 (p = 0.4) in sexually active patients; all 45 patients with satisfaction data were satisfied or very satisfied[12] |
| ntAAU (non-transecting augmented anastomotic urethroplasty with dorsal onlay BMG) | 42 patients; dorsal onlay technique | 90.5% anatomical success at median 18 months; postoperative median IIEF-5 of 22; questionnaires were available for 31/42 patients[13] |
An important caveat for augmented repairs: in long bulbar strictures, transecting augmented anastomotic urethroplasty was independently associated with stricture recurrence compared to non-transecting dorsal onlay (HR 4.8, p = 0.002), in a retrospective institutional comparison with an era change.[14] It did not compare the named non-transecting augmented variants.[14]
Outcomes
Stricture-Free Rates
Comparative studies have not detected a statistically significant recurrence difference between transecting and non-transecting approaches. In the 2026 VeSpAR phase II conference abstract, 51 men were assigned vessel-sparing and 49 transecting anastomotic repair; 24-month cystoscopic failure-free survival was 93.6% versus 88.3%, and 9/51 vessel-sparing assignments (18%) converted intraoperatively because of full-thickness spongiofibrosis.[25] The authors reported noninferiority under a prespecified 10% margin and 80% confidence interval; this preliminary result applies to the trial's selected short bulbar strictures.[2][9][25]
- Retrospective multi-institutional comparison (352 patients): cystoscopic patency >16 Fr was 97.9% with non-transecting versus 93.8% with transecting repair (p = 0.18) at a cohort mean follow-up of 64.2 months[1]
- Meta-analysis of 19 studies (Oszczudlowski et al.): pooled RR 1.06 (95% CI 0.82–1.36); no difference[2]
- Meta-analysis of 13 studies, 1,683 patients (Zhao et al.): no significant difference in success rate, Qmax, or overall complications[8]
Sexual Function and Penile Outcomes
This is the primary domain of benefit for ntBU:
- Multi-institutional analysis (Chapman et al., 352 patients): At six months, the study's composite sexual-dysfunction outcome (a SHIM decline of at least five points or a patient-reported adverse change) occurred in 4.3% after non-transecting versus 14.3% after transecting repair (p = 0.008). On multivariate analysis, only the transecting technique was independently associated with sexual dysfunction (p = 0.01); age, stricture length, etiology, and surgeon were not.[1]
- Meta-analysis (Zhao et al., 1,683 patients): ntBU had a significantly lower incidence of erectile dysfunction compared to transecting bulbar urethroplasty (tBU); no differences in other perioperative outcomes.[8]
- Meta-analysis (Oszczudlowski et al., 19 studies): ED risk ratio 0.73 (95% CI 0.49–1.08), trending toward benefit but not statistically significant. Penile complications were significantly lower: RR 0.47 (95% CI 0.28–0.76, p < 0.05).[2]
- Scandinavian Urethroplasty Study (Nilsen et al.), randomized trial (151 patients with bulbar strictures ≤2 cm and no previous urethroplasty, 12-month follow-up): Compared transecting EPA to non-transecting BMG. tEPA had significantly more penile complications (p = 0.02), particularly reduced glans filling (p = 0.03) and shortened penis (p = 0.001). No difference in IIEF-5 scores. Recurrence, defined as need for retreatment, occurred in 12.9% overall among 147 with recurrence data: 12.0% after tEPA (9/75 randomized) and 13.2% after BMG (10/76 randomized) during 12-month follow-up[9][20]; the study was not designed to detect differences in recurrence. The penile complications questionnaire was not validated.[9]
- Lumen et al. (75 patients, 55 bulbar and 20 posterior, median follow-up 30 months): Stricture recurred in 8%. De novo ED was reported by 7 of 32 evaluable patients (21.9%) and post-void dribbling by 2 of 42 (4.7%) at 3 months.[10]
- Mixed-urethroplasty IIEF cohort (Frankiewicz et al., 103 patients). Higher baseline erectile-function scores and younger age were associated with better postoperative scores, while diabetes was associated with worse three-month scores.[15]
2026 trial update: Holm and colleagues restate the 12-month results: more penile shortening and reduced glans filling after tEPA than BMG, with one or more penile complications in 33% versus 16% (p = 0.02) and recurrence of 12.2% versus 13.0%. They note that no randomized trial has compared tEPA with ntEPA, so the superiority of ntEPA remains a hypothesis; follow-up of at least 6 years is planned.[20]
Other Perioperative Outcomes
| Outcome | Non-Transecting | Transecting | Notes |
|---|---|---|---|
| 90-day Clavien grade ≥2 complications | 4.3% | 8.1% | Not statistically significant (p = 0.25)[1] |
| Learning curve | No association detected in one series | — | Limited 75-pt tertile analysis[10] |
Predictors of Outcomes
- In a retrospective mixed-urethroplasty cohort (Frankiewicz et al., 103 patients), higher baseline erectile-function scores and younger age were associated with better postoperative IIEF scores.[15]
- Diabetes is associated with worse short-term erectile function outcomes[15]
- Combined penile and bulbar strictures were associated with worse long-term erectile-function outcomes in a multicenter IIEF analysis; only three patients had this stricture pattern.[15]
- Stricture length ≥5 cm was associated with lower patency in a 163-patient dorsal onlay augmented anastomotic cohort (median follow-up 31 months).[16]
- A small single-center analysis did not detect a learning-curve effect.[10]
Practice Trends
In a 2022 survey of Society of Genitourinary Reconstructive Surgeons (GURS) members (134 of 350 invited responded; published 2024), dorsal graft placement was preferred (66%) over ventral (34%) for bulbar urethroplasty with BMG.[17] Anastomotic urethroplasty was preferred over BMG for short bulbomembranous strictures after radiotherapy (63% versus 37%).[17] The survey did not ask about transecting versus non-transecting technique. Meta-analyses associate non-transecting repair with fewer penile complications and similar recurrence. For longer strictures needing augmentation, a retrospective comparison associated dorsal onlay with less recurrence than transecting augmented anastomotic repair, subject to selection and era confounding.[2][8][14]
Videos
References
-
Chapman DW, Cotter K, Johnsen NV, et al. "Nontransecting techniques reduce sexual dysfunction after anastomotic bulbar urethroplasty: results of a multi-institutional comparative analysis." J Urol. 2019;201(2):364–370. doi:10.1016/j.juro.2018.09.051
-
Oszczudlowski M, Yepes C, Dobruch J, Martins FE. "Outcomes of transecting versus non-transecting urethroplasty for bulbar urethral stricture: a meta-analysis." BJU Int. 2023;132(3):252–261. doi:10.1111/bju.16108
-
Virasoro R, DeLong JM. "Non-transecting bulbar urethroplasty is favored over transecting techniques." World J Urol. 2020;38(12):3013–3018. doi:10.1007/s00345-019-02867-8
-
Andrich DE, Mundy AR. "Non-transecting anastomotic bulbar urethroplasty: a preliminary report." BJU Int. 2012;109(7):1090–1094. doi:10.1111/j.1464-410X.2011.10508.x
-
Verla W, Oosterlinck W, Waterloos M, Lumen N. "Vessel-sparing excision and primary anastomosis." J Vis Exp. 2019;(143). doi:10.3791/58214
-
Morán E, Sáez Moreno I, Bonillo MA, et al. "Ventral approach for the non-transecting bulbar urethroplasty." Urology. 2021;152:197–198. doi:10.1016/j.urology.2021.02.003
-
Bogdanov AB, Veliev EI, Sokolov EA, et al. "Nontransecting anastomotic urethroplasty via ventral approach without full mobilization of the corpus spongiosum dorsal semicircumference." Urology. 2021;152:136–141. doi:10.1016/j.urology.2020.10.074
-
Zhao X, Xing Y, Zhang X, et al. "Low risk of erectile dysfunction after nontransecting bulbar urethroplasty for urethral stricture: a systematic review and meta-analysis." J Sex Med. 2023;21(1):11–19. doi:10.1093/jsxmed/qdad141
-
Nilsen OJ, Holm HV, Ekerhult TO, et al. "To transect or not transect: results from the Scandinavian Urethroplasty Study, a multicentre randomised study of bulbar urethroplasty comparing excision and primary anastomosis versus buccal mucosal grafting." Eur Urol. 2022;81(4):375–382. doi:10.1016/j.eururo.2021.12.017
-
Lumen N, Poelaert F, Oosterlinck W, et al. "Nontransecting anastomotic repair in urethral reconstruction: surgical and functional outcomes." J Urol. 2016;196(6):1679–1684. doi:10.1016/j.juro.2016.06.016
-
Welk BK, Kodama RT. "The augmented nontransected anastomotic urethroplasty for the treatment of bulbar urethral strictures." Urology. 2012;79(4):917–921. doi:10.1016/j.urology.2011.12.008
-
Marks P, Dahlem R, Janisch F, et al. "Mucomucosal anastomotic non-transecting augmentation (MANTA) urethroplasty: a ventral modification for obliterative strictures." BJU Int. 2023;132(4):444–451. doi:10.1111/bju.16112
-
Baudry A, Schirmann A, Guillot-Tantay C, et al. "Non-transecting anastomotic augmented urethroplasty with dorsal onlay buccal graft for the treatment of bulbous urethral strictures: results and complications." World J Urol. 2025;43(1):238. doi:10.1007/s00345-025-05633-1
-
Redmond EJ, Hoare DT, Rourke KF. "Augmented anastomotic urethroplasty is independently associated with failure after reconstruction for long bulbar urethral strictures." J Urol. 2020;204(5):989–995. doi:10.1097/JU.0000000000001177
-
Frankiewicz M, Białek Ł, Rydzińska M, et al. "Impact of urethroplasty on erectile function: a multicenter analysis of the International Index of Erectile Function score changes across different etiologies of urethral stricture." J Clin Med. 2025;14(9):2936. doi:10.3390/jcm14092936
-
Hoy NY, Kinnaird A, Rourke KF. "Expanded use of a dorsal onlay augmented anastomotic urethroplasty with buccal mucosa for long segment bulbar urethral strictures: analysis of outcomes and complications." Urology. 2013;81(6):1357–1361. doi:10.1016/j.urology.2013.02.012
-
Berg C, Singh A, Hu P, et al. "Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons." Urology. 2024;191:139–143. doi:10.1016/j.urology.2024.06.019
-
European Association of Urology. EAU Guidelines on Urethral Strictures: disease management in males. 2026. Current guideline.
-
European Association of Urology. EAU Guidelines on Urethral Strictures: perioperative care of urethral surgery. 2026. Current guideline.
-
Holm HV, Ohnesorge SS, Nilsen OJ. Long-term outcomes of transecting versus nontransecting bulbar urethroplasty: results from the Scandinavian Urethroplasty Study. Eur Urol Focus. 2026;12(3):316–318. doi:10.1016/j.euf.2026.05.007.
-
Findlay BL, Moring N, Miller AJ, et al. Comparison of functional and patient-reported outcomes following non-transecting anastomotic urethroplasty for lengthy (>2 cm) versus short (≤2 cm) bulbar urethral strictures. Urology. 2026;210:126-130. doi:10.1016/j.urology.2026.01.045.
-
Wibowo E, Satyagraha P. Non-Transecting Bulbar Urethroplasty. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:61-62.
-
Verla W, Oosterlinck W, Spinoit AF, Waterloos M. "A Comprehensive Review Emphasizing Anatomy, Etiology, Diagnosis, and Treatment of Male Urethral Stricture Disease." Biomed Res Int. 2019;2019:9046430. doi:10.1155/2019/9046430
-
Bugeja S, Andrich DE, Mundy AR. "Non-transecting bulbar urethroplasty." Transl Androl Urol. 2015;4(1):41-50. doi:10.3978/j.issn.2223-4683.2015.01.07
-
Verla W, Waterloos M, Waterschoot M, et al. "IP39-01 VeSpAR trial: A randomized controlled trial comparing vessel-sparing anastomotic repair and transecting anastomotic repair in isolated, short, bulbar urethral strictures." J Urol. 2026;215(5S):e805 [conference abstract]. doi:10.1097/01.JU.0001191512.50502.2b.01
-
Deameh MG, Mohamed H, Abdelshafi A, Mohamed T, Ramez M. "Association of Prior Urethroplasty and Technique With Outcomes After Artificial Urinary Sphincter Implantation: A Systematic Review and Meta-analysis." Urology. 2026;214:135-142. doi:10.1016/j.urology.2026.05.024