ntAAU Urethroplasty (Non-Transecting Augmented Anastomotic)
The ntAAU urethroplasty (Non-Transecting Augmented Anastomotic) is a variant of non-transecting bulbar urethroplasty described by Baudry, Schirmann, and Guillot-Tantay in 2025. It applies the vessel-sparing principle specifically to the traditional augmented anastomotic urethroplasty with dorsal onlay buccal graft: the stenotic mucosa and superficial spongiofibrosis are excised while preserving the deeper spongiosum in continuity, and the remaining stricture is augmented with a dorsal onlay BMG.[1]
For the broader non-transecting family, see Non-Transecting Bulbar Urethroplasty, ANTA, MsANTA / Joshi Step, and MANTA. For the transecting alternative, see Augmented Anastomotic Urethroplasty. For graft material, see Buccal Mucosa Graft.
Concept and Rationale
ntAAU and ANTA (Welk / Kodama 2012) share the same conceptual framework: non-transecting excision of the stricture segment combined with dorsal onlay BMG augmentation. The single-arm Baudry 2025 series reports outcomes at a median 18 months in 42 patients with bulbar strictures containing a nearly obliterative or obliterative segment; its 90.5% anatomical success is reported for the full cohort.[1] For a longer stricture whose critical segment is short, ntAAU combines focal excision with dorsal graft augmentation without full spongiosal transection.[1][2]
The clinical importance of avoiding spongiosal transection (the Chapman 2019 sexual-dysfunction signal,[3] the Oszczudlowski 2023 meta-analysis,[5] and the 151-patient Scandinavian RCT of transecting EPA versus BMG for unreconstructed bulbar strictures ≤2 cm[16]) is housed in the umbrella Non-Transecting Bulbar Urethroplasty article. In Redmond / Rourke's retrospective 507-patient comparison of transecting augmented anastomotic urethroplasty and pure dorsal onlay BMG, the anastomotic group had higher adjusted recurrence (HR 4.8, p = 0.002).[4] Redmond did not include a separate ntAAU arm.
Indications
- For bulbar strictures not amenable to EPA, the EAU 2026 guideline strongly recommends free graft urethroplasty and weakly recommends augmented non-transecting anastomosis when a short, nearly obliterative core can be excised and reapproximated without tension while preserving viable spongiosum. Its level-3 evidence summary concerns total length >2 cm with a critical area <1 cm.[10]
- The surgeon wishes to avoid full spongiosal transection with the aim of preserving vascularity; a sexual-function benefit for this specific variant is unproven.[3]
- Viable urethral plate edges remain for graft suturing, and the corporal tunica provides the bed for the dorsal onlay graft.[1][2]
Contraindications / limitations
- For LS-related disease, assess the full affected segment and local tissue quality. For penile strictures due to LS, EAU 2026 weakly recommends single-stage oral mucosa graft urethroplasty in the absence of adverse local conditions; for LS-proven urethral stricture, AUA 2023 strongly recommends against genital skin reconstruction.[10][14]
- Strictures suitable for pure dorsal onlay BMG (where the excisional component is unnecessary)
- Strictures whose obliterative core is too long for tension-free mucosal anastomosis while retaining viable spongiosum
- Short post-traumatic bulbar strictures with nearly complete or complete obliteration and full-thickness spongiofibrosis: use transecting EPA .[10]
Surgical Technique
The technique combines the principles of non-transecting excision with dorsal onlay buccal graft augmentation.[1]
Step 1. Approach. Bulbar urethra exposed via a perineal midline incision. The urethra is mobilized through the bulbospongiosus while preserving lateral structures and keeping the corpus spongiosum in continuity.[12]
Step 2. Dorsal urethrotomy and focal mucosectomy. Open the bulbar urethra dorsally to assess the most stenotic segment. As in ANTA, excise the scarred mucosa and superficial spongiofibrosis while preserving the deeper spongiosum in continuity.[1][7]
Step 3. Mucosal anastomosis at the obliterative core. The healthy mucosal edges at the site of excision are spatulated and anastomosed in a tension-free, mucosa-to-mucosa fashion, the "anastomotic" component.
Step 4. Dorsal onlay BMG augmentation. A buccal mucosal graft is placed as a dorsal onlay to augment the remaining strictured urethra, the "augmentation" component. The graft is sutured to the urethral plate edges and quilted to the underlying tunica albuginea of the corpora cavernosa.
Step 5. Closure. The dorsal graft lies against the corporal tunica; secure the urethral margins to the graft and close the remaining tissues without constriction. Bulbospongiosus and perineal tissues are approximated. Catheter duration depends on repair complexity and healing; 2–3 weeks is common after graft reconstruction. In Baudry’s ntAAU series, a suprapubic catheter was placed at surgery, the urethral catheter was removed at one week, and VCUG through the suprapubic tube at three weeks preceded suprapubic catheter removal if no extravasation was seen.[12] Assess for extravasation by urethrography before removal. [11]
The spongiosum remains in continuity throughout, avoiding complete spongiosal transection. Preserving bulbar arterial flow is the operative rationale.[1][6]
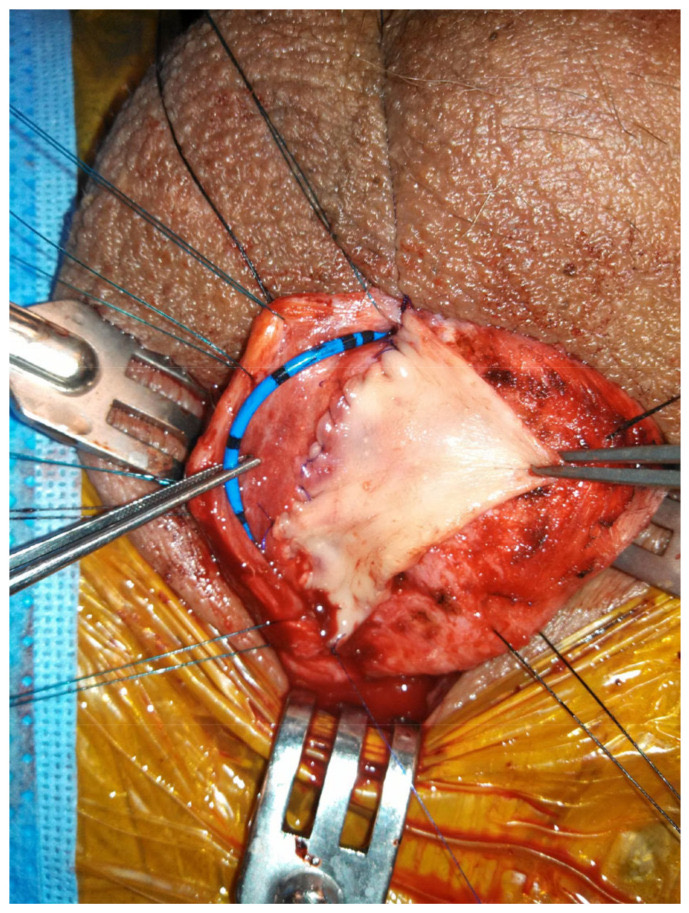
Non-transecting dorsal onlay buccal mucosa graft urethroplasty, the augmentation component of ntAAU: the bulbar urethra is opened dorsally without dividing the spongiosum and the graft is sutured to the urethral margins. From Coddington N, et al. J Clin Med. 2022;11(23):7033, Figure 2 (CC BY 4.0).[2]
Outcomes — Baudry 2025
The Baudry / Schirmann / Guillot-Tantay 2025 series:[1]
| Parameter | Result |
|---|---|
| Number of patients | 42 |
| Median follow-up | 18 months |
| Design | Retrospective, single-center, single-surgeon cohort; no comparator[12] |
| Anatomical success (16.5 Fr cystoscope passage) | 90.5%[1] |
| Functional success (Qmax >15 mL/s) | 83.3%[1] |
| Complications | 6/42 (14.2%) early events (urinary infection, suprapubic catheter obliteration, abscess, bleeding); the authors' 2024 preprint specifies 2/42 (4.8%) Clavien–Dindo grade III events (hematuria and abscess requiring reoperation)[1][12] |
| Postoperative median IIEF-5 | 22 among sexually active respondents in a cohort prescribed tadalafil 5 mg daily after catheter removal for six months to one year[1][12] |
| Salvage of failures | Redo urethroplasty |
After graft urethroplasty, EAU 2026 strongly recommends at least one year of routine follow-up and weakly recommends flexible cystoscopy at three months.[15] Its proposed standard-risk graft schedule includes uroflowmetry, PROMs, and anatomical evaluation at 3, 12, and 24 months, followed by uroflowmetry and PROMs at five years with anatomical evaluation on indication.[15]
ntAAU vs. ANTA
ntAAU and ANTA are conceptually similar: both excise the strictured segment without transecting the spongiosum and augment with dorsal onlay BMG. The two reports differ in cohort size, follow-up and outcome definitions.
| Feature | ANTA[7] | ntAAU[1] |
|---|---|---|
| Year | 2012 | 2025 |
| Spongiosum | Preserved | Preserved |
| Mucosa | Excised (mucosectomy) | Excised (mucosectomy) |
| Approach | Dorsal | Dorsal |
| Graft | Dorsal onlay BMG | Dorsal onlay BMG |
| Series indication | Bulbar stricture treated by complete excision plus onlay | Bulbar stricture >1 cm with a nearly obliterative or obliterative segment; reported mean total length 19.8 mm[12] |
| Original n | 21 | 42 |
| Success | 20/21 without retreatment; median cohort follow-up 2.3 years[7] | 90.5% anatomical / 83.3% functional; median follow-up 18 months[1] |
The Baudry 2025 series provides larger contemporary outcome data for the indication that ANTA originally targeted, with postoperative IIEF-5 documentation.
ntAAU in the Non-Transecting Family
| Feature | VS-EPA / ntEPA[6][13] | ANTA[7] | MsANTA[8] | MANTA[9] | ntAAU[1] |
|---|---|---|---|---|---|
| Initial report | VS-EPA 2007 / ntEPA 2012 | 2012 | 2022 | 2023 | 2025 |
| Spongiosum | Preserved | Preserved | Preserved | Preserved | Preserved |
| Mucosa | Excised | Excised | Preserved (incised) | Dorsal scar superficially excised | Excised |
| Approach | Dorsal or ventral | Dorsal | Dorsal or ventral | Ventral | Dorsal |
| Graft | None | Dorsal onlay BMG | Onlay BMG | Ventral onlay BMG | Dorsal onlay BMG |
| Ideal stricture | Short ≤2 cm | Bulbar stricture treated by complete excision plus onlay | Narrowed but viable mucosa | ≥2 cm with obliterative ≤1.5 cm | Graft-requiring bulbar stricture with a short, nearly obliterative core[10] |
Named variants overlap; their small cohorts, endpoints and follow-up differ and do not establish a ranking of procedures.
Key Takeaways
- ntAAU is a 2025 reported non-transecting augmented anastomotic technique (Baudry 2025).[1]
- ntAAU is conceptually similar to ANTA (2012): non-transecting excision and dorsal onlay BMG. Selection rests on total stricture length, the short critical segment and viable residual spongiosum.
- Anatomical success was 90.5% and functional success 83.3% in 42 patients at a median follow-up of 18 months.[1] In the Baudry series, 27 of 31 questionnaire respondents (87%; 31 of 42 treated patients responded) were satisfied or very satisfied.[1] The EAU 2026 guideline cites this result and makes a weak recommendation for augmented non-transecting anastomotic repair in short, nearly obliterative segments (level of evidence 3).[10]
- In Baudry's cohort, postoperative median IIEF-5 was 22 among sexually active questionnaire respondents prescribed tadalafil 5 mg daily after catheter removal.[1][12]
- Failures were managed with redo urethroplasty. The complication rate was 14.2%.[1]
Videos
References
-
Baudry A, Schirmann A, Guillot-Tantay C, et al. Non-transecting anastomotic augmented urethroplasty with dorsal onlay buccal graft for the treatment of bulbous urethral strictures: results and complications. World J Urol. 2025;43(1):238. doi:10.1007/s00345-025-05633-1.
-
Coddington N, Higgins M, Mian A, Flynn B. Non-transecting urethroplasty for bulbar urethral strictures — narrative review and treatment algorithm. J Clin Med. 2022;11(23):7033. doi:10.3390/jcm11237033.
-
Chapman DW, Cotter K, Johnsen NV, et al. Nontransecting techniques reduce sexual dysfunction after anastomotic bulbar urethroplasty: results of a multi-institutional comparative analysis. J Urol. 2019;201(2):364-370. doi:10.1016/j.juro.2018.09.051.
-
Redmond EJ, Hoare DT, Rourke KF. Augmented anastomotic urethroplasty is independently associated with failure after reconstruction for long bulbar urethral strictures. J Urol. 2020;204(5):989-995. doi:10.1097/JU.0000000000001177.
-
Oszczudlowski M, Yepes C, Dobruch J, Martins FE. Outcomes of transecting versus non-transecting urethroplasty for bulbar urethral stricture: a meta-analysis. BJU Int. 2023;132(3):252-261. doi:10.1111/bju.16108.
-
Jordan GH, Eltahawy EA, Virasoro R. The technique of vessel sparing excision and primary anastomosis for proximal bulbous urethral reconstruction. J Urol. 2007;177(5):1799-802. doi:10.1016/j.juro.2007.01.036.
-
Welk BK, Kodama RT. The augmented nontransected anastomotic urethroplasty for the treatment of bulbar urethral strictures. Urology. 2012;79(4):917-21. doi:10.1016/j.urology.2011.12.008.
-
Joshi P, Bandini M, Kulkarni SB. Mucosal-sparing augmented non-transected anastomotic (MsANTA) urethroplasty: a step forward in ANTA urethroplasty. BJU Int. 2022;130(1):133-136. doi:10.1111/bju.15734.
-
Marks P, Dahlem R, Janisch F, et al. Mucomucosal anastomotic non-transecting augmentation (MANTA) urethroplasty: a ventral modification for obliterative strictures. BJU Int. 2023;132(4):444-451. doi:10.1111/bju.16112.
-
European Association of Urology. EAU Guidelines on Urethral Strictures: disease management in males. 2026. Current guideline.
-
European Association of Urology. EAU Guidelines on Urethral Strictures: perioperative care of urethral surgery. 2026. Current guideline.
-
Baudry A, Schirmann A, Guillot-Tantay C, et al. "Non-transecting anastomotic augmented uretroplasty with dorsal onlay buccal graft for the treatment of bulbous urethral strictures: Results and complications." Research Square [preprint]. 2024. doi:10.21203/rs.3.rs-4960446/v1
-
Andrich DE, Mundy AR. "Non-transecting anastomotic bulbar urethroplasty: a preliminary report." BJU Int. 2012;109(7):1090-1094. doi:10.1111/j.1464-410X.2011.10508.x
-
Wessells H, Morey A, Souter L, et al. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
-
European Association of Urology. "EAU Guidelines on Urethral Strictures: Follow Up." 2026. Current guideline.
-
Nilsen OJ, Holm HV, Ekerhult TO, et al. "To Transect or Not Transect: Results from the Scandinavian Urethroplasty Study, A Multicentre Randomised Study of Bulbar Urethroplasty Comparing Excision and Primary Anastomosis Versus Buccal Mucosal Grafting." Eur Urol. 2022;81(4):375-382. doi:10.1016/j.eururo.2021.12.017.