Orandi Flap (Longitudinal Ventral Penile Skin Flap)
The Orandi flap (longitudinal ventral penile skin island flap) is an early pedicled penile skin flap for urethral reconstruction, described by Ahmad Orandi in 1968.[1] It is a vascularized island of penile skin on a dartos fascia pedicle, used for single-stage urethroplasty, and it influenced later penile skin-flap designs. Barbagli and colleagues reported success in 10 of 12 patients (83.3%) after the dorsal Orandi modification.[2] Srivastava and colleagues reported one-year primary success of 85% to 93.3% across three different preputial or penile flap groups.[5] Greenwell, Venn and Mundy called the Orandi procedure the "gold standard" for patch urethroplasty of an uncomplicated penile urethral stricture in 1999.[3]
For the transverse / circular variants, see McAninch Transverse Circular Penile Skin Flap. For the broader penile / preputial flap anatomy, see Pedicled Penile / Preputial Skin Flap. For graft alternatives, see Dorsal Onlay OMG Urethroplasty.
Historical Significance and Evolution
The original Orandi technique (1968)
Ahmad Orandi described a one-stage urethroplasty using a longitudinally oriented island of ventral penile skin, raised on a pedicle of dartos fascia, and transposed as a ventral onlay patch to augment the strictured urethra.[1][6] The technique made several contributions:
- It was an early pedicled island-flap technique for adult stricture reconstruction.
- It showed that dartos fascia can serve as a vascular pedicle, carrying the subdermal vascular plexus to the skin island.
- It was an early example of single-stage substitution urethroplasty, in which the urethra is reconstructed in one operation instead of two.
- It showed that hairless penile skin can serve as a urethral substitute.
See also the History of Urethral Surgery.
Subsequent developments
The Orandi flap directly inspired the next generation of penile skin flap techniques:
- Quartey 1983. Extended the concept to a transverse distal penile or preputial island flap supplied by the superficial external pudendal vessels, which in the original report reached from the meatus to the prostatic urethra.[7]
- McAninch 1993. Developed the circular fasciocutaneous flap, a hairless distal penile flap that uses Buck's fascia as its vascular conduit and provides up to 15 cm of length.[8]
- Srivastava 2012. Described the circumpenile flap for circumcised patients, using remaining penile shaft skin as a dorsal onlay flap.[5]
- Barbagli / Kulkarni 2019. Modified the Orandi flap to a dorsal onlay configuration, intended to reduce sacculation or diverticulum formation of the classic ventral placement.[2]
Anatomy and Vascular Basis
Dartos fascia — the universal penile flap pedicle
All penile skin flaps are fundamentally based on the dartos fascia, which Joshi, Bandini, and Kulkarni (2022) described as "the winner" among all pedicles in genitourinary reconstruction.[6]
- Dartos fascia lies between the penile skin and Buck's fascia.
- It contains a rich subdermal vascular plexus fed by branches of the external pudendal arteries.
- The dartos is continuous and highly elastic, but extensive mobilization should preserve its vascular supply; prior intervention or vascular compromise warrants assessment of the proposed skin island and pedicle.[28]
- When a skin island is raised on a dartos pedicle, the pedicle maintains perfusion through the subdermal plexus, the fundamental Orandi flap principle.[6]
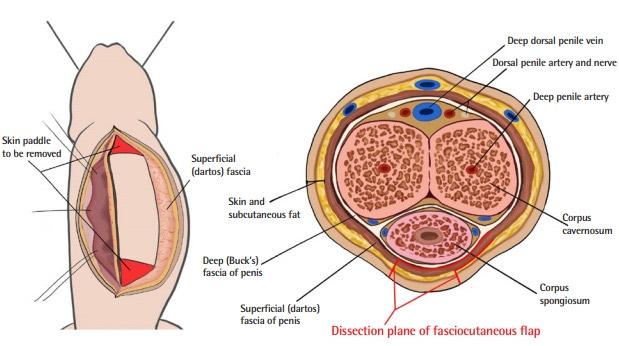
Flap elevation in a modified (tubed) Orandi urethroplasty: after the contralateral incision, a 2.5 × 6 cm skin paddle is raised with the superficial (dartos) fascia left intact as the pedicle, and the parts to be removed are marked in red; the transverse section shows the dissection plane of the fasciocutaneous flap (red line) superficial to Buck's fascia. From Heo JW, et al. Arch Plast Surg. 2020;47(6):613-618, Fig. 2 (CC BY-NC 4.0).[22]
Flap dimensions
- Orientation. Longitudinal (along the long axis of the penis); the defining feature distinguishing the Orandi flap from the transverse Quartey and circular McAninch flaps.
- Width. Typically 1.5–2.5 cm (sufficient for onlay augmentation).
- Length. Up to 6–8 cm, limited by the longitudinal dimension of the penile shaft skin. Circular flaps can reach up to 15 cm.[2][6][8]
- Skin source. Ventral penile shaft skin (classic Orandi) or lateral or dorsolateral penile skin (modifications).
Surgical Technique — Classic Ventral Onlay
Step 1 — Positioning and exposure. Supine or lithotomy according to stricture location; identify the strictured segment by palpation, urethral sound, or urethrography. With the penis on stretch, make a longitudinal ventral penile incision over the stricture, just lateral to the corpus spongiosum, extending to its lateral border.[28]
Step 2 — Flap design. Mark a longitudinal island of hairless ventral penile skin parallel to the shaft, inspecting the raphe and proximal shaft before harvest.[25][27] Width is typically 1.5–2.5 cm; length matches the stricture (up to 6–8 cm).
Step 3 — Flap harvest. Skin island incised circumferentially. Dissection deep to the skin but superficial to Buck's fascia, preserving the dartos fascia attached to the deep surface. The island is dissected from medial to lateral off Buck's fascia, leaving a lateral dartos pedicle attached to its deep surface.[27] Pedicle developed with sufficient length to allow tension-free reach to the strictured segment.
Step 4 — Urethrotomy. In the classic Orandi repair, open the urethra laterally opposite the initial skin incision, extending proximally and distally to healthy mucosa; inspect the lumen and spongiofibrosis.[28] The thinner lateral spongiosum may lessen pedicle tension. Later modifications have used a ventral urethrotomy.[29] The margins can be oversewn with a running locking absorbable stitch for hemostasis, as Orandi described.[1][21]
Step 5 — Flap placement (ventral onlay). Skin island rotated on its dartos pedicle and laid over the ventral urethrotomy. Suture one flap edge to the urethrotomy with absorbable suture (5-0 or 6-0 PDS or Vicryl), place the urethral catheter, then suture the opposite edge and apices over it.[28] Skin surface of the flap faces the urethral lumen (epithelial side inward). Dartos pedicle covers the external surface.
Step 6 — Closure and catheterization. Assess the donor defect for tension-free closure; Goel et al. described scrotal coverage when primary closure risked tension in a 10-man modified Orandi series, with meatal retraction in 2 men.[29] Close penile skin over the 16–18 Fr catheter placed during flap anastomosis. Catheterization commonly lasts 2–3 weeks; the EAU recommends urethrography before removal , using pericatheter RUG, RUG, or VCUG.[30] For a persistent significant leak, maintain or reinsert the catheter and repeat imaging after one week.[30]
Barbagli / Kulkarni Modification — Dorsal Onlay (2019)
Barbagli, Joshi, and Kulkarni 2019 described a modification, repositioning the longitudinal penile skin flap as a dorsal onlay rather than the traditional ventral onlay. The modification was designed to provide dorsal support and reduce sacculation.[2]
Modified technique
- Midline ventral penile incision.
- Urethra fully dissected from the corpora cavernosa (circumferential mobilization).
- Urethra opened longitudinally along its dorsal surface.
- Longitudinal penile skin island on the dartos pedicle harvested from the ventral penile skin (same as classic Orandi).
- Skin island moved over the corpora cavernosa to the dorsal surface.
- Opened urethra rotated and sutured over the penile skin flap; the flap now sits dorsally, supported by the corpora cavernosa.
Results
| Parameter | Result |
|---|---|
| Number of patients | 12 |
| Success rate | 83.3% (10/12) |
| Failures | 2 |
| Operating time | 60 min |
| Fistula | 0% |
| Urethral diverticulum | 0% |
No fistula or diverticulum was observed among 12 patients.
Dorsal vs. Ventral Onlay — The Sacculation Problem
The main clinical distinction between dorsal and ventral flap placement is the risk of pseudo-diverticulum or sacculation with postvoid dribbling. Bhandari, Dubey and Verma 2001 examined it in a small nonrandomized comparison of 40 patients with recurrent pendulous or bulbar strictures, treated with longitudinal penile or circumpenile flaps.[4]
| Parameter | Ventral Onlay (n = 21) | Dorsal Onlay (n = 19) | p value |
|---|---|---|---|
| Stricture recurrence | 3 patients reported; the abstract gives 24%, which does not match 3/21 | 2/19 (11%) | > 0.05 (NS) |
| Pseudo-diverticulum / sacculation | 29% (6/21) | 0% (0/19) | 0.01 |
| Postvoid dribbling | Present in sacculation cases | None | — |
| Urethrocutaneous fistula | 1 case | 0 | — |
Why ventral onlay causes sacculation
A ventral flap lacks the rigid support of the corpora cavernosa. The proposed mechanism is that intraluminal pressure during voiding balloons the unsupported patch outward, forming a pseudo-diverticulum that traps urine. In the Bhandari series, sacculation or pseudo-diverticulum with postvoid dribbling occurred in 6 of 21 ventral onlays and 0 of 19 dorsal onlays.[4]
Why dorsal support may reduce sacculation
When the flap is placed dorsally, it is supported by the rigid tunica albuginea of the corpora cavernosa, providing a mechanical backstop that may limit outward ballooning. Dorsal graft placement is based on a similar rationale.[2][4]
Clinical Outcomes
| Study | n | Flap type | Configuration | Stricture Length | Success | Follow-up | Key Findings |
|---|---|---|---|---|---|---|---|
| Barbagli / Kulkarni 2019[2] | 12 | Orandi longitudinal | Dorsal onlay | penile | 83.3% | — | 0% fistula, 0% diverticulum; 60-min OR time |
| Schulte-Baukloh 2004[26] | 202 | Raatzsch-modified Orandi | One-stage pedicled repair | — | 128/202 (63.4%) had good or improved outcomes without further surgery; penile subgroup 71.8% | Mean 46.2 mo (range 2–156) | 24.3% complications; different modification and endpoint |
| Bhandari 2001[4] | 40 | Longitudinal / circumpenile | 19 dorsal, 21 ventral | pendulous / bulbar | No significant recurrence difference; VO count/percentage inconsistent in abstract | Median 27.5 mo | Sacculation 29% VO vs 0% DO (p = 0.01) |
| Srivastava 2012[5] | 144 | Preputial DOF (60), TF (54), circumpenile DOF (30) | Dorsal onlay or tubularized | pendular / bulbar | Primary success: 85–93.3% (1-yr); 75–86.7% (3-yr) across three groups | Mean 40.1 mo | TF had a higher failure rate than DOF; circumpenile flap effective in circumcised patients (retrospective) |
| Mathur 2014[11] | 58 | Preputial flap (circumcised excluded) | Onlay | median 4.85 cm | 81% | 42 mo | Diabetes (RR 5.21) and smoking (RR 4.19) predict failure |
| Dubey 2007 alternation-assigned comparison (flap arm)[10] | 28 | Longitudinal (5) or circumpenile (23) penile skin flap | Dorsal onlay | Mean 6 cm (range 4–12; anterior) | 24/28 without recurrence requiring retreatment | Median 24.2 mo | Higher penile morbidity than BMG; troublesome postvoid dribbling in 9/28; 18/28 would recommend at six months |
| Fuchs 2018 (flap group)[12] | 87 | Penile skin flap | various | median 4.5 cm (all 403 complex reconstructions) | 78.2% | median 50.7 mo (all 403 complex reconstructions) | Flap use declining; comparable to BMG (78.5%); PU had higher observed success (94.8%); nonrandomized selection |
| de la Rosette 1991[13] | 50 | Pedicled island flap | various | complicated | 68% | — | 20% fistula; 32% recurrence; worse outcomes with ≥ 3 prior urethrotomies |
| Greenwell / Mundy 1999[3] | 79 | Various incl. Orandi | Patch / circumferential | bulbar / penile | — | — | Orandi declared "gold standard" for penile patch urethroplasty; 2-stage better for circumferential |
Combination Technique — Orandi Flap + Dorsal BMG
For narrow penile strictures, combining a dorsal BMG with a ventral Orandi flap has been described as a single-stage alternative to staged urethroplasty. Karapanos 2024 described this combined approach with preservation of the native urethral plate and corpus spongiosum:[9]
Technique
- Dorsal onlay BMG quilted to the corpora cavernosa.
- Longitudinal ventral penile skin flap (Orandi-type) transposed ventrally.
- The flap is sutured to the scarred native urethral mucosa on one side and to the BMG on the other, forming a neourethra of triangular cross-section.
- The preserved corpus spongiosum is wrapped around the flap ventrally for reinforcement.
Results (12 patients, median 38-mo follow-up)
- Success was 91.7% (11 of 12).
- No sacculation or diverticula were observed.
- Three transient fistulas healed with prolonged urinary diversion.
- Postvoid dribbling occurred in 5 of 12 patients (41.7%) despite the absence of sacculation.
- Median stricture length was 5 cm (IQR 3.8–7) and median operating time 205 min.
Related combinations have been described. Iselin and Webster 1999 combined dorsal onlay penile skin grafts with an Orandi flap in 4 of 29 bulbar strictures that extended significantly into the penile urethra.[14] Morey 2001 used dorsal grafts to augment or replace an inadequate urethral plate in four of 37 transverse penile island flap onlays (three buccal grafts and one cadaveric dermal graft); all four voided without further instrumentation at reported follow-up of six months to three years.[15] A 2025 case report combined BMG with a Q-flap.[20]
Comparison of Penile Skin Flap Types
| Feature | Orandi (Longitudinal) | Quartey (Transverse Preputial) | McAninch (Circular) | Circumpenile (Srivastava) |
|---|---|---|---|---|
| Year described | 1968[1] | 1983[7] | 1993[8] | 2012[5] |
| Orientation | Longitudinal | Transverse | Circumferential | Circumferential |
| Pedicle | Dartos fascia | Superficial external pudendal vessels | Buck's fascia as vascular conduit (McAninch 1993) | Dartos fascia |
| Maximum length | 6–8 cm | Meatus to prostatic urethra in the original report | Up to 15 cm | variable |
| Requires prepuce | No | Distal penile or preputial skin | No | No (designed for circumcised) |
| Technical complexity | Simplest | Moderate | Most complex | Moderate |
| Operative time | 60 min (Barbagli dorsal, n = 12)[2] | — | — | — |
| Reported use | Penile stricture repair with a longitudinal penile skin island[2] | Transverse distal penile or preputial island described to reach from the meatus to the prostatic urethra[7] | Circular distal penile island in complex anterior strictures[8] | Circumpenile dorsal onlay in selected circumcised patients[5] |
Advantages
- Technical simplicity. Barbagli reported a 60-min operation in a small penile-stricture cohort.[2]
- No prepuce required. The Orandi flap uses penile shaft skin and can be performed in circumcised patients when sufficient healthy skin remains. Quartey's original transverse island also permitted distal penile skin as an alternative to prepuce.[2][5][7]
- Reliable dartos pedicle. Consistent vascularity.[6]
- Versatility. Ventral onlay (classic), dorsal onlay (Barbagli modification), or combined with dorsal BMG for complex strictures.[2][4][9]
- Penile urethra. Greenwell, Venn and Mundy 1999 stated that "for a patch urethroplasty of an uncomplicated stricture in the penile urethra, the Orandi procedure remains the 'gold standard'".[3]
Limitations
- Limited length (6–8 cm). Longitudinal orientation restricts the flap to shorter strictures. McAninch described circular flap reconstruction in ten patients with complex strictures 8–21 cm long; the 18- and 21-cm defects required supplemental grafts.[6][8]
- Sacculation with ventral placement. In a 40-man comparison of longitudinal penile/circumpenile flaps, pseudo-diverticulum and/or sacculation with postvoid dribbling occurred in 6/21 ventral-onlay patients (29%) and 0/19 dorsal-onlay patients.[4]
- Lichen sclerosus. The AUA guideline states that surgeons should not use genital skin for reconstruction in proven lichen sclerosus stricture .[16] Oral mucosa is preferred.[16][17][18]
- Requires suitable penile donor skin. An Orandi flap needs sufficient healthy penile shaft skin and a viable dartos pedicle.[6] Mathur’s cited cohort used a different, preputial flap and excluded circumcised patients.[11] The EAU recommends flaps for a poorly vascularized urethral bed .[25]
- Hair-bearing skin risk. AUA Clinical Principle: surgeons should not use hair-bearing skin for substitution urethroplasty. Care to harvest only hairless distal penile skin.[16]
- Declining use. In a single tertiary center's 2007-2017 series, penile skin flaps made up 21.6% of complex anterior reconstructions and were used less often over time.[12]
Predictors of Failure
| Predictor | Hazard / Risk Ratio | Source |
|---|---|---|
| Smoking | HR 4.0 (95% CI 1.2–12.9) | Whitson / McAninch 2008[19] |
| Smoking | RR 4.19 (CI 1.54–45.0) | Mathur 2014[11] |
| History of hypospadias repair | HR 4.4 (95% CI 1.3–14.6) | Whitson / McAninch 2008[19] |
| Stricture length 7–10 cm | HR 7.0 (95% CI 1.4–34.7) | Whitson / McAninch 2008[19] |
| Diabetes mellitus | RR 5.21 (CI 2.31–64.68) | Mathur 2014[11] |
| Panurethral stricture | RR 2.73 | Mathur 2014[11] |
| Previous urethroplasty | RR 2.4 | Mathur 2014[11] |
| Severe periurethral fibrosis | RR 2.37 | Mathur 2014[11] |
| ≥3 prior urethrotomies | highest recurrence proportion | de la Rosette 1991[13] |
Dorsal Penile Skin Flap vs. BMG
Dubey's 2007 prospective comparison assigned 55 patients by alternation to dorsal-onlay BMG (27) or penile skin flap (28). The flap arm contained five longitudinal and 23 circumpenile flaps; patients with lichen sclerosus, unhealthy penile skin, oral mucosal pathology, prior urethroplasty, or more than one prior dilation or urethrotomy were excluded.[10]
- Recurrence requiring retreatment. Three of 27 BMG patients and four of 28 flap patients recurred (p > 0.05); median follow-up was 22.6 and 24.2 months, respectively.[10]
- Operating time. 162 min for BMG versus 224 min for the flap (p = 0.001).
- Morbidity. In the flap group, 6 of 28 patients (21%) had superficial penile skin necrosis, 1 needed skin grafting and 2 (7%) had penile torsion. The BMG group had minor morbidity in 25.6%, resolved by 4 weeks.
- Postvoid dribbling. Nine patients in the flap arm and four in the BMG arm reported troublesome postvoid dribbling.[10]
- Recommendation to another patient. At six months, 24/27 BMG patients (88.9%) and 18/28 flap patients (64.3%) said they would recommend the procedure.[10]
A pedicled flap carries its own blood supply, which is the usual rationale for choosing it in scarred, poorly vascularized urethral beds where a free graft might not take (failed prior urethroplasty, extensive spongiofibrosis). This is reasoning from flap physiology and expert teaching; no comparative data are cited for it.[6] If penile donor skin or its pedicle has been irradiated, assess tissue quality and vascular supply before flap harvest.[28]
Current Role and Guideline Context
AUA Guideline 2023[16]
- Surgeons may reconstruct long multi-segment strictures with one-stage or multi-stage techniques using oral mucosal grafts, penile fasciocutaneous flaps, or a combination .[16]
- Surgeons should use oral mucosa as the first choice when using grafts .[16]
- Surgeons should not use genital skin for reconstruction in lichen sclerosus-proven stricture .[16]
- Surgeons should not use hair-bearing skin for substitution urethroplasty .[16]
Contemporary practice trends
The EAU 2026 guideline recommends a graft over a flap when both are equally indicated .[25] A 2023 systematic review of single-stage augmentation urethroplasty found no significant overall success or postvoid-dribbling difference between oral mucosa grafts and penile skin flaps; larger and longer-followed study subgroups favored oral mucosa.[24]
Fuchs 2018 documented the evolving landscape over a decade:[12]
- BMG accounted for 61.3% of complex reconstructions and its share stayed stable
- Penile skin flaps accounted for 21.6% and were used less often over time
- Perineal urethrostomy use increased (4.3% to 38.7%, p = 0.01)
- Observed success (no further operative management): PU 94.8%, BMG 78.5%, skin flap 78.2% (p = 0.003)[12]
Despite the decline, penile skin flaps remain an option where oral mucosa is unavailable (for example, dyskeratotic oral changes from gutkha, tobacco and betel-nut use, per Mathur), in patients with depleted oral donor sites, and in complex strictures needing vascularized tissue.[6][11]
Special Considerations
Circumcised patients
The classic Orandi flap can be performed in circumcised patients using remaining penile shaft skin. Srivastava 2012 studied the circumpenile flap in circumcised patients, reporting 93.3% success at 1 yr and 86.7% at 3 yr.[5]
Regional considerations
In South Asia, gutkha, tobacco, pan masala and betel nut consumption is associated with dyskeratotic oral changes, and buccal mucosa may be unsuitable for grafting. Penile and preputial skin flaps remain an alternative there. Mathur 2014, whose series used preputial flaps, wrote: "We prefer this technique in this part of the world where buccal mucosa cannot be used because of dyskeratotic changes."[11]
Follow-Up
Offer routine follow-up for at least one year after urethroplasty . For penile flap repairs, the EAU standard-risk proposal assesses uroflowmetry, patient-reported outcomes including sexual function, and anatomy at 3, 12, and 24 months, with further review at five years and longer follow-up when indicated; investigate recurrent symptoms or declining flow.[31]
Key Takeaways
The Orandi longitudinal ventral penile skin island flap is an early pedicled flap urethroplasty, described in 1968. Its reported strengths are a short operation (60 min in the Barbagli dorsal modification), dartos-based vascularity, and use in circumcised patients and those with unsuitable oral mucosa.[1][2][5][11] The Barbagli dorsal onlay modification (2019) places the flap on the corpora for dorsal support. Small series found less sacculation with dorsal placement.[2][4] Oral mucosa is commonly used for substitution urethroplasty. In the 2007 alternation-assigned dorsal-onlay comparison, BMG had less penile morbidity; 24/27 BMG versus 18/28 flap patients would recommend the procedure, while recurrence requiring retreatment occurred in 3/27 versus 4/28.[10] A separate 2019 randomized trial of long penile strictures reported success in 39/42 dorsolateral BMG patients and 36/42 ventral penile-flap patients (p = 0.5) at intermediate follow-up; the flap arm pooled Orandi, McAninch, and Q designs. Neither trial estimates an Orandi-specific treatment effect.[10][23] The Orandi flap is still used in complex strictures, depleted oral donor sites, and populations where oral mucosa is unavailable.[6][10][11][12] Genital skin is not used in lichen sclerosus.[16][17]
Videos
References
-
Orandi A. One-stage urethroplasty. Br J Urol. 1968;40(6):717-9. doi:10.1111/j.1464-410x.1968.tb11872.x. PMID: 4883846.
-
Barbagli G, Joshi PM, Kulkarni SB, et al. Penile urethroplasty using Orandi's dorsal skin flap: a new technique. BJU Int. 2019;124(5):892-896. doi:10.1111/bju.14881.
-
Greenwell TJ, Venn SN, Mundy AR. Changing practice in anterior urethroplasty. BJU Int. 1999;83(6):631-5. doi:10.1046/j.1464-410x.1999.00010.x.
-
Bhandari M, Dubey D, Verma BS. Dorsal or ventral placement of the preputial / penile skin onlay flap for anterior urethral strictures: does it make a difference? BJU Int. 2001;88(1):39-43. doi:10.1046/j.1464-410x.2001.02257.x.
-
Srivastava A, Vashishtha S, Singh UP, et al. Preputial / penile skin flap, as a dorsal onlay or tubularized flap: a versatile substitute for complex anterior urethral stricture. BJU Int. 2012;110(11 Pt C):E1101-8. doi:10.1111/j.1464-410X.2012.11296.x.
-
Joshi PM, Bandini M, Kulkarni SB. Common flaps in genitourinary reconstruction. Urol Clin North Am. 2022;49(3):361-369. doi:10.1016/j.ucl.2022.04.001.
-
Quartey JK. One-stage penile / preputial cutaneous island flap urethroplasty for urethral stricture: a preliminary report. J Urol. 1983;129(2):284-7. doi:10.1016/s0022-5347(17)52051-0.
-
McAninch JW. Reconstruction of extensive urethral strictures: circular fasciocutaneous penile flap. J Urol. 1993;149(3):488-91. doi:10.1016/s0022-5347(17)36125-6.
-
Karapanos L, Halbe L, Storz E, et al. Preservation of the native urethral plate and corpus spongiosum combined with buccal mucosa graft plus Orandi's penile skin flap as an alternative to staged urethroplasty for narrow penile strictures. Int J Urol. 2024;31(10):1095-1101. doi:10.1111/iju.15521.
-
Dubey D, Vijjan V, Kapoor R, et al. Dorsal onlay buccal mucosa versus penile skin flap urethroplasty for anterior urethral strictures: results from a randomized prospective trial. J Urol. 2007;178(6):2466-9. doi:10.1016/j.juro.2007.08.010.
-
Mathur RK, Nagar M, Mathur R, et al. Single-stage preputial skin flap urethroplasty for long-segment urethral strictures: evaluation and determinants of success. BJU Int. 2014;113(1):120-6. doi:10.1111/bju.12361.
-
Fuchs JS, Shakir N, McKibben MJ, et al. Changing trends in reconstruction of complex anterior urethral strictures: from skin flap to perineal urethrostomy. Urology. 2018;122:169-173. doi:10.1016/j.urology.2018.08.009.
-
de la Rosette JJ, de Vries JD, Lock MT, Debruyne FM. Urethroplasty using the pedicled island flap technique in complicated urethral strictures. J Urol. 1991;146(1):40-2. doi:10.1016/s0022-5347(17)37709-1.
-
Iselin CE, Webster GD. Dorsal onlay graft urethroplasty for repair of bulbar urethral stricture. J Urol. 1999;161(3):815-8. doi:10.1016/s0022-5347(01)61779-8. PMID: 10022691.
-
Morey AF. Urethral plate salvage with dorsal graft promotes successful penile flap onlay reconstruction of severe pendulous strictures. J Urol. 2001;166(4):1376-8. doi:10.1016/s0022-5347(05)65773-4. PMID: 11547078.
-
Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
-
Stewart L, McCammon K, Metro M, Virasoro R. SIU/ICUD consultation on urethral strictures: anterior urethra — lichen sclerosus. Urology. 2014;83(3 Suppl):S27-30. doi:10.1016/j.urology.2013.09.013.
-
Chung ASJ, Suarez OA. Current treatment of lichen sclerosus and stricture. World J Urol. 2020;38(12):3061-3067. doi:10.1007/s00345-019-03030-z.
-
Whitson JM, McAninch JW, Elliott SP, Alsikafi NF. Long-term efficacy of distal penile circular fasciocutaneous flaps for single stage reconstruction of complex anterior urethral stricture disease. J Urol. 2008;179(6):2259-64. doi:10.1016/j.juro.2008.01.087.
-
Anadani A, Obaidin A, Badawi B, Lutfi MY. One-stage urethroplasty using a combination of buccal mucosa graft and Q penile skin flap for a complicated urethral stricture: a challenging case report. Medicine (Baltimore). 2025;104(12):e41888. doi:10.1097/MD.0000000000041888.
-
Myers JB, Morey AF. Anterior Urethral Reconstruction: Penile Island Flaps. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:473–479.
-
Heo JW, Hong WT, Kim YH, Yang CE, Kim J, Kim SW. Urethroplasty of extensive penile urethral strictures with a longitudinal ventral tubed flap of penile skin (modified Orandi urethroplasty): 20 years of follow-up of two cases. Arch Plast Surg. 2020;47(6):613-618. doi:10.5999/aps.2019.00941.
-
Ali AI, Hamid AA, Abdel-Rassoul MA, et al. "Buccal mucosal graft versus penile skin flap urethroplasty for long segment penile urethral stricture: a prospective randomized study." Cent European J Urol. 2019;72(2):191-197. doi:10.5173/ceju.2019.1899
-
Song L, Zhang R, Lu C, Chen Y. "Factors to consider in augmentation urethroplasty with oral mucosa graft or penile skin flap for anterior urethral stricture: a systematic review and meta-analysis." Eur Urol Open Sci. 2023;50:113-122. doi:10.1016/j.euros.2023.02.010
-
Lumen N, Campos-Juanatey F, Dimitropoulos K, et al. "EAU Guidelines on Urethral Strictures: Tissue Transfer." EAU Guidelines. EAU Guidelines Office; Arnhem, Netherlands; 2026. ISBN 978-94-92761-32-5. Guideline
-
Schulte-Baukloh H, Stürzebecher B, Blömers F, Fleck H, Knispel HH. "Orandi one-stage urethroplasty using the subcutaneous pedicle graft modification of Raatzsch--long-term results." Scand J Urol Nephrol. 2004;38(4):321-325. doi:10.1080/00365590410028836
-
Bryk DJ, Yamaguchi Y, Zhao LC. "Tissue transfer techniques in reconstructive urology." Korean J Urol. 2015;56(7):478-486. doi:10.4111/kju.2015.56.7.478
-
Shaw NM, Amend G, Breyer BN. "Genital flaps for anterior urethral reconstruction." Plast Aesthet Res. 2021;8:52. doi:10.20517/2347-9264.2021.53
-
Goel A, Kumar M, Singh M. "Orandi flap for penile urethral stricture: polishing the gold standard." Can Urol Assoc J. 2015;9(3-4):E160-E163. doi:10.5489/cuaj.2455
-
Lumen N, Campos-Juanatey F, Dimitropoulos K, et al. "EAU Guidelines on Urethral Strictures: Perioperative Care of Urethral Surgery." EAU Guidelines. EAU Guidelines Office; Arnhem, Netherlands; 2026. ISBN 978-94-92761-32-5. Guideline
-
Lumen N, Campos-Juanatey F, Dimitropoulos K, et al. "EAU Guidelines on Urethral Strictures: Follow Up." EAU Guidelines. 2026. Guideline