Preputial Spiral Graft Urethroplasty (PSGU)
Preputial spiral graft urethroplasty (PSGU) is a single-stage technique described in 2023 by Kulkarni, Joshi, Basile and Bandini for panurethral strictures, defined as anterior urethral strictures longer than 10 cm. A helicoidal harvest from a preputial skin cylinder spanning inner and outer prepuce yields one continuous graft. The initial report described lengths up to 20 cm; the later multicenter report describes grafts usually exceeding 25 cm.[1][2]
For the canonical free-graft framework, see Penile / Preputial Skin Graft and Buccal Mucosa Graft. For the related pedicled flap, see Quartey Flap and Pedicled Preputial Tube. For the alternative panurethral free-graft strategy, see Kulkarni One-Sided Dorsolateral BMG. For conventional flat inner-preputial and penile-skin free grafts, see the Flat Penile Skin / Inner Preputial Free Grafts section below.
Concept and Rationale
Panurethral strictures are often treated with two-stage procedures or with multiple buccal mucosa grafts (BMGs) harvested from both cheeks and sometimes the tongue. The authors propose that recurrence tends to occur where separate grafts meet.[2] The spiral harvest starts with a preputial skin cylinder from circumferential incisions about 5 cm apart, then cuts it helically into a continuous graft about 1.5–2 cm wide from a limited donor area.[1][2] A single graft avoids inter-graft joins and oral harvest. Whether it reduces recurrence compared with multiple oral grafts has not been demonstrated.
Surgical Technique
Based on the description by Kulkarni 2023:[1]
- Preoperative assessment. Examine the prepuce for active LS or skin lesions.[2] Retrograde and voiding cystourethrography and uroflowmetry (Qmax) characterize stricture length and severity. Intraoperative urethroscopy confirms stricture extent, especially proximally.[2] For penile involvement, counsel that adverse intraoperative findings may require conversion to staged repair .[11]
- Graft harvest. Make circumferential incisions about 5 cm apart, dissect the preputial skin cylinder superficial to dartos while preserving the preputial ring, then stretch it on a 30 mL syringe and cut a 1.5–2 cm-wide spiral graft.[2] The initial report described grafts up to 20 cm; mark the helix before cutting, remove attached dartos fascia and trim the graft to the measured defect.[1][2]
- Urethral exposure. Exposure is typically by the Kulkarni one-sided dorsal onlay technique: a perineal approach, penile invagination and one-sided urethral mobilization, which is intended to preserve the lateral blood supply.[3]
- Stricturotomy. Open the urethra dorsally at 12 o'clock along the stricture and into healthy proximal mucosa; open the meatus with a dorsal urethrotomy.[2]
- Graft placement. The spiral preputial graft is laid as a dorsal onlay over the entire length of the opened stricture and sutured to the urethral plate edges.
- Closure and catheter. Close in layers over a urethral catheter. In the reported technique, tubularize the urethra with a running watertight suture over a 14–20 Fr silicone catheter, which remains for four weeks.[2]
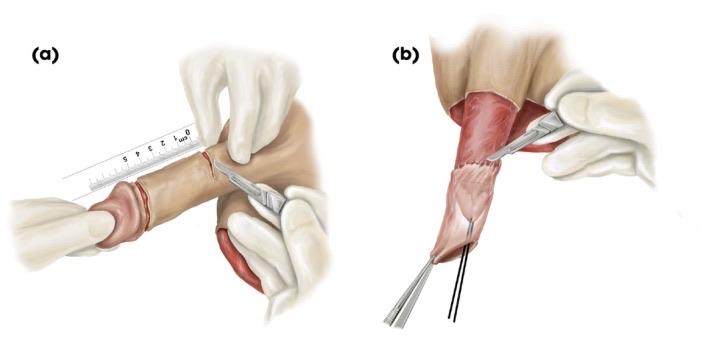
Preputial graft harvest: (a) subcoronal and preputial skin incisions; (b) the preputial cylinder is harvested while the dartos fascia is preserved. From Bandini M, et al. BJU Int. 2025;136(4):640-646, Fig. 1 (CC BY-NC).[2]
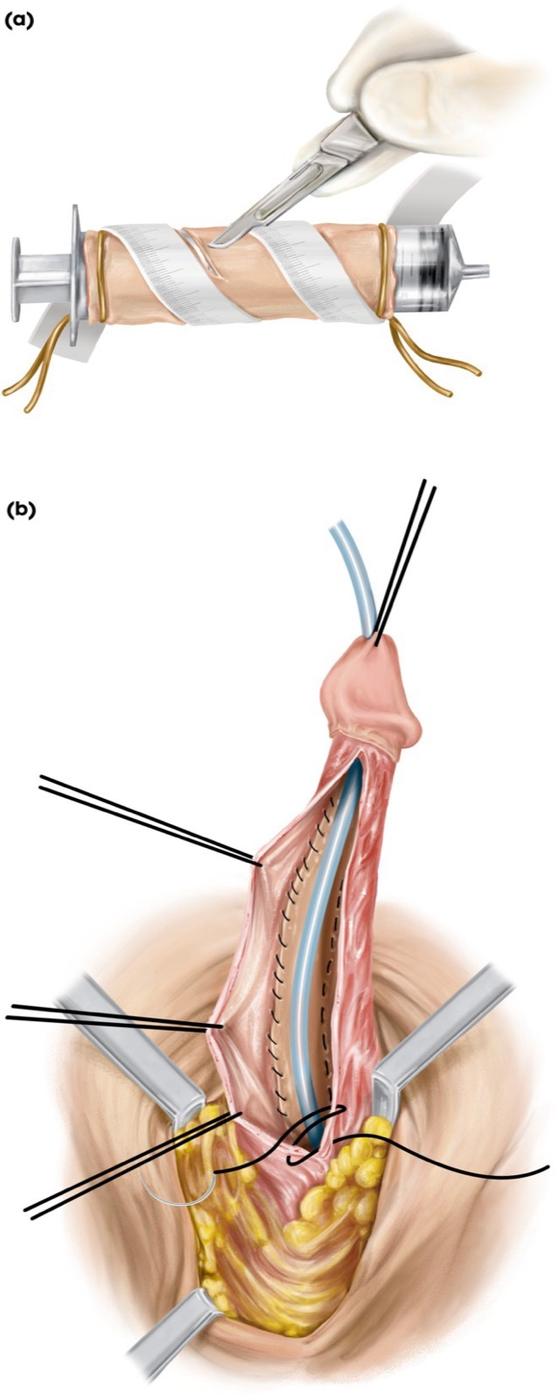
(a) The spiral graft is cut while the preputial cylinder is held on a 30 mL syringe and fixed with a tourniquet at each end. (b) The preputial spiral graft is placed as a dorsal onlay over the corpora and fixed to the native urethra. From Bandini M, et al. BJU Int. 2025;136(4):640-646, Fig. 2 (CC BY-NC).[2]
Indications
- Panurethral strictures (anterior urethral stricture > 10 cm).[1][2]
- Patients with an intact prepuce (uncircumcised).[2]
- Patients in whom buccal mucosa is unsuitable, for example oral dyskeratotic changes from tobacco / gutkha use, or limited oral mucosa from prior bilateral harvest.[4]
Prerequisites and Contraindications
- Intact foreskin is mandatory; circumcised patients are excluded.[2][4]
- LS-related urethral stricture. The AUA 2023 amendment recommends against genital skin in LS-proven strictures .[6] The multicenter PSGU series required absence of active LS but included eight men with LS as the stricture etiology.[2]
- Risk factors for failure of preputial skin flaps. Mathur's series of 58 preputial skin flap repairs identified diabetes (RR 5.21) and smoking (RR 4.19) as predictors of failure, with post-infective etiology, panurethral stricture, length above 70 mm, previous urethroplasty and severe periurethral fibrosis also associated with failure.[4]
Outcomes
| Study | N | Median Stricture Length | Follow-Up | Qmax Improvement | Recurrence Rate | Complications |
|---|---|---|---|---|---|---|
| Kulkarni 2023 (initial series)[1] | 20 | Not specified | 12 mo | 6.5 → 15.1 mL/s | 5% (1/20) | 6/20 patients had at least one complication within 30 days, including one grade IIIa |
| Bandini 2025 (multicenter)[2] | 114 | 16 cm | median 16 mo (IQR 7–24) | 4.5 mL/s (baseline n=106 without catheter) → 24 mL/s (p < 0.001) | 9.6% (11/114), urethrography-confirmed after symptoms with Qmax < 10 mL/s or recurrent UTI | 23% (26/114) had a complication within 30 days (mostly Clavien-Dindo I) |
The 2023 initial series appears to be included in the later 114-patient multicenter cohort.[1][2]
Findings from the largest multicenter series (114 patients across India, Colombia, Egypt, and Italy):[2]
- Median operative time 134 minutes (IQR 123–142).
- Median Qmax improved from 4.5 mL/s preoperatively (among 106 men without an indwelling catheter) to 24 mL/s at median 16-month follow-up (p < 0.001).[2]
- Success was defined as Qmax > 10 mL/s without symptoms.[2]
- Because the graft comes from the prepuce, no oral donor site is created, and with it no oral donor-site morbidity such as pain, numbness or restricted mouth opening.
- Preputial graft tissue lies close to the surgical field and is easily harvested, and a dorsolateral inner preputial graft series reports the procedure can be done under regional anesthesia.[5]
- Preputial tissue is an option where buccal mucosa quality is compromised by tobacco or betel-nut use.[4]
Comparison With Buccal Mucosa Graft
The AUA 2023 guideline amendment names oral mucosa as the first-choice graft for substitution urethroplasty .[6] A 2026 meta-analysis of 11 comparative studies (1,018 adults with anterior strictures) reported higher pooled success with penile skin grafts, but inconsistent success definitions, follow-up, surgical methods, and graft types limit application to PSGU.[12] PSGU is supported by observational cohorts. In a 2022 survey of GURS members (134 respondents), 90% preferred multiple BMGs over a combined graft and flap for panurethral strictures, before the multicenter PSGU data were published.[8]
Limitations and Current Evidence Gaps
- Follow-up. The largest series has a median follow-up of 16 months (IQR 7–24), and long-term data beyond 2 years are lacking.[2]
- Prepuce. An intact prepuce is required, which excludes circumcised patients.[2]
- Lichen sclerosus. For LS-proven urethral stricture, the AUA recommends against genital-skin reconstruction .[6] The PSGU cohort excluded active preputial LS but included eight men with LS as the stricture etiology.[6][2]
- Comparators. No randomized comparison of PSGU with single-stage or staged BMG urethroplasty has been reported for panurethral strictures.
- Experience. The technique was first described in 2023; in the 2025 multicenter series, 91/114 patients (79.8%) were treated at the Kulkarni Center and the remaining 23 across four other centers.[1][2]
Flat Penile Skin / Inner Preputial Free Grafts
Conventional flat penile skin and inner preputial free grafts are non-pedicled substitutes for the urethral plate, harvested as full-thickness strips and placed as onlay or inlay augmentation grafts. Buccal mucosa has largely replaced them in routine use (Buccal Mucosa Graft). Penile skin remains a free-graft option when oral harvest is unavailable, refused or exhausted by prior surgery.
Dorsolateral Inner Preputial Graft (DLIPG)
Tyagi and colleagues described dorsolateral substitution urethroplasty with an inner preputial graft (DLIPG). In a retrospective analysis of prospectively maintained data from 80 patients with anterior strictures (mean stricture length 65 mm), success was 69/80 (87%) at a mean follow-up of 48 months (range 30–66). Success was defined as a stable Qmax above 14 mL/s or calibration with a 16 Fr catheter.[5]
RCT Evidence: Penile Skin vs BMG
Two randomized studies compared conventional free penile skin grafts with BMG in anterior strictures; Alrefaey included 17/92 men with panurethral disease, but neither trial tested PSGU.[10][7] Their success definitions differed: PeeBuSt counted success if any of Qmax > 15 mL/s, 16 Fr calibration or 17 Fr cystoscope passage was met at 18 months, whereas Alrefaey required no voiding symptoms, RUG patency and no reintervention at 12 months.[10][7]
| Trial | Design | Success |
|---|---|---|
| Tyagi 2022 PeeBuSt[10] | 100 randomized; 95 analyzed | PSG 42/47 versus BMG 44/48 at 18 months (p = 0.70); powered for a large difference, not equivalence |
| Alrefaey 2025[7] | Superiority trial; 98 randomized, 92 analyzed | PSG 41/44 versus BMG 47/48 at 12 months (p = 0.346); baseline imbalances in stricture etiology and location |
PeeBuSt and Alrefaey did not test equivalence.[9] Dubey 2007 compared a penile skin flap with BMG (55 patients).[9] Oral mucosa remains the AUA first-choice graft.[6]
Contraindications
Lichen sclerosus. The AUA 2023 guideline amendment gives a Strong Recommendation (Grade B) against genital skin in LS-proven urethral strictures, citing very high long-term failure rates.[6]
Videos
References
1. Kulkarni SB, Joshi PM, Basile G, Bandini M. Novel single-stage preputial spiral graft for panurethral stricture: a step-by-step description of the technique. World J Urol. 2023;41(9):2459-2463. doi:10.1007/s00345-023-04514-9.
2. Bandini M, Joshi P, Bafna S, et al. Establishing the role of single-stage preputial spiral graft urethroplasty for panurethral stricture. BJU Int. 2025. doi:10.1111/bju.16796.
3. Takekawa K, Horiguchi A, Shinchi M, et al. One-sided dorsal onlay urethroplasty with penile invagination (Kulkarni urethroplasty) for complex anterior urethral strictures: a single-center experience. Int J Urol. 2025;32(6):749-755. doi:10.1111/iju.70048.
4. Mathur RK, Nagar M, Mathur R, et al. Single-stage preputial skin flap urethroplasty for long-segment urethral strictures: evaluation and determinants of success. BJU Int. 2014;113(1):120-126. doi:10.1111/bju.12361.
5. Tyagi S, Parmar K, Sharma A, et al. Dorsolateral inner preputial graft urethroplasty for anterior urethral strictures: long-term outcomes from a single tertiary care centre. World J Urol. 2021;39(9):3549-3554. doi:10.1007/s00345-021-03613-9.
6. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
7. Alrefaey A, Anwar MA, Abdelmagid ME, et al. Comparative outcomes of penile skin grafts versus buccal mucosal grafts in urethroplasty for the treatment of extensive anterior urethral strictures. Sci Rep. 2025;15(1):29508. doi:10.1038/s41598-025-14191-w.
8. Berg C, Singh A, Hu P, et al. Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons. Urology. 2024;191:139-143. doi:10.1016/j.urology.2024.06.019.
9. Dubey D, Vijjan V, Kapoor R, et al. Dorsal onlay buccal mucosa versus penile skin flap urethroplasty for anterior urethral strictures: results from a randomized prospective trial. J Urol. 2007;178(6):2466-9. doi:10.1016/j.juro.2007.08.010.
10. Tyagi S, Parmar KM, Singh SK, et al. 'Pee'BuSt Trial: a single-centre prospective randomized study comparing functional and anatomic outcomes after augmentation urethroplasty with penile skin graft versus buccal mucosa graft for anterior urethral stricture disease. World J Urol. 2022;40(2):475-481. doi:10.1007/s00345-021-03843-x.
11. European Association of Urology Urethral Strictures Guidelines Panel. "EAU Guidelines on Urethral Strictures: Disease Management in Males." EAU Guidelines. 2026. Full text.
12. Abbas SM, Farhan M, Khan A, et al. "Penile skin graft versus buccal mucosal graft for anterior urethral strictures in adult urethroplasty- a systematic review and meta-analysis." Int Urol Nephrol. 2026;58(6):1895-1910. doi:10.1007/s11255-025-04955-8