Primary Endoscopic Realignment (PER)
Primary endoscopic realignment (PER) is the early endoscopic placement of a transurethral catheter across a disrupted urethra in order to restore luminal continuity, most often in the setting of pelvic fracture urethral injury (PFUI) and, less frequently, anterior (bulbar) urethral injury from straddle trauma. PER has been described as an early alternative to SPT followed by delayed urethroplasty, or as an adjunct after initial SPT placement, in selected posterior and anterior injuries.[1][2][3] In partial injury, a stenting catheter may allow healing; in complete PFUI, realignment aims to correct the distraction defect, while any reduction in stenosis severity or need for reconstruction remains uncertain.[18][27]
For the injury-specific pathway, see Pelvic Fracture Urethral Injury (PFUI). Obliterative post-PFUI stenosis generally requires delayed anastomotic urethroplasty in an experienced center; abdominoperineal access is reserved for selected complex defects. Blind core-through and repeated cut-to-the-light procedures are not substitutes for urethroplasty.[7]
Indications
- Male posterior urethral disruption from PFUI in a hemodynamically stable patient, particularly partial injuries where retrograde catheter placement has failed.[4][5] Female PFUI follows a separate pathway: EAU 2026 recommends repair within seven days once stable , because early realignment has high stricture and fistula rates.[27]
- Anterior (bulbar) urethral injury from blunt straddle trauma, selected partial disruptions; comparative benefit is based mainly on observational evidence.[6]
- The WSES-AAST 2019 guidelines prefer immediate endoscopic realignment over immediate urethroplasty in hemodynamically stable patients with complete posterior urethral lesions and no other life-threatening injuries, and recommend an attempt at endoscopic realignment for blunt anterior urethral injury (GoR 1C).[5]
Relative contraindications / situations favoring SPT alone
- Hemodynamic instability or polytrauma requiring damage control.[5]
- Complete posterior urethral disruption in centers without endoscopic expertise. The AUA 2020 Urotrauma Guideline states that clinicians should perform SPT placement as the preferred initial management for most PFUI cases (Recommendation; Grade C).[4]
- The AUA 2023 Urethral Stricture Guideline Amendment states that repeated endoscopic maneuvers after PFUI (intermittent catheterization, blind "cut to the light" procedures) should be avoided because they are rarely successful.[7]
- Open realignment: ACS 2025 advises against it in PFUI.[1] EAU 2026 describes open realignment as possible but prefers endoscopy because open surgery has greater operative burden and blood loss.[1][27]
Approach Selection
Three principal techniques exist; the dual-endoscopic rendezvous is the main technique, with fluoroscopic and magnetic-catheter variants reserved for selected scenarios.[8][9][10][11]
| Approach | Setup | Strengths | Weaknesses |
|---|---|---|---|
| Retrograde-only | Retrograde cystoscopy with atraumatic, visually guided catheter/wire placement | Simplest; no SPT or antegrade access required | Low success in complete disruption; proximal stump obscured by hematoma[12] |
| Combined antegrade + retrograde (dual endoscopic) | Flexible scope through SPT + rigid/flexible scope retrograde; "light-to-light" rendezvous | Main technique for complete disruption; direct visualization of both stumps | Requires SPT, lithotomy, general anesthesia[8][9] |
| Fluoroscopic-guided (IR) | Antegrade + retrograde wires under fluoroscopy; supine | Avoids lithotomy and general anesthesia for a hemodynamically stable patient with complex pelvic fractures; concurrent pelvic embolization has been reported | No direct visualization; catheter-placement technical success was 13/15 (87%) in complete posterior disruptions and 12/13 (92%) in a separate, broader traumatic urethral injury cohort[1][10][13] |
| Magnetic catheter rendezvous | Coaxial magnetic sounds advanced antegradely + retrogradely; magnetic attraction crosses gap | Simple; no cystoscope required | Magnetic catheters not widely available; limited adoption[11] |
Surgical Technique — Dual Endoscopic (Combined Antegrade-Retrograde)
Prerequisite — suprapubic access
- An SPT (≥14 Fr Foley) is placed first, percutaneously under ultrasound or fluoroscopic guidance, or via open cystotomy. An 18-gauge spinal needle for bladder localization is helpful when the bladder is displaced by pelvic hematoma.[4][1]
- The suprapubic tract should be dilated to accommodate a flexible cystoscope (typically 15.5–16.5 Fr). Some surgeons mature the tract for several days before realignment; others dilate at the time of the procedure.[14]
Antegrade limb
- A flexible cystoscope is introduced through the suprapubic tract into the bladder.
- The scope is navigated through the bladder neck into the prostatic urethra to the proximal end of the disruption.
- In complete disruption, the proximal stump appears as a blind cavity filled with hematoma; copious irrigation clears clot and improves visualization.[8][9]
Retrograde limb
- A rigid or flexible cystoscope is advanced retrogradely from the meatus to the distal blind end of the bulbar or membranous urethra.
- Hematoma and disrupted spongiosum are inspected; irrigation is again used to improve visibility.[2]
Rendezvous and guidewire passage
- Rendezvous visualization. Identify the proximal and distal ends endoscopically to guide atraumatic wire passage.[8][9]
- A 0.035-inch hydrophilic guidewire is passed through the disruption, most commonly antegradely from the suprapubic tract through the prostatic urethra and out the meatus, establishing through-and-through wire access.[2][8]
- Forceful or blind wire passage is avoided; false passages into the rectum or periurethral tissues may complicate later urethroplasty.[2]
Catheter placement
- A Council-tip Foley catheter (16–18 Fr) is railroaded over the guidewire across the injury site; the end-hole accommodates the wire.[8]
- Inflate the balloon in the bladder, remove the wire, and confirm intravesical position by irrigation. Avoid traction on the balloon catheter because it can injure the remaining bladder-neck sphincter mechanism.[27]
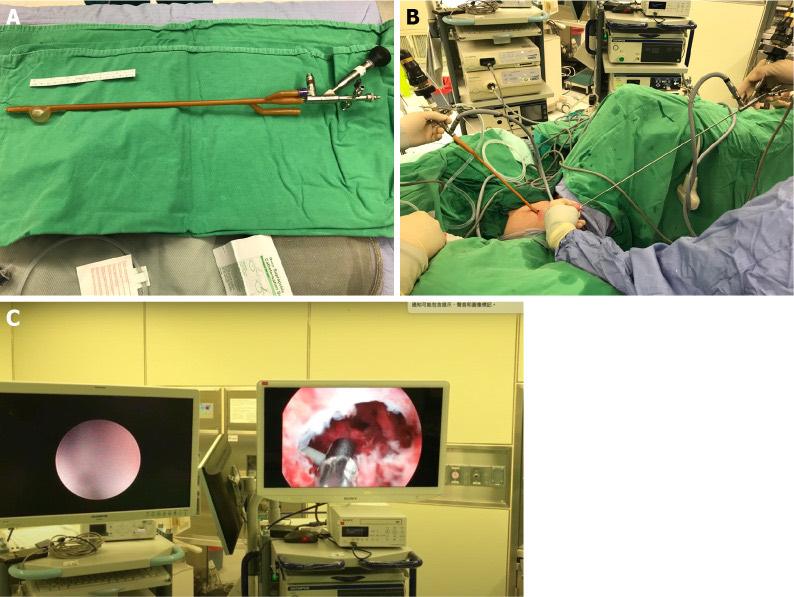
Primary endoscopic realignment in a pelvic-fracture case with bulbar urethral disruption: (A) the tip of a Foley catheter incised and a semi-rigid 4.5/6.5 Fr ureteroscope inserted through it; (B) simultaneous antegrade and retrograde endoscopy; (C) the antegrade guidewire grasped with forceps through a cystoscope and pulled out through the external urethral meatus. From Ho CJ, Yang MH. World J Clin Cases. 2022;10(3):1050-1055, Figure 2 (CC BY-NC 4.0).[25]
Fluoroscopic-Guided (IR) Variant
This variant is particularly useful when lithotomy positioning is impossible because of pelvic hardware, unstable fractures, or lower-extremity injury.[10]
- The patient remains supine; no lithotomy, no general anesthesia required.
- Through an existing suprapubic tract or a newly placed ultrasound-guided suprapubic sheath, an antegrade catheter and guidewire are advanced into the bladder and prostatic urethra under fluoroscopy. A simultaneous retrograde catheter and guidewire are advanced from the meatus.[10][26]
- If either guidewire crosses, a Foley can be advanced over it; when both fail to cross, an antegrade snare can capture the retrograde wire, establishing through-and-through access for Foley placement.[26]
- Technical success: Jeon achieved Foley placement in 13/15 patients (87%; mean procedure time 66 minutes), with concurrent pelvic embolization in 11/15.[10] Symptomatic stricture developed in 9/13 successfully realigned patients (69%) during follow-up.[10] Lee reported Foley placement in 12/13 (92%) and a mean procedure time of 20 minutes; 6/12 successfully realigned patients developed symptomatic stricture at a mean 4.3 months.[13]
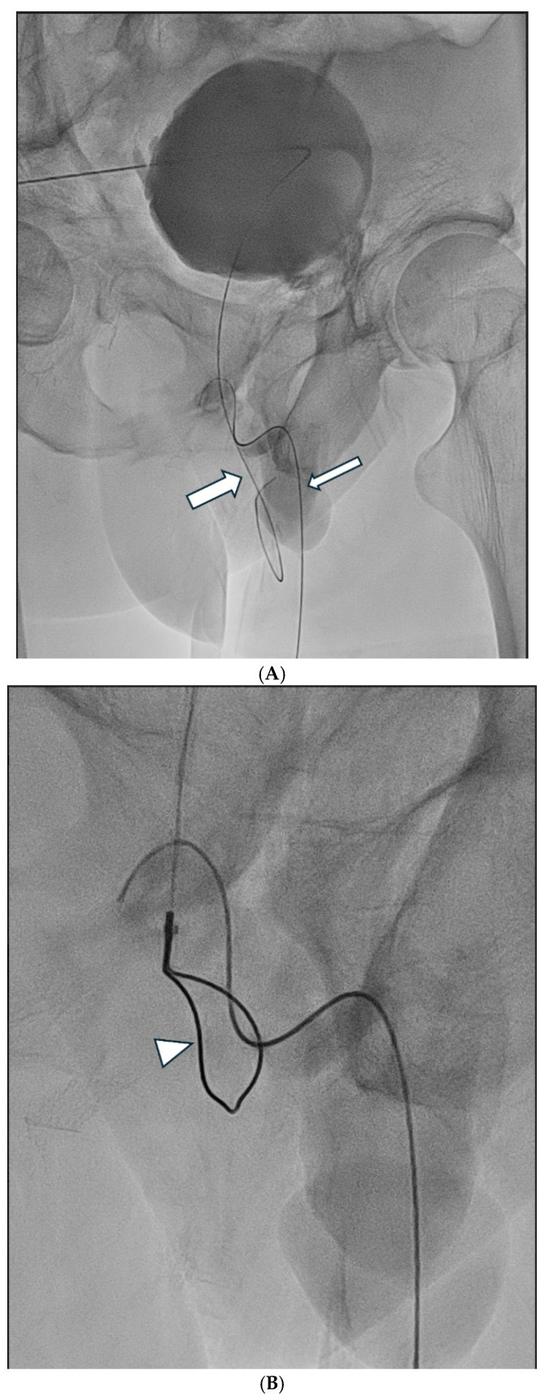
Interventional radiology-guided Foley placement in a 67-year-old man with traumatic membranous urethral disruption: (A) antegrade (thick arrow) and retrograde (thin arrow) guidewires fail to traverse the disrupted segment; (B) a 15 mm snare (arrowhead) introduced through the suprapubic tract captures the retrogradely advanced guidewire; (C) the guidewire is externalized, giving through-and-through access for Foley placement, with contrast extravasation at the membranous injury (black arrow). From Chung H, et al. J Clin Med. 2026;15(13):5096, Figure 3 (CC BY 4.0).[26]
Magnetic Catheter Rendezvous
Coaxial magnetic urethral catheters are introduced simultaneously antegradely (through the SPT) and retrogradely (through the meatus). The magnetic attraction between the two catheter tips guides them across the disrupted segment without endoscopic visualization. In Porter's original series, realignment was achieved in 11/13 patients (85%). Stricture developed in 5/10 with follow-up (50%) a mean 6.1 months after realignment; magnetic catheters have limited availability and adoption.[11]
Timing and Catheter Protocol
| Window | Practical considerations |
|---|---|
| Day 0–2 (immediate) | Some Level 1 centers perform PER on the day of injury, often concomitantly with orthopedic fixation or laparotomy, which avoids a second operating room trip. Median time to realignment was 2 days in one Level 1 series, with 72% performed simultaneously with another surgical service.[15] |
| After initial stabilization | If PER is attempted, ACS 2025 says it should occur within a few days of injury once the patient is hemodynamically stable, without a numerical cutoff.[1] A historical five-patient series described realignment 7–19 days after complete PFUI but did not test whether waiting improves visualization.[12] |
| No established late cutoff | Kim's series performed realignment within 5 days, Chung's at a median of 2 days (range 0–6), and Cohen's five-patient complete-PFUI series at 7–19 days. None of these series establishes a 2–3-week fibrosis threshold or the effect of delay on passage difficulty.[12][15][16] |
Catheter duration and post-removal
- Catheter indwelling time is reported as 4–10 weeks (mean about 5–6 weeks) across the cited endoscopic series; the IR studies report a mean of 52.3 days among 13 technically successful complete posterior realignments and 25 days in a separate traumatic urethral injury cohort.[10][13][15][16] The ACS guideline gives no duration and leaves it to the outpatient urology follow-up visit.[1]
- After early realignment for male PFUI, EAU 2026 describes catheterization for three weeks following partial rupture and six weeks following complete rupture, with voiding urethrography at catheter removal.[27] For other urethral injuries, assess healing by urethrography when planning catheter removal; decide the imaging and drainage plan before a trial of void.[5]
- Do not automatically prescribe repeated dilation or self-catheterization after failure of realignment in a patient suitable for definitive urethroplasty.[7]
- Mean time to failure after catheter removal was 79 days in Leddy's Level 1 series; close surveillance with uroflowmetry, post-void residual, and cystoscopy is needed.[17] AUA recommends monitoring for stricture, erectile dysfunction and incontinence for at least one year after urethral injury (Statement 23; Recommendation, Grade C).[4]
Outcomes — Posterior (PFUI)
The evidence for PER in complete PFUI is mixed. In the prospective TURNS cohort of complete PFUI after failed retrograde cystoscopic catheter placement, PER was not associated with a lower obstruction rate than initial SPT.[18] Owen’s 2025 meta-analysis compared primary realignment with SPT followed by delayed urethroplasty and found no significant difference in reported stricture rates (OR 1.23, 95% CI 0.24–6.37).[19] Wen and Jiang’s 2025 meta-analysis of initial realignment versus SPT diversion reported a lower pooled stricture proportion after realignment (OR 0.09, 95% CI 0.04–0.22); Barrett’s 2014 meta-analysis also favored realignment.[28][21]
| Study | Design / N | PER outcome | SPT outcome | Comment |
|---|---|---|---|---|
| McCormick 2023 (TURNS) | Multicenter prospective, complete PFUI, n = 69 | Obstruction 36/37; urethroplasty 31 patients (abstract labels this 87%; denominator not the full 37) | Obstruction 94%; urethroplasty 91% | No significant difference (p = 0.471, p = 0.784)[18] |
| Owen 2025 meta-analysis | 11 studies, 769 patients | Stricture OR 1.23 (95% CI 0.24–6.37); incontinence OR 1.02 (0.59–1.79); ED OR 0.97 (0.64–1.46) | — | All 11 studies nonrandomized; no detected superiority[19] |
| Zou 2017 | Retrospective, n = 522; cystostomy patients were referred with stricture | Stricture 111/129 (86%); mean stricture length 3.2 cm among those with stricture; simple perineal anastomosis 57/111 (51%) | Stricture 393/393 (100%) in this selected referral cohort; mean length 3.7 cm; simple perineal anastomosis 138/393 (35%) | Shorter strictures and more simple anastomoses were observed after PER in these selected cohorts[20] |
| Barrett 2014 meta-analysis | Systematic review | Stricture rate significantly lower (OR 0.12, 95% CI 0.04–0.41, p < 0.001) | — | Older studies; selection bias likely[21] |
| Johnsen 2015 | Single-center retrospective | Definitive therapy in 37%; only 26% required urethroplasty | 79% required urethroplasty | Time to urethroplasty longer with PER (14.6 vs 5.8 mo, p = 0.003)[2] |
Erectile dysfunction and incontinence rates do not differ significantly between PER and SPT. In Zou’s selected cohort, erectile dysfunction was reported in 14/98 evaluable PER patients (14.3%) versus 49/303 evaluable cystostomy patients (16.2%); incontinence was reported in 10/129 (8%) immediately after injury in the PER group and in 30/393 (7.6%) cystostomy patients before subsequent urethroplasty.[20] Owen’s pooled odds ratios for erectile dysfunction and incontinence were 0.97 and 1.02, respectively.[19][20]
Outcomes — Anterior (Bulbar) Straddle Injury
AUA recommends prompt urinary drainage after anterior straddle injury (Statement 25; Recommendation, Grade C); its discussion cautions against immediate repair or debridement while injury borders are indistinct.[4] WSES-AAST recommends initial urinary drainage for blunt anterior injury and an endoscopic realignment attempt before surgery (GoR 1C).[5] The Japanese Urological Association's 2023 guideline recommends suprapubic catheter placement rather than primary realignment as initial management for straddle injury (Grade C1).[29]
Evidence differs for partial and complete blunt bulbar injuries:
- In a propensity-matched study by Peng et al., patients with partial bulbar disruption managed by PER required no further urethral surgery in 41.5% of cases, versus only 14.6% with cystostomy alone (p < 0.05 in the primary abstract).[6]
- For complete bulbar disruption, Peng compared emergency anastomosis with cystostomy, not with PER.
- In a 15-man series of complete bulbar rupture, modified rigid-ureteroscope PER achieved catheter placement in all 15. During follow-up lasting 12–64 months, 8/15 (53%) developed grade I strictures at 10–27 weeks postsurgery and underwent 4–10 dilations; 3/15 (20%) developed postoperative erectile dysfunction that the authors reported resolved after 12 weeks of sildenafil.[3]
Impact on Subsequent Urethroplasty
A frequently raised concern is whether prior endoscopic manipulation worsens the stricture pattern or reduces success of later anastomotic urethroplasty.
- Retrospective comparison. Among patients with stricture in Zou’s selected cohorts, mean stricture length was 3.2 cm after PER versus 3.7 cm in cystostomy patients referred with stricture; simple perineal anastomosis was used in 57/111 (51%) versus 138/393 (35%), respectively.[20]
- Potential harm. Two retrospective series report that previous endoscopic realignment or open urethroplasty was associated with a lower success rate of subsequent anastomotic urethroplasty for post-traumatic stricture. In Culty’s series of 51 patients, satisfactory results exceeded 90% without prior manipulation and 60% with it.[23] Singh found that up to two prior visual internal urethrotomies did not affect the outcome.[22][23]
- Long-term outcomes. Chung’s Level 1 series reported a 9% overall success rate for realignment (29 of 32 patients failed) but a 96% study-defined success rate for excision and primary anastomosis in 24 selected patients treated primarily or secondarily; success meant no secondary procedure or the ability to pass a cystoscope across the injury or anastomosis.[15] In a retrospective single-surgeon cohort of 119 patients who all underwent perineal urethral anastomosis after PFUI, initial primary realignment versus SPT did not predict long-term complications.[24]
Guideline Summary
| Guideline | Position |
|---|---|
| AUA Urotrauma 2020 | SPT is the preferred initial management for most PFUI (Recommendation; Grade C). Clinicians may perform PER in hemodynamically stable patients (Option; Grade C) but should not make prolonged attempts at endoscopic realignment .[4] |
| AUA Urethral Stricture Amendment 2023 | Repeated endoscopic maneuvers (intermittent catheterization, blind cut-to-the-light) after PFUI should be avoided. Surgeons should perform delayed urethroplasty instead of delayed endoscopic procedures for obstruction or obliteration after PFUI .[7] |
| ACS Best Practices 2025 | Complete PFUI is managed initially with SPT. No strong evidence shows that PER changes the stenosis rate or the complexity of reconstruction for complete PFUI. For partial injuries, successful PER may lower the stenosis rate. Open realignment has no role.[1] |
| EAU Urological Trauma 2026 | Early endoscopic realignment in male PFUI when feasible ; initial SPT with urethroplasty after at least three months for complete posterior disruption ; selected early urethroplasty at two days to six weeks for stable complete PFUI with a short gap, soft perineum, and feasible lithotomy .[27] |
| WSES-AAST 2019 | Immediate endoscopic realignment preferred over immediate urethroplasty in stable patients with complete posterior lesions; an attempt at endoscopic realignment for blunt anterior injury (GoR 1C). Predates the TURNS results.[5] |
Technical Pearls and Pitfalls
- Avoid false passages. Forced wire passage through hematoma can create rectal or periurethral tracts that complicate later urethroplasty. Gentle, atraumatic technique with copious irrigation and direct visualization is required.[2]
- Plan antegrade and retrograde access. AUA describes flexible or rigid cystoscopes, video monitors and fluoroscopy for selected realignment in a staffed operating room after stabilization.[4]
- Manage irrigation pressure. Adequate irrigation is required to clear hematoma but excessive pressure extravasates into the pelvic hematoma cavity.
- Do not pursue blind "cut to the light" in obliterated PFUI. The AUA 2023 amendment advises against it because long-term success is rare.[7]
- Concomitant procedures. PER pairs well with same-anesthetic orthopedic fixation or laparotomy at Level 1 centers, reducing OR trips and allowing simultaneous pelvic embolization in the IR-guided variant.[10][15]
- Track failure early. Mean time to failure after catheter removal was 79 days in Leddy's series; structured surveillance (uroflow, PVR, cystoscopy) is needed to catch recurrence.[17]
Practical Role
PER selection depends on the injury pattern. For complete PFUI, the prospective TURNS cohort found that PER was not associated with a lower obstruction or subsequent urethroplasty rate than initial SPT.[18] The AUA 2020 guideline recommends SPT as preferred initial management for most PFUI (Grade C), and ACS 2025 best practices recommend initial SPT for complete PFUI.[4][1] For partial injuries, atraumatic catheter drainage with selected realignment may allow healing; a benefit over SPT is possible but the evidence is limited and injury-specific.[6][1] When PER fails, anastomotic urethroplasty remains feasible. A 58-patient retrospective series associated earlier endoscopic realignment or urethroplasty with lower subsequent anastomotic success.[22] A 51-patient series reported fewer satisfactory results after prior endoscopic or open manipulation.[23] In a 119-patient cohort selected for reconstruction after PFUI, initial primary realignment did not predict later complications.[24]
Videos
References
1. Johnsen N, Wessells H, Archer-Arroyo K, et al. Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons; 2025. Official guideline.
2. Johnsen NV, Dmochowski RR, Mock S, et al. Primary endoscopic realignment of urethral disruption injuries — a double-edged sword? J Urol. 2015;194(4):1022-6. doi:10.1016/j.juro.2015.03.112.
3. Zhang Z, Fang L, Chen D, et al. A modified endoscopic primary realignment of severe bulbar urethral injury. J Endourol. 2021;35(3):335-341. doi:10.1089/end.2020.0567.
4. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
5. Coccolini F, Moore EE, Kluger Y, et al. Kidney and uro-trauma: WSES-AAST guidelines. World J Emerg Surg. 2019;14:54. doi:10.1186/s13017-019-0274-x.
6. Peng X, Guo H, Zhang X, Wang J. Straddle injuries to the bulbar urethra: what is the best choice for immediate management? J Trauma Acute Care Surg. 2019;87(4):892-897. doi:10.1097/TA.0000000000002388.
7. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
8. Gheiler EL, Frontera JR. Immediate primary realignment of prostatomembranous urethral disruptions using endourologic techniques. Urology. 1997;49(4):596-9. doi:10.1016/s0090-4295(97)80002-7.
9. Melekos MD, Pantazakos A, Daouaher H, Papatsoris G. Primary endourologic re-establishment of urethral continuity after disruption of prostatomembranous urethra. Urology. 1992;39(2):135-8. doi:10.1016/0090-4295(92)90269-3.
10. Jeon CH, Kwon H, Kim JH, et al. Complete posterior urethral disruption accompanied by complex pelvic fractures: clinical outcomes of fluoroscopic primary posterior urethral realignment. J Vasc Interv Radiol. 2021;32(3):343-349. doi:10.1016/j.jvir.2020.10.029.
11. Porter JR, Takayama TK, Defalco AJ. Traumatic posterior urethral injury and early realignment using magnetic urethral catheters. J Urol. 1997;158(2):425-30. doi:10.1016/s0022-5347(01)64494-x
12. Cohen JK, Berg G, Carl GH, Diamond DD. Primary endoscopic realignment following posterior urethral disruption. J Urol. 1991;146(6):1548-50. doi:10.1016/s0022-5347(17)38162-4.
13. Lee MS, Kim SH, Kim BS, Choi GM, Huh JS. The efficacy of primary interventional urethral realignment for the treatment of traumatic urethral injuries. J Vasc Interv Radiol. 2016;27(2):226-31. doi:10.1016/j.jvir.2015.08.006.
14. White JL, Hirsch IH, Bagley DH. Endoscopic urethroplasty of posterior urethral avulsion. Urology. 1994;44(1):100-5. doi:10.1016/s0090-4295(94)80017-0.
15. Chung PH, Wessells H, Voelzke BB. Updated outcomes of early endoscopic realignment for pelvic fracture urethral injuries at a Level 1 trauma center. Urology. 2018;112:191-197. doi:10.1016/j.urology.2017.09.032.
16. Kim FJ, Pompeo A, Sehrt D, et al. Early effectiveness of endoscopic posterior urethra primary alignment. J Trauma Acute Care Surg. 2013;75(2):189-94. doi:10.1097/TA.0b013e31829bb7c8.
17. Leddy LS, Vanni AJ, Wessells H, Voelzke BB. Outcomes of endoscopic realignment of pelvic fracture associated urethral injuries at a Level 1 trauma center. J Urol. 2012;188(1):174-8. doi:10.1016/j.juro.2012.02.2567.
18. McCormick BJ, Keihani S, Hagedorn J, et al. A multicenter prospective cohort study of endoscopic urethral realignment versus suprapubic cystostomy after complete pelvic fracture urethral injury. J Trauma Acute Care Surg. 2023;94(2):344-349. doi:10.1097/TA.0000000000003774.
19. Owen K, Joe W, Palgunadi IN, Soebhali B. A systematic review and meta-analysis of surgical approaches in pelvic fracture-associated urethral injury: primary endoscopic realignment versus delayed urethroplasty. World J Urol. 2025;43(1):603. doi:10.1007/s00345-025-05994-7.
20. Zou Q, Zhou S, Zhang K, Yang R, Fu Q. The immediate management of pelvic fracture urethral injury — endoscopic realignment or cystostomy? J Urol. 2017;198(4):869-874. doi:10.1016/j.juro.2017.04.081.
21. Barrett K, Braga LH, Farrokhyar F, Davies TO. Primary realignment vs suprapubic cystostomy for the management of pelvic fracture-associated urethral injuries: a systematic review and meta-analysis. Urology. 2014;83(4):924-9. doi:10.1016/j.urology.2013.12.031.
22. Singh BP, Andankar MG, Swain SK, et al. Impact of prior urethral manipulation on outcome of anastomotic urethroplasty for post-traumatic urethral stricture. Urology. 2010;75(1):179-82. doi:10.1016/j.urology.2009.06.081.
23. Culty T, Boccon-Gibod L. Anastomotic urethroplasty for posttraumatic urethral stricture: previous urethral manipulation has a negative impact on the final outcome. J Urol. 2007;177(4):1374-7. doi:10.1016/j.juro.2006.11.092.
24. Neu S, Remondini T, Hird A, et al. A retrospective look at long-term outcomes after definitive surgical repair for traumatic pelvic fracture urethral injuries — does initial management make a difference? Urology. 2022;160:203-209. doi:10.1016/j.urology.2021.10.036.
25. Ho CJ, Yang MH. Novel method of primary endoscopic realignment for high-grade posterior urethral injuries: a case report. World J Clin Cases. 2022;10(3):1050-1055. doi:10.12998/wjcc.v10.i3.1050.
26. Chung H, Park MH, Jung E, Kim S, Kim JG, Choi YU. Interventional radiology-guided Foley catheterization for pelvic fracture with urethral injury: a single-center retrospective case series. J Clin Med. 2026;15(13):5096. doi:10.3390/jcm15135096.
27. European Association of Urology. EAU Guidelines on Urological Trauma. 2026. Official guideline.
28. Wen JH, Jiang SJ. "Update on Suprapubic Cystostomy Diversion vs. Primary Realignment for the Management of Blunt Posterior Urethral Injuries: A Systematic Review and Meta-Analysis." Urol J. 2025;22(4):169-175. doi:10.22037/uj.v22i.8061
29. Horiguchi A, Shinchi M, Ojima K, et al. "The Japanese Urological Association's clinical practice guidelines for urotrauma 2023." Int J Urol. 2024;31(2):98-110. doi:10.1111/iju.15331.