Urethral Diverticulectomy
Urethral diverticulectomy excises the diverticular sac, closes the urethral communication, and reinforces the repair with multilayer closure (± Martius interposition) to minimize fistula and recurrence. Most cases are female and approached transvaginally; rare male diverticula are typically post-urethroplasty / stricture and approached perineally with reconstruction tailored to the resulting urethral defect length.[1][2][3]
For the diagnostic workup of a periurethral mass, see Female Urethral & Periurethral Masses and Urethral Diverticulum (Female). For interposition flap principles, see Martius Flap (foundations).
Epidemiology and Etiology
Urethral diverticula (UD) are epithelium-lined outpouchings of the urethral mucosa; the often-quoted 1–6% prevalence range comes from selected historical populations.[5][36] In Olmsted County, the annual diagnosed incidence was 17.9 per million adult women (95% CI 10.9–24.9).[36] The dominant etiologic theory is chronic infection or abscess of the periurethral (Skene's) glands rupturing into the urethral lumen.[2][4] An identifiable risk factor was present in 45 of 121 women in one series: traumatic vaginal delivery (15%), prior periurethral surgery (14%) and urethral dilation (8%).[1]
In men, UD are typically acquired, associated with urethral stricture, prior urethroplasty, trauma, or prolonged catheterization.[16][17]
Clinical Presentation
The classic "3 Ds" (dysuria, dyspareunia, dribbling) are present together in only about 5% and are no longer reliable as a diagnostic triad.[7] In Baradaran’s 54-woman operated cohort, recurrent UTI occurred in 70%, SUI and dyspareunia each in 60%, and a tender anterior vaginal wall mass was found on examination in 52%; in Pincus’s 78-woman diagnosed cohort, recurrent UTI occurred in 23%, incontinence (not specifically SUI) in 39%, dyspareunia in 12%, and dysuria in 18%. Post-void dribbling and pelvic pain may also occur.[7][8] Up to 21% are asymptomatic.[7][8] In a prospective model, the combination of LUTS, post-micturition dribbling and recurrent UTI had the highest odds of a positive ultrasound finding (OR 13.78).[22] Tender anterior vaginal wall mass is the most common physical finding; expression of purulent or mucoid material through the urethra supports the diagnosis.[7]
Imaging and Diagnosis
MRI (post-void T2-weighted) is the preferred modality for size, location, configuration (simple, U-shaped, saddle or circumferential), and sphincter relationship.[2][3][10][12] EAU 2026 guidelines recommend MRI for diagnosis and characterization , with urethroscopy, VCUG and ultrasound where necessary.[21] In a surgically selected cohort, MRI and operative findings differed in 10/41 women (24.4%), including two intra-diverticular cancers missed on MRI.[13] Prior polyacrylamide hydrogel injection can mimic a diverticulum on MRI; reconcile imaging with the injection history before operating.[21]
| Modality | Sensitivity / utility |
|---|---|
| MRI (T2 post-void) | Preferred modality; configuration + sphincter relationship[2][3] |
| Pelvic floor ultrasound | Reported sensitivity 94% and specificity 100% in 196 symptomatic women; final diagnosis incorporated ultrasound and VCUG findings, limiting independent validation of these estimates.[23] |
| VCUG | Sensitivity 72–78% in the series cited; complementary detrusor / sphincter info[2][23] |
| Double-balloon positive-pressure urethrography | Depicted suspected diverticula in 12/12 selected women (nine underwent excision), versus 8/12 by VCUG; another small series missed 3/4 surgically confirmed diverticula. MRI is preferred for anatomic planning.[34][35][21] |
Configuration. The most common location was midurethral 46% (distal 30%, proximal 21%) in one series.[1] Circumferential UD is associated with more difficult repair and recurrence in some female cohorts; a single-surgeon series of 68 women reported OR 7.97 (95% CI 1.14–55.69).[10]
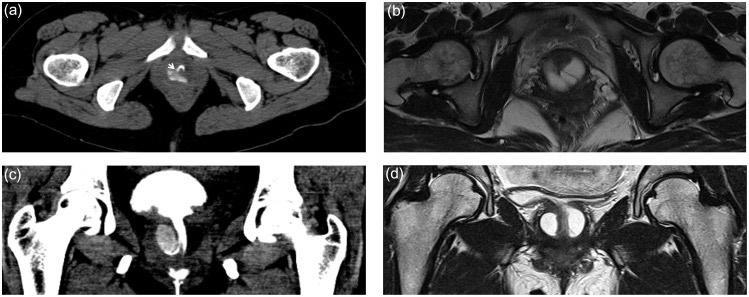
Female urethral diverticulum in a 42-year-old woman: (a) axial CT voiding cystourethrography (voiding phase) showing a diverticulum partially filled with contrast; (b) axial T2-weighted MRI showing the overall shape and complexity of the diverticulum; (c) coronal CT voiding cystourethrography showing the ostium clearly; (d) coronal T2-weighted MRI, in which the ostium is less clearly seen. From Lee YJ, et al. PLoS One. 2014;9(9):e107448, Figure 2 (CC BY 4.0).[31]
Indications
- Symptomatic UD. Recurrent UTIs, pain, dyspareunia, incontinence, voiding dysfunction.[3]
- Asymptomatic or minimally symptomatic small UD may be observed. In men, post-void manual decompression has been used for small, unobstructed diverticula.[16] EAU guidelines advise warning patients managed conservatively of a small (1–6%) risk of cancer in the diverticulum .[21]
- All excised specimens to pathology. Malignancy (predominantly adenocarcinoma) is reported in about 1–6% of diverticula.[21] Individual surgical series found carcinoma in 1 of 89 and 1 of 40 specimens.[5][8]
Preoperative Preparation
- MRI reviewed to plan approach (supine versus prone), Martius need, and urethral-transection requirement for circumferential disease.[1][2][3]
- Videourodynamics / VCUG to assess detrusor function and pre-existing SUI: 17/121 (14%) had SUI on videourodynamics in Osman, while 29/70 (41%) in Malde’s Martius-interposition cohort had pre-existing SUI.[1][18]
- Treat any active UTI to completion before surgery.
- Suspected carcinoma. If examination or imaging suggests a urethral tumor, obtain urethrocystoscopy with biopsy before choosing the operation; stage confirmed cancer before planning resection.[37]
- Acute sepsis or a large periurethral abscess. Avoid significant manual compression of a tense, infected diverticulum; transvaginal drainage followed by definitive excision and repair at a later procedure has been described.[29]
- Consent for de novo SUI (16/121 [13%] in Osman and 13/89 [15%] in Reeves, each calculated over the full surgical cohort), symptomatic recurrence (4% in Osman), recurrent or residual diverticulum (3.4% in Reeves), urethrovaginal fistula, urethral stricture, and the small risk of malignancy.[1][5][21]
- Perioperative antibiotic prophylaxis per protocol.
- No diverticulectomy-specific VTE recommendation exists; apply the general reconstructive-pelvic-surgery risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page.
Technique 1 — Standard Transvaginal Excision with Three-Layer Closure
Transvaginal resection with or without reconstruction accounted for 84% of patients in a systematic review.[33]
- Setup. 16–18 Fr urethral Foley as a stent or guide; ± SPC for postop drainage.
- Cystourethroscopy. Identify the diverticular ostium (identified in 60% of one series), assess number and location, exclude intra-urethral pathology.[19] A guidewire or ureteric catheter into the diverticulum aids intraoperative identification. A Trattner double-balloon catheter, with a proximal balloon seated at the bladder neck and a distal balloon occluding the external meatus, has been described as an older alternative: sterile milk or methylene blue instilled through the catheter distends the urethra and diverticulum, and periodic reinflation after placement aids identification and mobilization of the sac; a standard 18-Fr Foley substitutes when the device is unavailable.[24]
- Hydrodissection + vaginal incision. Dilute vasopressin or 1:200,000 epinephrine for hemostasis; inverted-U incision (preferred) or midline longitudinal over the mass.[8][1] Plain normal saline is used instead of a vasoconstrictor by some authors, to allow earlier recognition of bleeding vessels and avoid delayed hemorrhage.[27]
- Vaginal flap elevation. Develop the plane between vaginal wall and periurethral fascia; raise lateral flaps wide enough for a tension-free three-layer closure. Maintain flap thickness for blood supply.
- Periurethral fascia incision. Midline longitudinal; preserve fascial flaps as the second layer.[8] Other atlas sources describe a transverse periurethral-fascia incision instead, with proximal and distal fascial layers developed before the diverticulum is mobilized.[28]
- Diverticular sac dissection. Sharp and blunt circumferential mobilization; identify the neck. Keep the urethral catheter as a palpable guide to avoid urethrotomy. Adherent or previously infected sacs require meticulous sharp dissection.
- Sac and ostium excision. Dissect to the urethral communication; excise the entire sac and ostium (incomplete removal is a recognized cause of recurrence). An adherent rim of urethral wall may be excised when needed. Send tissue for pathology.[21][30]
- Layer 1 — urethral mucosa. Interrupted or running 4-0 polyglactin; transverse closure to avoid lumen narrowing; watertight (test with saline or methylene blue via the Foley).[8] Other atlas illustrations show the urethral defect reapproximated longitudinally over the catheter instead; the requirement common to both is a watertight, tension-free closure.[28]
- Layer 2 — periurethral fascia. Interrupted 3-0 polyglactin in a direction perpendicular to layer 1 (the cardinal three-layer principle). For UD > 4 cm, Lask described bipedicle double-opposing fascial flaps in a 17-woman retrospective series, with left and right fascial flaps advanced and overlapped for a double-thickness layer.[8][19]
- Layer 3 — vaginal wall. Running 2-0 polyglactin in a third orientation; tension-free; trim redundancy as needed.[8]
- Final check. Retrograde fill ± end-of-case cystourethroscopy for patency and watertightness.[11]
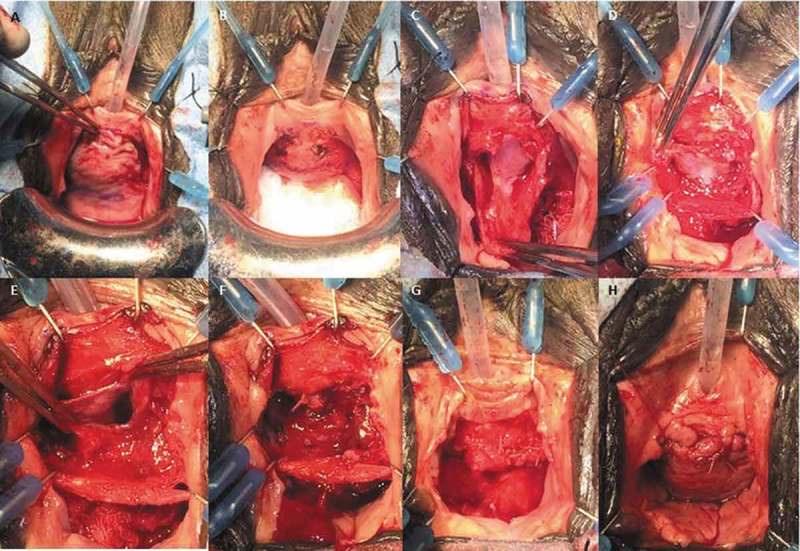
Transvaginal urethral diverticulectomy: (a) inverted-U incision marked on the anterior vaginal wall, with a weighted vaginal speculum and Scott retractor; (b) after dissection of the anterior vaginal wall flap (packed away with moist gauze), a transverse incision in the periurethral fascia; (c) periurethral fascia dissected off the diverticulum; (d) diverticulum grasped and dissected circumferentially down to the ostium; (e) diverticulum excised; (f) urethra closed with running 4-0 absorbable suture; (g) periurethral fascia closed with interrupted 3-0 absorbable sutures perpendicular to the urethral closure; (h) anterior vaginal wall flap closed with running-locking 2-0 absorbable suture. From Greiman AK, et al. Arab J Urol. 2019;17(1):49-57, Figure 8 (CC BY 4.0).[30]
Technique 2 — Modified Prone Jack-Knife (Chapple / Osman, Sheffield)
Offers excellent surgical access, and a more ergonomic position for the surgeon, for large or complex UD.[1]
- Supine phase. Cystourethroscopy; place urethral Foley, suprapubic catheter, and 5 Fr ureteric stents for proximal or large UD to protect the orifices.
- Reposition prone jack-knife. Hips flexed over a break or bolster; buttocks taped apart; surgeon seated with direct view of the anterior vaginal wall.
- Dissection / excision / closure. Identical principles to Technique 1 (steps 3–11).
- Martius flap. Used in 30% of the Sheffield cohort; ipsilateral labium majus harvest, subcutaneous tunnel, interposed between fascial and vaginal layers.[1] A later chapter by the same Sheffield group estimates that a Martius flap is needed in about 15% of cases, particularly when vaginal or submucosal tissue is deficient or dead space is substantial.[26]
Outcomes (n = 121, mean follow-up 10 mo). 73% continent, 4% symptomatic recurrence, 13% de-novo SUI, 9% Clavien-Dindo I–II.[1]
Technique 3 — Bipedicle Double-Opposing Fascial Flaps (Lask, for UD > 4 cm)
Same setup as Technique 1; the modification is at Layer 2:[19]
- After urethral mucosal closure, the periurethral fascia is incised midline-longitudinally and the two fascial flaps (each on its lateral pedicle) are advanced and overlapped in opposite directions with interrupted 3-0 Vicryl, producing a double-thickness fascial layer.
- Outcomes (n = 17, UD > 4 cm). No recurrence at mean follow-up of 5 ± 2.4 yr in this retrospective series.
Technique 4 — Circumferential / Dorsal UD: Urethral Transection and Reconstruction
In Ko's single-surgeon series, initial cure, defined as symptom resolution without residual diverticulum on MRI, occurred in 16/25 (64%) circumferential and 27/27 (100%) simple UD after at least one year of follow-up.[10] Some complex dorsal components require urethral transection for exposure.[12][21]
Rovner / Nickles steps:
- Standard vaginal incision and flap elevation.
- Complete urethral transection at the level of the diverticulum to access the dorsal wall.
- Excise the entire mucosalized surface (partial urethrectomy as needed).
- Reconstruction. End-to-end anastomosis when feasible; tubularization of the dorsal diverticular wall to substitute a urethral segment when the dorsal tissue is healthy enough.[12]
- Selective Martius interposition for tissue reinforcement.
- Selective pubovaginal sling. Rovner and Wein used a sling selectively.
Outcomes. In 9 women, all had subjective pain relief; 6 of 8 were pad-free; 1 had a fistula and 1 a stricture.[12]
Mehta alternative. A single-patient video report describes segmental excision without formal transection, incising around or dorsal to the meatus into the retropubic space to access the dorsal component, followed by two-layer urethral repair reinforced with a fibromuscular flap.[11]
Technique 5 — Marsupialization (Spence-Duckett, distal UD only)
Reserved for distal UD that does not involve the continence mechanism at the midurethra.[6][14]
Classic. Metzenbaum scissors (one blade in urethra, one in diverticulum); incise through the posterior urethral wall and anterior vaginal wall from ostium to meatus; marsupialize diverticular mucosa to vaginal epithelium.
Modified (Welch). In a single-patient video report, Welch et al. incised from a small ostium along the posterior urethra toward the anterior vaginal wall and excised sac tissue before marsupialization. The authors intended to reduce urethral shortening and improve cosmesis; symptoms resolved without new incontinence at six weeks.[6]
Limitation. Essentially a generous meatotomy; risk of urethral shortening and cosmetic deformity. Ginsburg and Genadry confined marsupialization to UD in the lower third of the urethra; formal excision for the upper two-thirds.[14]
Additional risks. Excessive ventral extension can injure the proximal or distal sphincter and cause SUI; a pseudo-septum forming between the marsupialized urethra and the anterior vaginal wall can cause dyspareunia in sexually active women.[26] For rare cases of acute infection or pregnancy when complete excision cannot be performed, diverticulotomy creating a temporary urethrovaginal fistula for decompression has been described. One source advises against this because of sphincter injury and the complexity of later reconstruction,[26] while another describes it as an option for highly symptomatic acute infection unresponsive to antibiotics, or when elective excision must be delayed, followed by definitive repair with planned excision.[27] Diverticulotomy is a temporizing maneuver, not a definitive repair.
Technique 6 — Partial Excision / Symptomatic-to-Asymptomatic Conversion
Chen et al. described partial resection with cauterization of residual sac wall for selected complex UD when complete dissection threatened the sphincter; their uncontrolled 21-woman series also included complete resections and excluded radiographically suspected carcinoma.[15]
- Mean OR time 75.7 ± 28.9 min; mean EBL 25.5 ± 10.7 mL; median catheterization 15 d.[15]
- Symptom resolution was 76.2% (16/21), but 9/21 women (42.9%) had residual or recurrent diverticulum on imaging without symptoms; the series included complete and partial resections. Complications were mostly Clavien I–II.[15]
Technique 7 — Male Urethral Diverticulectomy
Approach to reconstructable male UD is perineal or penile according to location (most are bulbar or pendulous).[16][17] In Cinman’s 22-man series, three underwent urinary diversion: two had neurogenic bladders requiring intermittent catheterization, and one had heavily scarred, irradiated urethral tissue.[16]
- Mobilize the urethra; identify the diverticulum.
- Excise the sac; assess resulting urethral defect length.
- Reconstruction by defect length:
- Use primary closure or anastomosis only when tissue quality and location permit a tension-free, non-narrowing repair.
- Larger defects may require buccal mucosa graft or an appropriate vascularized flap; the 4-cm threshold in a small series is not a general EPA rule, particularly for penile defects.[17]
- Multilayer closure with dartos / spongiosal coverage.
- Outcomes. Alphs reported 12/13 (92%) success and 42% complications at median 21.7-month follow-up.[17] Cinman’s mixed-management cohort included 22 men (12 diverticulectomy and urethroplasty, seven managed without surgery, three diverted). In Cinman’s 22-man cohort (median follow-up 2.3 years), recurrence occurred in 1/11 men after diverticulectomy; 10/11 (91%) were recurrence-free.[16]
Outcomes Summary
| Outcome | Reported rate |
|---|---|
| Reported outcomes after transvaginal excision | Ockrim: 20/24 (83%) three-layer repairs successful and 29/30 (97%) ultimately cured of diverticulum; Reeves: 72% dry and cured at 3–20 months.[1][2][3][5] |
| Initial cure — simple UD | 100% in Ko’s 27 simple cases; Ockrim also reported 19/19 cured at first attempt.[3][10][2] |
| Initial cure — circumferential UD | 64% in Ko’s circumferential subgroup.[3][10] |
| Cure after reoperation | Ko: 8/11 (73%) cured after a second operation; overall eventual cure after initial and repeat operations was 92.6%. Reeves reported both redo patients recovered well and were dry, without a separate anatomic-cure estimate.[3][5][10] |
| Recurrence after surgery | Observed proportions vary by cohort and follow-up: 4–10% in several cited series and 15/68 (22%) after initial repair in Ko. El-Nashar observed 14/114 (12.3%) recurrences, although postoperative follow-up information was available for 82/114 (71.9%), and estimated five-year cumulative recurrence at 23.4% (95% CI 13.9–37.0).[1][2][3][10][32] |
| De-novo SUI | 16/121 (13% of the full cohort) in Osman (mean follow-up 10 months), 13/89 (15% of the full cohort) in Reeves (follow-up 3–20 months); Malde reported 10/41 (24%) immediately after surgery, declining to 5/41 (12%) at 12 months.[1][2][5][18] |
| Resolution of pre-existing SUI | ~ 50%[1] |
| Urethrovaginal fistula | 0.9–8.3% (EAU review)[21] |
| Carcinoma in surgical specimens | Reeves reported 1/89 (1.1%), Pincus 1/40 (2.5%), and Thomas 5/90 (5.6%) in selected surgical series; the EAU’s 6% figure for neoplastic alterations includes invasive adenocarcinoma.[5][8][21][38] |
Concomitant Anti-Incontinence Procedure
In Bradley’s multicenter retrospective cohort (485 women; 96 with a concomitant sling; mean follow-up 14.6 months), a concomitant pubovaginal sling was associated with greater resolution of pre-existing SUI (aOR 2.27).[20] The study did not detect a difference in de novo SUI (aOR 0.86; 95% CI 0.25–2.92).[20] Short-term retention (<6 weeks; aOR 2.50), long-term retention (>6 weeks; aOR 6.98) and recurrent UTI (aOR 3.27) were more frequent with the sling.[20] Concomitant versus staged continence surgery is decided after confirming true SUI and discussing retention and infection tradeoffs. Some patients improve after diverticulectomy alone: in the Sheffield series 54% of women with pre-existing SUI were continent after excision, and the authors advocate deferring an incontinence procedure.[1] EAU 2026 guidelines state that bothersome SUI may be addressed at diverticulectomy with a non-synthetic sling and do not recommend a concomitant synthetic midurethral sling, because of the risk of erosion, extrusion and fistula next to a fresh suture line.[21]
Postoperative Management
- Urethral catheter: removed with the suprapubic catheter after 3 weeks in the Sheffield excision series; median catheterization was 15 days (IQR 14–21) in Chen’s mixed diverticulectomy/partial-resection cohort.[1][15]
- SPC (if placed) clamped at urethral catheter removal; removed once voiding with acceptable PVR confirmed.
- Before the voiding trial, a pericatheter VCUG can assess the repair. If extravasation is seen, continue catheter drainage and repeat pericatheter VCUG in 1–2 weeks until the leak resolves.[30]
- Voiding trial; PVR (median 26 mL in Sheffield).[1]
- Postoperative bladder spasms are managed with anticholinergics or beta-3 agonists; pain control favors non-narcotic options.
- Examine at about six weeks and reassess symptoms and continence at 6–12 months. Repeat MRI or ultrasound if a mass, recurrent UTI, dribbling, or other symptoms suggest residual or recurrent disease; later symptoms warrant reassessment. Consider an autologous fascial PVS for persistent bothersome SUI.[1][5][21]
- Pelvic-floor muscle training postoperatively. - Pelvic-floor muscle training postoperatively. In Malde’s Martius-interposition series, 10/41 women without pre-existing SUI (24%) reported de novo SUI immediately after surgery and 5/41 (12%) still reported it at 12 months; Osman reported de novo SUI in 16/121 (13%) in a separate series with mean follow-up of 10 months.[1][18]
Technical Pearls and Pitfalls
- Watertight multilayer closure with no overlapping suture lines is a stated principle of transvaginal diverticulectomy.[21]
- Bleeding during initial vaginal-flap elevation should be minimal. More than minimal bleeding at this step suggests dissection has strayed too deep, into the wrong plane; stop and reassess the plane, particularly in reoperative cases.[25]
- Brisk retropubic bleeding (for example while traversing the endopelvic fascia for a concomitant sling) can be managed with vaginal packing and several minutes of manual elevation of the anterior vaginal wall against the posterior symphysis pubis, using a hand, sponge stick or retractor; through-and-through absorbable sutures in the lateral vaginal fornices control vessels that cannot be visualized. Bleeding that persists despite prolonged compression may indicate major-vessel injury and can require retropubic exploration.[25]
- A Martius flap without meticulous urethral repair does not prevent recurrence, fistula or SUI, according to a single-patient video report and review.[9]
- Circumferential configuration was an independent predictor of lower cure in one series (OR 7.97, 95% CI 1.14–55.69).[10]
- Convert to urethral transection if the dorsal component cannot be adequately accessed ventrally.[12][21]
- Avoid excessive cautery near the urethra; thermal injury leads to delayed necrosis or fistula.
- Preserve periurethral fascia as much as possible; it is the second layer and supports the continence mechanism.
- A previously placed Martius flap can be re-mobilized and repositioned for recurrent repair, as described in one patient.[9]
- End-of-case cystourethroscopy confirms patency and watertightness.[11]
Videos
References
1. Osman NI, Mangir N, Reeves FA, et al. The modified prone jack-knife position for the excision of female urethral diverticula. Eur Urol. 2021;79(2):290-297. doi:10.1016/j.eururo.2020.11.016.
2. Ockrim JL, Allen DJ, Shah PJ, Greenwell TJ. A tertiary experience of urethral diverticulectomy: diagnosis, imaging and surgical outcomes. BJU Int. 2009;103(11):1550-1554. doi:10.1111/j.1464-410X.2009.08348.x.
3. Greenwell TJ, Spilotros M. Urethral diverticula in women. Nat Rev Urol. 2015;12(12):671-680. doi:10.1038/nrurol.2015.230.
4. Ganabathi K, Leach GE, Zimmern PE, Dmochowski R. Experience with the management of urethral diverticulum in 63 women. J Urol. 1994;152(5 Pt 1):1445-1452. doi:10.1016/s0022-5347(17)32442-4.
5. Reeves FA, Inman RD, Chapple CR. Management of symptomatic urethral diverticula in women: a single-centre experience. Eur Urol. 2014;66(1):164-172. doi:10.1016/j.eururo.2014.02.041.
6. Welch EK, Dengler KL, Welgoss JA. Urethral diverticulum marsupialization with modified Spence-Duckett procedure. Urology. 2023;176:248. doi:10.1016/j.urology.2023.02.040.
7. Baradaran N, Chiles LR, Freilich DA, et al. Female urethral diverticula in the contemporary era: is the classic triad of the "3Ds" still relevant? Urology. 2016;94:53-56. doi:10.1016/j.urology.2016.04.005.
8. Pincus JB, Laudano M, Leegant A, Downing K. Female urethral diverticula: diagnosis, pathology, and surgical outcomes at an academic, urban medical center. Urology. 2019;128:42-46. doi:10.1016/j.urology.2018.12.052.
9. Dykes N, Dwyer P, Rosamilia A, Zilberlicht A. Video and review of the surgical management of recurrent urethral diverticulum. Int Urogynecol J. 2020;31(12):2679-2681. doi:10.1007/s00192-020-04357-7.
10. Ko KJ, Suh YS, Kim TH, et al. Surgical outcomes of primary and recurrent female urethral diverticula. Urology. 2017;105:181-185. doi:10.1016/j.urology.2017.02.040.
11. Mehta S, Suh C, Harmanli O. Circumferential urethral diverticulum: a surgical conundrum. Int Urogynecol J. 2020;31(12):2683-2685. doi:10.1007/s00192-020-04359-5.
12. Rovner ES, Wein AJ. Diagnosis and reconstruction of the dorsal or circumferential urethral diverticulum. J Urol. 2003;170(1):82-86; discussion 86. doi:10.1097/01.ju.0000067291.70172.b5.
13. Chung DE, Purohit RS, Girshman J, Blaivas JG. Urethral diverticula in women: discrepancies between magnetic resonance imaging and surgical findings. J Urol. 2010;183(6):2265-2269. doi:10.1016/j.juro.2010.02.016.
14. Ginsburg D, Genadry R. Suburethral diverticulum: classification and therapeutic considerations. Obstet Gynecol. 1983;61(6):685-688. PMID 6405333
15. Chen X, Ang X, Xu X, et al. Experience in conversion of symptomatic urethral diverticulum to asymptomatic status through surgery. Sci Rep. 2025;15(1):7533. doi:10.1038/s41598-025-90748-z.
16. Cinman NM, McAninch JW, Glass AS, Zaid UB, Breyer BN. Acquired male urethral diverticula: presentation, diagnosis and management. J Urol. 2012;188(4):1204-1208. doi:10.1016/j.juro.2012.06.036.
17. Alphs HH, Meeks JJ, Casey JT, Gonzalez CM. Surgical reconstruction of the male urethral diverticulum. Urology. 2010;76(2):471-475. doi:10.1016/j.urology.2009.11.080.
18. Malde S, Sihra N, Naaseri S, et al. Urethral diverticulectomy with Martius labial fat pad interposition improves symptom resolution and reduces recurrence. BJU Int. 2017;119(1):158-163. doi:10.1111/bju.13579.
19. Lask A, Rappaport YH, Neheman A, et al. Transvaginal surgical repair of large urethral diverticula with bipedicle double-opposing flaps of the periurethral fascia. Int Urogynecol J. 2021;32(11):2969-2973. doi:10.1007/s00192-020-04486-z.
20. Bradley SE, Leach DA, Panza J, et al. A multicenter retrospective cohort study comparing urethral diverticulectomy with and without pubovaginal sling. Am J Obstet Gynecol. 2020;223(2):273.e1-273.e9. doi:10.1016/j.ajog.2020.06.002.
21. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS: Urethral Diverticulum. 2026. Guideline.
22. Barakat B, Franke K, Hijazi S, et al. Correlation between symptoms and imaging findings including pelvic floor ultrasound to improve the symptom-based diagnosis of female urethral diverticulum (CHECK-UD study). Int Urogynecol J. 2022;33(8):2267-2274. doi:10.1007/s00192-021-04770-6.
23. Barakat B, Gauger U, Rehme C, Hadaschik B, Wolff I, Hijazi S. Diagnosis of female urethral diverticulum using pelvic floor ultrasound and comparison with voiding cystourethrogram (imaging study). Int Urogynecol J. 2023;34(2):563-569. doi:10.1007/s00192-022-05340-0.
24. Karram MM, Mahdy A. Repair of Suburethral Diverticulum. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1037-1048.
25. Cox L, Gilchrist AS, Rovner ES. Urethral Diverticulectomy. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:221-230. doi:10.1007/978-3-319-49855-3_20
26. Saad S, Osman N, Alsulaiman OA, Chapple CR. Surgical Repair of Urethral Diverticula. In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:857-867.
27. Wang AY, Rovner ES. Female Urethral Diverticulectomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:672-681.
28. Zheng Y, Rovner ES. Urethral Diverticulum. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:1189-1200. doi:10.1201/9781003144243-121
29. Vasavada SP. Urethral Diverticula. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:562-566.
30. Greiman AK, Rolef J, Rovner ES. Urethral diverticulum: a systematic review. Arab J Urol. 2019;17(1):49-57. doi:10.1080/2090598X.2019.1589748.
31. Lee YJ, Son SJ, Paick JS, Kim SW. Preoperative CT voiding cystourethrography using 16-multidetector CT in female urethral diverticulum. PLoS One. 2014;9(9):e107448. doi:10.1371/journal.pone.0107448.
32. El-Nashar SA, Singh R, Bacon MM, et al. "Female urethral diverticulum: presentation, diagnosis, and predictors of outcomes after surgery." Female Pelvic Med Reconstr Surg. 2016;22(6):447-452. doi:10.1097/SPV.0000000000000312
33. Bodner-Adler B, Halpern K, Hanzal E. "Surgical management of urethral diverticula in women: a systematic review." Int Urogynecol J. 2016;27(7):993-1001. doi:10.1007/s00192-015-2862-y
34. Golomb J, Leibovitch I, Mor Y, Morag B, Ramon J. "Comparison of voiding cystourethrography and double-balloon urethrography in the diagnosis of complex female urethral diverticula." Eur Radiol. 2003;13(3):536-542. doi:10.1007/s00330-002-1539-3
35. Neitlich JD, Foster HE Jr, Glickman MG, Smith RC. "Detection of urethral diverticula in women: comparison of a high resolution fast spin echo technique with double balloon urethrography." J Urol. 1998;159(2):408-410. doi:10.1016/S0022-5347(01)63934-X
36. El-Nashar SA, Bacon MM, Kim-Fine S, Weaver AL, Gebhart JB, Klingele CJ. "Incidence of female urethral diverticulum: a population-based analysis and literature review." Int Urogynecol J. 2014;25(1):73-79. doi:10.1007/s00192-013-2155-2
37. Gakis G, Bruins HM, Cathomas R, et al. "European Association of Urology Guidelines on Primary Urethral Carcinoma-2020 Update." Eur Urol Oncol. 2020;3(4):424-432. doi:10.1016/j.euo.2020.06.003
38. Thomas AA, Rackley RR, Lee U, Goldman HB, Vasavada SP, Hansel DE. "Urethral diverticula in 90 female patients: a study with emphasis on neoplastic alterations." J Urol. 2008;180(6):2463-2467. doi:10.1016/j.juro.2008.08.040