Urethral Prolapse Repair (Female)
Female urethral prolapse is the complete circumferential eversion of urethral mucosa through the external meatus. For pathophysiology, presentation, diagnosis and differential, see the clinical-conditions article: Urethral Prolapse.
The condition has a bimodal distribution (prepubertal girls and postmenopausal women), and management depends on age, symptoms and tissue viability: conservative treatment for selected uncomplicated cases, prompt surgery for severe or ischemic presentations.
Indications for Surgical Intervention
In prepubertal girls with mild symptoms, conservative care can be used.[1] Surgery is indicated for:[1][2][3][4]
- Failed conservative management (persistent prolapse despite an adequate trial of topical estrogen and sitz baths).
- Vascular compromise. Thrombosis, necrosis, or gangrene of the prolapsed mucosa.
- Significant or recurrent bleeding.
- Acute urinary retention.
- Persistent pain.
- Severe symptoms at presentation: large, symptomatic prolapse unlikely to respond to conservative measures.
Acute thrombosed prolapse represents a surgical urgency.[3]
Conservative Management
| Modality | Notes |
|---|---|
| Topical estrogen cream | Used to counteract hypoestrogenism; regimens vary (2 weeks of estrogen cream, antibiotics and sitz baths in Richardson) |
| Sitz baths | Warm soaks to reduce edema and improve hygiene |
| Antibiotics | Treat documented infection when present; routine antibiotic prophylaxis is not established |
| Treat precipitants | Constipation, chronic cough, straining |
Reported response rates with conservative therapy:[1][2][5][6]
- Richardson 1982: 5/5 (100%) prepubertal girls resolved with antibiotics, estrogen and sitz baths over 2 weeks; no recurrence at 4–12 mo.
- Holbrook & Misra 2012: of 21 girls, 13 with mild symptoms were managed conservatively, seven underwent reduction under GA, and one underwent examination under anesthesia; the report gives no separate response fraction for conservative care.
- Carley 2002: partial response to estrogen in a 90-year-old; surgery was ultimately required.
- Yang & Huang 2004: regression after 1 wk of estrogen, antibiotics and sitz baths in a postmenopausal woman, confirmed by ultrasound.
Reduction Under General Anesthesia (Pediatric)
Holbrook & Misra (2012) introduced manual reduction under GA as a novel intermediate step between conservative therapy and excision in girls.[1]
- 7 girls with more symptomatic prolapse underwent reduction under GA.
- Complete reduction in 3/7; the remaining 4 had partial reduction and continued conservative therapy, with 2 resolving over 3 months and 2 keeping minimal residual prolapse.
- One recurrence occurred, 2 years after reduction, in a patient with severe chronic constipation.
- The authors concluded that surgical excision is almost never required in girls (retrospective case series, level of evidence 4).
Four-Quadrant Excisional Technique
The four-quadrant technique has been described for symptomatic prolapse. Shurtleff and Barone reported its use in three girls.[7] Hall et al. reported 26 excisions of prolapse or caruncle; most used a four-quadrant variant, while earlier cases used traction and excision.[4] Pfeuti and Linder described one thrombosed case in a 77-year-old woman.[3]
Step-by-Step Technique
- Positioning. Dorsal lithotomy under general anesthesia (regional or local in selected adults).
- Endoscopic assessment. In Hall et al.'s commonly used four-quadrant approach, cystoscopy assessed the extent of prolapse before excision.[4] Pfeuti and Linder performed rigid urethroscopy to assess proximal coaptation in one thrombosed adult case.[3]
- Catheter placement. If a catheter is used through the meatus to identify the lumen and guide excision, choose an age- and anatomy-appropriate size; Noya-Mourullo et al. used 16 Ch in adult women, while the Hall/Shurtleff four-quadrant approach permits excision without a catheter.[4][7][15] Some surgeons omit the catheter, since it can be difficult to work around during excision; when used and postoperative swelling is significant, it may be removed after one day.[14]
- Traction and delineation. Bilateral Allis clamps on the prolapsed tissue to delineate redundant mucosa from surrounding vaginal epithelium.[3]
- Stay sutures. Absorbable stay sutures (4-0 Vicryl) are placed in the urethral mucosa proximal to the planned incision line to prevent mucosal retraction upon excision.[3]
- Quadrant-by-quadrant excision. The prolapsed tissue is divided into four quadrants (12–3, 3–6, 6–9, 9–12 o'clock):
- Begin at the 12 to 3 o'clock quadrant (the least edematous area).
- Incise using needlepoint electrocautery at the urethral junction laterally and healthy mucosa medially.[3]
- Excise circumferentially, preserving the underlying urethral wall.
- Each quadrant is excised and immediately sutured before proceeding to the next, which prevents circumferential mucosal retraction.[7]
- Mucosal reapproximation. Join residual urethral mucosa to the adjacent mucosal edge with interrupted absorbable sutures, preserving an everted, non-stenotic meatus.[7] Hall et al. used 3-0 Vicryl to perimeatal mucosa; Noya-Mourullo et al. used 4-0 absorbable sutures to the vaginal rim in postmenopausal women; and Pfeuti and Linder joined vaginal epithelium in one 77-year-old thrombosed case.[3][4][15]
- Dependent quadrants last. The 6 o'clock (posterior) quadrants are excised last because they are the most edematous and friable.[3]
- Catheter management. Caliber and duration depend on age, anatomy, edema, and extent of excision. In Hall et al.'s protocol, a recovery-room voiding trial followed excision of <50% of mucosal circumference; after more extensive excision, Foley drainage continued for 3–4 days before an office voiding trial.[4] An adult 18-Fr protocol should not be applied to children.[3][8]
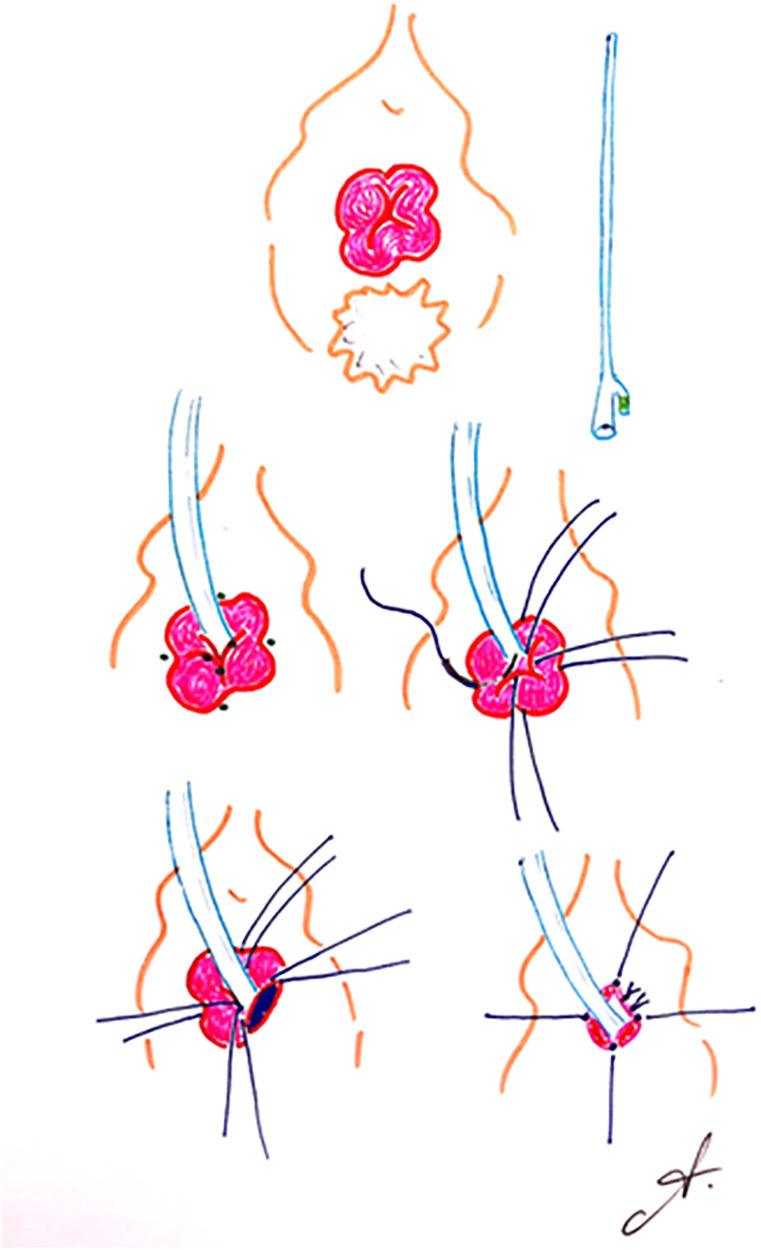
Four-point (four vertex) technique for urethral prolapse, drawn by the first author: circumferential prolapsed urethral mucosa at the meatus; catheter placed and four cardinal points marked; sutures placed at the four points; quadrant excision of the prolapsed mucosa; completed meatal reconstruction around the catheter. From Noya-Mourullo A, et al. Front Surg. 2023;10:1149729, Figure 1 (CC BY 4.0).[15]
Technical Pearls
- Excise one quadrant at a time and suture immediately; this prevents retraction.[7]
- Place proximal stay sutures before excision.[3]
- Start with the least edematous quadrant; finish with the most dependent / edematous.[3]
- Reapproximate urethral mucosa to adjacent mucosa, not skin, to create a well-everted meatus; the external edge may be perimeatal or vestibular mucosa, while vaginal epithelium was used in one thrombosed adult case.[3][4][7]
- Lowe 1986, on histology of two specimens, proposed that prolapse results from poor attachment between the urethral smooth-muscle layers and noted that obliteration of the cleavage plane between them is important for successful treatment.[9]
Historical Techniques (Largely Abandoned)
| Technique | Rationale | Why Abandoned | Reference |
|---|---|---|---|
| Ligation over a Foley | Ligature around the prolapsed base over an indwelling Foley → ischemic sloughing | High partial-recurrence, infection, and pain rates (Fernandes 1993) | [10] |
| Cautery / fulguration | Electrocautery or chemical cautery of the prolapsed mucosa | Traditional approach; replaced by medical therapy and excision | [2] |
| Cryosurgery | Freezing of the prolapsed tissue | Traditional approach; not currently used | [2] |
Reported Outcomes by Management Strategy
| Series | n | Age range | Technique | Complications | Recurrence |
|---|---|---|---|---|---|
| Hall 2017[4] | 26 (prolapse or caruncle; subtype counts not reported) | 3–81 (mean 38.8) | Excision, mostly a four-quadrant variant; earlier traction and excision | Among 24 with follow-up: 6 minor bleeds, 1 further bleed requiring Foley tamponade, and 1 urinary retention | 3/24 had visible recurrent prolapse in the mixed cohort (12.5%); 1 re-excised; median follow-up 38 days |
| Hillyer 2009[8] | 34 | All age groups; pediatric emphasis | Most underwent circumferential excision over Foley | None major reported | Not specified |
| Fernandes 1993[10] | 23 | Pediatric | Conservative / ligation / excision | Ligation: high complication rate; complete excision gave the best results | Ligation: partial recurrence |
| Holbrook 2012[1] | 21 | 2–15 | Conservative (13); reduction under GA (7); examination under GA (1) | None reported | One recurrence 2 years after reduction (1 of 7 reduced) |
| Pfeuti 2026[3] | 1 | 77 | Four-quadrant excision (acute thrombosed) | Not reported | Not reported |
| Noya-Mourullo 2023[15] | 17 women; 19 procedures | Postmenopausal (mean 70.4 yr) | Four-vertex excision | 14/17 asymptomatic; 2 dysuria; 1 urgency; preoperative incontinence resolved in 9/10, with 1 later requiring a suburethral tape; 3 reported impaired sexual activity; no meatal stenosis observed (final follow-up duration unspecified) | Not reported |
| Shurtleff 2002[7] | 3 | 4–8 | Four-quadrant excision | Not reported | Not reported |
Complications of Excision
- Postoperative bleeding. Six of 24 patients with available follow-up (25%) had minor bleeding that resolved spontaneously; one further patient required Foley tamponade for persistent bleeding in Hall et al.[4]
- Urinary retention. Temporary; 1/24 (about 4%) with available follow-up in Hall et al.[4]
- Meatal stenosis. Recognized risk of circumferential excision.[1] The four-quadrant technique with mucosal reapproximation was designed to preserve a non-stenotic meatus.[7]
- Recurrence. In Hall et al.'s mixed prolapse/caruncle excision cohort, 3/24 patients with follow-up (12.5%) had visible recurrent prolapse (median follow-up 38 days); 1 of the 3 underwent re-excision.[4]
- De novo SUI. Theoretically possible with excessive tissue removal; not specifically reported in the prolapse literature.
Treatment Algorithm
The approach below follows the algorithm proposed by Hall et al. (2017), with the pediatric step taken from Holbrook & Misra.[1][4] Zuo & Napoe (2023) similarly recommended that meatal lesions can be managed conservatively first but should be excised in the setting of thrombosis, significant or recurrent bleeding, acute urinary retention, or persistent pain.[11]
| Presentation | Recommended Treatment |
|---|---|
| Asymptomatic / mild symptoms | Conservative management (topical estrogen, sitz baths, observation) |
| Moderate symptoms; failed conservative | Surgical excision (four-quadrant technique) |
| Severe at presentation (thrombosis, necrosis, significant bleeding, retention) | Expedited surgical excision |
| Recurrence after excision | Re-excision if symptomatic |
| Pediatric symptomatic | Consider reduction under GA before excision (Holbrook intermediate step) |
Specimen Pathology
For an uncertain meatal lesion or a patient with prior malignancy, obtain a biopsy to establish the diagnosis.[4] Submit excised prolapse tissue for histopathological examination, particularly in postmenopausal women or when a meatal lesion is atypical; benign meatal lesions can mimic malignancy, and one of 17 women in an adult prolapse excision series had urothelial dysplasia.[15][12]
Special Surgical Considerations
- Acute thrombosed prolapse. The standard four-quadrant technique is technically challenging because of tissue friability and edema. In one 77-year-old woman with acute thrombosis, Pfeuti and Linder used proximal stay sutures, began in the least edematous quadrant and used needlepoint electrocautery.[3]
- Postmenopausal patients with concomitant pelvic-organ prolapse. Carley 2002 described a 90-year-old woman with concomitant urethral and uterovaginal prolapse who ultimately required surgery.[5]
- Pediatric patients. Urethral prolapse must be recognized to avoid misdiagnosis as sexual abuse. The circumferential appearance with a central urethral lumen supports prolapse. Absence of trauma signs does not exclude abuse; assess the history and any safeguarding concerns separately.[13][7][10]
See Also
- Urethral Prolapse (clinical conditions): pathophysiology, presentation, diagnosis, differential
- Female Urethral Reconstruction (atlas)
- Distal Urethrectomy with Advancement Meatoplasty
- Female Urethral & Periurethral Masses
Videos
References
1. Holbrook C, Misra D. "Surgical Management of Urethral Prolapse in Girls: 13 Years' Experience." BJU Int. 2012;110(1):132–4. doi:10.1111/j.1464-410X.2011.10752.x
2. Richardson DA, Hajj SN, Herbst AL. "Medical Treatment of Urethral Prolapse in Children." Obstet Gynecol. 1982;59(1):69–74. PMID: 7078852
3. Pfeuti CK, Linder BJ. "Management of Acute Thrombosed Urethral Prolapse." J Minim Invasive Gynecol. 2026;33(6):674-675. doi:10.1016/j.jmig.2026.01.032
4. Hall ME, Oyesanya T, Cameron AP. "Results of Surgical Excision of Urethral Prolapse in Symptomatic Patients." Neurourol Urodyn. 2017;36(8):2049–55. doi:10.1002/nau.23232
5. Carley ME, Klingele CJ, Boldt KL, Gebhart JB. "Concomitant Urethral and Uterovaginal Prolapse in a Postmenopausal Woman: A Case Report." J Reprod Med. 2002;47(11):939–42. PMID: 12497686
6. Yang JM, Huang WC. "Transperineal Sonographic Findings in a Woman With Urethral Mucosa Prolapse." J Clin Ultrasound. 2004;32(5):261–3. doi:10.1002/jcu.20026
7. Shurtleff BT, Barone JG. "Urethral Prolapse: Four Quadrant Excisional Technique." J Pediatr Adolesc Gynecol. 2002;15(4):209–11. doi:10.1016/s1083-3188(02)00157-2
8. Hillyer S, Mooppan U, Kim H, Gulmi F. "Diagnosis and Treatment of Urethral Prolapse in Children: Experience With 34 Cases." Urology. 2009;73(5):1008–11. doi:10.1016/j.urology.2008.10.063
9. Lowe FC, Hill GS, Jeffs RD, Brendler CB. "Urethral Prolapse in Children: Insights Into Etiology and Management." J Urol. 1986;135(1):100–3. doi:10.1016/s0022-5347(17)45530-3
10. Fernandes ET, Dekermacher S, Sabadin MA, Vaz F. "Urethral Prolapse in Children." Urology. 1993;41(3):240–2. doi:10.1016/0090-4295(93)90565-r
11. Zuo SW, Napoe GS. "Evaluation and Management of Urethral and Periurethral Masses in Women." Curr Opin Obstet Gynecol. 2023;35(6):517–24. doi:10.1097/GCO.0000000000000914
12. Conces MR, Williamson SR, Montironi R, et al. "Urethral Caruncle: Clinicopathologic Features of 41 Cases." Hum Pathol. 2012;43(9):1400–4. doi:10.1016/j.humpath.2011.10.015
13. Canadian Paediatric Society. The medical evaluation of pre-pubertal children with suspected sexual abuse. Position statement.
14. Gebhart JB. Surgical Repair of Urethral Prolapse. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1029-1030.
15. Noya-Mourullo A, Herrero-Polo M, Heredero-Zorzo O, García-Gómez F, Urrea-Serna C, Marquez-Sanchez MT, et al. Four vertex technique for correcting urethral prolapse: technique description and cohort study. Front Surg. 2023;10:1149729. doi:10.3389/fsurg.2023.1149729.