Ventral Onlay Glanuloplasty
Ventral onlay glanuloplasty (VOG) is a single-stage buccal mucosal graft reconstruction for selected fossa-navicularis strictures. Wayne and colleagues described a ventral glans incision with graft onlay and closure without extensive glans-wing mobilization. The reported outcome cohort excluded lichen sclerosus.[1]
Indications
The AUA guideline allows dilation or meatotomy, with or without a guidewire, for a first, uncomplicated stricture confined to the meatus or fossa navicularis when it is not associated with previous hypospadias repair, failed endoscopic treatment, previous urethroplasty or lichen sclerosus.[2] Surgeons should offer urethroplasty for recurrent meatal or fossa-navicularis strictures .[2] VOG has been described for selected isolated fossa-navicularis strictures. Its 10-patient outcome cohort comprised iatrogenic cases without LS.[1]
Selection
Define distal stricture extent and tissue quality before choosing VOG, transmeatal grafting, meatoplasty or staged reconstruction. The published series addressed fossa-navicularis disease and permitted separately treated proximal skip strictures. Its median stricture length was 2 cm, with some longer strictures included, and causes were mainly iatrogenic (transurethral prostate resection 4/10, GreenLight laser vaporization 2/10, cystolitholapaxy 1/10, traumatic catheterization 3/10).[1] The VOG cohort excluded LS, so it provides no LS-specific outcome estimate.[1] For LS-related penile strictures, EAU guidance recommends avoiding genital skin for augmentation and performing single-stage oral mucosa graft urethroplasty when local tissue conditions permit . For meatal and fossa-navicularis strictures, it recommends offering open meatoplasty or distal urethroplasty .[3]
The ten analyzed patients came from 11 VOG repairs among 17 fossa-navicularis repairs in a single-surgeon database of 151 urethroplasties.[1] Lichen sclerosus was associated with recurrence: in a two-center series of 93 distal repairs, recurrence was 20.5% with LS and 7.5% without it.[4] Prior hypospadias repair is another cause; it accounted for 16 of 32 patients (50%) in a single-center series of dorsal inlay BMG repair for meatal and fossa strictures.[5]
Technique Overview
The following summarizes the published technique.[1]
- Place a traction suture on the glans (2-0 silk in the published series) and pass a sensor wire through the stricture if possible. Open the ventral glans and urethra in the midline from the meatus to healthy proximal mucosa, place mucosal stay sutures, and perform cystoscopy to identify additional narrowing.[1]
- Harvest, defat and tailor buccal mucosa. Wayne and colleagues describe adding a dorsal Asopa inlay when narrowing is particularly severe; their reported 10-patient VOG outcome cohort excluded repairs with this adjunct.[1] Anastomose the graft longitudinally to the ventral urethrotomy margins to augment the distal lumen, with interrupted sutures at the apex and a running 5-0 PDS suture along the lateral edges over a 20 Fr red rubber catheter.
- Cover the graft with dartos tissue and reapproximate the glans without extensive glans-wing undermining. Mature the distal graft edge to the glans to form the neomeatus.
- Check caliber and tension, then catheterize. The authors discharged patients with a Foley catheter that was removed at the 3-week visit, when patency was assessed with voiding cystourethrography (VCUG).
Dartos fascia covers the graft. The glans edges are closed with a deep horizontal mattress suture followed by interrupted sutures, without extensive glans-wing undermining.[1]
Outcomes and Limits
Of 11 treated patients, one with LS was excluded from the reported analysis. Success required no extravasation on VCUG at 3 weeks and no later dilation or other instrumentation. Nine of ten analyzed patients met this definition at median 30-month follow-up (IQR 24.3–36.8); one recurrence, at 419 days, required dilation and triamcinolone. All ten reported satisfaction with appearance, and no 30-day complications were recorded. This is a small uncontrolled retrospective series.[1]
A related single-stage ventral onlay BMG repair for fossa-navicularis strictures, reported in six patients, gave a mean flow rate of 12 mL/s at 3 months, no fistula, and one recurrence at a more proximal site at median 37-month follow-up.[6]
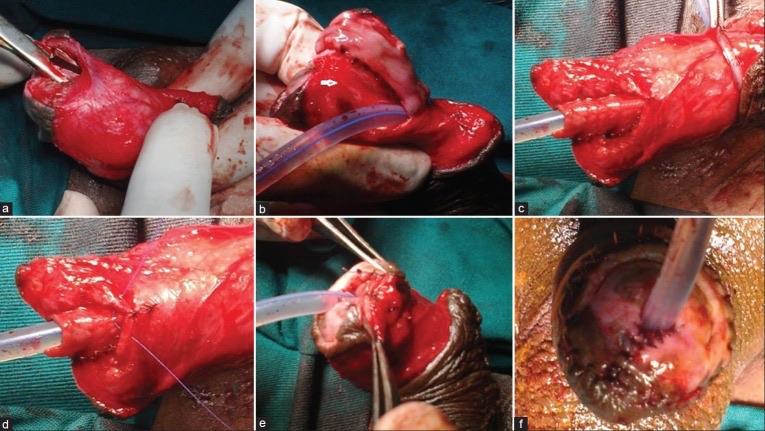
The related single-stage ventral onlay buccal mucosal graft (BMG) repair. (a) The stenosed meatus is opened ventrally up to the corona. (b) BMG sutured to one side of the preserved dorsal mucosal strip (white arrow). (c) BMG rolled over a 24 Fr catheter and sutured to the other free edge of the mucosal strip. (d) First layer of glans wings approximated with an anchoring suture on the ventral BMG. (e) Glans wings closed in three layers. (f) Neomeatus formed by suturing the distal graft along the initial ventral meatal slit, allowing free movement of a 24 Fr catheter. From Chowdhury PS, et al. Indian J Urol. 2014;30(1):17-22, Figure 2 (CC BY-NC-SA).[6]
Functional outcomes and complications are reported in more detail for the glans-sparing transurethral repairs. A 2023 single-center ventral-inlay series reported 42/44 (95%) patent without further intervention at mean 36 months; two recurrences extended proximally.[11] In the 12-institution ventral inlay series, median Qmax rose from 5 to 18 mL/s and median IPSS fell from 15 to 5, and no patient developed a fistula, glanular dehiscence, graft necrosis or chordee.[7] In the transurethral dorsal inlay series, urinary tract infection occurred in 25%, with no de novo erectile dysfunction, chordee or wound infection, and all satisfaction respondents were satisfied or very satisfied.[8]
Comparison With Alternatives
| Technique | Study | n | Follow-up | Result |
|---|---|---|---|---|
| VOG | Retrospective series[1] | 10 | Median 30 months | 9 of 10 successful; no 30-day complications |
| Meatotomy or meatoplasty, including substitution in some meatoplasties | Two-center series[4] | 93: 73 meatotomy, 20 meatoplasty; 13/20 meatoplasties used substitution | Mean 61 months (distal urethroplasty) | No further intervention in 84% overall; reported subgroup success was 87% for meatotomy, 75% for meatoplasty and 66% for substitution within meatoplasty |
| Ventral transverse penile skin island flap (Jordan flap) | Original description[9] | 5 | Median 17 months | Excellent cosmetic and functional results in all 5 |
| Tailored mixed reconstruction (16 penile skin flaps, 2 primary anastomoses, 1 buccal graft) | Single-center series[10] | 19 | Mean 42.7 months | Durable functional and cosmetic success in 18 (94.7%) |
| Dorsal inlay BMG through the opened glans | Single-center series[5] | 32 | Median 42 months | Success 69%; recurrence-free survival 79% at 12 and 74% at 24 months |
| Transurethral ventral BMG inlay (glans-sparing) | Multi-institutional series[7] | 68 enrolled; 57 with at least 12 months of follow-up | Median 17 months among followed patients | 54/57 (95%) stricture-free |
| Transurethral dorsal inlay BMG (glans-sparing) | Single-center series[8] | 16 | Median 28.8 months | Anatomic success 15 of 16 (93.8%); functional success 16 of 16 |
The studies differ in etiology mix, LS inclusion, definition of success and follow-up, and none is randomized. The glans-sparing transurethral inlays avoid any external glans incision, whereas VOG opens the ventral glans but avoids extensive glans-wing mobilization.[1][7][8] Larger distal substitution series report lower success rates (66% and 69%) than the ten-patient VOG series.[4][5]
See Also
- Buccal Mucosa Graft
- Meatotomy and Meatoplasty
- Distal Urethral Reconstruction
- Lichen Sclerosus
- Urethral Stricture
References
1. Wayne G, Perez A, Demus T, et al. Ventral onlay glanuloplasty for treatment of fossa navicularis strictures. Int Braz J Urol. 2022;48(5):798–804. doi:10.1590/S1677-5538.IBJU.2022.0067. Full text.
2. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
3. EAU Guidelines on Urethral Strictures: disease management in males. Guideline. Accessed September 12, 2026.
4. Meeks JJ, Barbagli G, Mehdiratta N, Granieri MA, Gonzalez CM. "Distal Urethroplasty for Isolated Fossa Navicularis and Meatal Strictures." BJU Int. 2012;109(4):616–619. doi:10.1111/j.1464-410X.2011.10248.x
5. Zumstein V, Dahlem R, Maurer V, et al. "Single-Stage Buccal Mucosal Graft Urethroplasty for Meatal Stenoses and Fossa Navicularis Strictures: A Monocentric Outcome Analysis and Literature Review on Alternative Treatment Options." World J Urol. 2020. doi:10.1007/s00345-019-03035-8. PMID 31786639
6. Chowdhury PS, Nayak P, Mallick S, Gurumurthy S, David D, Mossadeq A. "Single Stage Ventral Onlay Buccal Mucosal Graft Urethroplasty for Navicular Fossa Strictures." Indian J Urol. 2014;30(1):17–22. doi:10.4103/0970-1591.124200. PMID 24497676
7. Daneshvar M, Simhan J, Blakely S, et al. "Transurethral Ventral Buccal Mucosa Graft Inlay for Treatment of Distal Urethral Strictures: International Multi-Institutional Experience." World J Urol. 2020;38(10):2601–2607. doi:10.1007/s00345-019-03061-6. PMID 31894369
8. Farrell MR, Campbell JG, Zhang L, et al. "Transurethral Reconstruction of Fossa Navicularis Strictures With Dorsal Inlay Buccal Mucosa Graft Urethroplasty." World J Urol. 2022;40:1523–1528. doi:10.1007/s00345-022-03994-5
9. Jordan GH. "Reconstruction of the Fossa Navicularis." J Urol. 1987;138(1):102–104. doi:10.1016/S0022-5347(17)43006-0. PMID 3599186
10. Armenakas NA, Morey AF, McAninch JW. "Reconstruction of Resistant Strictures of the Fossa Navicularis and Meatus." J Urol. 1998;160:359–363. doi:10.1016/S0022-5347(01)62895-7
11. Sterling J, Daneshvar M, Nikolavsky D. "Transurethral ventral inlay buccal mucosa graft urethroplasty: technique and intermediate outcomes." BJU Int. 2023;132(1):109-111. doi:10.1111/bju.16007