Ventral Onlay Oral Mucosal Graft Urethroplasty
Ventral onlay oral mucosal graft (OMG) urethroplasty is a substitution urethroplasty that augments a ventral urethrotomy with a free buccal or lingual mucosal graft. In male bulbar repair, the corpus spongiosum is closed over the graft.[4] In the cited female series, periurethral fascial flaps support the graft.[7] In a survey of GURS members conducted in 2022 and published in 2024, 34% of 134 respondents preferred ventral placement for bulbar grafting.[2] Comparative evidence has not shown a clear difference in patency, and sexual-function results vary.[1][2]
For the dorsal alternative, see Dorsal Onlay OMG Urethroplasty. For graft material, see Buccal Mucosa Graft. For the focal-obliterative-segment hybrid, see Augmented Anastomotic Urethroplasty.
Indications
- Proximal bulbar urethral strictures. The thick corpus spongiosum provides mechanical and vascular support to the graft.[3][4]
- Bulbar strictures too long for excision and primary anastomosis (generally > 2 cm; the randomized trial enrolled incomplete strictures longer than 2 cm)[4][12]
- Selected bulbomembranous strictures after TURP[6]
- Non-traumatic strictures of various etiologies (idiopathic, iatrogenic, inflammatory)[3]
- Female urethral strictures. Ventral onlay is one option, using periurethral fascial flaps for support. It uses transvaginal exposure, described on the dedicated Female Ventral Onlay Urethroplasty page; neither ventral nor dorsal repair is preferred for every woman.[7][16]
The AUA Urethral Stricture Disease Guideline Amendment (2023) names oral mucosa as the first-choice graft and states that buccal and lingual mucosal grafts may be used as equivalent alternatives .[8]
Rationale for ventral placement
The ventral approach is suited to the proximal bulbar urethra for the following reasons:[3][4][10]
- The corpus spongiosum is thickest in the proximal bulb, providing a vascularized bed for graft take via imbibition and inosculation.
- The technique requires less urethral mobilization than the classic dorsal onlay (Barbagli); the urethra does not need to be rotated 180°.
- The intercrural space is not dissected. The authors of a proximal bulbar comparison propose that this, with less urethral mobilization, explains the better erectile outcomes they observed.[10]
- The ventral surface is more directly accessible through a perineal approach.
Surgical Technique
Positioning and exposure
- Patient in lithotomy; perineal midline incision.
- The bulbospongiosus muscle is divided in the midline to expose the corpus spongiosum.[3][4]
Key steps
- Ventral urethrotomy. The corpus spongiosum is incised ventrally in the midline through the strictured segment. The urethrotomy extends into healthy urethra proximally and distally.[3][4]
- Stricture assessment. Inspect the lumen and confirm stricture length, severity, and whether a usable urethral plate remains. An obliterative or nearly obliterative segment may require augmented anastomotic or two-sided graft repair.[4][18] For a standard ventral onlay, the urethra is not mobilized circumferentially from the corpora cavernosa.[4][10]
- Graft harvest. Buccal mucosa is harvested from the inner cheek, or lingual mucosa from the ventrolateral tongue. The graft is defatted and tailored, typically matching the length and width of the urethrotomy.[3][8] Morey and McAninch (1996) described a two-team approach in which one team harvests the graft from the mouth while the perineal team exposes and calibrates the stricture. In their 13 men with complex, refractory bulbar strictures treated with a nontubularized buccal onlay graft (concomitant penile flap or excision and primary anastomosis in 8), none required dilation or instrumentation at a median follow-up of 18 months, and operative time was shorter than with other forms of substitution urethroplasty.[17]
- Graft placement. The oral mucosal graft is placed on the ventral urethral surface with the epithelial side facing the lumen; interrupted or running absorbable sutures (typically 5-0 or 6-0 polyglycolic acid) may be used to attach it to the urethrotomy edges.[3][4] In the technique reported by Mousa et al., a urethral catheter is passed after proximal graft fixation, and graft-edge suturing is completed over it before spongiosal closure.[10]
- Spongioplasty. The corpus spongiosum is closed over the graft in the midline, providing a vascularized tissue bed that supports graft take and helps limit graft sacculation or diverticulum formation. Spongioplasty is specific to the ventral approach.[11]
- Closure and catheter plan. Bulbospongiosus muscle and perineal tissues are closed in layers. A urethral catheter (typically 16–18 Fr) is left in place.[3] After urethroplasty, catheterization commonly lasts two to three weeks. EAU 2026 strongly recommends validated urethrography to assess for urinary extravasation before catheter removal; persistent significant extravasation calls for continued catheter drainage and repeat assessment after one week.[20] After male graft substitution urethroplasty, EAU 2026 strongly recommends at least one year of routine follow-up.[21] Its proposed standard-risk schedule includes uroflowmetry, patient-reported urinary and sexual outcomes, and anatomic assessment at 3, 12 and 24 months.[21]
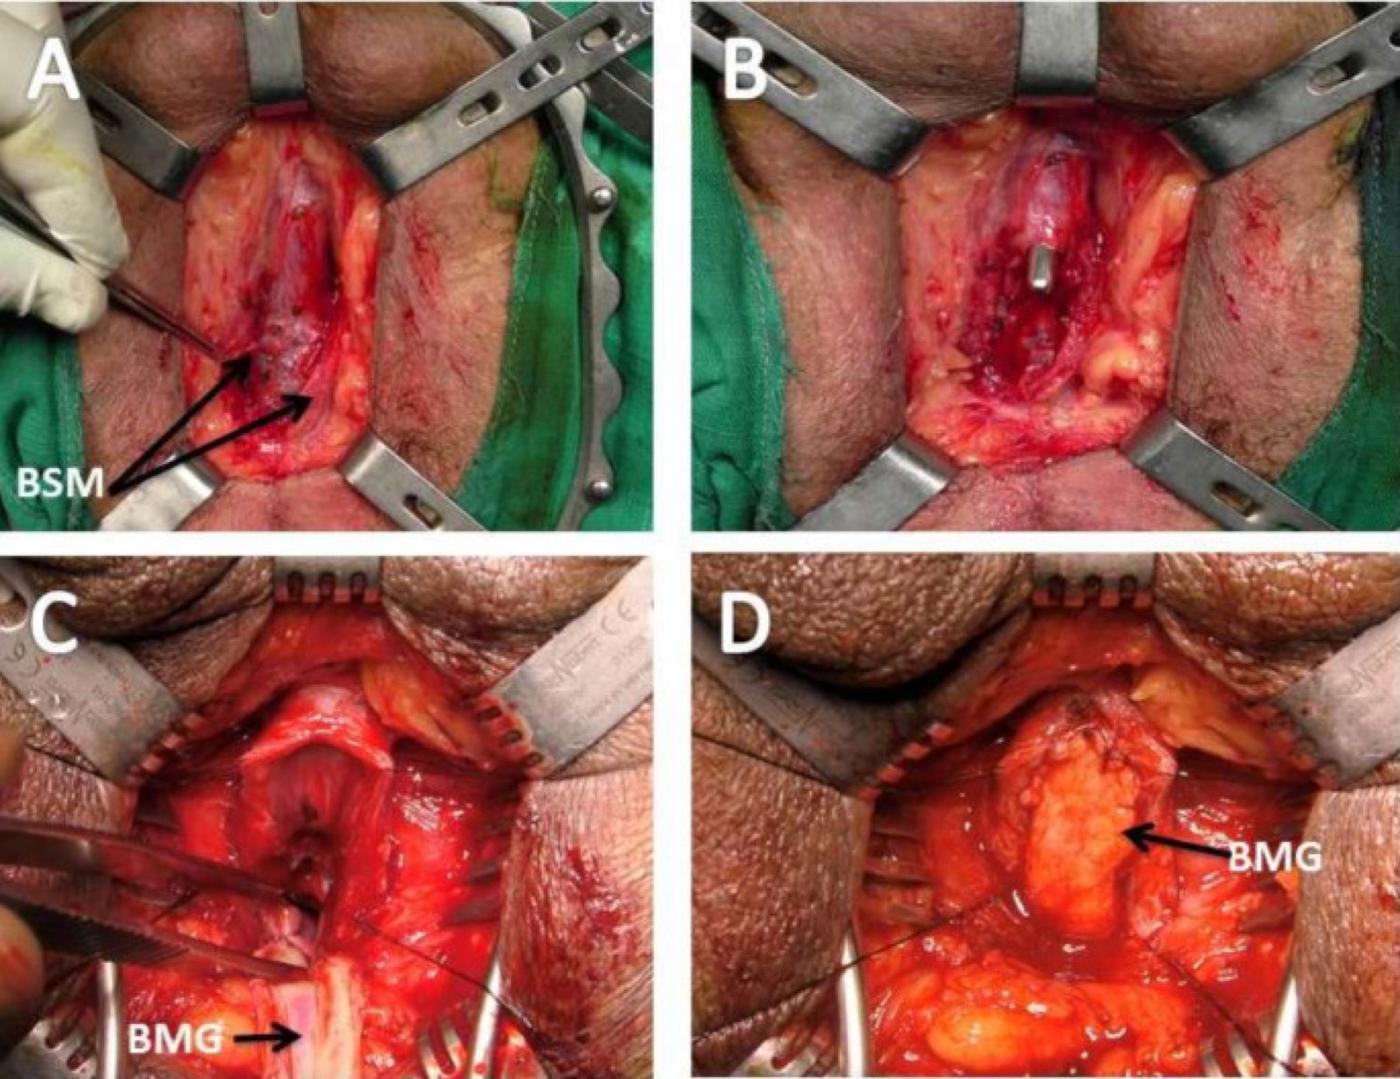
Ventral onlay buccal mucosal graft urethroplasty: (A) bulbospongiosus muscle (BSM) divided in the midline to expose the bulb; (B) urethra opened ventrally over a 16 Fr urethral dilator; (C) proximal anastomosis of the buccal mucosal graft (BMG) to the urethra with three interrupted sutures; (D) graft sutured to both urethral edges over a 16 Fr urethral catheter. From Mousa A, et al. World J Urol. 2025;43(1):87, Fig. 1 (CC BY 4.0).
Spongioplasty and pseudospongioplasty
Spongioplasty, closure of the corpus spongiosum over the ventral graft, stabilizes and vascularizes the graft. In the pendulous and distal bulbar urethra the spongiosum is often too thin for adequate coverage. When spongiosal tissue is inadequate for graft coverage, Cordon et al. described pseudospongioplasty as an option: periurethral vascularized tissue flaps are mobilized bilaterally and sutured together in the midline over the graft.[11] A two-surgeon retrospective comparison reported success in 37/46 pseudospongioplasties (80%, mean follow-up 41 months) versus 47/56 conventional repairs (84%, 39 months; p = 0.645). Stricture distributions and lengths differed (mean 5.8 versus 4.7 cm).[11]
Outcomes
| Study | n | Success | Follow-up | Key Findings |
|---|---|---|---|---|
| Barbagli 2013, single center[3] | 214 | 85.5% | median 54 mo | Nontraumatic bulbar strictures 1.3–6.8 cm (LS, panurethral and failed hypospadias excluded). Preoperative Qmax was the only significant predictor of outcome (OR 1.35, p = 0.001) |
| Vasudeva 2015, RCT ventral vs dorsal[12] | 80 (40 / arm) | 90% ventral vs 92.5% dorsal | 12 mo | Incomplete bulbar strictures longer than 2 cm; no significant difference in IPSS, Qmax or success |
| Shalkamy 2023, retrospective[13] | 165 | 87.1% ventral vs 88.3% dorsal | mean 52 mo | No significant difference in erectile or voiding outcomes |
| Mousa 2025, retrospective, proximal bulbar in sexually active men[10] | 133 | 91.7% ventral vs 90.4% dorsal (failure: obstructive voiding with cystoscopic or radiographic recurrence) | 12 mo | Ventral had significantly higher IIEF scores and lower observed ED rates at 3 and 12 months; imaging/endoscopy was considered for poor-flow complaints |
| Hassan 2025, meta-analysis[1] | 655 (8 studies) | RR 1.00 (no difference) | variable | Transient ED significantly lower with ventral (RR 0.24, p = 0.006) |
| Mousa 2024, post-TURP bulbomembranous[6] | 30 | 90% (3 recurrences) | 12 mo | Mean Qmax 19.1 mL/s at 12 months; 2 patients with postoperative incontinence |
| Cordon 2014, pseudospongioplasty[11] | 102 | 80% pseudospongioplasty; 84% conventional | 39–41 mo | Nonrandomized groups with different stricture locations; no significant success difference |
The European Urology systematic review of 41 studies (3,683 patients) concluded that no single technique appears superior for bulbar free-graft urethroplasty, with both dorsal and ventral onlay achieving ≤20% recurrence over medium-term follow-up.[5] In a later single-center survey, 10/104 respondents had required secondary treatment for recurrent symptoms by survey follow-up.[19] Median follow-up for respondents was 7.4 years.[19] The response rate was 20%, 38% had a partial-thickness augmented anastomotic component, and anatomical patency was not measured.[19]
Advantages
- Less urethral mobilization. The urethra is not circumferentially mobilized or rotated, which may preserve dorsal blood supply and reduce operative complexity.[4][10]
- No intercrural-space dissection. This is a proposed explanation for the lower transient-ED rates.[10]
- Transient-ED signal. A 2025 meta-analysis reported lower transient ED after ventral than dorsal onlay (RR 0.24, 95% CI 0.08–0.67; p = 0.006).[1] EAU 2026 strongly recommends choosing graft position by surgical practice, expertise and intraoperative findings.[18]
- Technically straightforward access. The ventral surface is directly accessible through a standard perineal incision without urethral rotation.[4]
- Graft bed in the proximal bulb. Thick spongiosum provides vascular support.[3]
- Applicable to female urethral strictures. One 42-patient, single-surgeon cohort reported 41/42 without recurrence at mean 38.1 months.[7]
Disadvantages and Limitations
- Graft sacculation or diverticulum. Without the rigid support of the corpora cavernosa (as in dorsal onlay), the graft may sacculate ventrally, particularly if spongioplasty is inadequate. Patterson and Chapple report that complications of ventral onlay tend to be more prevalent in series with longer follow-up.[9]
- Dependent on adequate spongiosum. In the pendulous urethra and distal bulbar urethra, the thin spongiosum may not provide sufficient graft coverage, necessitating pseudospongioplasty.[11] Severe spongiosal scarring after traumatic bulbar injury can leave a poor vascular bed for conventional ventral onlay grafting.[4]
- Penile strictures. Thin penile spongiosum limits ventral graft support. Patterson and Chapple (2008) favored staged repair or selected one-stage dorsal onlay based on their review of older series.[9] A later systematic review reported the best observed penile graft outcomes for dorsal onlay.[14] The EAU 2026 guideline finds no high-level evidence that one penile augmentation technique is superior and bases staging on stricture complexity and local tissue quality.[18]
- Technique selection. Patterson and Chapple conclude that outcomes of ventral and dorsal onlay are equivalent in experienced hands and suggest that dorsal onlay may be less dependent on surgical expertise, and so more suitable for surgeons new to urethroplasty.[9]
- Evidence limits. Comparative series differ substantially in selection and follow-up. Recurrence rates rise with longer follow-up for both dorsal and ventral onlay.[5]
Complications
- Stricture recurrence. 10–20% over medium-term follow-up; rates increase with longer follow-up.[3][5]
- Transient ED. 1.6–5%, significantly lower than dorsal onlay in meta-analysis.[1][10][13]
- Persistent ED. The pooled comparison is very imprecise (RR 0.57, 95% CI 0.03–12.20).[1]
- Graft sacculation or diverticulum. A potential complication; minimized by adequate spongioplasty.[9]
- Postoperative complications. In one retrospective series, 90-day complications occurred in 17.6% overall (15.5% dorsal, 19.4% ventral).[13]
- Urinary incontinence after post-TURP bulbomembranous repair. Two of 30 patients developed postoperative incontinence in the retrospective ventral-onlay cohort.[6] Across reconstructive approaches for bulbomembranous stricture after surgery for benign prostatic obstruction, EAU 2026 reports incontinence in up to 25% and strongly recommends counseling patients about de novo incontinence.[18]
- Postvoid dribbling and ejaculatory change. These may follow bulbar dissection and midline bulbospongiosus division. The EAU review reports postvoid dribbling in 20–21% of ventral-onlay series; evidence for routine muscle- and nerve-sparing modification is conflicting.[18]
- Fistula and diverticulum. The EAU review found two urethrocutaneous fistulas and one diverticulum in ventral-onlay series.[5][18]
- Donor-site morbidity. Donor-site morbidity is that of oral mucosa harvest and does not depend on graft placement (see Buccal Mucosa Graft).
Ventral vs. Dorsal Onlay — Evidence Summary
| Parameter | Ventral Onlay | Dorsal Onlay |
|---|---|---|
| Success rate in Mousa 2025 retrospective proximal-bulbar cohort | 91.7% (n = 60)[10] | 90.4% (n = 73)[10] |
| Meta-analysis RR (success) | 1.00 (95% CI 0.94–1.06; p = 0.97)[1] | — |
| Transient ED at 3 months in Shalkamy 2023 and Mousa 2025 | 1.6–5%[13][10] | 3.9–25%[13][10] |
| ED present at 12 months in Shalkamy 2023 and Mousa 2025 | 1.7–3.2%[10][13] | 1.9–13.7%[13][10] |
| Qmax at 12 months | comparable (MD −0.57, p = 0.43) | — |
| Urethral mobilization | No circumferential mobilization or rotation | Classic Barbagli requires circumferential mobilization and rotation; one-sided dorsal onlay uses unilateral mobilization[10] |
| Graft bed | corpus spongiosum | tunica albuginea of corpora cavernosa |
| Risk of sacculation | higher (theoretical) | lower (rigid corporal support) |
| Anatomic setting | Proximal bulb has thick spongiosum for ventral coverage; no bulbar graft position is established as best[3][18] | Bulbar and selected penile repairs; no bulbar graft position is established as best[14][18] |
| Surgeon preference among 134 GURS survey respondents for bulbar BMG | 34%[2] | 66%[2] |
The data on erectile function are conflicting across studies. The Hassan 2025 meta-analysis and Mousa 2025 found significantly lower transient ED with ventral onlay, whereas Shalkamy 2023 found no significant difference in IIEF scores or ED rates (transient ED 1.6% ventral versus 3.9% dorsal, p = 0.41).[1][10][13] The studies differ in patient population, stricture location (proximal versus distal bulbar) and the extent of urethral mobilization. Mousa's single-surgeon cohort compared dorsal repairs in 2019–2021 with ventral repairs in 2021–2023 after the center observed ED.[10]
Circumferential Grafting (Gelman) and the Palminteri Distinction
Gelman and Siegel described circumferential BMG replacement for selected totally or nearly obliterated anterior segments with intact corpus spongiosum, unsuitable for excisional or augmented anastomotic repair. The spongiosum was opened dorsally without transection: one graft was quilted to the corporal bodies and the other to the opened spongiosum, then their edges joined. Among 18 patients, one early recurrence was treated with DVIU; initial success was 94%, and all were subsequently free of obstructive stricture symptoms at mean 50 months.[15]
This differs from Palminteri double-face augmentation, which widens a salvageable native plate through ventral access. The plate requirement and incision sequence differ between the two operations.
Special Considerations
- Proximal bulbar strictures in sexually active men. Mousa's 133-patient retrospective study associated ventral placement with higher IIEF scores.[10]
- Post-TURP bulbomembranous strictures. In the cited retrospective cohort, 3/30 recurred and 2/30 developed postoperative incontinence.[6]
- Female urethral strictures. In the single-surgeon cohort, 41/42 patients were stricture-free at mean 38.1 months and none developed incontinence.[7] The EAU 2026 review pooled 247 women with ventral oral mucosal grafts (177 onlay, 70 inlay; 90.7% stricture-free at 6 to 38.1 months) and reported new stress incontinence in 8 (3.2%).[16] The guideline states that the urethroplasty technique should be determined by surgeon experience, availability and quality of graft or flap material, and quality of the ventral versus dorsal urethra.[16]
- Penile strictures. Thin ventral spongiosum may make dorsal or staged augmentation preferable; selected ventral repairs need an adequate vascular bed and coverage.[9][14]
- Preoperative Qmax as a predictor. In Barbagli's series, preoperative Qmax was the only significant predictor of surgical outcome (OR 1.352, p = 0.001), while age, stricture length, type of stenosis, and previous treatment were not significant predictors.[3]
Videos
References
-
Hassan AA, Soliman AM, Shouman HA, et al. Dorsal- vs ventral-onlay buccal mucosal graft urethroplasty for urethral strictures: a meta-analysis. BJU Int. 2025. doi:10.1111/bju.16811.
-
Berg C, Singh A, Hu P, et al. Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons. Urology. 2024;191:139-143. doi:10.1016/j.urology.2024.06.019.
-
Barbagli G, Montorsi F, Guazzoni G, et al. Ventral oral mucosal onlay graft urethroplasty in nontraumatic bulbar urethral strictures: surgical technique and multivariable analysis of results in 214 patients. Eur Urol. 2013;64(3):440-7. doi:10.1016/j.eururo.2013.05.046.
-
Horiguchi A. Substitution urethroplasty using oral mucosa graft for male anterior urethral stricture disease: current topics and reviews. Int J Urol. 2017;24(7):493-503. doi:10.1111/iju.13356.
-
Barratt R, Chan G, La Rocca R, et al. Free graft augmentation urethroplasty for bulbar urethral strictures: which technique is best? A systematic review. Eur Urol. 2021;80(1):57-68. doi:10.1016/j.eururo.2021.03.026.
-
Mousa A, Eissa A, Rawal AY, Zoeir A. Outcomes of ventral onlay buccal mucosal graft urethroplasty in bulbomembranous urethral strictures post-transurethral resection of the prostate. Urology. 2024;186:9-14. doi:10.1016/j.urology.2024.01.018.
-
Berdondini E, Eissa A, Margara A, et al. Ventral onlay buccal mucosa graft urethroplasty for female urethral stricture: medium-term results in a single surgeon experience. Urology. 2024;193:194-200. doi:10.1016/j.urology.2024.06.045.
-
Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
-
Patterson JM, Chapple CR. Surgical techniques in substitution urethroplasty using buccal mucosa for the treatment of anterior urethral strictures. Eur Urol. 2008;53(6):1162-71. doi:10.1016/j.eururo.2007.10.011.
-
Mousa A, Eissa A, Raheem AA, Zoeir A. Ventral versus dorsal onlay buccal mucosal graft urethroplasty for non-traumatic proximal bulbar urethral strictures in sexually active men: erectile and urinary functions. World J Urol. 2025;43(1):87. doi:10.1007/s00345-025-05441-7.
-
Cordon BH, Zhao LC, Scott JF, Armenakas NA, Morey AF. Pseudospongioplasty using periurethral vascularized tissue to support ventral buccal mucosa grafts in the distal urethra. J Urol. 2014;192(3):804-7. doi:10.1016/j.juro.2014.03.003.
-
Vasudeva P, Nanda B, Kumar A, et al. Dorsal versus ventral onlay buccal mucosal graft urethroplasty for long-segment bulbar urethral stricture: a prospective randomized study. Int J Urol. 2015;22(10):967-71. doi:10.1111/iju.12859.
-
Shalkamy O, Elatreisy A, Salih E, et al. Erectile and voiding function outcomes after buccal mucosa graft urethroplasty for long-segment bulbar urethral stricture: ventral versus dorsal onlay technique. World J Urol. 2023;41(1):205-210. doi:10.1007/s00345-022-04220-y.
-
Jasionowska S, Bochinski A, Shiatis V, et al. Anterior urethroplasty for the management of urethral strictures in males: a systematic review. Urology. 2022;159:222-234. doi:10.1016/j.urology.2021.09.003.
-
Gelman J, Siegel JA. Ventral and dorsal buccal grafting for 1-stage repair of complex anterior urethral strictures. Urology. 2014;83(6):1418-22. doi:10.1016/j.urology.2014.01.024.
16. EAU Guidelines on Urethral Strictures, 2026: disease management in females. https://uroweb.org/guidelines/urethral-strictures/chapter/disease-management-in-females. Accessed September 12, 2026.
17. Morey AF, McAninch JW. "When and how to use buccal mucosal grafts in adult bulbar urethroplasty." Urology. 1996;48(2):194-198. doi:10.1016/S0090-4295(96)00154-9
18. European Association of Urology. EAU Guidelines on Urethral Strictures, limited update 2026, sections 6.3.1.b and 6.3.2.e (disease management in males). Guideline. Accessed October 3, 2026.
19. Santiago JE, Gross MD, Accioly JPE, et al. "Decision regret and long-term success rates after ventral buccal mucosa graft urethroplasty." BJU Int. 2025;135(2):303-309. doi:10.1111/bju.16566
20. European Association of Urology. EAU Guidelines on Urethral Strictures, limited update 2026, section 10, Perioperative Care of Urethral Surgery. Guideline. Accessed October 5, 2026.
21. European Association of Urology. EAU Guidelines on Urethral Strictures, limited update 2026, section 11, Follow Up. Guideline. Accessed October 7, 2026.