Transperineal Reanastomosis (TPRA)
Transperineal reanastomosis (TPRA) uses perineal access, scar excision and proximal urethral mobilization to reconnect the urethra to the bladder outlet. It has been used for highly recurrent or obliterative VUAS after radical prostatectomy, as a last option before urinary diversion, and when prior abdominal surgery makes transabdominal access difficult. It mirrors the perineal approach to PFUI repair.[2][3] See primary reanastomosis for operative principles, the retropubic and robotic approaches and the original cohorts.
Patency and continence
In the initial Hamburg series, anastomotic patency was reported in 14/15 (93.3%) at a mean follow-up of 20.5 months; the extended cohort reported 20/23 (87%) without recurrent stricture at a median follow-up of 45 months.[2][3] The 23-patient series extends the earlier 15-patient experience. A later, partly overlapping Hamburg cohort of 46 men reported six VUAS retreatments, with Kaplan-Meier retreatment-free survival of 91% at two years and 88% at five years (median follow-up 80 months).[5] This endpoint is freedom from retreatment, rather than measured anatomical patency.[5] Only 1/46 men (2.2%) in this cohort had prior pelvic radiotherapy, so its outcome estimates chiefly describe patients without prior radiation.[5] The recurrence in the first series and all three in the extended series were treated endoscopically.[2][3] In the 46-man cohort, five of six retreatments were endoscopic; one patient required bladder-neck closure and suprapubic diversion.[5] Almost all patients were already incontinent: 14 of 15 in the first series, and all 23 in the extended series.[2][3] Incontinence worsened in 9 of 15 (60%) in the first series, and no de novo incontinence occurred.[2] At follow-up, erectile dysfunction was present in 13/15 men, and 5/15 (33.3%) reported worse erectile function than before TPRA.[2] AUS was implanted in 10 of 15 and 17 of 23 (73.9%).[2][3] In the later 46-man cohort, 30/46 (65%) received a staged AUS; 7/30 (23%) underwent explantation at median AUS follow-up of 97 months, including five for urethral erosion.[5] The extended 23-patient series reported complications in 2/23 (8.7%, Clavien-Dindo grades II–III), including rectal injury.[1][3]
Redo vesicourethral anastomosis differs from PFUI repair because the continence mechanism is already vulnerable. EAU guidelines make a strong recommendation to warn patients that incontinence is inevitable after transperineal redo VUA, because the approach disrupts the external sphincter, and that anti-incontinence surgery may be needed later.[1] AUS placement is deferred at least three to six months so that patency is confirmed.[1] EAU weakly recommends a retropubic approach when the patient is continent before surgery and notes that perineal and retropubic approaches have not been compared directly for urinary incontinence.[1] Separately, a 2025 retrospective comparison of 18 open perineal and 10 robot-assisted VUA reconstructions reported study-defined patency of 14/18 (77.8%) versus 8/10 (80.0%), defined by passage of a 16 Fr cystoscope or maximum flow >15 mL/s, and lower observed de novo incontinence with robot assistance.[7] The AUA amendment reports 83.3% incontinence after perineal reconstruction among preoperatively continent patients in small cohorts.[4]
Selection
| Favors TPRA | Favors another approach |
|---|---|
| Already incontinent, with delayed AUS acceptable | Continent before surgery, when preserving continence is central |
| Short VUAS with an intact bladder neck may also be approached perineally[1]; prior abdominal surgery can limit retropubic access | Preoperative continence favors retropubic redo VUA [1] |
| Obliterative or highly recurrent VUAS needing perineal mobilization | In radiation-associated, non-obliterative stenosis with a viable graft bed, dorsal BMG has been described; it has not been compared directly with TPRA. Assess bladder function and local tissue before choosing repair.[1][5][6] |
| A last outlet option before diversion | Patient unwilling to accept a staged AUS pathway |
Other factors are stenosis length and location, available urethra, prior operations or radiation, bladder function and the patient's priorities. EAU advises redo VUA only with adequate bladder function and in the absence of urethral necrosis, calcification or fistula, and only in experienced high-volume centers, particularly after radiotherapy.[1]
Operative logic
The operation borrows from posterior urethroplasty: perineal exposure, proximal urethral mobilization, scar excision and tension-free mucosa-to-mucosa reanastomosis. Longer gaps may require progressive perineal maneuvers such as corporal separation or partial inferior pubectomy, or a combined approach. In the post-prostatectomy patient the operation is aimed at outlet patency first and continence restoration later.[1]
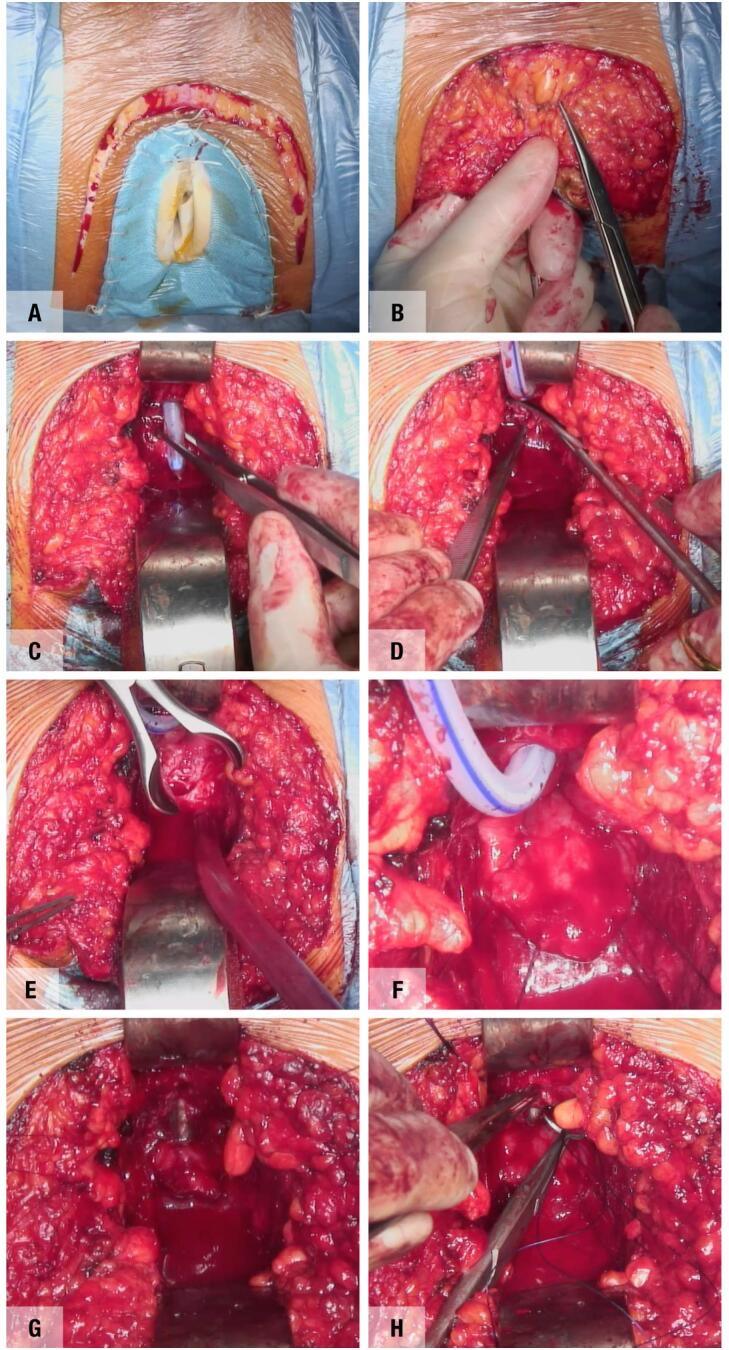
Transperineal vesicourethral reanastomosis: (A) exaggerated lithotomy position and half-moon perineal incision; (B) urethral dissection under digital rectal guidance; (C) exposure of the anastomotic site and identification of the stenosis; (D, E) meticulous excision of the scar tissue; (F) extensive mobilization of the urethra and bladder for a tension-free reanastomosis; (G, H) eight circumferential sutures preplaced, with the three dorsal sutures (11, 12 and 1 o'clock in lithotomy) tied first, followed by Foley insertion and completion of the remaining five. From Klemm J, et al. Int Braz J Urol. 2026;52(4):e20260112, Figure 1 (CC BY).[5]
References
1. European Association of Urology. EAU Guidelines on Urethral Strictures. 2026. Disease management in males, sections 6.3.5–6.3.6. Guideline.
2. Reiss CP, Pfalzgraf D, Kluth LA, et al. "Transperineal Reanastomosis for the Treatment for Highly Recurrent Anastomotic Strictures as a Last Option Before Urinary Diversion." World Journal of Urology. 2014;32(5):1185-90. doi:10.1007/s00345-013-1180-6
3. Schuettfort VM, Dahlem R, Kluth L, et al. "Transperineal Reanastomosis for Treatment of Highly Recurrent Anastomotic Strictures After Radical Retropubic Prostatectomy: Extended Follow-Up." World Journal of Urology. 2017;35(12):1885-1890. doi:10.1007/s00345-017-2067-8
4. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
5. Klemm J, Oberneder K, Roessler N, Schulz RJ, Wagner MC, Schuettfort VM, et al. "Patient-Reported Outcomes of Transperineal Reanastomosis for Recurrent or Obliterative Post-Prostatectomy Vesicourethral Anastomotic Stenosis." International Brazilian Journal of Urology. 2026;52(4):e20260112. doi:10.1590/S1677-5538.IBJU.2026.0112
6. Sterling J, Simhan J, Flynn BJ, et al. "Multi-Institutional Outcomes of Dorsal Onlay Buccal Mucosal Graft Urethroplasty in Patients With Postprostatectomy, Postradiation Anastomotic Stenosis." J Urol. 2024;211(4):596-604. doi:10.1097/JU.0000000000003848
7. Savun M, Çolakoğlu Y, Özdemir H, et al. "Comparison of open perineal and robot-assisted reconstruction in vesicourethral anastomotic stenosis." World J Urol. 2025;43(1):413. doi:10.1007/s00345-025-05808-w