Bladder Neck Closure
Bladder neck closure (BNC) is an irreversible salvage operation that permanently excludes the urethral outlet in selected patients with refractory incontinence or a devastated, nonreconstructible outlet. It requires a dependable alternative drainage route: a continent catheterizable channel, an incontinent diversion or a permanent suprapubic catheter.[1] Here "closure" is distinct from bladder neck contracture, which shares the abbreviation BNC.
The AUA/SUFU NLUTD guideline states that clinicians may offer bladder neck closure with concomitant bladder drainage to select patients with NLUTD and refractory SUI after a thorough discussion of risks, benefits and alternatives . The guideline text cites continence rates of 75% to 100%, with fistulization and recurrent incontinence in up to 25%, and advises discussing loss of male fertility and the need for assisted reproduction beforehand.[1] Selection considers the bladder, urethra, hand and cognitive function, caregiver support, prior surgery and the patient's goals. Every lesser operation need not be attempted first when anatomy or function makes it unsuitable. BNC is the endpoint of the bladder neck reconstruction escalation ladder.[1]
Indications and alternatives
- Neurogenic bladder. Chronic catheterization can erode the urethra, and prior bladder neck procedures may have failed. In a cohort of 13 women with spinal cord injury managed by chronic indwelling urethral catheter, 6 (46%) developed urethral erosion at a mean follow-up of 7 years.[25] All 39 patients in Shpall's series and all 29 in Ginger's had neurogenic bladder.[4][20]
- Bladder exstrophy and other congenital outlet disease. BNC follows multiple failed outlet reconstructions. In Kavanagh's 28 patients, 19 (68%) had undergone 20 unsuccessful bladder neck procedures beforehand.[3][18][22]
- Recalcitrant post-prostatectomy vesicourethral anastomotic stenosis with incontinence. Spahn's series included 10 such men. VUAS reconstruction is considered first when the tissue allows it.[2][24]
- Severely compromised female outlet. Causes include urethral erosion from indwelling catheters, failed anti-incontinence surgery with severe intrinsic sphincter deficiency, and post-vulvectomy or radiation injury.[2][5][16]
- Complex urethrovesical fistula or radiation-damaged urethra in men. Ullrich described BNC combined with prostatectomy and intestinal interposition in five men.[23]
A bladder that is painful, infected, poorly compliant or otherwise unsalvageable may need a different diversion strategy rather than closure alone.[2][3][4][1]
The AUA/SUFU female SUI guideline states that, in women with severe outlet dysfunction or recurrent or persistent SUI after surgery, clinicians may offer an obstructing pubovaginal sling or bladder neck closure with urinary drainage .[5] Its text lists the options for a severely compromised outlet as an autologous pubovaginal sling, an obstructing autologous sling, closure with a catheterizable stoma, an AUS, and total urinary diversion. These alternatives are chosen by anatomy, drainage needs and goals; when outlet tissue permits, an obstructing autologous sling preserves transurethral access for emergency catheterization and ureteroscopy.[1] The tension needed for an obstructing configuration should preclude a synthetic sling.[5]
Chancellor's 14-woman series reported dryness at mean 24 months after an obstructing pubovaginal sling. Drainage and concomitant reconstruction varied: 2 had sling plus CIC alone, 5 enterocystoplasty, 5 a bladder chimney, and 2 suprapubic drainage. The authors suggested the sling may be superior to formal closure because it carries no fistula risk from bladder neck transection. The series was small and uncontrolled.[6]
In selected men with an end-stage urethra after AUS failure, permanent perineal urethral ligation with chronic suprapubic drainage is another salvage option.[7][8]
Reservoir and drainage planning
| Drainage plan | Requirements and consequences |
|---|---|
| Continent catheterizable channel | Safe storage pressures, adequate reservoir, reliable intermittent catheterization by patient or caregiver, and durable access |
| Permanent suprapubic catheter | Dependable continuous drainage, catheter-change support and a plan for blockage or dislodgement; the tube remains the bladder's outlet |
| Ileovesicostomy or another incontinent route | Individual assessment of drainage, obstruction, appliance needs and possible reoperation |
| Augmentation with reconstruction | Selected when storage capacity or compliance cannot safely support the intended regimen; it adds bowel, metabolic, stone and perforation risks |
Bladder storage is assessed before outlet resistance is increased, particularly when the planned regimen requires intermittent emptying. In patients with relevant NLUTD undergoing closure with a continent catheterizable channel, assess storage pressure and compliance by urodynamics; temporarily occlude a severely incompetent outlet during filling when needed to measure these parameters.[1] Continuous suprapubic drainage is a different physiological plan from a continent storage reservoir.[1] Zhu and Stoffel suggest a minimum bladder capacity of 100 mL and compliance of 15 mL/cm H2O before vesical neck closure, citing the risk of continued leakage, closure failure, rupture or reflux in a small or poorly compliant bladder.[26] In Jayanthi's 28 patients (mean follow-up 29 months), 11 had closure and Mitrofanoff diversion without augmentation, and 4 patients who did not initially have augmentation later needed it, 2 for hydronephrosis and 2 for persistent incontinence.[18]
Grimsby's 109-child study concerned mixed bladder neck reconstruction, closure and sling procedures without augmentation, not closure alone. Estimated ten-year rates were 30% for subsequent augmentation, 70% for additional continence procedures and more than 50% for upper-tract changes. Patients with a prior vesicostomy or reflux surgery were at higher risk. These data support long-term surveillance when augmentation is deferred.[9]
Operative principles
Abdominal approach
- Obtain exposure appropriate to prior surgery and any planned augmentation or channel (lower midline or Pfannenstiel incision). Identify and protect the ureteral orifices.
- Divide the bladder neck completely, separating the bladder from the urethral outlet and preserving viable tissue for a tension-free closure.
- Close the bladder side securely in two layers with absorbable suture and oversew the urethral stump. Separate suture lines when feasible. Verify watertightness and unobstructed alternative drainage.[4][10]
- Interpose vascularized tissue between the closed bladder neck and the urethral stump, particularly in scarred or previously operated tissue.[10][11]
Hensle reported initial success in 12 of 13 patients, and eventual success in all 13, with bladder neck division, two-layer closure and omental interposition.[10] Interposition options include:
| Interposition | Reported experience |
|---|---|
| Omental flap | Pedicled omentum placed between the suture lines; the usual choice in Hensle's series[10] |
| Rectus abdominis muscle flap | Inferior epigastric-based; used when omentum is unavailable. Smith described 6 patients, all continent with no fistulas at mean 45.5 months[11] |
| Human acellular dermis | In a retrospective exstrophy cohort of 147 patients, fistulas occurred in 5.8% with acellular dermis or native-tissue flaps and 20.8% without interposition (P = 0.039). Acellular dermis is not a vascularized flap[12] |
| Intestinal patch | Ileocecal or sigmoid segment at the closure site, with concomitant prostatectomy for unsalvageable urethral disease. Ullrich described 5 men with mean follow-up of 6 months[23] |
No comparative trial establishes one material or a flap as mandatory.
For women, Zhu and Stoffel describe a three-layer closure: two running 4-0 Monocryl sutures approximate mucosa to mucosa, an interrupted horizontal Lembert layer follows, and a third layer placed from the posterior neck toward the anterior bladder rotates the neck cephalad. This is the chapter authors' described technique, and no comparative outcome is reported for it.[26]
In selected men, Isom-Batz and Zimmern describe a supraprostatic closure that avoids deep pelvic dissection and division of the dorsal venous complex, preserving the prostate and distal urethra. They state this approach preserves antegrade ejaculatory flow and a potential for future fertility, though the chapter reports no fertility outcomes or comparative data for the claim.[27]
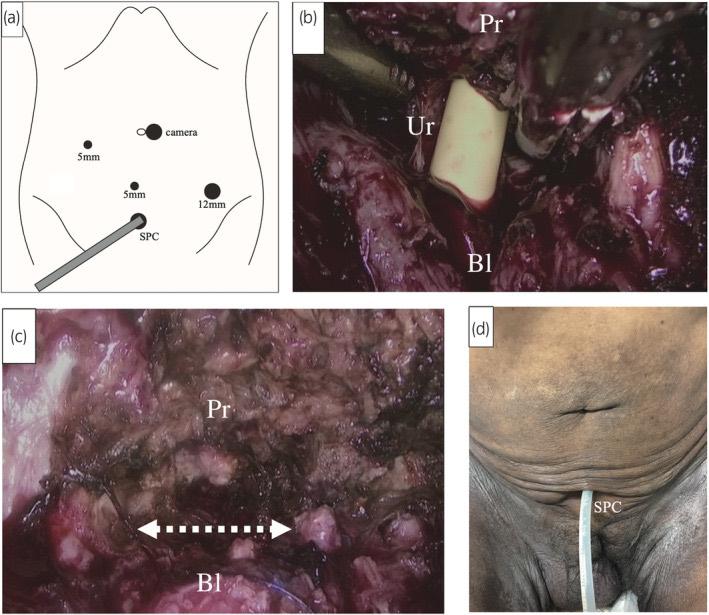
Retroperitoneoscopic bladder neck closure in a 56-year-old man: (a) trocar schema with suprapubic catheter (SPC); (b) urethra (Ur) divided at the internal urethral orifice, between prostate (Pr) and bladder (Bl); (c) proximal urethra and bladder neck sutured closed, with bladder and prostate completely separated (two-headed arrow); (d) perineal wound closed after the bladder neck closure. From Doi Y, et al. IJU Case Rep. 2024;7(6):495-498, Fig. 2 (CC BY 4.0).[29]
Transvaginal approach
In selected women, vaginal access avoids laparotomy. It has been used particularly in women with a urethra destroyed by chronic catheterization.[5][13][14]
- Make an anterior vaginal wall incision and develop the plane between the vaginal wall and the bladder neck and urethra.
- Dissect the bladder neck circumferentially, mobilize it from the supporting pelvic attachments, separate the urethra from the bladder, and resect any necrotic outlet tissue to viable edges.[28]
- Identify the ureteral orifices before closure, especially when outlet erosion brings them close to the repair. Close the bladder neck in multiple layers with viable tissue.[28]
- Close the vaginal wall as a separate layer over the repair.[13][14][15]
Zhu and Stoffel describe a wide inverted-U, full-thickness anterior vaginal-wall flap with its apex near the urethral meatus and extended proximally for a long, low-tension flap. They use the pubic symphysis as a landmark during urethral dissection, place lateral bladder-neck holding sutures to avoid an asymmetric excision, and, after mucosal coaptation, place a horizontal suture incorporating the inferior pubic symphysis to rotate the neck anteriorly.[26]
In Rovner's posterior urethral flap technique, the dorsally bivalved urethra is rotated cephalad onto the incised anterior bladder wall. The suture line then lies high in the retropubic space, away from the ureteral orifices and the vaginal incision. The technique was designed to lower the risk of ureteral injury and fistula. It was reported in 11 women with mean follow-up of 9.6 months, and one failed at 6 weeks.[15]
David A. Ginsberg describes tagging the sutures of a two-layer bladder-neck closure and passing their needles through the undersurface of the pubic symphysis or the anterior abdominal wall, drawing the closure anteriorly and away from the vaginal-wall closure line; he notes the maneuver requires adequate bladder-neck mobility. This is distinct from Rovner's posterior urethral flap and has not been evaluated against it.[28]
In Willis's retrospective comparison of 64 women with suprapubic drainage, initial urethral continence after the first closure was 85.7% after transvaginal and 81.5% after retropubic closure (P = 0.74).[16] The transvaginal group had shorter operative time (78 vs 138 minutes), shorter stay (1.5 vs 4.9 days) and fewer short-term complications (5.7% vs 31.0%).[16] In Ginger's 29 debilitated patients, all 3 who had a non-retropubic closure (2 transvaginal, 1 perineal) developed a fistula (P = 0.01).[20]
Combined abdominal and vaginal approach
Levy reported that 2 of 5 transvaginal closures (40%) in 4 women were successful. The group then used a combined abdominal and transvaginal repair, which succeeded in 10 consecutive patients (follow-up 6 to 40 months, mean 15.6). The abdominal component allows tissue interposition and better visualization, and the vaginal component helps dissect the destroyed outlet.[19]
Outcomes
Closure success, continence and freedom from further surgery are distinct outcomes.
| Series | Patients and follow-up | Result |
|---|---|---|
| Spahn 2010 | 17 adults: 10 post-prostatectomy, 1 post-vulvectomy, 6 neurogenic; median follow-up 68 months | Primary closure in all 17; initial continence 82%. Three needed further continence reconstruction and four had stomal stenosis.[2] |
| Kavanagh 2012 | 28 patients: 15 exstrophy, 13 neurogenic; augmentation plus Mitrofanoff; median follow-up 69 months | Initial closure 27/28; one fistula repaired. Eleven patients (39.3%) required further surgery, including three augment-rupture repairs.[3] |
| Shpall 2004 | 39 adults with neurogenic dysfunction and varied reconstruction; mean follow-up 36.9 months | Overall complications 31%; six vesicourethral fistulas (15%), four requiring repair. High pressures, previous bladder neck surgery and noncompliance with catheter care were risk factors for prolonged leakage.[4] |
| O'Connor 2005 | 35 patients; mean follow-up 79 months | 29 initial successful closures (83%); 33 (94%) after one additional closure procedure.[17] |
| Jayanthi 1995 | 28 patients aged 1 to 20 years; closure with Mitrofanoff; mean follow-up 29 months | 27 (96%) totally continent; closure primarily successful in 24 (86%). Five had bladder calculi and five needed stomal revision.[18] |
| Nguyen 2003 | 20 children after multiple failed outlet operations; mean follow-up 5.4 years | 40% dry at 3 months and 85% completely continent at 2 years after additional surgery. Of 15 followed beyond 3 years, only 40% remained dry, and stomal leakage developed in 47% after a dry year. Stomal stenosis occurred in 30% and stones in 40%.[22] |
| Landau 2009 | 12 children followed at least 10 years (mean 12.4) | Closure cured incontinence in all 6 patients with a modified posterior bladder neck flap; 2 of the earlier 6 needed revision. CIC compliance was good and upper tracts were preserved.[21] |
| Ginger 2010 | 29 debilitated patients (24 women) with suprapubic tube; retropubic closure in 26 | Early complication rate 52%. Persistent leakage in 8; all 3 non-retropubic closures developed fistulas.[20] |
Complications
Percentages differ with population, reservoir, drainage route, follow-up and whether additional operations count as success. Series report:
- Vesicourethral or vesicovaginal fistula. This is the signature complication: 15% in Shpall's adults and 40% at 3 months in Nguyen's children.[4][22] Reported risk factors are high-pressure bladder systems, prior bladder neck surgery, noncompliance with catheter care and absent interposition.[4][20][22][12]
- Stomal stenosis. It occurred in 23% (Spahn) and 30% (Nguyen).[2][22] In Spahn's series, 3 of 8 abdominal stomas and 1 of 9 umbilical stomas stenosed.[2][22]
- Bladder calculi. They occurred in 40% of Nguyen's children and 5 of 28 in Jayanthi's series.[22][18]
- Augment rupture. Kavanagh repaired 3 augment ruptures among 28 patients, and Ullrich reported 1 among 5.[3][23]
- Stomal incontinence. It developed late in 47% of the 15 children followed beyond 3 years in Nguyen's series after a dry year; the authors related late leakage in part to catheterization compliance.[22]
- Upper-tract change. Kavanagh observed no progressive or de novo hydronephrosis, and Spahn no ureteral obstruction. In Grimsby's mixed pediatric cohort of bladder neck reconstruction, closure and sling procedures without augmentation, the ten-year cumulative incidence of upper-tract changes exceeded 50%.[2][3][9]
Postoperative drainage and lifelong follow-up
After formal closure, a urethral Foley does not traverse the closed bladder neck. Temporary healing catheters through a channel or suprapubic tract are managed according to the reconstruction and confirmation of healing. Do not remove a permanent suprapubic catheter because a 2–3-week cystogram is satisfactory: it remains the drainage route unless a working alternative has deliberately been established. Catheter blockage or dislodgement requires prompt assessment because the urethral escape route has been closed.[1][15]
Cystography at approximately 2–3 weeks is described in some operative protocols, including Rovner's. It assesses healing and does not remove the need for permanent drainage. Maintain dependable decompression, assess leakage and infection, and distinguish fistula from catheter bypass or stomal incontinence. Poor catheter care in the postoperative period was associated with leakage in Ginger's series.[4][15][20]
Follow renal function, upper tracts and bladder storage according to the underlying condition and reconstruction. Teach catheterization or catheter care and provide an emergency drainage plan. Long-term CIC compliance was good beyond 10 years in Landau's small pediatric series.[1][21] Augmented patients need the additional long-term surveillance described in augmentation cystoplasty.[1]
Guideline positioning
- AUA/SUFU NLUTD 2021 (Statement 47). Clinicians may offer bladder neck closure and concomitant bladder drainage to select patients with NLUTD and refractory SUI .[1]
- AUA/SUFU female SUI 2023 (Statement 22). Clinicians may offer an obstructing pubovaginal sling or bladder neck closure with urinary drainage to women with severe outlet dysfunction or surgical failure .[5]
- AUA urethral stricture guideline amendment 2023 (Statement 29). Surgeons may perform robotic or open reconstruction for recalcitrant bladder neck stenosis or post-prostatectomy VUAS . The text cites robotic patency of 72.7% to 75%.[24]
Technical pearls
- Interpose vascularized tissue (omentum or rectus muscle) when feasible.[10][11] In Benz's retrospective exstrophy cohort, fistulas occurred in 5.8% with a flap or acellular dermis and 20.8% without interposition.[12] In a separate 192-patient classic-exstrophy cohort, three or more prior bladder mucosal violations were associated with fistula after closure; the authors suggested considering a pedicled muscle flap for this subgroup, without testing its preventive effect.[30] In a 35-patient cloacal-exstrophy cohort, fistula occurred in 47.4% of those with at least two prior bladder mucosal violations; the authors likewise suggested considering prophylactic muscle interposition without testing its preventive effect.[31]
- Use autologous tissue when the goal is bladder neck occlusion with a sling. The tension required should preclude synthetic mesh.[5]
- Plan the drainage route before transection. The catheterizable channel, ileovesicostomy or suprapubic tube must already be designed.[3][4]
- Consider concurrent augmentation when reservoir capacity or compliance is borderline. In Grimsby's mixed pediatric cohort of bladder neck reconstruction, closure and sling procedures without augmentation, the estimated ten-year cumulative incidence of later augmentation was 30%.[9]
- Maintain bladder drainage during healing; some operative protocols obtain cystography at about 2–3 weeks to assess closure integrity. Remove temporary healing catheters according to the reconstruction, and maintain a permanent suprapubic catheter until another dependable drainage route is established.[4][15]
Related procedures
- Bladder-neck reconstruction principles
- Vesicourethral anastomotic stenosis (VUAS)
- Autologous pubovaginal sling
- Continent catheterizable channels
- Urinary diversion
Videos
References
1. Ginsberg DA, Boone TB, Cameron AP, et al. The AUA/SUFU guideline on adult neurogenic lower urinary tract dysfunction: treatment and follow-up. J Urol. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239.
2. Spahn M, Kocot A, Loeser A, Kneitz B, Riedmiller H. Last resort in devastated bladder outlet: bladder neck closure and continent vesicostomy — long-term results and comparison of different techniques. Urology. 2010;75(5):1185-92. doi:10.1016/j.urology.2009.11.070.
3. Kavanagh A, Afshar K, Scott H, MacNeily AE. Bladder neck closure in conjunction with enterocystoplasty and Mitrofanoff diversion for complex incontinence: closing the door for good. J Urol. 2012;188(4 Suppl):1561-5. doi:10.1016/j.juro.2012.02.027.
4. Shpall AI, Ginsberg DA. Bladder neck closure with lower urinary tract reconstruction: technique and long-term followup. J Urol. 2004;172(6 Pt 1):2296-9. doi:10.1097/01.ju.0000144072.15735.32.
5. Kobashi KC, Vasavada S, Bloschichak A, et al. Updates to surgical treatment of female stress urinary incontinence (SUI): AUA/SUFU guideline (2023). J Urol. 2023;209(6):1091-1098. doi:10.1097/JU.0000000000003435.
6. Chancellor MB, Erhard MJ, Kiilholma PJ, Karasick S, Rivas DA. Functional urethral closure with pubovaginal sling for destroyed female urethra after long-term urethral catheterization. Urology. 1994;43(4):499-505. doi:10.1016/0090-4295(94)90241-0.
7. Van Dyke M, Ortiz N, Baumgarten A, et al. Permanent urethral ligation after AUS cuff erosion: is it ready for prime time? Neurourol Urodyn. 2021;40(1):211-218. doi:10.1002/nau.24535.
8. Arnold PJ, Soyster ME, Burns RT, Mellon MJ. The role of urethral ligation after AUS failure and end stage urethra. Int Urol Nephrol. 2022;54(11):2827-2831. doi:10.1007/s11255-022-03315-0.
9. Grimsby GM, Menon V, Schlomer BJ, et al. Long-term outcomes of bladder neck reconstruction without augmentation cystoplasty in children. J Urol. 2016;195(1):155-61. doi:10.1016/j.juro.2015.06.103.
10. Hensle TW, Kirsch AJ, Kennedy WA, Reiley EA. Bladder neck closure in association with continent urinary diversion. J Urol. 1995;154(2 Pt 2):883-5. doi:10.1016/S0022-5347(01)67194-5.
11. Smith EA, Kaye JD, Lee JY, Kirsch AJ, Williams JK. Use of rectus abdominis muscle flap as adjunct to bladder neck closure in patients with neurogenic incontinence: preliminary experience. J Urol. 2010;183(4):1556-60. doi:10.1016/j.juro.2009.12.044.
12. Benz KS, Jayman J, Maruf M, et al. The role of human acellular dermis in preventing fistulas after bladder neck transection in the exstrophy-epispadias complex. Urology. 2018;117:137-141. doi:10.1016/j.urology.2018.04.011.
13. Petrikovets A, Sun H, Sheyn D, Slopnick E, Hijaz A. Transvaginal bladder-neck closure: a step-by-step video for female pelvic surgeons. Int Urogynecol J. 2019;30(1):159-161. doi:10.1007/s00192-018-3766-4.
14. Zimmern PE, Hadley HR, Leach GE, Raz S. Transvaginal closure of the bladder neck and placement of a suprapubic catheter for destroyed urethra after long-term indwelling catheterization. J Urol. 1985;134(3):554-7. doi:10.1016/s0022-5347(17)47290-9.
15. Rovner ES, Goudelocke CM, Gilchrist A, Lebed B. Transvaginal bladder neck closure with posterior urethral flap for devastated urethra. Urology. 2011;78(1):208-12. doi:10.1016/j.urology.2010.11.054.
16. Willis H, Safiano NA, Lloyd LK. Comparison of transvaginal and retropubic bladder neck closure with suprapubic catheter in women. J Urol. 2015;193(1):196-202. doi:10.1016/j.juro.2014.07.091.
17. O'Connor RC, Stapp EC, Donnellan SM, et al. Long-term results of suprapubic bladder neck closure for treatment of the devastated outlet. Urology. 2005;66(2):311-315. doi:10.1016/j.urology.2005.03.009.
18. Jayanthi VR, Churchill BM, McLorie GA, Khoury AE. Concomitant bladder neck closure and Mitrofanoff diversion for the management of intractable urinary incontinence. J Urol. 1995;154(2 Pt 2):886-8. doi:10.1016/S0022-5347(01)67195-7.
19. Levy JB, Jacobs JA, Wein AJ. Combined abdominal and vaginal approach for bladder neck closure and permanent suprapubic tube: urinary diversion in the neurologically impaired woman. J Urol. 1994;152(6 Pt 1):2081-2. doi:10.1016/s0022-5347(17)32313-3.
20. Ginger VA, Miller JL, Yang CC. Bladder neck closure and suprapubic tube placement in a debilitated patient population. Neurourol Urodyn. 2010;29(3):382-6. doi:10.1002/nau.20751.
21. Landau EH, Gofrit ON, Pode D, et al. Bladder neck closure in children: a decade of followup. J Urol. 2009;182(4 Suppl):1797-801. doi:10.1016/j.juro.2009.03.074.
22. Nguyen HT, Baskin LS. The outcome of bladder neck closure in children with severe urinary incontinence. J Urol. 2003;169(3):1114-6; discussion 1116. doi:10.1097/01.ju.0000051581.87633.02.
23. Ullrich NF, Wessells H. A technique of bladder neck closure combining prostatectomy and intestinal interposition for unsalvageable urethral disease. J Urol. 2002;167(2 Pt 1):634-6. doi:10.1016/S0022-5347(01)69101-8.
24. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
25. McGuire EJ, Savastano J. Comparative urological outcome in women with spinal cord injury. J Urol. 1986;135(4):730-1. doi:10.1016/s0022-5347(17)45833-2.
26. Zhu A, Stoffel J. Female Vesical Neck Closure. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:454-460.
27. Isom-Batz G, Zimmern PE. Bladder neck closure: male and female. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:296-304.
28. Ginsberg DA. Transvaginal Bladder Neck Closure. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:239-244. doi:10.1007/978-3-319-49855-3_22
29. Doi Y, Ochi A, Okamoto Y, Komiya A, Kuji H, Suzuki K, et al. Retroperitoneoscopic bladder neck closure for continuous urinary incontinence in Fournier's gangrene. IJU Case Rep. 2024;7(6):495-498. doi:10.1002/iju5.12788.
30. Harris TGW, Crigger CB, Sholklapper TN, et al. "The impact of repeated bladder surgery on successful bladder neck closure in classic bladder exstrophy: The role of mucosal violations." J Pediatr Urol. 2023;19(4):372.e1-372.e7. doi:10.1016/j.jpurol.2023.04.022
31. Crigger CB, Harris TGW, Sholklapper TN, et al. "Mucosal Violations and Their Effect on Successful Bladder Neck Closure in Cloacal Exstrophy." J Pediatr Surg. 2023;58(12):2313-2318. doi:10.1016/j.jpedsurg.2023.05.009