Transurethral Incision of Bladder Neck Contracture (TUIBNC)
Transurethral incision of bladder neck contracture (TUIBNC) is an initial endoscopic treatment for non-obliterative bladder neck stenosis after benign prostate surgery and for vesicourethral anastomotic stenosis (VUAS) after radical prostatectomy. EAU guidelines recommend transurethral resection or hot-knife incision for bladder neck stenosis after benign outlet surgery, and visually controlled dilation or direct vision internal urethrotomy for non-obliterative VUAS.[1] AUA guidelines allow dilation, incision or resection according to surgeon preference and expect comparable outcomes.[10]
See BNC, VUAS, the resection technique, and, for open or robotic reconstruction, Y-V plasty, T-plasty and combined abdominoperineal repair.
Definition and etiology
BNC is fibrotic narrowing of the bladder neck that presents with obstructive symptoms, reduced flow and raised post-void residual. After transurethral prostate surgery it presented at a median of 5.8 months in a single-center review of 1008 patients (20 cases, 2%). Incidence was 4.7% after bipolar TURP and 1.3% after transurethral enucleation.[18] After radical prostatectomy, narrowing at the vesicourethral anastomosis is termed VUAS, a distinct lesion from post-benign-surgery BNC; post-prostatectomy cases are common in referral series.[1][2]
Selection and operative safety
Confirm the prior operation, radiation exposure, stenosis location and length, residual lumen, baseline continence, and bladder function. Cystoscopy detects narrowing but usually cannot define stenosis length. For nearly obliterative stenosis, EAU strongly recommends combined retrograde urethrography and voiding cystourethrography to assess its proximal extent; consider MRI urethrography when a fistula is suspected.[28] Identify fistula, radionecrosis or complete obliteration before attempting treatment. Do not attempt endoluminal treatment of a completely obliterated posterior stenosis .[1] Releasing obstruction can reveal or worsen sphincteric incontinence.[1]
For VUAS or radiation-induced bulbomembranous stenosis, the EAU strongly recommends avoiding deep 6 and 12 o'clock DVIU incisions because of rectal injury and urosymphyseal fistula risk; the latter is of particular concern after radiotherapy.[1] Lateral incisions do not eliminate sphincter injury, extravasation or fistula risk. The desired endpoint is controlled opening of the stenosis within the patient's anatomy.[1] Cao's post-benign-surgery BNC series described incising to the adipose layer at 5, 7 and 12 o'clock, then excising redundant bladder-neck and prostatic-urethral scar with a cutting loop.[25]
Positioning and VTE Prophylaxis
TUIBNC is performed transurethrally with the patient in lithotomy. The AUA urethral stricture guideline's general perioperative framework recommends assessing lower-extremity mobility before positioning and careful extremity padding in lithotomy to avoid pressure on the calf muscles, peroneal nerve and ulnar nerve, with sequential compression devices to reduce both venous thromboembolism and nerve-compression injury; it frames added parenteral VTE prophylaxis mainly as a consideration for open urethral reconstruction, not a brief transurethral incision such as this one. Neither the AUA nor EAU stricture guideline states a BNC- or VUAS-specific pharmacologic VTE recommendation; apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page.[24]
Technique
- Obtain a preoperative urine culture, treat active UTI and give perioperative antibiotic prophylaxis according to AUA general urethral-intervention guidance.[24] Assess the lumen cystoscopically and establish safe access under direct vision. Antegrade assessment through a suprapubic tract can help when anatomy is uncertain.
- In the published Nealon/Ramirez protocol, a 24 Fr balloon permits resectoscope access, followed by bilateral 3 and 9 o'clock incisions with an electrocautery Collins knife.[2][3] Both series divide the scar deeply; depth must be adapted to the location, prior reconstruction and radiation injury. A Collins electrocautery knife is distinct from a cold knife.
- Confirm a patent channel, hemostasis and catheter drainage. Catheter size and duration depend on tissue injury, the procedure performed and the drainage plan. Nealon's series used a 20 Fr urethral catheter for approximately four days.[2] The AUA guideline's general framework recommends a shorter indwelling catheter after endoscopic intervention than after open urethral reconstruction; it describes urethrography or voiding cystography before catheter removal after open reconstruction, with longer drainage if a leak persists.[24]
| Variant | Notes |
|---|---|
| Holmium laser incision | A retrospective 41-patient day-surgery series of balloon dilation plus holmium incision reported six cases of urge incontinence and one recurrent BNC after 12 months.[22] A retrospective 372-patient post-TURP BNS incision cohort analyzed outcomes by instrument.[26] |
| Radial (tri- or quadrant) cold-knife incision | Used in mitomycin C protocols[12] |
| Incision with transverse mucosal realignment | An endoscopic Y-V type repair; see transverse mucosal realignment. Earlier support came from small observational cohorts[1][4]; a retrospective 2026 cohort of 92 men after benign prostate surgery reported 93.5% initial cystoscopic patency and 83.7% freedom from reintervention after one procedure at median 15.9 months of follow-up.[27] |
Comparative data do not identify a superior incision energy for posterior stenosis.[1]
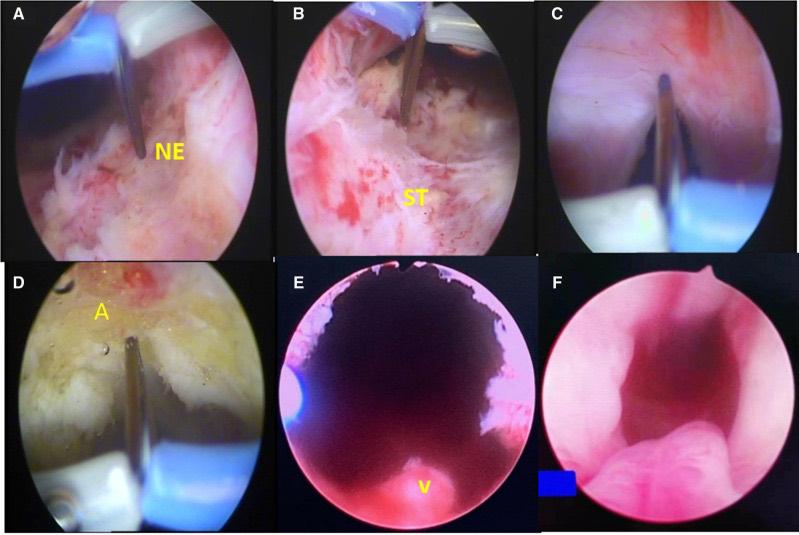
Cao and colleagues' post-benign-surgery technique: (A–D) incisions at 5, 7 and 12 o'clock with a needle electrode (NE), creating an incisional pathway from the bladder neck to the proximal verumontanum that reaches the adipose layer (A); (E) immediate resectoscopic view after incision, with the verumontanum (V); (F) cystoscopic view of the bladder neck 1 month later. This depth at 12 o'clock is specific to the series, not a general endpoint for VUAS or irradiated tissue.[1] From Cao G, et al. Front Surg. 2022;9:871099, Figure 2 (CC BY).[25]
Outcomes and their limits
| Study | Population and design | Reported outcome |
|---|---|---|
| Nealon 2022 | Retrospective, 123 patients with heterogeneous BNC/VUAS; balloon plus Collins incisions, no injection | 101/123 (82.1%) patent after one procedure; 116/123 (94.3%) after a second; median follow-up 12 months. Patency assessment included passage of a 16 Fr cystoscope at approximately 2 months.[2] |
| Ramirez 2013 | 50 patients; 78% had failed previous TUIBNC | 72% success after one procedure, 86% after two; mean follow-up 12.9 months.[3] |
| Rosenbaum 2021 | 60 patients after benign prostate surgery; VUAS excluded; 49 resections and 11 incisions | 32/60 (53%) had no study-defined recurrence (any further urinary instrumentation) at median 22-month follow-up (IQR 12–32); this was assessed through records and patient interviews, without standardized cystoscopy. The comparison was nonrandomized.[5] |
| Abramowitz 2021 | 19 patients, one surgeon; incision plus mucosal realignment | 17/19 (89%) met the 17 Fr cystoscopic patency criterion at four months after one procedure, and 19/19 after a repeat procedure; median follow-up was six months. No new incontinence was reported.[4] |
| Quarta 2025 | 110 patients after BPE surgery, 91.8% with holmium laser incision | Among patients with IPSS assessed at 3 months, symptoms were mild in 64.0%, moderate in 30.7% and severe in 5.3%.[11] |
| Castellani 2024 | Retrospective incision cohort from 12 centers; 372 men with stenosis after TURP | By one year, 29/372 (7.8%) had recurrent stenosis; postoperative incontinence was reported in 17.2%, and 12.4% had a complication.[26] |
A 2024 systematic review of 40 studies and 1,452 patients with post-prostatectomy anastomotic stenosis estimated freedom from study-defined VUAS recurrence at the end of follow-up at 72.8% (95% CI 64.4–79.9%); median study follow-up was 23.7 months (IQR 13–32). Adjustment for publication bias lowered the estimate to 62.9% (53.6–71.4%). Radiotherapy was associated with lower success. Techniques, definitions and follow-up varied.[6]
Risk factors for failure
| Factor | Evidence |
|---|---|
| Two or more prior endoscopic BNC procedures | Associated with failure in Ramirez (p = 0.03) and Nealon (the only factor on multivariable analysis)[2][3] |
| More than 10 pack-years of smoking | Associated with failure in Ramirez (p = 0.039)[3] |
| Pelvic radiation | Lower success; prospective comparisons are lacking[6][10] |
| Interval to current BNC treatment or symptom onset | In Rosenbaum, recurrence after BNC treatment was associated with shorter intervals from prior BPH surgery (p = 0.01) and from any prior endoscopic treatment (p = 0.046) to current BNC treatment; in Quarta, BNS symptoms beginning <6 months after BPE surgery were associated with IPSS-defined BNI failure at 3 months (OR 3.87)[5][11] |
| Small prostate at the original operation | Under 50 g was associated with failure in Quarta (OR 3.47)[11] |
Complications
Sphincteric incontinence is the main concern. Any endoluminal treatment may cause de novo incontinence (up to 25%) or worsen existing incontinence (up to 15%).[1] After the reported procedure, study-defined failure occurred in 22/123 (18%) of Nealon's cohort, 14/50 (28%) of Ramirez's cohort and 28/60 (47%) of Rosenbaum's mixed resection/incision cohort; these reflect, respectively, cystoscopic nonpatency, further surgery for obstruction and any further urinary instrumentation.[2][3][5] Bleeding and infection are standard endoscopic risks.
Intralesional adjuncts
Mitomycin C should not be used for posterior stenosis outside a clinical trial under EAU guidance.[1] Among 55 analyzed patients from 66 treated in the TURNS cohort, 4/55 had serious adverse events (7%), including osteitis, bladder-neck necrosis and rectourethral fistula; 3 needed or were planning cystectomy.[7] Other uncontrolled series have more favorable safety reports.[1][7] The AUA amendment notes conflicting data on mitomycin C for recurrent VUAS.[10]
Reported mitomycin C protocols use cold-knife radial incisions and injection of 0.3 to 0.4 mg/mL at each site, or 2 mg in 5 mL sterile water, sometimes with one month of daily clean intermittent catheterization.[12][16][23] These are individual surgeons' protocols.[12][16][23]
| Series | n | Population | One-procedure success | Cumulative | Follow-up |
|---|---|---|---|---|---|
| Vanni 2011[12] | 18 | All failed prior incision | 72% | 89% after two | Median 12 months |
| Rozanski 2021[13] | 86 | 91% had a prior DVIU | 65% | 90% overall | Median 21.1 months |
| Sourial 2017[14] | 29 | Recurrent VUAS after prostatectomy (injection plus dilation) | 79% | 86% with salvage injection | 12 months |
| Hacker 2022[15] | 51 | BNC or VUAS after prostate cancer treatment | 45% | 84% (up to four procedures) | Median 32 months |
| Farrell 2015[16] | 37 | Recurrent strictures and BNC | 75.7% needed no further surgery | Median 23 months | |
| TURNS 2015[7] | 55 | 80% failed prior dilation or incision | 58% | 75% after repeat | Median 9.2 months |
Radiation was associated with lower success. In Rozanski, overall success after repeat procedures was 94% in nonradiated and 76% in radiated patients (p = 0.04).[13] In Hacker, patients treated with prostatectomy followed by radiation had the shortest interval to recurrence (p = 0.018).[15]
Triamcinolone has been used with incision or resection in recurrent cases; the first report was of 7 patients in 1979.[19] Zhang's 28-patient series of highly recurrent bladder neck contracture after TURP reported 92.9% treatment success after resection plus intraoperative and serial postoperative injections (2 mL of 40 mg/mL at 8 sites, then every 4 weeks for three doses); 25/28 had adequate voiding at a median 2.8 years, with one patient limited by detrusor underactivity without recurrence.[8]
| Steroid series | n | Population | Result |
|---|---|---|---|
| Zhang 2021[8] | 28 | Highly recurrent post-TURP BNC | 92.9% reported treatment success; 25/28 adequate voiding at median 2.8 years |
| Sun 2022[17] | 46 | BNC after TURP or PVP; GreenLight vaporization plus weekly triamcinolone for three doses | No recurrence in follow-up; immunohistochemistry showed lower collagen I, MMP-3 and TGF-β after treatment |
| Wu 2024[18] | 20 | BNC after TURP or enucleation; incision plus betamethasone | 7/20 (35%) recurred at median 1.8 months; median follow-up 35.8 months |
| Kravchick 2013[20] | 14 of 29 | Recurrent anastomotic stenosis after prostatectomy; dilation plus TRUS-guided steroid | No incontinence in the steroid group; TUR required no retreatment, but 4/7 patients (57.1%) developed incontinence |
A meta-analysis of randomized trials found that local steroids with internal urethrotomy prolonged the time to recurrence but did not change the high recurrence rate.[21]
The Pang meta-analysis addressed male urethral strictures across heterogeneous settings. It found that any adjunct was associated with less recurrence (OR 0.37) and that mitomycin C had the lowest odds (intralesional OR 0.23, 95% CI 0.11-0.48). Pang's estimates include no direct BNC comparison of adjuncts. Urinary infection (2.9% to 14%), bleeding (8.8%) and extravasation (5.8%) were reported with steroid injection.[9]
For drug mechanisms, evidence and safety, use the antimitotic/antifibrotic hub and intralesional corticosteroid hub.[2] Nealon's no-injection series reported favorable outcomes.[2]
Continence and further treatment
Record continence before treatment. In Ramirez's referral cohort, 39/50 already had concomitant SUI; 78% is that cohort's baseline prevalence.[3] Twenty-six subsequently underwent AUS placement at a mean of 2.9 months, and 2 of those 26 needed repeat transurethral treatment for recurrent stenosis. Among the 26 men who underwent AUS placement, the authors reported more than 90% long-term urethral patency.[3] EAU advises waiting three to four months after DVIU before incontinence surgery, with cystoscopy to exclude recurrence first.[1]
Establish stable patency before continence surgery and reassess symptoms, storage function and suitability for an AUS. Repeated endoscopic treatment can stabilize selected non-obliterative stenoses . For recalcitrant stenosis, AUA allows robotic or open reconstruction , and cites robotic patency of 72.7% to 75% with a risk of incontinence that may require an AUS.[24] The approach is chosen by location, tissue quality, radiation, bladder function and the patient's goals. For recurrent or complex posterior stenosis with loss of bladder capacity or incapacitating local symptoms, EAU weakly recommends urinary diversion.[1] EAU advises against posterior urethral stents .[1][10]
References
1. European Association of Urology. EAU Guidelines on Urethral Strictures. 2026. Disease management in males, sections 6.3.5–6.3.6. Guideline.
2. Nealon SW, Bhanvadia RR, Badkhshan S, et al. Transurethral incisions for bladder neck contracture: comparable results without intralesional injections. J Clin Med. 2022;11(15):4355. doi:10.3390/jcm11154355.
3. Ramirez D, Zhao LC, Bagrodia A, et al. Deep lateral transurethral incisions for recurrent bladder neck contracture: promising 5-year experience using a standardized approach. Urology. 2013;82(6):1430-5. doi:10.1016/j.urology.2013.08.018.
4. Abramowitz DJ, Balzano FL, Ruel NH, Chan KG, Warner JN. Transurethral incision with transverse mucosal realignment for the management of bladder neck contracture and vesicourethral anastomotic stenosis. Urology. 2021;152:102-108. doi:10.1016/j.urology.2021.02.035.
5. Rosenbaum CM, Vetterlein MW, Fisch M, et al. Contemporary outcomes after transurethral procedures for bladder neck contracture following endoscopic treatment of benign prostatic hyperplasia. J Clin Med. 2021;10(13):2884. doi:10.3390/jcm10132884.
6. Delchet O, et al. Post-prostatectomy anastomotic stenosis: systematic review and meta-analysis of endoscopic treatment. BJU Int. 2024. doi:10.1111/bju.16141.
7. Redshaw JD, Broghammer JA, Smith TG, et al. Intralesional injection of mitomycin C at transurethral incision of bladder neck contracture may offer limited benefit: TURNS Study Group. J Urol. 2015;193(2):587-92. doi:10.1016/j.juro.2014.08.104.
8. Zhang L, Liu S, Wu K, Mu X, Yang L. Management of highly recurrent bladder neck contractures via transurethral resection combined with intra- and post-operative triamcinolone acetonide injections. World J Urol. 2021;39(2):527-532. doi:10.1007/s00345-020-03224-w.
9. Pang KH, Chapple CR, Chatters R, et al. A systematic review and meta-analysis of adjuncts to minimally invasive treatment of urethral stricture in men. Eur Urol. 2021;80(4):467-479. doi:10.1016/j.eururo.2021.06.022.
10. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482.
11. Quarta L, Bandini M, Corsini C, et al. Assessing predictors of failure after bladder neck incision in patients who developed bladder neck stenosis following transurethral surgery for benign prostatic enlargement. Prostate. 2025;85(15):1424-1431. doi:10.1002/pros.70027.
12. Vanni AJ, Zinman LN, Buckley JC. Radial urethrotomy and intralesional mitomycin C for the management of recurrent bladder neck contractures. J Urol. 2011;186(1):156-60. doi:10.1016/j.juro.2011.03.019.
13. Rozanski AT, Zhang LT, Holst DD, et al. The effect of radiation therapy on the efficacy of internal urethrotomy with intralesional mitomycin C for recurrent vesicourethral anastomotic stenoses and bladder neck contractures: a multi-institutional experience. Urology. 2021;147:294-298. doi:10.1016/j.urology.2020.09.035.
14. Sourial MW, Richard PO, Bettez M, Jundi M, Tu LM. Mitomycin-C and urethral dilatation: a safe, effective, and minimally invasive procedure for recurrent vesicourethral anastomotic stenoses. Urol Oncol. 2017;35(12):672.e15-672.e19. doi:10.1016/j.urolonc.2017.07.031.
15. Hacker EC, Maganty A, Pere MM, Rusilko PJ. Outcomes of vesicourethral anastomotic stenosis and bladder neck contracture with direct visual internal urethrotomy with mitomycin-C after prostate cancer treatment. Urology. 2022;165:331-335. doi:10.1016/j.urology.2022.01.041.
16. Farrell MR, Sherer BA, Levine LA. Visual internal urethrotomy with intralesional mitomycin C and short-term clean intermittent catheterization for the management of recurrent urethral strictures and bladder neck contractures. Urology. 2015;85(6):1494-9. doi:10.1016/j.urology.2015.02.050.
17. Sun X, Jin X, Leng K, Zhao Y, Zhang H. 180-W GreenLight laser photoselective vaporization with multiple triamcinolone acetonide injections for the treatment of bladder neck contractures. Lasers Med Sci. 2022;37(8):3115-3121. doi:10.1007/s10103-022-03568-2.
18. Wu MH, Liu JX, Zhang YF, et al. Bladder neck contracture following transurethral surgery of prostate: a retrospective single-center study. World J Urol. 2024;42(1):14. doi:10.1007/s00345-023-04715-2.
19. Farah RN, DiLoreto RR, Cerny JC. Transurethral resection combined with steroid injection in treatment of recurrent vesical neck contractures. Urology. 1979;13(4):395-7. doi:10.1016/0090-4295(79)90338-8.
20. Kravchick S, Lobik L, Peled R, Cytron S. Transrectal ultrasonography-guided injection of long-acting steroids in the treatment of recurrent/resistant anastomotic stenosis after radical prostatectomy. J Endourol. 2013;27(7):875-9. doi:10.1089/end.2012.0661.
21. Zhang K, Qi E, Zhang Y, Sa Y, Fu Q. Efficacy and safety of local steroids for urethra strictures: a systematic review and meta-analysis. J Endourol. 2014;28(8):962-8. doi:10.1089/end.2014.0090.
22. Sun J, Xia SQ, Tong Z, Xiao DD, Chen B. Transurethral columnar balloon dilation of the prostate combined with holmium laser incision for bladder neck contracture in day-surgery mode. Lasers Med Sci. 2023;38(1):279. doi:10.1007/s10103-023-03942-8.
23. Klein R, Vasan R, Guercio C, Rusilko P. Minimally invasive management of posterior urethral stricture/stenosis with DVIU and mitomycin C injection. Urology. 2024;183:e317-e319. doi:10.1016/j.urology.2023.10.006.
24. American Urological Association. Urethral Stricture Disease: AUA Guideline (published 2016; amended 2023), unabridged version. Guideline.
25. Cao G, Liu L, Du J, Li W, Li Q, Luo N, et al. Transurethral incision of the bladder neck at three points with a needle-type electrode for bladder neck contracture. Front Surg. 2022;9:871099. doi:10.3389/fsurg.2022.871099.
26. Castellani D, Stramucci S, Enganti B, et al. "One-Year Outcomes of Transurethral Treatment of Bladder Neck Stenosis Following Transurethral Resection of the Prostate. Results from a Large, Multicenter Series." Int J Gen Med. 2024;17:1967-1974. doi:10.2147/IJGM.S459441
27. Curtis J, Schrup S, Moring N, et al. "Transurethral Incision With Transverse Mucosal Realignment for the Treatment of Bladder Neck Contractures After Benign Prostate Surgery; Mid-term Outcomes." Urology. 2026 Jul 16. Online ahead of print. doi:10.1016/j.urology.2026.07.018
28. European Association of Urology. EAU Guidelines on Urethral Strictures. 2026. Diagnostic evaluation, section 5.2.1. Guideline.