Appendicovesicostomy (Mitrofanoff Procedure)
Appendicovesicostomy (the Mitrofanoff procedure) uses a vascularized appendix between the bladder or reservoir and an accessible skin stoma to permit clean intermittent catheterization (CIC). Mitrofanoff described it in 1980, with the distal appendix implanted in the bladder in a submucosal nonrefluxing fashion and the proximal end brought out as an inconspicuous stoma.[1] The tunneled reservoir insertion provides a flap-valve continence mechanism. The appendix is often preferred when it has suitable length, caliber and blood supply, but successful long-term use may require revision.[1][2][3]
See channel principles for reservoir pressure, access and follow-up, and Yang-Monti channels for bowel alternatives.
The Mitrofanoff principle
The principle is a narrow, supple tube implanted in a nonrefluxing manner in a reservoir and brought to a catheterizable stoma for intermittent emptying. The appendix is the commonest source of the tube. A ureter, Fallopian tube or tailored intestine may be used instead. The tube is buried in the reservoir wall in a tunnel about 5 cm long.[25] The reservoir can be the native bladder, an augmented bladder or a continent pouch. In Woodhouse's review, about 90% of patients were continent and up to 30% had conduit complications, particularly stenosis at the skin level.[25] That review found no significant difference in results by diagnosis, source of the tube or type of reservoir.[25] Sumfest's 47-patient series supported the appendix as the preferred catheterizable segment.[7]
Selection
AUA/SUFU supports catheterizable channels, with or without augmentation, in selected NLUTD patients to facilitate catheterization.[4] That AUA/SUFU guidance applies to adults .[4] The 2023 CUA/PUC pediatric NLUTD guideline separately permits a channel for select school-aged children or all adolescents with NLUTD who have difficulty performing urethral CIC .[40] Confirm that the patient or a dependable caregiver can catheterize and manage the stoma long term. Assess reservoir storage pressure and compliance when deciding whether a channel alone is appropriate. In selected adults with NLUTD who are refractory to or intolerant of less invasive therapies for detrusor overactivity and/or poor bladder compliance, AUA/SUFU permits augmentation cystoplasty .[4] Indications include difficult urethral access, urethral destruction, selected outlet closure and patient preference for easier abdominal access.[4]
Neurogenic disease, exstrophy or epispadias, cloacal anomalies, outlet obstruction and selected urinary diversions are common settings. Cain's 100-patient cohort was more than 90% neurogenic bladder, exstrophy-epispadias or cloacal anomaly combined.[5] In it, augmentation was performed in 52 patients, bladder neck reconstruction in 48 and a Malone antegrade colonic enema (MACE) in 17.[5] Harris's 50 patients had myelomeningocele (31), bladder exstrophy (6), prune-belly syndrome (2), posterior urethral valves (2) and other disorders (10).[26] Faure's 54 patients had neurogenic bladder (21), epispadias-exstrophy (12), bladder outlet obstruction (13), malignancy (6) and cloaca (2).[6]
Choose a stoma site that can be reached in the patient's usual seated position. The umbilicus can conceal the stoma, but convenience, channel reach, prior scars and body habitus take priority over a universal cosmetic preference. A bladder-neck closure makes an alternative dependable drainage route necessary; a CCC is one option, alongside selected permanent suprapubic drainage or diversion.[2][4]
Operative construction
Appendix and vascular pedicle
Assess appendiceal length, lumen and vascular anatomy before committing to the reconstruction. In VanderBrink's open technique, the right colon is mobilized along the white line of Toldt, as far as the hepatic flexure when needed, to bring the appendix and its pedicle to the stoma without tension.[36] Preserve the mesoappendix and appendicular vascular supply while separating the appendix from the cecum and securely closing the cecal defect. Calibrate for atraumatic passage of the planned catheter; do not force a fixed catheter size through an unsuitable appendix.[2][7][8]
VanderBrink describes taking the appendix with a cecal cuff to gain length and provide a wider skin opening intended to reduce skin-level stenosis; appendiceal lumen patency is assessed separately. If appendiceal length remains insufficient, adjacent cecal wall can be tubularized with the appendix over a stapler while preserving blood supply, a maneuver he describes as useful in patients with obesity.[36] Neither modification has been compared against the standard appendix-alone channel for stenosis or length outcomes.[36]
Plan orientation around pedicle reach and the selected stomal technique. The cecal base and distal appendiceal tip should be named explicitly during construction; “distal cut end” is ambiguous. Avoid twisting, tension and unnecessary skeletonization.[2][8]
Reservoir implantation
A submucosal or extravesical tunnel provides backed channel length without compressing it enough to impede catheterization. When channel implantation into an ileal or hindgut augment lacks bladder muscle or colonic taenia for backing, a serosal trough has been described in a pediatric exstrophy/epispadias series.[42] Published techniques commonly use several centimeters of backing; dimensions depend on the channel, reservoir and available anatomy.[2][9][10] A minimum intravesical submucosal tunnel of 2–3 cm has been described for the appendix without comparative continence outcomes.[36]
Wille's early robotic experience included 11 completed robotic cases. The one patient with less than 4 cm of backing developed leakage and subsequently became continent after bulking injection. This supports attention to backing. The series was too small to establish a 4-cm cutoff.[9]
Fixing the bladder to the abdominal wall near the proposed stoma, to reduce channel angulation and false passages, and securing the appendix to the outer bladder wall at the new hiatus, to limit channel retraction, have both been described as construction adjuncts. Repeatedly testing catheter passage and stomal continence with the bladder filled after each operative step has also been described, so a new difficulty can be traced to the step that introduced it.[36]
In Famakinwa's 18-child series, isolated channels were implanted extravesically in the anterior bladder, while channels accompanying augmentation were implanted intravesically on the posterior wall.[10]
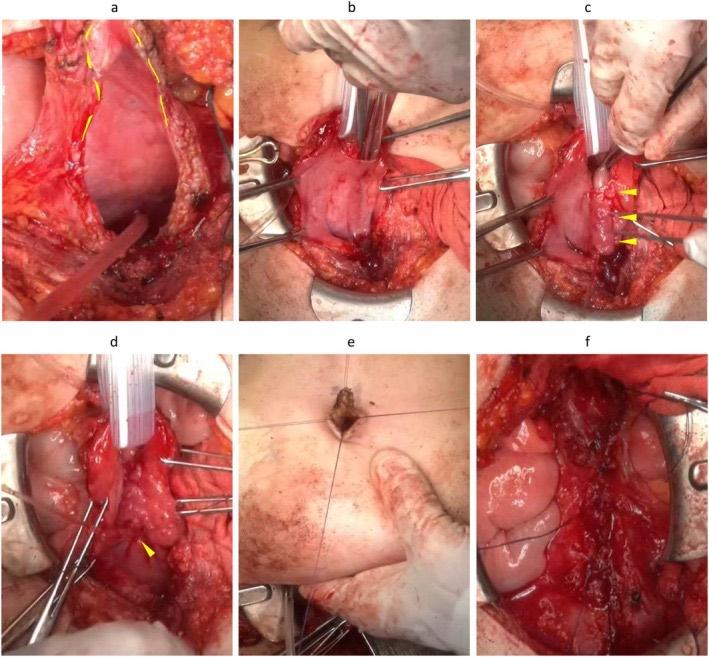
Open Mitrofanoff appendicovesicostomy combined with a Boari flap in an adult woman with complete urethral transection. (a) U-shaped incision of the anterior bladder wall (dotted line, Boari flap). (b) Submucosal tunnel of 55 mm. (c) The appendix is pulled into the submucosal tunnel (arrows). (d) Interrupted sutures join the bladder mucosa to the appendiceal mucosa (arrowhead). (e) V-flap incision of the umbilicus with interrupted sutures to the appendiceal mucosa. (f) Closure of the anterior bladder wall. From Mori K, et al. IJU Case Rep. 2026;9(2):e70154, Figure 2 (CC BY 4.0).[37]
Stomal maturation
Preserve distal blood supply and create an accessible, tension-free opening without a constricting circular scar. V-flap, VQ/VQZ and other skin-flap techniques can conceal bowel mucosa. Select the construction according to tissue and reach; no method eliminates stenosis.[11][12][13]
In De Ganck's retrospective series of 53 patients with 58 urinary or fecal stomas (45 appendiceal, 13 Monti), women and umbilical stomas had higher complication-to-follow-up ratios than men and abdominal-wall stomas on multivariable analysis.[27] The comparisons of skin-flap techniques are small and nonrandomized:
- The VQ plasty omits the Z component of the VQZ. In England's 21 patients, 23 stomas were constructed (11 VQZ, 12 VQ). VQ produced a neater skin-lined stoma with less scarring; this small comparison detected no difference in complications or stomal continence at mean follow-up of 15 versus 18.3 months.[28]
- The VR flap places the quadrilateral flap at 90 degrees to the V flap and allows a shorter conduit and a linear closure. In 12 children (24 channels, mean follow-up 18 months), all channels were continent, one patient needed revision and one needed dilation.[29]
- Landau reviewed 40 patients with 50 urinary or enema conduits: none of eight VQZ stomas required treatment for stenosis, compared with 8/31 umbilical conduits requiring dilation or revision for six stenoses and two obstructions.[11]
- Kurzrock compared 93 standard and 30 tip-preserving appendicostomies, including both urinary and enema channels. Stenosis occurred in 12/93 versus 0/30, with unequal median follow-up of 9.4 versus 3.3 years.[13]
- König reported 31 children, 30 appendiceal channels and 29 VQZ stomas. Six children had seven channel dysfunctions, and no superficial stenosis was observed. Among 21 survey responders, 20/21 (95%) used the channel daily and 0/21 reported channel leakage.[12]
Combined urinary and fecal access
A split appendix can provide urinary and antegrade-enema channels when its length and branching vascular supply permit. Confirm both segments remain perfused and reach their destinations without tension. Kajbafzadeh's 40-patient series combined split-appendix urinary and MACE channels with augmentation cystoplasty. Appendices were 9–15 cm long (mean 10.3 cm); all patients were reported continent at mean 22-month follow-up, and complications occurred in 3/40 (7.5%).[14] The authors considered a divided appendix suitable when it is 9 cm or more with a suitable branching mesentery.[14] A 2025 meta-analysis of 565 patients did not establish a complication advantage for split over intact appendix (29.2% versus 20.4%; OR 1.49, 95% CI 0.82–2.73); availability, perfusion and the need for two channels remain operative determinants.[39]
Daugherty retrospectively compared 106 simultaneous urinary and fecal reconstructions: 64 split appendices, 27 urinary Monti channels and 15 whole appendices used for the urinary channel. At median 44.5 months, no significant difference in revision-free survival was detected. Urinary subfascial revision occurred in 5/27 Monti channels versus none in the other two groups. Shorter operating time and stay in the split group are observational associations.[15]
What long-term outcomes mean
Distinguish stomal dryness, continued channel use, urethral continence and freedom from revision.
| Study | Population and follow-up | Findings and limits |
|---|---|---|
| Reuvers 2017 | 128 pediatric appendicovesicostomies; mean 10.1 years | All but one still used the channel; 32% required reintervention. Stomal incontinence occurred in 6.3%. Continued use was 99%; the report does not give a dry rate.[16] |
| Abdelhalim 2022 | 120 channels: 74 appendix, 33 Monti, 13 tapered ileum; median 11.4 years | Eventual dryness at intervals ≥3 hours in 90.8%; 26/120 required 42 interventions. About one-third of interventions occurred after five years. Ileal channels had higher adjusted odds of reoperation; tissue selection was not randomized.[17] |
| O'Connor 2019 | 176 consecutive adults; 173 included; mean follow-up 78.6 months, median 60 | Among 162 patients alive at last assessment, 123/162 (75.9%) still used a channel; 111/123 users (90.2%) reported continence. Complete channel revision occurred in 67/173 (38.7%). Channel incontinence was more frequent with ileum than appendix. The separate median 142-month interval since creation is not the reported clinical follow-up.[3] |
| Polm 2024 | 173 channels under adult surveillance; median 12.4 years | 92/173 required any revision. Major revision occurred in 27/90 appendiceal, 31/51 Monti and 12/32 bladder-flap channels. Major includes open subfascial or complete revision; no significant difference in revision-free survival was found.[18] |
These cohorts differ in diagnoses, techniques and ascertainment and may overlap earlier institutional publications. Earlier series with shorter follow-up reported similar continence:
| Study | Population and follow-up | Findings and limits |
|---|---|---|
| Harris 2000 | 50 consecutive patients, one surgeon; mean age 13.1 years; mean follow-up 4.3 years | 96% continued to catheterize and 98% were continent. Stomal stenosis 10% (5 patients); revision 16%[26] |
| Cain 1999 | 100 patients (57 appendicovesicostomy); mean follow-up 2 years | Stoma continent in 98 of 100. Complications requiring another procedure in 20, including stomal stenosis in 12. Continent vesicostomy had the most stomal problems (6 of 21)[5] |
| Faure 2017 | 54 patients with continent catheterizable channels (76% appendix); median follow-up 4.3 years | Operative revision in 33/54 (61%), mostly in the first 2 years. Stomal stenosis was the commonest complication, followed by leakage and conduit stricture.[6] |
| Gowda 2008 | 65 adults; mean age 38.4 years; mean follow-up 75.2 months | 46% had catheterization problems, most easy to treat. Five patients (8%) were converted to an ileal conduit. After two unrelated deaths, 58/63 surviving patients (92%) had a conduit, of which 97% were catheterizable and 95% continent[31] |
| Sahadevan 2008 | 29 adults identified; 28 assessed; median follow-up 126 months | 89% (25/28) reported continence. Stomal stenosis needing intervention in 15/28 (54%; nine needed stomal reconstruction), calculi in 8/28 (29%), and conversion to ileal conduit in 5/28 (18%; mean 82 months)[32] |
Harris reported appendicovesicostomy revision in 8/50 patients (16%)[26], while Faure reported operative revision in 33/54 (61%)[6]; Abdelhalim, Reuvers, O'Connor and Polm used differing reoperation, reintervention or revision endpoints and follow-up.[17][16][3][18] Counsel about substantial long-term reintervention risk.[6][16][18] In a 15-patient adult laparoscopic and robotic series (11 appendicovesicostomies and four Yang-Monti channels), 14 patients also underwent augmentation. At mean 22-month follow-up, 13/15 (87%) reported no regret about the overall reconstruction.[33]
Exstrophy context
Maruf's cohort included 432 classic-exstrophy patients who underwent successful closure and a continence procedure; continence was assessed in 350. Among evaluated patients, 124/133 after bladder-neck closure with a CCC were continent versus 91/142 after isolated bladder-neck reconstruction. Continence meant at least three hours dry without nighttime leakage. This was a selected observational comparison. The authors concluded that only about 25% of patients are expected to void normally per urethra.[19]
Complications and practical response
Skin stenosis, deeper channel stenosis, angulation, redundancy, false passage and reservoir or channel leakage require different treatment. Complications can arise years after construction, even when early follow-up was uncomplicated.[16][17][20][18]
Timing and frequency differ by series:
- Timing. In Jacobson's 81 patients (119 stomas, mean follow-up 80.1 months), 48 unique channel events occurred, clustered in the first 2 years and then declined significantly (P = 0.0013).[20] Difficult catheterization occurred in 20.1% of channels at an average of 29.9 months and stomal stenosis in 12.6% at an average of 19.9 months.[20] In Thomas's 78 patients (117 stomas), stomal stenosis appeared at a mean of 6.2 months (antegrade enema channels) and 9.4 months (bladder channels), and half were treated with surgical revision.[30] Abdelhalim, by contrast, found 32.5% of interventions more than 5 years after surgery.[17]
- Stenosis. Reported rates include 10% (Harris), 13% of standard appendicostomies (Kurzrock, 75% within a year) and 54% in adults (Sahadevan).[26][13][32] Kurzrock cited a literature range of 12% to 45% after appendicostomy.[26][13][32]
- False passage. It occurred in 6% of continent bladder channels (mean 6.5 months) and 10% of antegrade enema channels (mean 3.6 months) in Thomas's series, and was usually managed by catheter drainage alone.[30]
- Stones. They formed in 32% of Duckett’s mixed-channel cohort of 41 pediatric bladder reconstructions (61% appendix channels) at average follow-up of 3.2 years (mucus and bacteriuria as the nidus) and in 29% of Sahadevan’s assessed adults.[8][32]
- Conduit stricture and stenosis at the bladder level. Reuvers reported 9.4%.[16]
Inaccessible sole drainage channel. This is urgent. Avoid repeated forceful catheterization. Obtain prompt reconstructive-urology assessment and establish safe drainage, using endoscopic guidance or another route when needed. Assess storage pressure and incomplete emptying before treating leakage as an isolated tunnel defect.[4]
- Superficial stenosis: selected dilation, a temporary stomal device or skin revision. The L-stent report included only seven treated patients with subjective improvement; most also used topical betamethasone.[21]
- Recurrent stenosis: buccal graft revision is a salvage option. Radojicic reported no recurrent stenosis in ten mixed channel types at mean 22 months; only three were appendiceal channels.[22]
- Deep stricture, false passage or angulation: guided catheter drainage, endoscopic treatment or surgical revision according to anatomy. Avoid assuming that repeated blind dilation will address a structural kink.[16][20]
- Leakage: review reservoir pressure, emptying and tunnel integrity. Bulking injection may help selected patients; evidence is too limited to promise durable success.[4][9]
Alternatives when the appendix is unavailable
The appendix may be absent, needed for a MACE or unsuitable. Channel principles and the Yang-Monti page cover the alternatives. In Lemelle’s 46 patients (65 conduits: 41 urinary Mitrofanoff and 24 fecal Malone), 61/65 (93.8%) were in use at mean follow-up of 5.3 years, with no significant difference by appendix versus Yang-Monti channel; the authors recommended Yang-Monti when the appendix is unsuitable.[34] In Polm's 112 children (117 channels), surgical revision was required in 52% with no difference in revision-free survival among appendix, tubularized bladder flap and Monti channels.[35] Major revision occurred in 32/117 channels (27%) overall and was significantly more frequent with Monti channels (10/19, 53%) than with appendiceal (15/67, 22%) or bladder-flap channels (7/31, 23%).[35] Ileal channels had higher adjusted odds of reoperation than appendix channels in Abdelhalim's cohort of patients aged up to 21 years, and higher rates of full channel revision for incontinence in O'Connor's adult series (36.0% vs 19.5%, P = 0.03).[17][3]
Minimally invasive approaches
Open, laparoscopic-assisted and robotic construction are feasible in experienced hands. Comparative evidence is predominantly retrospective and confounded by concomitant operations and case selection. In a 2026 meta-analysis of six pediatric comparative studies (147 robotic, 123 open procedures), robotic surgery was associated with less blood loss and shorter stay, while no significant difference was detected in reintervention, stenosis or incontinence.[38]
Chua compared 12 laparoscopic-assisted with 11 open isolated appendicovesicostomies after prior abdominal surgery. Median blood loss (50 vs 100 mL, P = 0.048) and stay (3.5 vs 6 days, P = 0.029) were lower in the laparoscopic-assisted group.[23] No significant difference in major complications or continence was detected.[23] Famakinwa's robotic series comprised 18 children (10 intravesical, 8 extravesical), with mean operative time of 494 minutes, mean stay of 5.2 days, median follow-up of 24.2 months and stomal continence of 94.4%.[10]
Cerchia's exploratory series of seven boys describes fully laparoscopic and laparoscopic-assisted techniques for settings without robotics.[24]
Follow-up
Review catheter passage, drainage schedule, leakage, stoma changes, infections, renal function and upper tracts throughout life. In adults with NLUTD whose impaired storage or voiding places the upper tracts at risk, AUA/SUFU recommends repeat urodynamics at an appropriate interval after treatment .[4] Adjust catheter size and timing to the reconstruction; teach an urgent access-failure plan before discharge.[4][18]
For NLUTD with lower urinary tract reconstruction incorporating bowel, AUA/SUFU advises annual history, examination and symptom assessment, a basic metabolic panel and urinary tract imaging . The statement text notes that a patient with only a continent stoma and no augmentation is not at risk of the electrolyte or acid-base abnormalities seen after augmentation, so annual evaluation without a metabolic panel would suffice. Follow augmentation surveillance when relevant.[4]
Annual screening cystoscopy from year ten is not routine. In adults with NLUTD, AUA/SUFU advises against screening or surveillance cystoscopy .[41] After lower urinary tract reconstruction using bowel in adults with NLUTD, gross hematuria or symptomatic recurrent UTI warrants cystoscopy .[4] In adults with NLUTD after bowel reconstruction, unexplained suprapubic pain also warrants full evaluation, including cystoscopy, urine cytology and abdominopelvic CT.[4]
Videos
References
1. Duckett JW, Snyder HM. "Continent Urinary Diversion: Variations on the Mitrofanoff Principle." The Journal of Urology. 1986;136(1):58-62. doi:10.1016/s0022-5347(17)44725-2
2. Cendron M, Gearhart JP. "The Mitrofanoff Principle. Technique and Application in Continent Urinary Diversion." The Urologic Clinics of North America. 1991;18(4):615-21. doi:10.1016/s0094-0143(21)00363-3
3. O'Connor EM, Foley C, Taylor C, et al. "Appendix or Ileum — Which Is the Best Material for Mitrofanoff Channel Formation in Adults?" The Journal of Urology. 2019;202(4):757-762. doi:10.1097/JU.0000000000000356
4. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Treatment and Follow-Up." The Journal of Urology. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239
5. Cain MP, Casale AJ, King SJ, Rink RC. "Appendicovesicostomy and Newer Alternatives for the Mitrofanoff Procedure: Results in the Last 100 Patients at Riley Children's Hospital." The Journal of Urology. 1999;162(5):1749-52. doi:10.1016/s0022-5347(05)68230-4
6. Faure A, Cooksey R, Bouty A, et al. "Bladder Continent Catheterizable Conduit (The Mitrofanoff Procedure): Long-Term Issues That Should Not Be Underestimated." Journal of Pediatric Surgery. 2017;52(3):469-472. doi:10.1016/j.jpedsurg.2016.09.054
7. Sumfest JM, Burns MW, Mitchell ME. "The Mitrofanoff Principle in Urinary Reconstruction." The Journal of Urology. 1993;150(6):1875-7. doi:10.1016/s0022-5347(17)35921-9
8. Duckett JW, Lotfi AH. "Appendicovesicostomy (and Variations) in Bladder Reconstruction." The Journal of Urology. 1993;149(3):567-9. doi:10.1016/s0022-5347(17)36150-5
9. Wille MA, Zagaja GP, Shalhav AL, Gundeti MS. "Continence Outcomes in Patients Undergoing Robotic Assisted Laparoscopic Mitrofanoff Appendicovesicostomy." The Journal of Urology. 2011;185(4):1438-43. doi:10.1016/j.juro.2010.11.050
10. Famakinwa OJ, Rosen AM, Gundeti MS. "Robot-Assisted Laparoscopic Mitrofanoff Appendicovesicostomy Technique and Outcomes of Extravesical and Intravesical Approaches." European Urology. 2013;64(5):831-6. doi:10.1016/j.eururo.2013.05.007
11. Landau EH, Gofrit ON, Cipele H, et al. "Superiority of the VQZ Over the Tubularized Skin Flap and the Umbilicus for Continent Abdominal Stoma in Children." The Journal of Urology. 2008;180(4 Suppl):1761-5. doi:10.1016/j.juro.2008.04.070
12. König A, Wiseman AX, Wildhaber B, Vidal I, Birraux J. "Mitrofanoff Procedure in Children: Use of the Appendix and VQZ Plasty Seems to Minimize Complications." Pediatric Surgery International. 2025;41(1):304. doi:10.1007/s00383-025-06204-6
13. Kurzrock EA. "A New Appendicostomy Technique to Prevent Stomal Stenosis." The Journal of Urology. 2020;203(6):1200-1206. doi:10.1097/JU.0000000000000711
14. Kajbafzadeh AM, Chubak N. "Simultaneous Malone Antegrade Continent Enema and Mitrofanoff Principle Using the Divided Appendix: Report of a New Technique for Prevention of Stoma Complications." The Journal of Urology. 2001;165(6 Pt 2):2404-9. doi:10.1016/S0022-5347(05)66215-5
15. Daugherty M, Strine A, Frischer J, et al. "Outcomes According to Channel Type for Continent Catheterizable Channels in Patients Undergoing Simultaneous Urinary and Fecal Reconstruction." Journal of Pediatric Surgery. 2021;56(8):1335-1341. doi:10.1016/j.jpedsurg.2020.11.002
16. Reuvers SHM, van den Hoek J, Blok BFM, et al. "20 Years Experience With Appendicovesicostomy in Paediatric Patients: Complications and Their Re-Interventions." Neurourology and Urodynamics. 2017;36(5):1325-1329. doi:10.1002/nau.23045
17. Abdelhalim A, Omar H, Edwan M, et al. "Reoperation for Channel Complications in Children With Continent Cutaneous Catheterizable Channels: The Test of Time." Urology. 2022;159:196-202. doi:10.1016/j.urology.2021.08.015
18. Polm PD, Christiaans CHH, Dik P, Wyndaele MIA, de Kort LMO. "Continent Catheterizable Urinary Channels: Lessons for Lifelong Urological Care From a Comparative Analysis of Very Long-Term Complications and Revision-Free Survival of Three Different Types." Neurourology and Urodynamics. 2024;43(5):1083-1089. doi:10.1002/nau.25350
19. Maruf M, Manyevitch R, Michaud J, et al. "Urinary Continence Outcomes in Classic Bladder Exstrophy: A Long-Term Perspective." The Journal of Urology. 2020;203(1):200-205. doi:10.1097/JU.0000000000000505
20. Jacobson DL, Thomas JC, Pope J, et al. "Update on Continent Catheterizable Channels and the Timing of Their Complications." The Journal of Urology. 2017;197(3 Pt 2):871-876. doi:10.1016/j.juro.2016.08.119
21. Mickelson JJ, Yerkes EB, Meyer T, Kropp BP, Cheng EY. "L Stent for Stomal Stenosis in Catheterizable Channels." The Journal of Urology. 2009;182(4 Suppl):1786-91. doi:10.1016/j.juro.2009.02.068
22. Radojicic ZI, Perovic SV, Rados DP, Petar VM. "Buccal Mucosa Grafts for Repair of Stenotic Catheterizable Continent Stoma." The Journal of Urology. 2008;180(4 Suppl):1767-9. doi:10.1016/j.juro.2008.03.116
23. Chua ME, Ming JM, Kim JK, et al. "Laparoscopic-Assisted Versus Open Appendicovesicostomy Procedure in Patients With Prior Abdominal Surgeries: A Comparative Study." Urology. 2018;116:93-98. doi:10.1016/j.urology.2018.02.036
24. Cerchia E, Serpentino M, Nguyen Duy V, et al. "Minimally Invasive Mitrofanoff in Children: Versatile Laparoscopic Strategies-From Low-Resource to Non-Robotic High-Cost Settings in an Exploratory Case Series." Journal of Clinical Medicine. 2026;15(5):1954. doi:10.3390/jcm15051954
25. Woodhouse CR. "The Mitrofanoff Principle for Continent Urinary Diversion." World Journal of Urology. 1996;14(2):99-104. doi:10.1007/BF00182565
26. Harris CF, Cooper CS, Hutcheson JC, Snyder HM. "Appendicovesicostomy: The Mitrofanoff Procedure — A 15-Year Perspective." The Journal of Urology. 2000;163(6):1922-6. doi:10.1016/s0022-5347(05)67599-4
27. De Ganck J, Everaert K, Van Laecke E, Oosterlinck W, Hoebeke P. "A High Easy-to-Treat Complication Rate Is the Price for a Continent Stoma." BJU International. 2002;90(3):240-3. doi:10.1046/j.1464-410x.2002.02805.x
28. England RJ, Subramaniam R. "Functional and Cosmetic Outcome of the VQ Plasty for Mitrofanoff Stomas." The Journal of Urology. 2007;178(6):2607-10. doi:10.1016/j.juro.2007.08.030
29. Franc-Guimond J, González R. "Simplified Technique to Create a Concealed Catheterizable Stoma: The VR Flap." The Journal of Urology. 2006;175(3 Pt 1):1088-91. doi:10.1016/S0022-5347(05)00403-9
30. Thomas JC, Dietrich MS, Trusler L, et al. "Continent Catheterizable Channels and the Timing of Their Complications." The Journal of Urology. 2006;176(4 Pt 2):1816-20. doi:10.1016/S0022-5347(06)00610-0
31. Gowda BD, Agrawal V, Harrison SC. "The Continent, Catheterizable Abdominal Conduit in Adult Urological Practice." BJU International. 2008;102(11):1688-92. doi:10.1111/j.1464-410X.2008.07885.x
32. Sahadevan K, Pickard RS, Neal DE, Hasan TS. "Is Continent Diversion Using the Mitrofanoff Principle a Viable Long-Term Option for Adults Requiring Bladder Replacement?" BJU International. 2008;102(2):236-40. doi:10.1111/j.1464-410X.2008.07467.x
33. Rey D, Helou E, Oderda M, et al. "Laparoscopic and Robot-Assisted Continent Urinary Diversions (Mitrofanoff and Yang-Monti Conduits) in a Consecutive Series of 15 Adult Patients: The Saint Augustin Technique." BJU International. 2013;112(7):953-8. doi:10.1111/bju.12257
34. Lemelle JL, Simo AK, Schmitt M. "Comparative Study of the Yang-Monti Channel and Appendix for Continent Diversion in the Mitrofanoff and Malone Principles." The Journal of Urology. 2004;172(5 Pt 1):1907-10. doi:10.1097/01.ju.0000140448.36332.fc
35. Polm PD, de Kort LMO, de Jong TPVM, Dik P. "Techniques Used to Create Continent Catheterizable Channels: A Comparison of Long-Term Results in Children." Urology. 2017;110:192-195. doi:10.1016/j.urology.2017.08.030
36. VanderBrink BA. Appendicovesicostomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:392-399.
37. Mori K, Iwata T, Kawada T, et al. "Mitrofanoff Appendicovesicostomy With Boari Flap for Complete Female Urethral Transection: A Case Report." IJU Case Reports. 2026;9(2):e70154. doi:10.1002/iju5.70154
38. Liu Y, Xu Z, Feng S, Tian Y. "Comparative outcomes of robot-assisted and open appendicovesicostomy in children: a systematic review and meta-analysis." Pediatr Surg Int. 2026;42(1):362. doi:10.1007/s00383-026-06601-5
39. Chua ME, Rivera K, Romao R, et al. "Mitrofanoff complications: time-to-event analysis of split versus intact appendix and meta-analysis." World J Urol. 2025;43(1):90. doi:10.1007/s00345-024-05434-y
40. Chua ME, Yadav P, Wang PZT, et al. "2023 Canadian Urological Association/Pediatric Urologists of Canada guideline: Pediatric patients with neurogenic lower urinary tract dysfunction: Full-text version." Can Urol Assoc J. 2023;17(10):E338-E357. doi:10.5489/cuaj.8390
41. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Diagnosis and Evaluation." J Urol. 2021;206(5):1097-1105. doi:10.1097/JU.0000000000002235
42. Baradaran N, Stec AA, Gupta A, Keating MA, Gearhart JP. "Using a serosal trough for fashioning a continent catheterizable stoma: technique and outcomes." BJU Int. 2013;111(5):828-833. doi:10.1111/j.1464-410X.2012.11319.x