Augmentation Cystoplasty
Augmentation cystoplasty (AC) increases bladder capacity and lowers storage pressure in selected patients with refractory neurogenic or non-neurogenic bladder dysfunction.[1][2][3] AUA/SUFU says clinicians may offer AC to selected NLUTD patients refractory to or intolerant of less invasive treatment for detrusor overactivity and/or poor compliance .[4] For idiopathic OAB, it says clinicians may offer AC or diversion only to severely impacted patients who have not responded to all other therapeutic options .[51] The modern operation is usually a detubularized ileocystoplasty: a short ileal segment is isolated, opened along its antimesenteric border, reconfigured into a low-pressure patch, and anastomosed to a widely bivalved bladder.[1][8][9]
The core indication for augmentation is an unsafe reservoir: high storage pressures, poor compliance, and progressive upper-tract deterioration despite optimized conservative therapy.[2][4][5] AC lowers storage pressure and protects the upper tracts, with conversion to diversion in 2.7% at 10 years in one spina bifida cohort, but it exchanges one disease state for a lifelong reconstructed system that requires reliable emptying (often clean intermittent catheterization [CIC]), mucus management, metabolic surveillance, and vigilance for stones, perforation, and late malignancy.[1][17][19][20]
EAU 2026 makes a strong recommendation to offer augmentation for low compliance and/or refractory neurogenic detrusor overactivity. Its evidence statement (level 3) describes augmentation as effective when all less invasive treatments have failed. EAU states that lifelong follow-up is required given the morbidity of the procedure.[33]
Indications
Augmentation cystoplasty is indicated when the bladder remains hostile despite appropriate medical and minimally invasive management:
| Indication | Practical meaning |
|---|---|
| Refractory low-capacity / poorly compliant bladder | Failure or intolerance of appropriate storage therapy and optimized emptying; botulinum toxin is considered where suitable[1][4] |
| Unsafe storage pressure | High filling pressure or poor compliance on urodynamics that threatens the upper tracts; detrusor leak-point pressure should not be used alone to estimate risk[2][4][33] |
| Upper-tract deterioration | Hydronephrosis, vesicoureteral reflux, recurrent pyelonephritis, or declining renal function attributable to a hostile bladder[2][5][17] |
| Refractory incontinence | Incontinence despite CIC and medical therapy, especially in neurogenic bladder patients with salvageable outlet function or a plan for concomitant outlet surgery[2][17][18] |
Common underlying disease states include spina bifida, spinal cord injury, posterior urethral valves, bladder exstrophy, genitourinary tuberculosis, and severe idiopathic detrusor overactivity or fibrosis.[1][3][6]
Practical contraindications
Selection depends on disease, renal reserve, bowel health, and a workable lifelong care plan:
- Significant renal insufficiency or azotemia. Increases the consequences of bowel-mediated solute exchange, especially with colon and ileum[2][7][23]
- No dependable emptying and irrigation plan. Patients or caregivers must be able to perform catheterization if needed; spontaneous voiding cannot be guaranteed, and an inaccessible or unmanageable reservoir risks retention, stones, and perforation[1][4]
- Short bowel, major prior bowel resection, or active inflammatory bowel disease. May limit usable segment choice or make bowel incorporation unacceptable[2][3]
- Untreated outlet obstruction or unresolved outlet incompetence. Many patients need a concomitant outlet procedure[1][16]
- Active or recently treated urothelial carcinoma of the native bladder. Establish current tumor stage, grade and treatment-response category with the oncologic team before planning augmentation of a contracted bladder after TURBT or intravesical therapy.[35][48] AUA/SUO recommends offering radical cystectomy to surgically fit patients with high-grade T1 disease after one induction BCG course , and to high-risk patients with persistent or recurrent disease within 12 months after two induction cycles or BCG maintenance .[48] Prior BCG exposure alone does not establish these indications: in low- or intermediate-risk Ta disease, clinicians should not perform radical cystectomy until bladder-sparing modalities (staged TURBT or intravesical therapy) have failed .[48] Neither the AUA/SUO guideline nor NCCN addresses reconstruction of a cancer-free bladder contracted after BCG, and no series reports augmentation in this setting. Vesical malignancy is a classic contraindication to augmentation.[7] Augmentation also leaves the native urothelium in place, so cancer surveillance continues. BCG contracture severe enough to need surgery is rare: two databases found 1 case each (0.05% and 0.3% of their cystectomies).[49] Both patients had cystoprostatectomy with an orthotopic ileal neobladder, neither specimen held residual cancer, and symptoms resolved.[49] Decide between augmentation and cystectomy with the oncologic team; the choice rests on cancer history and surveillance needs.
Preoperative Decision Framework
Before offering AC, the reconstructive question is whether the patient needs a bigger low-pressure reservoir, a different outlet, or an incontinent bypass altogether.
The classic augmentation candidate
- Safe renal reserve, or at least enough reserve to tolerate bowel incorporation
- Proven low-capacity / poor-compliance bladder on urodynamics
- Failure of optimized medical therapy and usually botulinum toxin
- Patient or caregiver ability to catheterize if required, with frequency tailored to urine production, capacity, pressures, and residuals
- Willingness to irrigate mucus and accept lifelong follow-up[1][4]
The patient who may be better served by diversion
In patients unable to catheterize, medically fragile patients, or those with recurrent complications from a hostile native bladder, ileal conduit or ileovesicostomy may be preferable to augmentation.[4][21]
The pre-transplant candidate
Voiding-dysfunction evaluation (symptom scores, prostate ultrasound, urodynamics) is not routinely performed before kidney transplantation and is generally reserved for patients with a urologic cause of end-stage renal disease or a prior urologic intervention. When a candidate has a history of high-pressure voiding from bladder outlet obstruction plus bilateral hydronephrosis and renal cortical atrophy, determining bladder capacity and voiding pressures before transplant can guide management of the future allograft, since a high-pressure bladder found on that evaluation may need pharmacologic or procedural measures to maintain normal filling pressures. In an oliguric or anuric dialysis candidate without a demonstrated hostile reservoir, timing of elective transurethral outlet surgery is individualized: pretransplant TURP may be followed by bladder-neck contracture or urethral scarring, while obstructive symptoms may appear only after urine flow resumes following transplantation.[53] These patients are counseled that catheterization and further procedures, including augmentation if still indicated, may be needed once the graft is producing urine and true bladder behavior can be assessed. Periodic instillation to keep a defunctionalized, anuric bladder capacious ("bladder cycling") has been proposed, but the cited study did not test cycling or measure recovery of bladder capacity. In its retrospective comparison, 41 recipients with prolonged anuria and 31 preemptive recipients had no significant difference in surgical complications; the anuric group had more admissions for complicated UTI.[41] When a later kidney transplant is performed in a patient who already has an augmented bladder, the augment's vascular pedicle and its anastomotic orientation should be identified before dissection proceeds, because disrupting it can compromise the cystoplasty.[42]
Required preoperative workup
- History focused on catheterization ability, continence goals, bowel history, prior abdominal surgery, and prior radiation or tuberculosis
- Urodynamics documenting low capacity and/or poor compliance
- Upper-tract imaging for hydronephrosis or reflux
- Baseline renal function and electrolytes
- Ventriculoperitoneal shunt status. Many adults with spina bifida still carry a pediatric VP shunt placed for Chiari II-associated hydrocephalus; note its presence before any transabdominal reconstruction. A retrospective series of 31 children with ventriculoperitoneal shunts undergoing bladder reconstruction with bowel found shunt infections in 3/31 (9.6%) within 2 months postoperatively; rates were 2/19 (10.5%) with and 1/12 (8.3%) without mechanical bowel preparation (p = 1.0). Maintain a low threshold for shunt infection or malfunction postoperatively.[37]
- Counseling that augmentation is a lifelong reconstructed state[1][2][4]
Technique Overview
Gold standard: enterocystoplasty
Enterocystoplasty remains the reference standard because bowel provides a large compliant patch that can be configured into a low-pressure reservoir.[1][3] The main technical principle is detubularization: the isolated bowel is opened so that coordinated tubular contractions are reduced; residual pressure waves may persist.[8][9]
Core steps of augmentation cystoplasty
- Mobilize and widely bivalve the bladder to create a broad native plate. For a severely thick, fibrotic bladder wall, EAU 2026 identifies supratrigonal cystectomy before augmentation as an alternative preparation.[33]
- Isolate the chosen bowel segment with preservation of mesenteric blood supply.
- Re-establish bowel continuity.
- Detubularize and reconfigure the segment into a patch or cup.
- Anastomose the bowel patch to the opened bladder in a tension-free, watertight fashion.
- Add concomitant procedures as needed: catheterizable channel, ureteral reimplantation, or outlet surgery.[1][8][16]
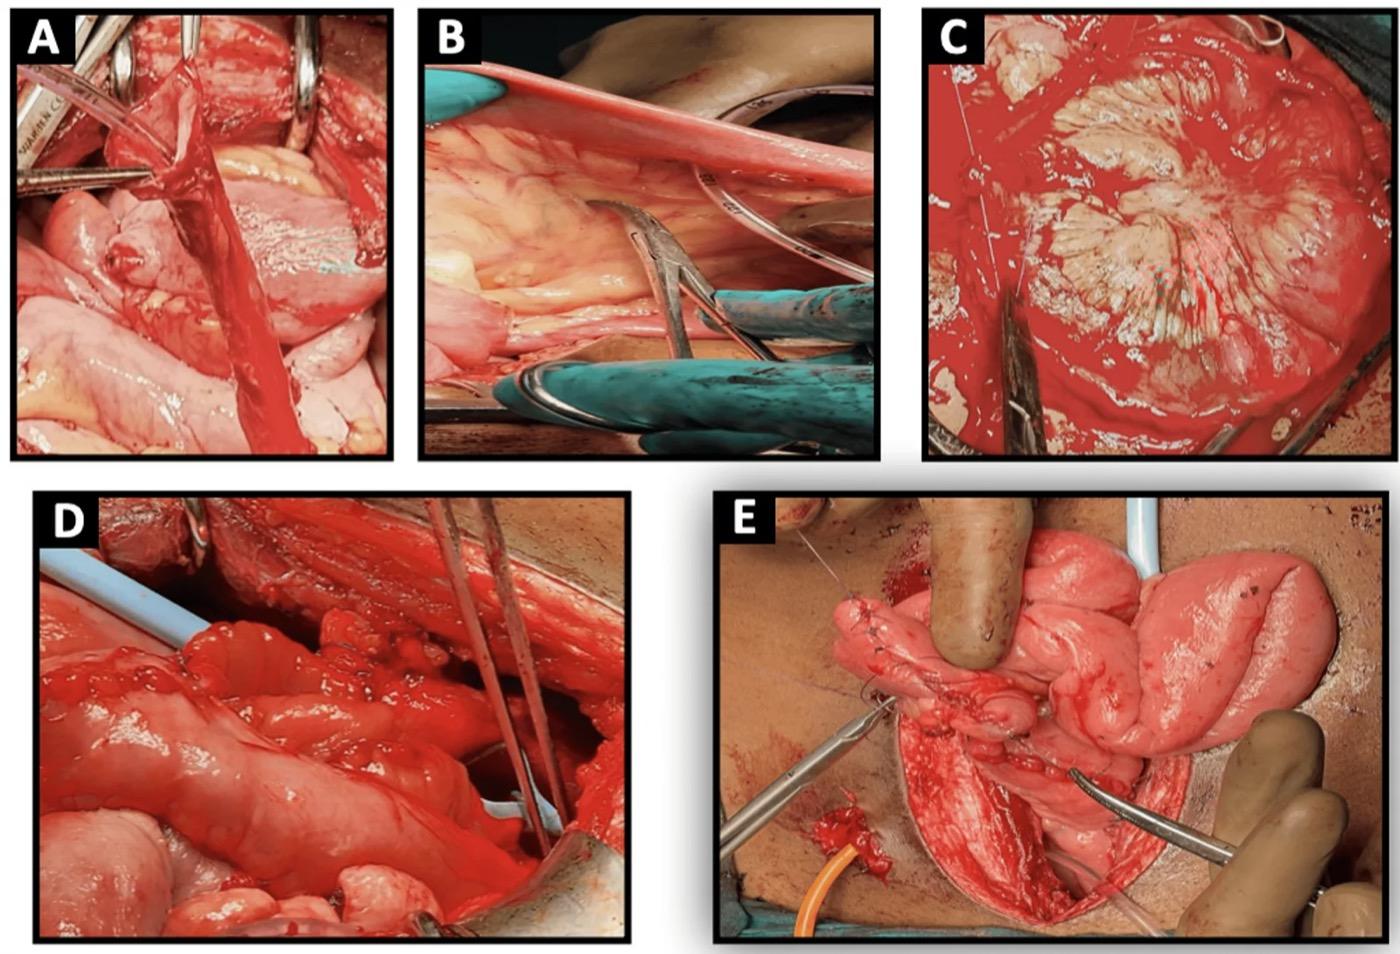
Open ileal augmentation cystoplasty with concomitant procedures in an adolescent girl. (A) Left ureteric reimplantation. (B) A 30-cm ileal segment harvested 20 cm proximal to the ileocecal junction. (C) The detubularized ileal segment in a U configuration. (D) An 18-Fr Malecot catheter placed. (E) Completed augmentation cystoplasty, with the Mitrofanoff channel brought out through a V-flap stoma in the right lower quadrant and a Foley catheter in situ. From Jain P, et al. Cureus. 2026;18(8):e114796, Figure 4 (CC BY 4.0).[50]
Positioning, Drainage, and VTE Prophylaxis
Augmentation is a transabdominal (open, laparoscopic, or robotic) operation performed supine; when a catheterizable channel, bladder-neck procedure, or intraoperative cystoscopy is also planned, one published robotic pediatric technique instead uses supine semi-lithotomy with about 10° Trendelenburg, siting the extra robotic arm port at the planned stoma location so catheter and cystoscopic access do not require repositioning.[34] That series used two suprapubic tubes (because one was prone to dislodgement or clogging) and a urethral Foley catheter for free drainage for 4 weeks; the small appendicovesicostomy catheter was capped and secured to the abdomen. At 4 weeks the channel catheter was removed and CIC teaching began, with the suprapubic tubes removed after the patient or family demonstrated competent CIC.[34] Ureteral stents are added when reimplantation is performed. This is one published drainage protocol; no consensus duration has been established across the wider literature.[34]
No augmentation-specific VTE recommendation exists in the AUA/SUFU NLUTD guideline.[4] This is major abdominal surgery with a bowel anastomosis, often a long operative time, and a population that includes limited-mobility neurogenic-bladder patients; apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page, weighted toward the higher end for this operation.
Segment Selection and Configuration
| Technique | Reconstructive role | Key advantages | Main tradeoffs |
|---|---|---|---|
| Ileocystoplasty | Standard modern augmentation | Familiar segment, reliable mesentery, low-pressure dynamics after detubularization[1][8][9] | Hyperchloremic metabolic acidosis, mucus, B12 deficiency risk with longer segments[22][23] |
| Sigmoidocystoplasty | Alternative when colon is preferred | Can reduce small-bowel handling; cup-patch configuration outperforms tubular colon[8][9] | Similar acidosis / mucus issues; colon can be bulky in a deep pelvis |
| Ileocecal cystoplasty | — | Helpful when a wide gap exists between ureters and bladder or when massively dilated ureters require implantation[9] | More complex bowel work; same bowel-related surveillance burden |
| Gastrocystoplasty | Historical niche, mostly renal-insufficiency logic | Lower chloride reabsorption, less mucus, lower stone burden, avoids further small-bowel resection[3][10][11] | Hematuria-dysuria syndrome, metabolic alkalosis, concerning malignancy signal[10][11][28] |
Why ileum remains the default
Ileum is the default segment for its reach, ease of detubularization and reservoir dynamics. Comparative evidence is limited: in one series of 133 patients, sigmoid colon showed a trend toward less small-bowel obstruction and no difference in perforation or stone formation compared with ileum.[8] A typical segment length is 15–40 cm, but the exact length is driven by bladder plate size, target capacity, mesenteric reach, and whether a concomitant channel is needed.[1][8][9]
Configuration matters more than segment name
The major technical lesson from the classic enterocystoplasty literature is that detubularized reconfigured bowel behaves better than intact tubular bowel. A small historical comparison found fewer volume-dependent contractions and higher continence with a sigmoid cup patch than with tubular sigmoid or intact ileocecal segments.[9] A 133-patient series found no perforation difference between ileal and sigmoid augmentations.[8] In a separate retrospective spina bifida cohort, reconfigured ileocystoplasty was associated with lower perforation risk.[20]
Alternative and Salvage Augmentation Strategies
Autoaugmentation
Autoaugmentation (vesicomyotomy / detrusorectomy) removes detrusor over the dome while leaving the urothelium intact, allowing the mucosa to bulge outward as a pseudodiverticulum.[12][13] It avoids bowel-related morbidity and does not preclude later enterocystoplasty.[12][13] A directed review of pediatric series concluded that compliance gains after autoaugmentation were generally smaller and shorter-lived than after enterocystoplasty.[54]
Seromuscular colocystoplasty lined with urothelium (SCLU)
SCLU combines autoaugmentation with a demucosalized colonic patch placed over preserved urothelium, aiming to avoid bowel-mucosa complications such as mucus and metabolic exchange.[8]
Ureterocystoplasty
Ureterocystoplasty uses a suitably dilated ureter to augment the bladder without bowel. Many reported operations use the ureter of a poorly functioning renal unit; selected approaches preserve the kidney with a separate drainage reconstruction.[14] Applicability is limited to patients with a suitable ureteral scenario.
Robot-assisted augmentation
Robot-assisted laparoscopic ileocystoplasty has been reported in both adult and pediatric series, often combined with Mitrofanoff creation.[15][16] Potential recovery and cosmetic benefits must be weighed against operative complexity and time.
An earlier laparoscopic-extracorporeal technique has been described in which the selected ileal segment is delivered through the umbilical or a lower-port incision for extracorporeal isolation, detubularization, and reconfiguration before reinsertion; the authors preferred completing the posterior bowel-to-bladder wall first, using intravesical visualization before the anterior wall could obstruct the pelvic view, and described a wide curvilinear anterior cystotomy when a uterus limited access. No comparative outcome for this sequence or incision was reported.[44]
Concomitant Procedures
Augmentation often succeeds only when paired with additional reconstructive steps:
| Concomitant procedure | Why it is added |
|---|---|
| Continent catheterizable channel (Mitrofanoff / appendicovesicostomy) | For patients who cannot catheterize the native urethra reliably[1][16] |
| Ureteral reimplantation | For selected anatomic obstruction or ureteral reconstruction needs; high-pressure reflux, including high-grade (IV–V) reflux, can improve with augmentation alone. In one series, 87.5% of 16 grade IV–V ureters followed after augmentation without reimplantation resolved or improved. EAU notes uncertainty about routine simultaneous reimplantation for high-grade reflux; some reconstructive surgeons instead correct high-grade reflux at the time of augmentation as a matter of practice[33][1][5][9][45][46] |
| Outlet procedure | Sling, AUS, bladder-neck reconstruction, or bladder-neck closure when continence will not be achieved by augmentation alone[1][16][18] |
In many patients the real construct is a rebuilt reservoir plus a rebuilt outlet.
Stomal stenosis is the most common failure of a catheterizable channel. Dilation should be cautious and limited to the minimum size needed to resume catheterization; aggressive dilation risks injury to the adjacent bowel and fistula formation. A short, knotted catheter left flush with the skin (an "L stent") can be used intermittently for stomal narrowing. In a retrospective series, seven of eight patients with stenosis used one, all seven reported improvement, and six also used topical betamethasone; the series did not quantify surgical revision avoidance.[39] When revision is required, channel replacement or an above-fascia repair achieved more durable patency than a below-fascia repair in a multi-institutional adult cohort, though postoperative channel incontinence occurred in 40% of all revisions.[40]
Outcomes
Reservoir function
Across modern series and reviews, AC reliably increases bladder capacity and compliance while reducing storage pressure.[1][17][19] Renal protection is attributed to the lower storage pressure rather than to the larger volume alone.
Continence
Reported continence rates range from 78% to 95%, especially when concomitant outlet procedures are used appropriately.[8][18] Venn and Mundy reported 78% continence with cystoplasty alone in neuropathic bladders, rising to 90% with an artificial urinary sphincter, and 93% for detrusor instability; Shekarriz reported 95% overall.[8][17][18] Reported success varies because some series define success as daytime dryness, others as social continence, and others include patients with catheterizable channels or AUS.
Upper-tract preservation
Hydronephrosis and reflux improve or resolve in most patients, and renal function often stabilizes when the reservoir is made safe early enough.[5][17]
Durability
In Szymanski et al.’s retrospective cohort of 413 patients with spina bifida, estimated 10-year conversion to diversion was 2.7%, but any reoperation was 43.9%. These are time-to-event estimates from a mixed-era cohort; in the 222-patient modern subgroup, corresponding estimates were 4.0% and 46.0%.[20]
Quality of life
Some patients report better continence and independence after successful augmentation, alongside burdens of CIC, irrigation, stone surveillance, and reintervention.[1][19] A 2025 adult NLUTD review found three pre/post reconstruction studies (augmentation and/or catheterizable channels; n = 94). Only one study (n = 67) used validated quality-of-life measures and reported relative improvements across measured domains of about 7%–28%; the other two used unvalidated measures.[52]
Complications
Augmentation cystoplasty requires lifelong maintenance. Early risks include bowel-bladder anastomotic leak, ileus or bowel obstruction, postoperative UTI, and acute kidney injury; seven of 22 children in one retrospective series had at least one early complication.[17] The main late complications follow.
Stones
Bladder or reservoir stones were the most frequent late surgical complication in the 413-patient Szymanski spina bifida cohort, with an estimated 28.2% 10-year risk (32.9% in its modern subgroup) and recurrence in 52.4%.[20] The same cohort's actuarial curve puts stone risk at approximately 15% at 5 years and 40% at 20 years.[20] Chang et al. reported urinary-tract stones in 8/22 patients (36.4%), comprising bladder stones in 5/22 (22.7%) and kidney stones in 3/22 (13.6%), over mean follow-up of 13.4 years.[17] Continent catheterizable channels and exstrophy anatomy increased stone risk in Shekarriz's series;[8] mucus and bacteriuria are also implicated. Cystoscopy can be technically difficult in a capacious or heavily folded augment and can miss a small calculus; when symptoms or other findings raise concern despite a negative view, axial imaging remains a reasonable diagnostic option.[43] After reconstruction, retrograde ureteral access may remain possible through the native urethra or an orthotopic diversion. If retrograde access fails and shock-wave lithotripsy is unsuitable or ineffective, percutaneous antegrade ureteroscopy is an option even for mid- to distal ureteral stones, depending on anatomy and stone location.[36]
Perforation
Reservoir perforation is a potentially fatal late event. In Szymanski et al.’s spina bifida cohort, estimated 10-year risk was 9.6% with detubularized reconfigured ileocystoplasty versus 23.7% without it, and 8.8% in the modern subgroup.[20] In a transitional-clinic cohort of 385 patients with prior ileal, sigmoid, or ascending-colon augmentation (median follow-up 26 years), spontaneous perforation occurred in 3% (13/385) with one associated death (0.25%); perforation was significantly associated with substance abuse, nonadherence with catheterization, and physical or intellectual disability requiring a surrogate to perform and monitor catheterization.[47]
Chronic bacteriuria and symptomatic UTI
Asymptomatic bacteriuria is common in catheterized augmented systems.[1][19] AUA/SUFU states that clinicians should not perform surveillance urine testing, including culture, in asymptomatic NLUTD patients (Statement 23) and should not treat asymptomatic bacteriuria (Statement 24); both are Moderate Recommendations, Evidence Level: Grade C.[55] Assess new symptoms for UTI or pyelonephritis.
Mucus
Mucus production is inherent to bowel incorporation. It contributes to catheter blockage, irrigation burden, and stone formation.[1][21]
Bowel morbidity and reoperation
In the Szymanski spina bifida cohort, the 10-year risk of bowel obstruction requiring laparotomy was 4.5%, and the 10-year risk of any additional surgery was 43.9%.[20] A systematic review of adult neurogenic augmentation reported bowel dysfunction in 15%.[19][20]
Metabolic and Nutritional Consequences
| Segment | Major issue | Practical consequence |
|---|---|---|
| Ileum / colon | Hyperchloremic metabolic acidosis | The commonest chronic abnormality; monitor BMP lifelong[2][22][23] |
| Ileum | Vitamin B12 deficiency / bile salt malabsorption | Higher risk with longer ileal segments; periodic B12 monitoring is reasonable[2][23] |
| Ileum / colon | Bone demineralization | Chronic acidosis can mobilize bone calcium and contribute to osteoporosis[22][23] |
| Stomach | Hypochloremic metabolic alkalosis | Particularly relevant in patients with renal insufficiency[3][11] |
| Stomach | Hematuria-dysuria syndrome | Especially troublesome in sensate patients with preserved pelvic sensation[3][11] |
| Jejunum | Severe electrolyte derangement | Hyponatremia, hyperkalemia, and acidosis make jejunum an unattractive and generally avoided segment[2][22] |
Malignancy Risk and Surveillance
What is the actual risk?
Malignancy after augmentation is uncommon but real. Across heterogeneous studies in a systematic review, the reported probability of malignancy ranged from 0% to 5.5%, with a mean latency of 19 years and most tumors diagnosed more than 10 years after surgery.[25] The level of evidence was usually poor.[25] Adenocarcinoma was the commonest histologic type (51.6%), and half of the tumors arose at the entero-urinary anastomosis.[25][26]
The controversy is whether augmentation itself is independently oncogenic or whether congenital bladder dysfunction, chronic inflammation, stones, and infection already confer part of the risk.[24][27] The practical answer for follow-up is the same: these patients need lifelong vigilance.
Gastrocystoplasty deserves extra concern
Gastrocystoplasty has a particularly concerning malignancy signal, with multiple series reporting adenocarcinoma arising in augmented reservoirs.[10][28]
Surveillance in practice
Routine surveillance cystoscopy for every asymptomatic augmented patient remains controversial:
- AUA/SUFU NLUTD guideline. Clinicians should not perform screening or surveillance cystoscopy in NLUTD patients .[55] After reconstruction with bowel, they should perform cystoscopy for gross hematuria or symptomatic recurrent UTI .[4] The statement text adds unexplained suprapubic pain to the signs that warrant full evaluation. Its no-screening advice does not apply to patients with prior non-muscle-invasive bladder cancer, who continue cystoscopic surveillance according to oncologic risk.[4]
- Some centers advocate annual cystoscopy after year 10, but decision analyses and retrospective studies have questioned its effectiveness and cost-effectiveness in asymptomatic patients.[29][30][31]
- Gastrocystoplasty warrants specialist discussion because of its malignancy signal.[3][28]
Postoperative Management and Lifelong Follow-Up
Patients with bowel-incorporating bladder reconstructions require structured lifelong surveillance. AUA/SUFU advises the annual assessment below for NLUTD patients after lower urinary tract reconstruction incorporating bowel .[4]
Core follow-up elements
- Annual focused history, examination, and symptom assessment
- Annual basic metabolic panel
- Upper-tract imaging. AUA/SUFU advises annual imaging after bowel-incorporating reconstruction ; EAU 2026 advises ultrasound approximately every six months for high-risk neuro-urological patients, with intervals adjusted to risk and clinical change.[4][33]
- CIC education and adherence review
- Regular bladder irrigation to clear mucus. Among 75 patients with spina bifida who had already formed bladder stones after augmentation and catheterized through an abdominal stoma, daily 240 mL saline irrigation was associated with fewer recurrent bladder stones and symptomatic UTIs over 10 years than 60 or 120 mL irrigation[38]
- Monitor vitamin B12 over time when terminal ileum is incorporated; assess additional nutritional risks according to the segment and length used[4][23]
Functional follow-up
For patients whose impaired storage or voiding parameters place the upper tracts at risk, AUA/SUFU advises repeat urodynamics at an appropriate interval after treatment , and EAU 2026 recommends regular urodynamics in high-risk neuro-urological patients .[4][33] New leakage, symptoms, or upper-tract changes warrant earlier reassessment.[4][33]
Red-flag symptoms
Immediate evaluation is warranted for:
- New gross hematuria
- Recurrent unexplained symptomatic UTI
- Increasing suprapubic pain
- Difficult catheterization or acute retention
- Sudden abdominal pain / sepsis suggesting perforation[4][20]
Alternatives to Augmentation
| Alternative | Role |
|---|---|
| Intradetrusor botulinum toxin | Useful before augmentation, but many severely noncompliant bladders remain refractory; repeat treatment is required[4][32] |
| Ileal conduit | A reasonable alternative for the patient who cannot catheterize reliably, has major comorbidity, or would be poorly served by lifelong augmented-reservoir maintenance[21] |
| Ileovesicostomy | Incontinent low-pressure outlet preserving the native bladder. AUA/SUFU states that clinicians may offer it to select NLUTD patients and must counsel about the high risk of further treatment or surgery [4] |
| Sacral neuromodulation | AUA/SUFU states that clinicians may offer sacral neuromodulation to select NLUTD patients with urgency, frequency or urgency incontinence but should not offer it to patients with spinal cord injury or spina bifida .[4] |
Bottom Line for the Reconstructive Surgeon
Augmentation cystoplasty remains the reference bladder-salvage operation for the unsafe, refractory low-capacity bladder. The decision is whether the patient can manage a lifelong bowel-incorporating reservoir with reliable emptying or is better served by diversion.[1][4][20][21]
In the cited series, AC lowered storage pressure, protected renal function, and improved continence for most patients. Stones, metabolic complications, perforation, and late malignancy remain risks that require lifelong follow-up.
Podcasts
Videos
References
1. Cheng PJ, Myers JB. Augmentation cystoplasty in the patient with neurogenic bladder. World J Urol. 2020;38(12):3035-3046. doi:10.1007/s00345-019-02919-z
2. Roth JD, Cain MP. Neuropathic bladder and augmentation cystoplasty. Urol Clin North Am. 2018;45(4):571-585. doi:10.1016/j.ucl.2018.06.005
3. Biers SM, Venn SN, Greenwell TJ. The past, present and future of augmentation cystoplasty. BJU Int. 2012;109(9):1280-1293. doi:10.1111/j.1464-410X.2011.10650.x
4. Ginsberg DA, Boone TB, Cameron AP, et al. The AUA/SUFU guideline on adult neurogenic lower urinary tract dysfunction: treatment and follow-up. J Urol. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239
5. Stein R, Wiesner C, Beetz R, Schwarz M, Thüroff JW. Urinary diversion in children and adolescents with neurogenic bladder: the Mainz experience. Part I: bladder augmentation and bladder substitution--therapeutic algorisms. Pediatr Nephrol. 2005;20(7):920-925. doi:10.1007/s00467-005-1847-3
6. Ghorai RP, Jain S, Nayak B, et al. Long-term outcomes of augmentation cystoplasty in genitourinary tuberculosis in adults: a 12-year follow-up experience at a tertiary care center. Urology. 2024;189:119-125. doi:10.1016/j.urology.2024.04.031
7. Smith RB, van Cangh P, Skinner DG, Kaufman JJ, Goodwin WE. Augmentation enterocystoplasty: a critical review. J Urol. 1977;118(1 Pt 1):35-39. doi:10.1016/S0022-5347(17)57878-7
8. Shekarriz B, Upadhyay J, Demirbilek S, Barthold JS, González R. Surgical complications of bladder augmentation: comparison between various enterocystoplasties in 133 patients. Urology. 2000;55(1):123-128. doi:10.1016/S0090-4295(99)00443-4
9. Sidi AA, Reinberg Y, Gonzalez R. Influence of intestinal segment and configuration on the outcome of augmentation enterocystoplasty. J Urol. 1986;136(6):1201-1204. doi:10.1016/S0022-5347(17)45282-7
10. Vemulakonda VM, Lendvay TS, Shnorhavorian M, et al. Metastatic adenocarcinoma after augmentation gastrocystoplasty. J Urol. 2008;179(3):1094-1096. doi:10.1016/j.juro.2007.10.089
11. Kurzrock EA, Baskin LS, Kogan BA. Gastrocystoplasty: is there a consensus? World J Urol. 1998;16(4):242-250. doi:10.1007/s003450050061
12. Cartwright PC, Snow BW. Bladder autoaugmentation: early clinical experience. J Urol. 1989;142(2 Pt 2):505-508. doi:10.1016/S0022-5347(17)38798-0
13. Stöhrer M, Kramer G, Goepel M, et al. Bladder autoaugmentation in adult patients with neurogenic voiding dysfunction. Spinal Cord. 1997;35(7):456-462. doi:10.1038/sj.sc.3100441
14. Diamond DA, Chan IHY, Holland AJA, et al. Advances in paediatric urology. Lancet. 2017;390(10099):1061-1071. doi:10.1016/S0140-6736(17)32282-1
15. Gill IS, Rackley RR, Meraney AM, Marcello PW, Sung GT. Laparoscopic enterocystoplasty. Urology. 2000;55(2):178-181. doi:10.1016/S0090-4295(99)00526-9
16. Barashi NS, Rodriguez MV, Packiam VT, Gundeti MS. Bladder reconstruction with bowel: robot-assisted laparoscopic ileocystoplasty with Mitrofanoff appendicovesicostomy in pediatric patients. J Endourol. 2018;32(S1):S119-S126. doi:10.1089/end.2017.0720
17. Chang JW, Kuo FC, Lin TC, et al. Long-term complications and outcomes of augmentation cystoplasty in children with neurogenic bladder. Sci Rep. 2024;14(1):4214. doi:10.1038/s41598-024-54431-z
18. Venn SN, Mundy AR. Long-term results of augmentation cystoplasty. Eur Urol. 1998;34 Suppl 1:40-42. doi:10.1159/000052275
19. Hoen L, Ecclestone H, Blok BFM, et al. Long-term effectiveness and complication rates of bladder augmentation in patients with neurogenic bladder dysfunction: a systematic review. Neurourol Urodyn. 2017;36(7):1685-1702. doi:10.1002/nau.23205
20. Szymanski KM, Misseri R, Whittam B, et al. Additional surgeries after bladder augmentation in patients with spina bifida in the 21st century. J Urol. 2020;203(6):1207-1213. doi:10.1097/JU.0000000000000751
21. Ginsberg DA. The argument for ileal conduit for the poorly compliant bladder in the neurogenic lower urinary tract dysfunction patient refractory to minimally invasive treatment. Neurourol Urodyn. 2026. doi:10.1002/nau.70220
22. Gilbert SM, Hensle TW. Metabolic consequences and long-term complications of enterocystoplasty in children: a review. J Urol. 2005;173(4):1080-1086. doi:10.1097/01.ju.0000155248.57049.4e
23. Roth JD, Koch MO. Metabolic and nutritional consequences of urinary diversion using intestinal segments to reconstruct the urinary tract. Urol Clin North Am. 2018;45(1):19-24. doi:10.1016/j.ucl.2017.09.007
24. Soergel TM, Cain MP, Misseri R, et al. Transitional cell carcinoma of the bladder following augmentation cystoplasty for the neuropathic bladder. J Urol. 2004;172(4 Pt 2):1649-1651. doi:10.1097/01.ju.0000140194.87974.56
25. Biardeau X, Chartier-Kastler E, Rouprêt M, Phé V. Risk of malignancy after augmentation cystoplasty: a systematic review. Neurourol Urodyn. 2016;35(6):675-682. doi:10.1002/nau.22775
26. Garnier S, Vendrell J, Boillot B, et al. Malignancy after augmentation enterocystoplasty: a nationwide study of natural history, prognosis and oncogene panel analysis. J Urol. 2020;204(1):136-143. doi:10.1097/JU.0000000000000752
27. Higuchi TT, Granberg CF, Fox JA, Husmann DA. Augmentation cystoplasty and risk of neoplasia: fact, fiction and controversy. J Urol. 2010;184(6):2492-2496. doi:10.1016/j.juro.2010.08.038
28. Castellan M, Gosalbez R, Perez-Brayfield M, et al. Tumor in bladder reservoir after gastrocystoplasty. J Urol. 2007;178(4 Pt 2):1771-1774. doi:10.1016/j.juro.2007.05.100
29. Hamid R, Greenwell TJ, Nethercliffe JM, et al. Routine surveillance cystoscopy for patients with augmentation and substitution cystoplasty for benign urological conditions: is it necessary? BJU Int. 2009;104(3):392-395. doi:10.1111/j.1464-410X.2009.08401.x
30. Higuchi TT, Fox JA, Husmann DA. Annual endoscopy and urine cytology for the surveillance of bladder tumors after enterocystoplasty for congenital bladder anomalies. J Urol. 2011;186(5):1791-1795. doi:10.1016/j.juro.2011.07.028
31. Kokorowski PJ, Routh JC, Borer JG, et al. Screening for malignancy after augmentation cystoplasty in children with spina bifida: a decision analysis. J Urol. 2011;186(4):1437-1443. doi:10.1016/j.juro.2011.05.065
32. O'Connor RC, Johnson DP, Guralnick ML. Intradetrusor botulinum toxin injections (300 units) for the treatment of poorly compliant bladders in patients with adult neurogenic lower urinary tract dysfunction. Neurourol Urodyn. 2020;39(8):2322-2328. doi:10.1002/nau.24490
33. European Association of Urology. EAU Guidelines on Neuro-urology. 2026. Sections 3.4.3.5–3.4.3.7 and 3.7. Official guideline.
34. Adamic B, Kirkire L, Andolfi C, et al. Robot-assisted laparoscopic augmentation ileocystoplasty and Mitrofanoff appendicovesicostomy in children: step-by-step and modifications to UChicago technique. BJUI Compass. 2020;1(1):32-40. doi:10.1002/bco2.7
35. Babjuk M, Burger M, Capoun O, et al. European Association of Urology Guidelines on Non-muscle-invasive Bladder Cancer (Ta, T1, and Carcinoma in Situ). Eur Urol. 2022;81(1):75-94. doi:10.1016/j.eururo.2021.08.010
36. Okhunov Z, Duty B, Smith AD, Okeke Z. Management of urolithiasis in patients after urinary diversions. BJU Int. 2011;108(3):330-336. doi:10.1111/j.1464-410X.2011.10194.x
37. Casperson KJ, Fronczak CM, Siparsky G, O'Donnell C, Gundeti MS, Campbell JB, Wilcox DT. Ventriculoperitoneal shunt infections after bladder surgery: is mechanical bowel preparation necessary? J Urol. 2011;186(4 Suppl):1571-1575. doi:10.1016/j.juro.2011.03.074
38. Husmann DA. Long-term complications following bladder augmentations in patients with spina bifida: bladder calculi, perforation of the augmented bladder and upper tract deterioration. Transl Androl Urol. 2016;5(1):3-11. doi:10.3978/j.issn.2223-4683.2015.12.06
39. Mickelson JJ, Yerkes EB, Meyer T, Kropp BP, Cheng EY. L stent for stomal stenosis in catheterizable channels. J Urol. 2009;182(4 Suppl):1786-1791. doi:10.1016/j.juro.2009.02.068
40. Pagliara TJ, Gor RA, Liberman D, et al. Outcomes of revision surgery for difficult to catheterize continent channels in a multi-institutional cohort of adults. Can Urol Assoc J. 2018;12(3):E126-E131. doi:10.5489/cuaj.4656
41. Wu YJ, Veale JL, Gritsch HA. Urological complications of renal transplant in patients with prolonged anuria. Transplantation. 2008;86(9):1196-1198. doi:10.1097/TP.0b013e318187bd37
42. Tran C, Rabets J. Renal Transplantation in Patients with Lower Urinary Tract Dysfunction. In: Wood HM, Wood D, eds. Transition and Lifelong Care in Congenital Urology. Springer; 2015:149-162.
43. Brown RD, Monga M. Management of Calculi in Patients with Congenital Neuropathic Bladder. In: Wood HM, Wood D, eds. Transition and Lifelong Care in Congenital Urology. Springer; 2015:163-172.
44. Rackley RR, Ross JH, Abdelmalak J. Augmentation Cystoplasty: Open and Laparoscopic Approaches. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:289-295.
45. López Pereira P, Martinez Urrutia MJ, Lobato Romera R, et al. Should we treat vesicoureteral reflux in patients who simultaneously undergo bladder augmentation for neuropathic bladder? J Urol. 2001;165(6 Pt 2):2259-2261. doi:10.1016/S0022-5347(05)66179-4
46. Thomas JC, Clayton DB. Lower Urinary Tract Reconstruction in Children. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:941-973.
47. Husmann DA. Mortality following augmentation cystoplasty: a transitional urologist's viewpoint. J Pediatr Urol. 2017;13(4):358-364. doi:10.1016/j.jpurol.2017.05.008
48. Clark PE, Holzbeierlein J, Chang SS, et al. 2026 Updates to the Diagnosis and Treatment of Non-muscle Invasive Bladder Cancer: AUA/SUO Guideline. J Urol. Published online September 4, 2026. doi:10.1097/JU.0000000000005280. Corresponding AUA/SUO full guideline, approved August 2026; Statements 5, 26, 28 and 30.
49. Nieder AM, Sved PD, Stein JP, Skinner DG, Soloway MS. Cystoprostatectomy and orthotopic ileal neobladder reconstruction for management of bacille Calmette-Guérin-induced bladder contractures. Urology. 2005;65(5):909-912. doi:10.1016/j.urology.2004.11.053
50. Jain P, Singhania PP, Nikam S, Desai DK. Continent cutaneous urinary diversion with augmentation cystoplasty and bladder neck closure for a single-system ectopic ureter in an adolescent girl: a report of a rare case. Cureus. 2026;18(8):e114796. doi:10.7759/cureus.114796
51. Cameron AP, Chung DE, Dielubanza EJ, et al. "The AUA/SUFU guideline on the diagnosis and treatment of idiopathic overactive bladder." Neurourol Urodyn. 2024;43(8):1742-1752. doi:10.1002/nau.25532
52. Wu X, Berto FG, Welk B. "How do surgical interventions for neurogenic lower urinary tract dysfunction impact quality of life?" Neurourol Urodyn. 2025;44(2):267-275. doi:10.1002/nau.25621
53. Hurst FP, Neff RT, Falta EM, et al. "Incidence, predictors, and associated outcomes of prostatism after kidney transplantation." Clin J Am Soc Nephrol. 2009;4(2):329-336. doi:10.2215/CJN.04370808
54. Gurocak S, De Gier RPE, Feitz W. "Bladder augmentation without integration of intact bowel segments: critical review and future perspectives." J Urol. 2007;177(3):839-844. doi:10.1016/j.juro.2006.10.064
55. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Diagnosis and Evaluation." J Urol. 2021;206(5):1097-1105. doi:10.1097/JU.0000000000002235