Cutaneous Vesicostomy
"Vesicostomy" literally means an opening into the bladder. The term covers two clinically distinct categories:[1][3]
| Category | Stoma type | Continence | Drainage |
|---|---|---|---|
| Incontinent (cutaneous) vesicostomy | Open dome-to-skin stoma; no continence mechanism | None | Free drainage into a diaper or pad |
| Continent (catheterizable) vesicostomy | Catheterizable channel with a continence mechanism | Yes | Clean intermittent catheterization |
For continent vesicostomy options, see:
- Appendicovesicostomy (Mitrofanoff): standard appendiceal channel.
- Yang-Monti Channel: retubularized ileum (with Double Monti, Casale spiral, Tapered).
- Tubularized Bladder Flap: bowel-free continent vesicostomy from native bladder wall (Casale/Rink, Peard, Yachia, Stief-Becker, Klauber-Cendron, Casella-Ost hybrid).
- Hemi-Kock Continent Stoma: ileal-augmentation channel with stapled intussusception nipple valve.
- Indiana Augmentation Cystoplasty (IAC): ileocecal augmentation with plicated-ileocecal-valve continent channel.
- Principles of Continent Catheterizable Channels: design rules common to all of the above.
Blocksom Vesicostomy
The simplest tubeless cystocutaneous fistula, described by Blocksom in 1957: the bladder dome is brought to the suprapubic skin and sutured directly to the skin edges, draining freely into a diaper or absorbent pad.[2][5]
Technique
- Small transverse or vertical suprapubic incision.
- Bladder dome mobilized to the skin surface.
- Bring the bladder dome to the fascia and skin without tension, secure it at both levels, and mature a flush stoma; avoid excessive mobilization or a low abdominal-wall site that permits prolapse.[31]
- No tube or catheter required: gravity drainage into a diaper or pad.[2][5]
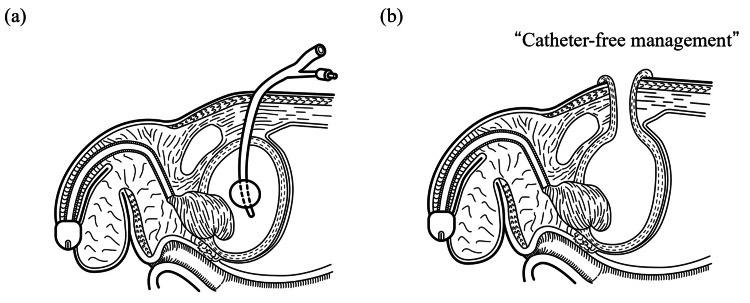
Sagittal schematic of two urinary diversion routes. (a) Conventional catheter-based suprapubic cystostomy. (b) Blocksom-type cutaneous vesicostomy, with the bladder opened directly to the suprapubic skin for catheter-free management. From Tobu S, et al. Cureus. 2026;18(2):e103710, Figure 1 (CC BY 4.0).[32]
Indications
- Pediatric. Blocksom vesicostomy provides temporary urinary drainage in infants and young children with neurogenic bladder (spina bifida), posterior urethral valves, vesicoureteral reflux, or other congenital lower-tract anomalies. It serves as a bridge when reliable catheterization or definitive treatment is not feasible or has failed.[1][6][7] Caregivers can perform CIC in infancy.[1][6][7] For posterior urethral valves, the EAU 2026 paediatric guideline indicates vesicostomy when the child is too small for endoscopic surgery, after failed valve ablation, or when there is no clinical improvement after ablation. It reports upper-tract stabilization or improvement in up to 90% and lists stomal stenosis, mucosal prolapse, peristomal dermatitis and bladder calculi as common complications.[31] Prolapse is attributed to extensive bladder mobilization and stoma placement too low on the abdominal wall.[31] For posterior urethral valves, the EAU guideline recommends considering high diversion when bladder drainage fails to prevent recurrent upper-tract infections, improve renal function or reduce upper-tract dilation .[31]
- Elderly or debilitated adults. Blocksom vesicostomy has been used for chronic urinary retention in patients with severe dementia, neurogenic bladder, or advanced prostate cancer who cannot manage catheters.[2][8]
Outcomes
- Snyder n = 48 (spina bifida, pediatric). No child lost bladder volume while diverted. Of the 16 closures, 12 patients were continent for at least 4 hours on CIC, some with adjuvant drug therapy.[6]
- Tobu n = 16 (elderly, mean age 78.6 yr, mean follow-up 55.7 mo). Catheter-free in 87.5%; complications 37.5% (all within 2 yr); only 2 required reoperation.[2]
- Fischer n = 67 (single institution, average duration 14.3 yr). Thirty-six retained vesicostomy; among these, 14 were satisfied, one unhappy, four deceased, and satisfaction was unknown for 17. Twenty-nine of 36 had spina bifida. Incomplete satisfaction ascertainment limits a broad “high satisfaction” claim.[9]
Complications
- In Di Benedetto's modified Lapides cohort, stomal stenosis occurred in 4/27 children (14.8%).[10]
- Stomal prolapse: uncommon; may need revision.[11]
- In the modified Lapides cohort, UTI occurred in 4/27 children (14.8%).[10]
- Recurrent upper-tract calculi occurred in 33% of patients in one myelomeningocele series.[11]
- In Di Benedetto's modified Lapides cohort, 2/27 children (7.4%) required stomal revision.[10] In Krahn's separate 50-child cutaneous vesicostomy cohort, the stomal revision rate was 20%.[7]
Lapides Vesicostomy
A modification using a U-shaped bladder-wall flap brought to the skin, intended to provide durable drainage. The uncontrolled series has no Blocksom stenosis comparator. The Di Benedetto pediatric series (n = 27) reported a revision rate of only 7.4%.[10]
Differences from Blocksom:
- Uses a flap of bladder wall rather than direct dome-to-skin suturing.
- Different flap configuration; comparative durability is not established.
- Still incontinent: no continence mechanism.
Permanent vs Temporary Vesicostomy
Although traditionally a temporary diversion, selected patients retain a vesicostomy for many years or into adulthood:[9][11]
- Hutcheson (n = 23, myelomeningocele): permanent vesicostomy resolved hydronephrosis in all.[11]
- Jeng (2025; 38 children with spina bifida, median follow-up 6.1 years): vesicostomy was associated with improvement in hydronephrosis, high-grade reflux and febrile UTI. In the 8 patients (21%) whose vesicostomy was reversed, the bladder remained hostile before reversal (detrusor pressure 39 cmH₂O, capacity 29% of age-expected, compliance 2.6 mL/cmH₂O), and all needed a channel, chimney or botulinum toxin afterward.[29]
- Fischer reported 36/67 (53.7%) retaining vesicostomy at last follow-up; satisfaction was known in only 15 of these 36 patients.[9]
For spinal dysraphism, the EAU/ESPU guideline recommends lifelong renal-function follow-up ; for PUV, the EAU guideline recommends lifelong bladder and renal monitoring . These disease-based recommendations continue after vesicostomy closure.[35][31]
Bladder-Neck Closure + Continent Vesicostomy — the "Last Resort"
When the bladder outlet is non-reconstructible (recurrent post-prostatectomy stricture with incontinence, post-vulvectomy, severe neurogenic outlet failure), the bladder neck may be closed with a continent vesicostomy as the sole planned drainage route.[21][22] Before closure, assess bladder storage pressure and compliance with urodynamics in patients with NLUTD whose compliance could worsen after outlet closure; confirm reliable patient or caregiver catheterization and specify an urgent drainage plan if channel access is lost.[33]
Spahn / Riedmiller n = 17
Median follow-up 68 months:[21]
- Indications: recurrent anastomotic stricture and post-prostatectomy incontinence (59%), neurogenic bladder (35%), post-vulvectomy (6%).[21]
- Continent outlet: appendicovesicostomy (n = 8) or ileal-intussusception valve (n = 9).[21]
- Simultaneous ileocecal augmentation in 9 patients with reduced capacity.
- Bladder-neck closure. Primary closure with omental interposition succeeded in 17/17 (100%).[21]
- Primary continence 82%.[21]
- 3 (18%) had continence failure (2 from reduced capacity, 1 iatrogenic); all reconstructed successfully.[21]
- Stomal stenosis 23% (3/8 abdominal, 1/9 umbilical).[21]
- Stoma placed using the "butterfly technique" (8) or at the umbilicus (9).
Reid n = 24 (10 with bladder-neck closure)
Closure successful in 8/10; CIC through abdominal stoma was "cleaner and more aesthetically pleasing"; a dry perineum reduces skin breakdown.[22]
Combined Bladder-Neck Reconstruction + Continent Stoma — bladder exstrophy
Kasprenski reported 24 patients with exstrophy-epispadias complex (median age 8.9 years) and median follow-up of 1.1 years for the full cohort (range 0.1–14.1). Seventeen had more than six months of follow-up and were evaluated for continence:[23]
- 12 of 17 (71%) were completely dry for >3-hour intervals.[23]
- 5 of 17 (29%) did not achieve continence; 3 of these 5 had subsequent bladder-neck transection.[23]
- Offers volitional voiding while maintaining a continent stoma as backup.
Benchekroun Hydraulic Ileal Valve (Historical)
Described by Benchekroun in 1975 (Morocco): a 14 cm ileal segment intussuscepted into itself along its entire length functions as a hydraulic check valve on the inkwell principle: retrograde reservoir pressure collapses the inner tube, preventing efflux while permitting catheter passage.[14][18]
Outcomes
- Benchekroun original series (n = 136). The valve was used mainly with ileocecal reservoirs (122/136); only four patients had a bladder reservoir. At a mean 38-month follow-up, 103/136 were continent immediately and 127/136 after valve repair; 88.3% catheterized easily.[14]
- Quinlan (Johns Hopkins) n = 9, follow-up up to 20 months. All were continent diurnally and nocturnally; five had problems (one valve fistula, one false passage, three stomal stenoses).[15] A later review by Leonard and Quinlan reported revision in 5 of 15 patients (33%) versus 58% with plicated ileal efferent limbs, and called the valve their "continence mechanism of choice" at the time.[19]
- Sanda / Gearhart n = 11 at 5 yr. The early report recorded complications requiring surgical revision in 13% at 18 months; among 11 patients followed for an average of five years, 91% had such complications. Late stomal stenosis occurred in 73%, calculi in 36% and devagination in 36%; 64% required major revision. Authors concluded that "novel forms of urinary diversion require extended follow-up for accurate assessment."[20]
- Hanna pediatric experience. 4/5 children developed stomal stenosis, 1 had valve perforation; only 1 of 5 still doing well at 6 years; described as "disappointing"; recommended Monti or Nissen-valve alternatives.[13]
- Guzman modification. Suture rather than staple stabilization of the inner tube; eliminated staples, reducing stone and fistula risk; all 7 continent at 6 mo–2 yr.[18]
Current status. Largely abandoned because of high long-term stenosis and devagination rates.[13][20]
Continence Mechanisms — At-a-Glance
| Mechanism | Principle | Channels using it |
|---|---|---|
| Flap valve (submucosal tunnel) | Channel runs along reservoir wall; rising pressure compresses channel against backing wall | Mitrofanoff (APV), Yang-Monti, TBF Casale/Rink |
| Intussusception nipple valve | Channel telescoped into reservoir; pressure collapses nipple lumen | Hemi-Kock, Kock pouch, TBF Peard |
| Hydraulic collapse (inkwell) | Intussuscepted ileal segment collapses under retrograde reservoir pressure | Benchekroun valve (largely abandoned) |
| Rectus-muscle compression | Channel passes through crossed rectus strands; lateral pressure adds to closure | TBF Yachia |
| Nissen fundoplication | Reservoir wall wrapped around channel base | Richter / Hanna Nissen valve |
| Plicated ileocecal valve + tapered ileum | Native valve reinforced; ileal peristalsis assists | Indiana pouch, IAC |
| Lich-Gregoir extravesical detrusor tunnel | Channel embedded in detrusor trough; muscle compression provides continence | TBF Stief-Becker, extravesical implantation[24] |
The Riley extravesical implantation experience (VanderBrink n = 84 of 394) reported 94% stomal continence with a 26% revision rate at mean 45 months (mostly skin-level or endoscopic), with the advantage of avoiding a large cystotomy.[24]
Stomal Stenosis — the Universal Challenge
Across all continent vesicostomy techniques, stomal stenosis is the dominant complication.
- Stomal stenosis occurred in 9 continent bladder channels (13%) in Thomas’s mixed-technique series and required revision in 14/31 (45%) with Cain’s Rink modification; in De Ganck’s mixed urinary-channel/ACE series, it accounted for more than half of 27 stoma-related complications.[3][16][25]
- One short-follow-up cohort saw many early problems, but complications continue throughout channel life. Thomas’s continent bladder-channel cohort documented stomal stenosis within 1–24 months after surgery (mean 9.4 months).[16] Harris’s 260-patient exstrophy cohort reported a median 1.9 years to stenosis.[26]
- Risk factors depend on cohort and technique. The 86% umbilical figure was 6/7 patients in a 31-patient TBF series.[3] In Harris’s 260 classic-exstrophy cohort, multifilament suture was associated with stenosis; sex, stoma-site, and channel comparisons were observational.[3][26][25]
- Etiology among the 65 patients with stenosis in Harris’s 260-patient exstrophy cohort: scar contracture 41/65 (63%), keloid 17/65 (26%), hypertrophic scar 7/65 (11%).[26]
- Management: assess the level and cause of narrowing. Skin-level stents, dilation, local incision or rearrangement, or deeper revision may be appropriate. In Harris’s exstrophy cohort, stomal incision for scar contractures had 100% reported success, while excision with local tissue rearrangement for hypertrophic scars or keloids had 66.7% reported success.[26] Seven L-stent users reported improvement, with concurrent topical therapy in most.[27] An acutely uncatheterizable reservoir requires prompt urologic care.[26][27][4][16]
De Ganck's summary stands: "a high easy-to-treat complication rate is the price for a continent stoma." In De Ganck's retrospective mixed urinary-channel/ACE cohort, 19/53 patients (36%) had stoma-related complications during a mean 2.8-year follow-up; the authors described most complications as relatively easy to treat and patient satisfaction as high.[25]
Other Channel Complications
- Stomal incontinence 2% (Cain, 100 patients) to 9% (Welk, 6 of 67).[12][28]
- False passage occurred in 4 urinary catheterizable channels (6%) in Thomas’s series, with most managed by catheter drainage.[16] Polm reported false channels requiring surgical revision in 10/117 urinary channels (9%).[17]
- Channel stricture 6%: operative or endoscopic resection.[28]
- Stomal prolapse 5%: usually late; operative revision.[28]
- Channel leakage occurred in 6/67 patients in Welk; injection was attempted in four and succeeded in two. Welk’s 50% injection result (2/4 attempts) is too small for a dependable cure estimate.[28]
- Bladder stones and bladder perforation are reported mainly when channels accompany augmentation or a pouch. EAU 2026, citing a systematic review in neurologic patients, gives tube stenosis 4–32%, bladder stones 20–25% and bladder perforation up to 40% in one case series.[30]
Welk observed early and later channel complications among 67 patients (median follow-up 28 months).[28] In a separate retrospective cohort of 173 channels under adult surveillance, 92 (53%) required surgical revision; median follow-up was 12.4 years.[34]
Decision Algorithm — Which Vesicostomy
Temporary urinary drainage (infants / children)
- Blocksom. This simple, tubeless, reversible diversion provides temporary drainage in selected children when reliable catheterization or definitive treatment is infeasible or has failed. For PUV, EAU guidance describes vesicostomy when endoscopic ablation is infeasible, fails, or gives no clinical improvement.[6][1][7][31]
- Lapides. Bladder-wall flap stoma. Comparative stenosis and revision rates against Blocksom are not established.[10]
Permanent incontinent drainage (elderly / debilitated)
- Blocksom. Useful in elderly patients with chronic retention and severe dementia who cannot manage catheters.[2][8]
Continent catheterizable stoma
- When the appendix is suitable: Appendicovesicostomy was the cited pediatric center's first option.[12]
- Appendix unavailable and adequate bladder capacity: Tubularized Bladder Flap.[17][3]
- Appendix unavailable and capacity marginal or augmentation needed: Yang-Monti (channel + augmentation patch from one pedicle).[3]
- Augmentation with a continent stoma: in Spahn's bladder-neck-closure series, nine patients received ileocecal augmentation with an embedded appendix (n = 4) or ileal intussusception valve (n = 5).[21] See IAC and Hemi-Kock for separate named techniques.
- Devastated bladder outlet: bladder-neck closure with continent vesicostomy (APV, ileal intussusception valve, or TBF); see above.[21][22]
Special Populations
- Bladder exstrophy. Continent stoma creation is common after failed bladder-neck reconstruction. Largest exstrophy-specific series (Harris n = 260): stomal stenosis 25% at median 1.9 yr; monofilament umbilicoplasty suture was associated with less stenosis (p = 0.009).[26]
- Myelomeningocele. Incontinent vesicostomy provides safe infant decompression. Timing of closure, CIC, or continent reconstruction is individualized, and 6–10 years describes one historical cohort's age at closure. Some patients with severe disability retain a permanent incontinent vesicostomy; in Fischer's cohort, 14 of the 15 retained-vesicostomy patients with known satisfaction were satisfied.[6][11][9]
- Devastated bladder outlet. Spahn described bladder-neck closure with continent vesicostomy as a "last resort"; the mixed-age series (ages 7–74 years) reported primary continence in 14/17 (82%) at median 68-month follow-up.[21]
See Also
- Ileovesicostomy: incontinent low-pressure ileal outlet (different operation: ileal-segment diversion with the bladder still in place).
- Appendicovesicostomy (Mitrofanoff)
- Yang-Monti Channel
- Tubularized Bladder Flap
- Hemi-Kock Continent Stoma
- Indiana Augmentation Cystoplasty
- Principles of Continent Catheterizable Channels
References
1. Bruce RR, Gonzales ET. Cutaneous vesicostomy: a useful form of temporary diversion in children. J Urol. 1980;123(6):927–928. doi:10.1016/s0022-5347(17)56196-0
2. Tobu S, Noguchi M. Long-term outcomes of Blocksom vesicostomy for elderly patients with chronic urinary retention. Int J Urol. 2022;29(11):1357–1361. doi:10.1111/iju.14999
3. Cain MP, Rink RC, Yerkes EB, Kaefer M, Casale AJ. Long-term followup and outcome of continent catheterizable vesicostomy using the Rink modification. J Urol. 2002;168(6):2583–2585. doi:10.1016/S0022-5347(05)64221-8
4. Peard L, Fox PJ, Andrews WM, et al. Continent catheterizable vesicostomy: an alternative surgical modality for pediatric patients with large bladder capacity. Urology. 2016;93:217–222. doi:10.1016/j.urology.2016.03.018
5. McGrath M, Alnaqi AA, Braga LH. Vesicostomy and colostomy in a premature neonate with posterior urethral valves, bilateral dysplastic kidneys, and high imperforate anus: the challenge of stoma placement. Urology. 2016;93:191–193. doi:10.1016/j.urology.2016.02.031
6. Snyder HM, Kalichman MA, Charney E, Duckett JW. Vesicostomy for neurogenic bladder with spina bifida: followup. J Urol. 1983;130(4):724–726. doi:10.1016/s0022-5347(17)51424-x
7. Krahn CG, Johnson HW. Cutaneous vesicostomy in the young child: indications and results. Urology. 1993;41(6):558–563. doi:10.1016/0090-4295(93)90104-i
8. Tobu S, Noguchi M, Kurata S, et al. Usefulness of Blocksom vesicostomy in elderly men with chronic urinary retention and severe dementia. Geriatr Gerontol Int. 2015;15(8):997–1000. doi:10.1111/ggi.12381
9. Fischer KM, Bowen DK, Kovell RC, Canning DA, Weiss DA. Follow-up and outcomes of patients with long-term cutaneous vesicostomies at a single institution. Urology. 2020;144:255–260. doi:10.1016/j.urology.2020.04.130
10. Di Benedetto V, Bankole Sanni R, Miano L, Monfort G. Vesicostomy in childhood: indications and results. Pediatr Surg Int. 1996;11(5–6):348–350. doi:10.1007/BF00497809
11. Hutcheson JC, Cooper CS, Canning DA, Zderic SA, Snyder HM. The use of vesicostomy as permanent urinary diversion in the child with myelomeningocele. J Urol. 2001;166(6):2351–2353. doi:10.1016/s0022-5347(05)65587-5
12. Cain MP, Casale AJ, King SJ, Rink RC. Appendicovesicostomy and newer alternatives for the Mitrofanoff procedure: results in the last 100 patients at Riley Children's Hospital. J Urol. 1999;162(5):1749–1752. doi:10.1016/s0022-5347(05)68230-4
13. Richter F, Stock JA, Hanna MK. Continent vesicostomy in the absence of the appendix: three methods in 16 children. Urology. 2002;60(2):329–334. doi:10.1016/s0090-4295(02)01735-1
14. Benchekroun A, Essakalli N, Faik M, et al. Continent urostomy with hydraulic ileal valve in 136 patients: 13 years of experience. J Urol. 1989;142(1):46–51. doi:10.1016/s0022-5347(17)38658-5
15. Quinlan DM, Leonard MP, Brendler CB, Gearhart JP, Jeffs RD. Use of the Benchekroun hydraulic valve as a catheterizable continence mechanism. J Urol. 1991;145(6):1151–1155. doi:10.1016/s0022-5347(17)38560-9
16. Thomas JC, Dietrich MS, Trusler L, et al. Continent catheterizable channels and the timing of their complications. J Urol. 2006;176(4 Pt 2):1816–1820; discussion 1820. doi:10.1016/S0022-5347(06)00610-0
17. Polm PD, de Kort LMO, de Jong TPVM, Dik P. Techniques used to create continent catheterizable channels: a comparison of long-term results in children. Urology. 2017;110:192–195. doi:10.1016/j.urology.2017.08.030
18. Guzman JM, Montes de Oca L, Gonzalez R, Ercole CJ. Modified Benchekroun technique for continent ileal stoma. J Urol. 1989;142(6):1431–1433. doi:10.1016/s0022-5347(17)39118-8
19. Leonard MP, Quinlan DM. The Benchekroun ileal valve. Urol Clin North Am. 1991;18(4):717–724. doi:10.1016/s0094-0143(21)00372-4
20. Sanda MG, Jeffs RD, Gearhart JP. Evolution of outcomes with the ileal hydraulic valve continent diversion: reevaluation of the Benchekroun catheterizable stoma. World J Urol. 1996;14(2):108–111. doi:10.1007/BF00182567
21. Spahn M, Kocot A, Loeser A, Kneitz B, Riedmiller H. Last resort in devastated bladder outlet: bladder neck closure and continent vesicostomy — long-term results and comparison of different techniques. Urology. 2010;75(5):1185–1192. doi:10.1016/j.urology.2009.11.070
22. Reid R, Schneider K, Fruchtman B. Closure of the bladder neck in patients undergoing continent vesicostomy for urinary incontinence. J Urol. 1978;120(1):40–42. doi:10.1016/s0022-5347(17)57033-0
23. Kasprenski M, Benz K, Jayman J, et al. Combined bladder neck reconstruction and continent stoma creation as a suitable alternative for continence in bladder exstrophy: a preliminary report. Urology. 2018;119:133–136. doi:10.1016/j.urology.2018.05.009
24. VanderBrink BA, Kaefer M, Cain MP, et al. Extravesical implantation of a continent catheterizable channel. J Urol. 2011;185(6 Suppl):2572–2575. doi:10.1016/j.juro.2011.01.027
25. De Ganck J, Everaert K, Van Laecke E, Oosterlinck W, Hoebeke P. A high easy-to-treat complication rate is the price for a continent stoma. BJU Int. 2002;90(3):240–243. doi:10.1046/j.1464-410x.2002.02805.x
26. Harris TGW, Haffar A, Crigger CB, et al. Stomal stenosis after continent urinary diversion in bladder exstrophy: risk factors and management. Urology. 2024;191:110–118. doi:10.1016/j.urology.2024.07.003
27. Mickelson JJ, Yerkes EB, Meyer T, Kropp BP, Cheng EY. L stent for stomal stenosis in catheterizable channels. J Urol. 2009;182(4 Suppl):1786–1791. doi:10.1016/j.juro.2009.02.068
28. Welk BK, Afshar K, Rapoport D, MacNeily AE. Complications of the catheterizable channel following continent urinary diversion: their nature and timing. J Urol. 2008;180(4 Suppl):1856–1860. doi:10.1016/j.juro.2008.03.093
29. Jeng G, Misseri R, King SJ, et al. "Cutaneous Vesicostomy: Effects on Future Bladder Outcomes in Patients With Spina Bifida." Journal of Pediatric Urology. 2025;21(6):1700-1706. doi:10.1016/j.jpurol.2025.07.023
30. European Association of Urology. EAU Guidelines on Neuro-urology. 2026. Section 3.4.3.e, urinary diversion. Official guideline.
31. European Association of Urology. EAU Guidelines on Paediatric Urology: Congenital Lower Urinary Tract Obstruction, Posterior Urethral Valves (section 21.4). 2026 limited update, March 2026. Guideline.
32. Tobu S, Yamaguchi Y, Yukimoto M, et al. Blocksom-type cutaneous vesicostomy in adult patients with severe motor and intellectual disabilities: a retrospective case series. Cureus. 2026;18(2):e103710. doi:10.7759/cureus.103710
33. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU guideline on adult neurogenic lower urinary tract dysfunction: Treatment and follow-up." J Urol. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239
34. Polm PD, Christiaans CHH, Dik P, Wyndaele MIA, de Kort LMO. "Continent catheterizable urinary channels: Lessons for lifelong urological care from a comparative analysis of very long-term complications and revision-free survival of three different types." Neurourol Urodyn. 2024;43(5):1083-1089. doi:10.1002/nau.25350
35. Abrahamson K, Bogaert G, Dellenmark-Blom M, et al. "Guidelines on spinal dysraphism in children and adolescents." Clinical guideline. EAU Guidelines Office; January 2025. Official guideline