Sigmoid Cystoplasty (Sigmoidocystoplasty)
Sigmoid cystoplasty is a form of augmentation cystoplasty that uses a detubularized segment of sigmoid colon to enlarge the bladder; it retains the native bladder, which distinguishes it from the sigmoid colon neobladder, a total orthotopic replacement performed after cystectomy. It can improve capacity and compliance, with practical advantages including pelvic proximity and a thick wall for selected ureteral implantation. A retrospective comparison reported a trend toward less small-bowel obstruction (SBO) with sigmoid than ileal augmentation.[1][2] The authors of that comparison favored sigmoid. Segment selection remains individualized.[1]
Indications
Sigmoid augmentation shares the general indication of refractory poor bladder compliance or neurogenic detrusor overactivity.[22][23] For idiopathic OAB, the 2024 AUA/SUFU guideline permits augmentation only in severely impacted patients who have not responded to all other therapeutic options .[27] Underlying conditions include neurogenic bladder, exstrophy and posterior urethral valves.[1][3][4] For IC/BPS, the 2022 AUA guideline states that major surgery may be undertaken only in carefully selected patients with bladder-centric symptoms or, rarely, an end-stage small fibrotic bladder after all other therapies have failed (Statement 22, Option; Grade C); pain may persist after surgery.[28] For adults with NLUTD, the 2021 AUA/SUFU guideline states that clinicians may offer augmentation cystoplasty to select patients refractory to or intolerant of less invasive therapy .[22] For children with non-progressive neurogenic dysfunction and impaired storage, the 2023 CUA/PUC guideline recommends considering intestinal augmentation after clinical and urodynamic assessment and discussion of alternatives and complications ; it does not prefer sigmoid.[26] For children and adolescents with spinal dysraphism, the 2025 EAU/ESPU/ERN guideline strongly recommends ileal or colonic augmentation for therapy-resistant detrusor overactivity, small capacity and poor compliance that may threaten the upper urinary tract or continence.[31] The EAU Neuro-Urology guideline (limited update, March 2026) recommends offering bladder augmentation for low bladder compliance or refractory neurogenic detrusor overactivity .[23]
For adult NLUTD candidates, clinicians assess whether the patient or a caregiver has the hand and cognitive function needed to perform regular clean intermittent catheterization before augmentation.[22]
Sigmoid is favored when:
- Ureteral reimplantation is needed, because the thick sigmoid wall accommodates a submucosal tunnel.[3][5]
- Bowel anatomy or prior surgery favors colon. Improvement in constipation was reported in one selected series.[4]
- Preserving small bowel is desirable, although colonic surgery still carries bowel obstruction and anastomotic risks.[1]
- A Mitrofanoff channel is planned, and the sigmoid "tail" modification can stabilize the catheterizable stoma.[5]
Surgical Technique (Goodwin cup-patch)
- Segment isolation. Approximately 15–25 cm of sigmoid is isolated on a perfused mesenteric pedicle. In Sato’s pregnancy-oriented technique, a 15–20 cm sigmoid segment is isolated on a sigmoid arterial pedicle, and selected vessels, including the marginal artery at the oral end, are divided for reach. When extra length is needed, all but one sigmoid artery and the left colic artery may be divided. The segment and pedicle pass retroperitoneally along the left ureter to the posterior bladder, away from the uterus.[24] In the authors’ retrospective pregnancy series, three women underwent this technique across four pregnancies; its proposed cesarean benefit remains preliminary.[24]
- Bowel continuity restoration. End-to-end or side-to-side colocolonic anastomosis.
- Detubularization. Opened along the antimesenteric border. In a small 1986 comparison, volume-dependent contractions were present in 15/16 patients with tubular sigmoid versus 1/8 with sigmoid cup-patch at mean 19.4-month follow-up.[6][6][2]
- Reconfiguration. Folded into a U-shaped or cup-patch configuration (Laplace's law).
- Cystotomy. The native bladder is bivalved.
- Anastomosis. The sigmoid patch is sutured to the widely opened native bladder with watertight apposition.[6][24]
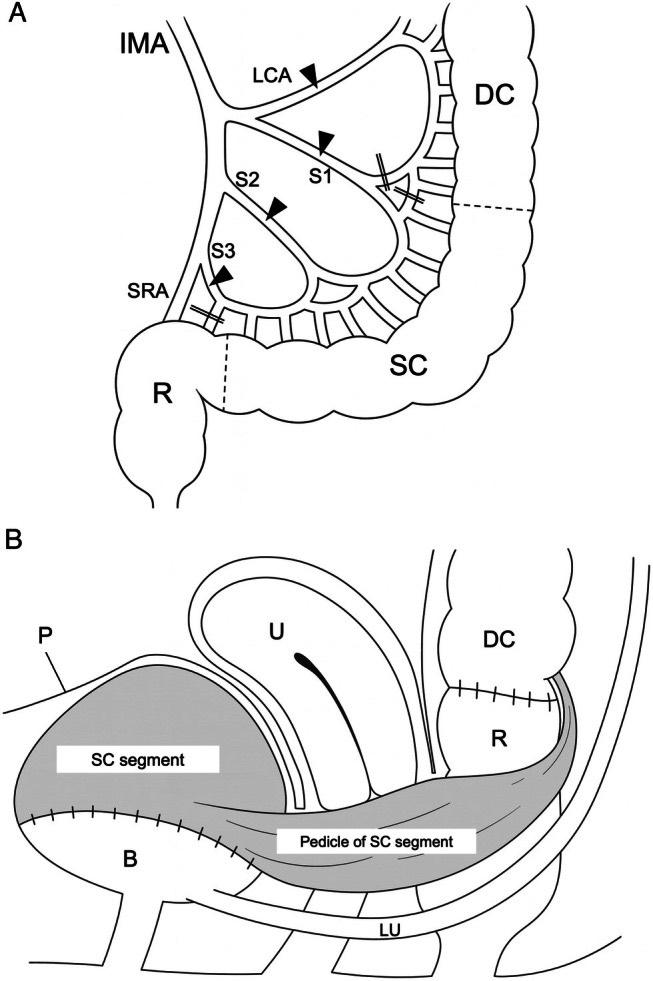
Sigmoid cystoplasty with retroperitoneal mesentery placement. (A) The sigmoid segment is mobilized on the distal sigmoid artery as its main blood supply; the double line marks the marginal artery divided to gain mobility, and the arrowheads mark sigmoid arteries and the left colic artery that may also be divided if more mesenteric length is needed for a tension-free reach to the bladder. (B) Sagittal view from the left of the completed cystoplasty, with the vascular pedicle placed retroperitoneally along the left ureter in anticipation of a future cesarean section. B, bladder; DC, descending colon; IMA, inferior mesenteric artery; LCA, left colic artery; LU, left ureter; P, peritoneum; R, rectum; S, sigmoid artery; SC, sigmoid colon; SRA, superior rectal artery; U, uterus. From Sato A, et al. Int J Urol. 2026;33(3):e70345, Figure 1 (CC BY-NC 4.0).[24]
Sigmoid "tail" modification. A 3–5 cm segment of nondetubularized colon is left intact and fixed to the posterior aspect of the anterior abdominal wall to stabilize a catheterizable stoma constructed from appendix or tapered ileum. It was described in seven children; one developed postoperative bowel obstruction and an abscess.[5]
Concomitant ureteral reimplantation, outlet surgery, or a catheterizable channel may be appropriate for specific anatomy and function.[1][3][5][7][8]
Outcomes
| Study / population | Reported outcome | Interpretation |
|---|---|---|
| Zhang 2012, 47 patients, mean 24 months | Mean capacity 160.6 → 468.5 mL; maximal detrusor pressure 31.1 → 10.9 cm H₂O | Retrospective; selected concomitant reimplantation[3] |
| Zhang 2014, 52 patients, mean 49 months | Safe capacity 113.8 → 373.1 mL; compliance 2.96 → 14.07 mL/cm H₂O | Retrospective[4] |
| Hayashi 2006, 86 patients, mean 13.1 years | Normal creatinine clearance in 80/86; continence score improved in 61/86 | Eight patients had increased renal scarring[7] |
In an 86-patient long-term series (Hayashi 2006, n=86, mean follow-up 13.1 yr), CrCl was normal in 93% and continence improved in 71%; bladder stones occurred in 21% but were absent at final review.[7] A later Hayashi follow-up reported stones in 12/40 analyzed patients (30%) at mean 24.3 years; 55/95 eligible records lacked complete follow-up.[34] Zhang 2014 (n=52, mean 49 months) reported increased safe capacity and compliance and a decrease in mean serum creatinine from 88.1 to 77.1 μmol/L; 16/47 patients with preoperative hydronephrosis still had grade I–II hydronephrosis.[4] All 52 reported improved constipation and satisfaction, and no overt acidosis or perforation was observed.[4]
Sigmoid vs. Ileum
| Feature | Sigmoid | Ileum |
|---|---|---|
| Bowel obstruction | Less small-bowel handling; lower-SBO trend in one retrospective comparison | Bowel handling and adhesions remain relevant |
| Anatomic proximity to bladder | Closer | Requires mobilization |
| Ureteral reimplantation | Thick wall; accommodates a submucosal tunnel | Thinner wall |
| Ileocecal valve | Preserved | Preserved |
| Bowel function | Improvement in constipation reported in one selected cohort | Bowel effects vary with segment, length, and baseline disease |
| Pathologic contractions in one retrospective study of colonic augmentation (segment not specified)[9] | 43% after colocystoplasty overall (35 patients) | 26% after ileocystoplasty (31 patients) |
| Mucus production | Clinically relevant mucus burden | Clinically relevant mucus burden; no dependable rank from these sources |
In one 84-patient retrospective long-term urodynamic study, postoperative pathologic contractions were reported in 43% of 35 colocystoplasty patients and 26% of 31 ileocystoplasty patients. Capacity and compliance improved in all three groups.[9]
Complications
- Persistent reservoir contractions. Also occur with ileum and stomach. The 12.5% (1/8, cup-patch), 43% and 26% figures above describe separate cohorts and configurations.[6][9] Zhang’s 52-patient sigmoid series required anticholinergics in 6/52 (11.5%).[2][4][6][9]
- Urinary tract stones. Approximately 21% (18/86) in the largest long-term series; risk factors include continent stomas and exstrophy.[1][7]
- Recurrent febrile UTIs. Approximately 21% (11/52).[4]
- Bowel dysfunction. Approximately 10.6% in Zhang 2012; in Zhang 2014 all 52 patients reported improved constipation.[3][4]
- Adhesive intestinal obstruction. Approximately 8.5% in Zhang 2012; the SBO rate trended lower than with ileocystoplasty in Shekarriz's comparison.[1][3]
- Bladder perforation. Shekarriz’s retrospective 133-patient series found no difference in perforation between sigmoid and ileal augmentation and observed the highest rate in neurogenic bladder.[1] In a separate retrospective series of 500 pediatric augmentation procedures with at least two years of follow-up, perforation occurred in 43 patients (8.6%); sigmoid use and bladder-neck surgery were associated with increased risk; approximately one-third of perforations occurred more than six years after augmentation.[29]
- Vesicoureteral reflux. Hayashi reported low-grade recurrence in 6/58 renal units reimplanted during augmentation (in five patients), and grade I reflux in two of 44 patients without reimplantation.[7] The comparison was not randomized.[7]
- Deteriorating renal function. 6.4% in Zhang 2012 (sigmoid) and 5.2% in Wang 2018 (augmentation cystoplasty, not restricted to sigmoid).[3][8]
Metabolic Disturbances
- In a six-dog model of total bladder replacement, all three colonic and all three ileal reservoirs were associated with severe acidosis at one year.[10]
- Pediatric series: significant hyperchloremic acidosis in 10%, borderline acidosis in 27% after sigmoidocystoplasty.[11]
- Calcium and phosphorus abnormalities in 16.5% and 43%, respectively, more frequent in acidotic patients, likely reflecting bony buffer activation; may delay growth in children.[11]
- Renal insufficiency increased the need for acidosis treatment in a mixed-segment series, but 3/30 children with sigmoidocystoplasty and normal renal function developed significant hyperchloremic acidosis during 1–10 years of follow-up.[2][11] Monitor bicarbonate regardless of baseline renal function.[2][11]
- Zhang 2014 reported no obvious metabolic acidosis at mean 49 mo.[4]
Treat documented acidosis with individualized alkali therapy and dependable emptying. Potassium-containing alkali requires caution in renal impairment or hyperkalemia. If potassium citrate extended-release tablets are used, their label contraindicates use in hyperkalemia or GFR <0.7 mL/kg/min; impaired potassium excretion can rapidly cause potentially fatal hyperkalemia.[32]
Histopathology and Malignancy Risk
Long-term histopathology of sigmoidocystoplasty:[7][12]
- Inflammation in all cases at >10-yr follow-up.
- In Hayashi’s 86-patient cohort, hyperplasia occurred in 9/86 (approximately 10%) and metaplasia in 4/86 (approximately 5%).[7]
- No malignancy was reported in these follow-up cohorts; their size, duration, biopsy selection, and possible cohort overlap prevent a conclusion of zero lifetime risk.
- In Miyano et al.’s 100-case sigmoidocolocystoplasty cohort (mean age at surgery, 10.6 years), PCNA staining was significantly more intense in patients who stopped regular bladder irrigation and in those who developed bladder stones than in the respective comparison groups.[12]
Overall malignancy risk after augmentation:[13][14][15]
- In Garnier’s 16-patient malignancy series, urothelial carcinomas were typically found after colocystoplasty and adenocarcinomas mainly after gastrocystoplasty; a separate systematic review found adenocarcinoma was the most common histology overall (51.6%).[13][15]
- A retrospective German survey reported tumors in 1.58% of cystoplasties versus 0.05% of ileal neobladders and 0.02% of ileal conduits.[14]
- A systematic review reported mean latency of 19 years.[15] In a separate 16-patient malignancy series, median latency was 20 years, tumors were often advanced at diagnosis, and one-year survival was 56%.[13]
- A 2011 multicenter analysis recommended regular endoscopy from at least the fifth postoperative year for cystoplasties; current AUA/SUFU guidance favors symptom-triggered evaluation in stable NLUTD.[14][22] Gross hematuria, recurrent unexplained symptomatic UTI, or suprapubic pain warrant investigation without waiting for an anniversary.[22][14][16]
Seromuscular Colocystoplasty Lined With Urothelium (SCLU)
SCLU is a variant designed to avoid incorporating intestinal mucosa into the urinary tract. See Seromuscular Colocystoplasty (SCLU) for the full technique and evidence.[17][18]
- A de-epithelialized (mucosa-stripped) sigmoid seromuscular patch is prepared, preserving the submucosa (to prevent patch contraction and fibrosis).[18]
- Native bladder urothelium is exposed by detrusorectomy at the dome.
- The seromuscular patch is placed over the exposed urothelium, which then lines the augmented segment.
SCLU outcomes[19][20][21]
- Jednak’s retrospective series reported a 1.8-fold rise in total capacity and a 2.4-fold rise in safe capacity among 28/32 patients with urodynamics at mean 1.5 years.[20] Jung’s retrospective series reported a 2.96-fold rise in mean bladder capacity among 33 patients at mean 6.0 years.[19]
- These small series reported no perforations, bowel obstruction, or metabolic abnormalities during their follow-up; those risks remain possible.
- Mucus production was not clinically significant at short-term follow-up in Jednak's series.
- Continence achieved in 71–81% after initial or secondary procedures.[20]
- Hourglass deformity occurred in 7/32 (22%) in an early series.[20] Augmentation failed in 4/32 (12.5%) at mean cohort follow-up of 1.6 years in that series.[20] In a later retrospective SCLU cohort using ileal or colonic patches, 8/37 (22%) underwent reaugmentation at mean 61-month follow-up.[25]
- Biopsy shows colonic mucosal regrowth in some patients (5/7 interpretable biopsies in one series).[20]
- A 20-patient SCLU study advised against a simultaneous catheterizable channel after 3/5 required reaugmentation; conventional augmentation and pure autoaugmentation were outside its scope.[21]
- Selected SCLU series combined it with an AUS. Storage safety and an effective emptying route remain necessary.
Long-Term Follow-Up
The AUA/SUFU NLUTD guideline states that after lower urinary tract reconstruction incorporating bowel the clinician should assess the patient annually with:[22]
- Focused history, physical examination and symptom assessment.
- Basic metabolic panel (electrolytes, bicarbonate, renal function).
- Urinary tract imaging, commonly renal ultrasound for hydronephrosis and stones.
The guideline states that clinicians should perform cystoscopy when gross hematuria or symptomatic recurrent UTI develops after such reconstruction .[22] It also states that clinicians should not perform screening or surveillance cystoscopy in NLUTD patients .[35] For women augmented for non-neurogenic OAB/UUI, the 2026 edition of the EAU female LUTS guideline recommends offering cystoscopic surveillance at 10 years or more after augmentation .[30]
Measures described in the literature but not required by the guideline:
- Regular bladder irrigation was advised after sigmoidocolocystoplasty by Miyano et al.; their study linked stopping irrigation to increased mucosal proliferation-marker staining.[12] The 2026 EAU Urolithiasis guideline weakly recommends regular saline irrigation for augmented bladders without a history of autonomic dysreflexia to reduce stone recurrence.[33]
- Monitoring for calcium and phosphorus abnormalities and bone health, particularly in children.[11]
Sigmoid vs. Ileum — When to Choose Sigmoid
Sigmoid cystoplasty is well suited when:[1][4][5][6]
- Ureteral reimplantation is needed, because the thick wall accommodates a submucosal tunnel.
- Bowel assessment and available anatomy favor using colon.
- Preserving small bowel is important, while accepting colonic surgical risks.
- The ileocecal valve and terminal ileum should be preserved (B₁₂ or bile-salt malabsorption risk).
- SCLU is planned (sigmoid is the standard segment for this technique).
Detubularization and cup-patch reconfiguration are used to limit sigmoid reservoir contractions; Sidi’s small comparative cohort reported fewer volume-dependent contractions with the cup-patch than tubular sigmoid.[6][9]
References
1. Shekarriz B, Upadhyay J, Demirbilek S, Barthold JS, González R. "Surgical Complications of Bladder Augmentation: Comparison Between Various Enterocystoplasties in 133 Patients." Urology. 2000;55(1):123-8. doi:10.1016/s0090-4295(99)00443-4
2. Mitchell ME, Piser JA. "Intestinocystoplasty and Total Bladder Replacement in Children and Young Adults: Followup in 129 Cases." The Journal of Urology. 1987;138(3):579-84. doi:10.1016/s0022-5347(17)43264-2
3. Zhang F, Liao L. "Sigmoidocolocystoplasty With Ureteral Reimplantation for Treatment of Neurogenic Bladder." Urology. 2012;80(2):440-5. doi:10.1016/j.urology.2012.05.010
4. Zhang P, Yang Y, Wu ZJ, et al. "Long-Term Follow-Up of Sigmoid Bladder Augmentation for Low-Compliance Neurogenic Bladder." Urology. 2014;84(3):697-701. doi:10.1016/j.urology.2014.05.025
5. Mathews R, Docimo S, Gearhart JP. "Sigmoid 'Tail' Modification for Bladder Augmentation." Urology. 1997;49(4):609-11. doi:10.1016/s0090-4295(97)00006-x
6. Sidi AA, Reinberg Y, Gonzalez R. "Influence of Intestinal Segment and Configuration on the Outcome of Augmentation Enterocystoplasty." The Journal of Urology. 1986;136(6):1201-4. doi:10.1016/s0022-5347(17)45282-7
7. Hayashi Y, Yamataka A, Kaneyama K, et al. "Review of 86 Patients With Myelodysplasia and Neurogenic Bladder Who Underwent Sigmoidocolocystoplasty and Were Followed More Than 10 Years." The Journal of Urology. 2006;176(4 Pt 2):1806-9. doi:10.1016/j.juro.2006.03.123
8. Wang Z, Liao L. "Effectiveness and Complications of Augmentation Cystoplasty With or Without Nonrefluxing Ureteral Reimplantation in Patients With Bladder Dysfunction: A Single Center 11-Year Experience." The Journal of Urology. 2018;199(1):200-205. doi:10.1016/j.juro.2017.07.073
9. Juhász ZS, Kispál Z, Kardos D, Vajda P. "Long-Term Urodynamic Findings Following Colo-, Gastro- And Ileocystoplasty." Pediatric Surgery International. 2024;40(1):131. doi:10.1007/s00383-024-05714-z
10. Mohler JL. "Metabolic Acidosis After Bladder Replacement: Comparison of Severity and Reversibility in Ileal and Colonic Reservoirs." The Journal of Urology. 1988;139(3):628-33. doi:10.1016/s0022-5347(17)42547-x
11. Beseghi U, Guys JM, Dibenedetto V, et al. "Metabolic Consequences of Sigmoidocystoplasty in Children." Pediatric Surgery International. 1996;11(2-3):150-2. doi:10.1007/BF00183750
12. Miyano T, Yamataka A, Iwashita K, et al. "Histology of the Neobladder Mucosa After Sigmoidocolocystoplasty." Journal of Pediatric Surgery. 2000;35(1):104-8. doi:10.1016/s0022-3468(00)80024-x
13. Garnier S, Vendrell J, Boillot B, et al. "Malignancy After Augmentation Enterocystoplasty: A Nationwide Study of Natural History, Prognosis and Oncogene Panel Analysis." The Journal of Urology. 2020;204(1):136-143. doi:10.1097/JU.0000000000000752
14. Kälble T, Hofmann I, Riedmiller H, Vergho D. "Tumor Growth in Urinary Diversion: A Multicenter Analysis." European Urology. 2011;60(5):1081-6. doi:10.1016/j.eururo.2011.07.006
15. Biardeau X, Chartier-Kastler E, Rouprêt M, Phé V. "Risk of Malignancy After Augmentation Cystoplasty: A Systematic Review." Neurourology and Urodynamics. 2016;35(6):675-82. doi:10.1002/nau.22775
16. Austen M, Kälble T. "Secondary Malignancies in Different Forms of Urinary Diversion Using Isolated Gut." The Journal of Urology. 2004;172(3):831-8. doi:10.1097/01.ju.0000134890.07434.8e
17. Gonzalez R, Buson H, Reid C, Reinberg Y. "Seromuscular Colocystoplasty Lined With Urothelium: Experience With 16 Patients." Urology. 1995;45(1):124-9. doi:10.1016/s0090-4295(95)97364-8
18. Buson H, Manivel JC, Dayanç M, Long R, Gonzalez R. "Seromuscular Colocystoplasty Lined With Urothelium: Experimental Study." Urology. 1994;44(5):743-8. doi:10.1016/s0090-4295(94)80220-3
19. Jung HJ, Lee H, Im YJ, et al. "Prerequisite for Successful Surgical Outcome in Urothelium Lined Seromuscular Colocystoplasty." The Journal of Urology. 2012;187(4):1416-21. doi:10.1016/j.juro.2011.12.009
20. Jednak R, Schimke CM, Barroso U Jr, Barthold JS, González R. "Further Experience With Seromuscular Colocystoplasty Lined With Urothelium." The Journal of Urology. 2000;164(6):2045-9. doi:10.1016/s0022-5347(05)66962-5. PMID 11061922
21. González R, Ludwikowski B, Horst M. "Determinants of Success and Failure of Seromuscular Colocystoplasty Lined With Urothelium." The Journal of Urology. 2009;182(4 Suppl):1781-4. doi:10.1016/j.juro.2009.02.062
22. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Treatment and Follow-Up." The Journal of Urology. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239
23. European Association of Urology. EAU Guidelines on Neuro-Urology. Limited update, March 2026. Blok B (Chair), et al. uroweb.org/guidelines/neuro-urology
24. Sato A, Asanuma H, Izawa M, et al. "Management of Pregnancy and Delivery After Augmentation Cystoplasty: A Novel Surgical Technique Using the Sigmoid Colon With Retroperitoneal Mesentery Placement Optimized for Cesarean Section." Int J Urol. 2026;33(3):e70345. doi:10.1111/iju.70345
25. Sun XG, Wang RY, Xu JL, et al. "Surgical outcomes of bladder augmentation: A comparison of three different augmentation procedures." World J Clin Cases. 2020;8(15):3240-3248. doi:10.12998/wjcc.v8.i15.3240
26. Chua ME, Yadav P, Wang PZT, et al. "2023 Canadian Urological Association/Pediatric Urologists of Canada guideline: Pediatric patients with neurogenic lower urinary tract dysfunction: Full-text version." Can Urol Assoc J. 2023;17(10):E338-E357. doi:10.5489/cuaj.8390
27. Cameron AP, Chung DE, Dielubanza EJ, et al. "The AUA/SUFU Guideline on the Diagnosis and Treatment of Idiopathic Overactive Bladder." J Urol. 2024;212(1):11-20. doi:10.1097/JU.0000000000003985
28. Clemens JQ, Erickson DR, Varela NP, Lai HH. "Diagnosis and Treatment of Interstitial Cystitis/Bladder Pain Syndrome." J Urol. 2022;208(1):34-42. doi:10.1097/JU.0000000000002756
29. Metcalfe PD, Casale AJ, Kaefer MA, et al. "Spontaneous bladder perforations: a report of 500 augmentations in children and analysis of risk." J Urol. 2006;175(4):1466-1470; discussion 1470-1471. doi:10.1016/S0022-5347(05)00672-5
30. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS. 2026 edition, sections 4.1.4.c.4 and 4.1.5.a. Guideline
31. Abrahamson K, Bogaert G, Dellenmark-Blom M, et al. "EAU–ESPU–ERN eUROGEN–ERN ITHACA–ERN ERKNet–IFSBH Guidelines on Spinal Dysraphism in Children and Adolescents." January 2025. Full guideline
32. Ascent Pharmaceuticals, Inc. "Potassium Citrate Extended-Release Tablets: Prescribing Information." DailyMed. Revised January 2021. Drug label
33. European Association of Urology. "EAU Guidelines on Urolithiasis: Bladder Stones," sections 6.4.5.b and 6.6. 2026. Guideline
34. Hayashi Y, Nishimura E, Shimizu S, et al. "Sigmoidocolocystoplasty for neurogenic bladder reviewed after 20 years." J Pediatr Surg. 2017;52(12):2070-2073. doi:10.1016/j.jpedsurg.2017.08.029
35. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Diagnosis and Evaluation." J Urol. 2021;206(5):1097-1105. doi:10.1097/JU.0000000000002235