Supratrigonal Cystectomy with Augmentation Cystoplasty
Supratrigonal cystectomy is a subtotal bladder resection in which the bladder body (dome and lateral walls) is excised above the level of the trigone, preserving the trigone, ureteral orifices, and bladder neck. It can be combined with augmentation cystoplasty using a bowel segment to reconstruct a larger, more compliant reservoir.[1] This procedure is distinct from radical cystectomy, which removes the entire bladder and is used for malignancy.
Definition and Anatomy
The resection line is placed directly above the ureteral orifices, removing the diseased supratrigonal bladder while leaving the trigone intact.[1] Preserving the trigone usually allows the native ureterovesical junctions to remain intact and may preserve spontaneous voiding.[1][2][7] Two patients in the long-term IC/BPS cohort underwent concomitant unilateral reimplantation.[1][2][7]
Indications
Supratrigonal cystectomy with augmentation cystoplasty is reserved for patients who have failed all conservative and less invasive therapies. Two primary indications:
- Interstitial cystitis / bladder pain syndrome (IC/BPS). Particularly the classic or ulcerative (Hunner lesion) subtype with reduced bladder capacity refractory to conservative treatment. The AUA guideline on IC/BPS states that major surgery (substitution cystoplasty, urinary diversion with or without cystectomy) may be undertaken in carefully selected patients with bladder-centric symptoms, or in the rare instance of an end-stage small fibrotic bladder, for whom all other therapies have failed (Option, Grade C). The best-known predictors of success are an end-stage fibrotic bladder, small bladder capacity under anesthesia and Hunner lesions; a large capacity under anesthesia suggests a functional or extravesical source of pain and is associated with treatment failure.[3]
- Neurogenic lower urinary tract dysfunction (NLUTD). Refractory neurogenic detrusor overactivity and/or poor bladder compliance, including spinal cord injury (SCI). AUA/SUFU states that clinicians may offer augmentation cystoplasty to select NLUTD patients refractory to or intolerant of less invasive therapies .[4] The EAU Neuro-Urology guideline recommends offering bladder augmentation for low compliance or refractory neurogenic detrusor overactivity and identifies the severely thick, fibrotic bladder wall as an indication for supratrigonal resection.[4][16]
Radiation-damaged bladders have been treated with cystectomy and urinary diversion for benign disease; this is a different operation from supratrigonal cystectomy with augmentation.[5]
End-stage ketamine-associated uropathy is a further benign indication. A review of 193 reconstructed patients lists partial or supratrigonal cystectomy with enterocystoplasty among the options; 124/193 (64%) underwent enterocystoplasty. Among 69 patients with pain outcome data, 16 had persistent postoperative pain, and all 16 reported relapse of ketamine use.[19] Staging, abstinence requirements and complication rates are on Ketamine-Associated Uropathy (Ketamine Cystitis).
Surgical Technique
The procedure has two main components:
- Supratrigonal resection. The bladder is mobilized and the dome or body is excised circumferentially just above the ureteral orifices, leaving the trigone as a cuff.[1] In Queissert et al.'s ulcerative IC/BPS series, a butterfly-shaped resection left an approximately 0.5–1 cm margin around the trigone.[7]
- Augmentation cystoplasty. A detubularized segment of bowel is anastomosed to the remaining trigonal remnant to create a low-pressure, high-capacity reservoir. Common bowel segments:
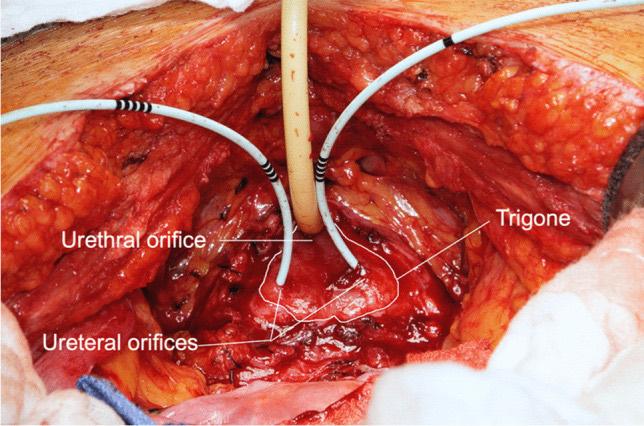
Operative field after supratrigonal cystectomy for ulcerative IC/BPS: the detrusor has been excised, leaving the residual trigone (outlined) with the stented ureteral orifices and the urethral orifice. From Queissert F, et al. Int Urogynecol J. 2022;33(5):1267-1272, Fig. 1 (CC BY 4.0).[7]
Surgical approaches
- Open surgery, the traditional approach.[1][7]
- Robot-assisted laparoscopic surgery has been described in small series with acceptable perioperative outcomes. A preliminary 10-patient totally intracorporeal RASCAC series reported median operative time 250 minutes, EBL 75 mL and hospitalization 12 days; one patient had a 30-day major complication and two developed late fistulas.[8] A 19-patient combined robotic and mini-laparotomy series described operative-time improvement after about five cases among experienced robotic surgeons.[8][9] A later single-center retrospective series of 71 robot-assisted procedures (41 NLUTD, 30 IC/BPS; median follow-up 4.8 years) reported early complications in 36.7%, mostly Clavien 2 or less, and three major late complications (one bladder perforation, two bowel obstructions).[17] Among 41 NLUTD patients, pad-free continence rose from 20/41 to 38/41; ISC continued routinely, and three patients later required an artificial urinary sphincter for continence.[17] Among 30 IC/BPS patients, pain scores fell from 7.8 to 2.2 and 4/30 had persistent severe symptoms.[17] At last follow-up, none were classified as spontaneous voiders: 19/30 voided by abdominal straining and 11/30 used ISC.[17] A systematic review of robotic surgery in NLUTD (eight studies, two of augmentation or continent diversion) concluded that current evidence is insufficient for firm conclusions; its meta-analysis compared robotic with open cystectomy and ileal conduit, not augmentation.[18]
Supratrigonal vs. Subtrigonal Cystectomy
A retrospective comparison included only 6 supratrigonal and 17 subtrigonal patients, with unequal mean follow-up (31.5 versus 93.9 months). All six supratrigonal patients voided spontaneously; 41% of the subtrigonal group required self-catheterization.[1] Subtrigonal cystectomy removes the trigone and requires ureteral reimplantation into the bowel segment.
Outcomes
IC/BPS
- In a 27-woman cohort, 26 had postoperative outcome data at median 171 months. 22/23 questionnaire respondents reported being much or very much better; patients with early diversion were not included in that satisfaction assessment. Persistent symptoms led to early diversion in 2/26 and late relapse occurred in 5/26, all of whom required ISC.[7]
- In a 13-patient series, all 10 with classic IC reported symptom relief after surgery, whereas pain persisted in all 3 with nonulcer IC despite some reduction in voiding frequency.[10]
- The AUA guideline's review pooled 11 cohorts of supratrigonal cystectomy with ileal and/or cecal augmentation (4 to 40 patients each, 170 in total): 39 patients (23%) failed, 27 underwent secondary cystectomy and diversion for persistent pain, and 103 of 144 (72%) reporting voiding ability voided spontaneously. Five studies reporting Hunner-lesion patients gave complete relief in 59 of 69 (86%).[3]
- At six months, a Korean series of 40 patients with Hunner-lesion IC/BPS reported lower pain scores (8.3 to 1.3), frequency, urgency, and nocturia, with increased bladder capacity. At last follow-up (median 12 months, IQR 7–17), 8/40 (20%) met the study's failure definition of persistent symptoms or <30% reduction in the symptom index.[11]
Neurogenic bladder
- In SCI patients, a large series (n=77) demonstrated study-defined long-term success rates of 93.5% for urodynamic parameters and 76.6% for urinary incontinence at a median 13 years after surgery. Bladder lithiasis occurred in 20.5%, and at least one febrile UTI in 55.8% (mostly within the first 2 years). No bladder cancer was diagnosed.[12]
- Another SCI series (n=61) using the Hautmann pouch showed improved or total continence in 89.7% and 74.1%, respectively, with significant improvements in maximum cystometric capacity (305 to 509 mL), compliance (15 to 42.7 mL/cmH₂O), and detrusor pressure at capacity (54.1 to 19.1 cmH₂O).[2]
- In a spinal cord injury rehabilitation cohort (n=29), continence improved from 7% to 69%, bladder capacity increased from 240 to 500 mL, and compliance from 13 to 50 mL/cmH₂O.[13]
Complications
Complications can require further surgery and are occasionally life-threatening. The following observations come from different populations and follow-up periods:
- Need for catheterization. This depends on baseline neurologic function, outlet procedures and reconstruction. In the long-term IC/BPS study, 8/26 performed ISC and one had long-term suprapubic drainage; the 41% estimate from Linn concerns subtrigonal reconstruction.[7][1][1][7]
- Urinary tract infection and pyelonephritis. Madec reported early (<30-day) pyelonephritis in 21.1% of 19 patients; Balanca reported at least one febrile UTI in 55.8% during long-term follow-up, mostly in the first two years.[9][12] In the 40-patient Hunner-lesion series, 7/40 (17.5%) had postoperative acute pyelonephritis, including five with reflux.[11]
- Bladder stones. 20.5% in adults with SCI (Balanca) and 5 of 22 children in a pediatric augmentation cohort (Chang), in long-term follow-up.[12][14]
- Bowel dysfunction (diarrhea, fecal incontinence). 27.5% in the Hautmann pouch SCI series.[2]
- Mucus production. Bowel augmentation produces mucus, which should be discussed before reconstruction.[4]
- Hyperchloremic metabolic acidosis from bowel-segment absorption.[6][13]
- Urinary fistula. Late fistulas were reported in two of ten patients in the robot-assisted series; both had low ISC compliance.[8]
- Vesicoureteral reflux. At three months, 7/40 (17.5%) in one Hunner-lesion IC/BPS series; most cases subsequently resolved.[11]
- Paralytic and obstructive ileus. These were early postoperative complications.[13]
- Bladder perforation. Reported as rare and life-threatening.[6][14]
- Malignancy risk. Malignancy after enterocystoplasty is documented in the broader augmentation literature. No cancers were reported in these two small cohorts; surveillance follows augmentation guidance.[6][12][14]
- Vitamin B₁₂ deficiency. This is possible with ileal segment use and requires long-term monitoring.[15]
For separate context, a mixed series of cystectomy with urinary diversion for benign disease (n=139, 53% supratrigonal resection) reported that 57% had Clavien-Dindo grade ≥ II complications, most commonly transfusion, prolonged ileus, and pyelonephritis. Duration of surgery was the only independent predictor of serious complications.[5]
Patient Selection
- Select for a bladder source of pain. Historical small cohorts reported better outcomes with Hunner-lesion disease, but AUA does not require Hunner lesions for all major surgery. Carefully selected bladder-centric disease or an end-stage small fibrotic bladder may qualify after other feasible treatments fail. Pelvic-floor and other extravesical pain sources are reassessed before irreversible surgery.[3] Lack of relief with a local anesthetic bladder instillation, pelvic muscle tenderness, or widespread pain raises the risk of failure; the AUA guideline states that IC/BPS surgery is not recommended for a polysymptomatic or polysyndromic presentation.[3] In ulcerative IC/BPS, assess trigonal involvement and pain with test catheterization before preserving the trigone; Queissert et al. advise considering complete cystectomy when catheterization provokes pain, is refused, or disease involves the trigone.[7]
- Surgery should be performed only by surgeons with extensive experience in IC/BPS or neurogenic bladder, with dedication to long-term follow-up.[3]
- Before reconstruction, assess whether the patient or caregiver can perform ISC if needed. The AUA/SUFU adult NLUTD guideline explicitly calls for assessing hand and cognitive function before augmentation.[4] Counsel patients about possible lifelong ISC, metabolic monitoring, and persistent or recurrent symptoms. Preoperative renal scars warrant particular attention because metabolic acidosis can develop after bowel augmentation.[16]
Long-Term Follow-Up
- Follow-up is lifelong. For NLUTD with bowel reconstruction, the AUA/SUFU guideline states that the clinician should assess the patient annually with a focused history, examination and symptom assessment, a basic metabolic panel and urinary-tract imaging .[4] B₁₂ is monitored over time when terminal ileum is used.[4][15]
- Repeat urodynamics according to risk and clinical change; AUA/SUFU advises repeat studies at an appropriate interval after treatment when impaired storage parameters, impaired voiding, or both place the upper tracts at risk .[4] One stable SCI cohort questioned routine repeated testing.[12] Reassess new incontinence, infection, upper-tract change or impaired emptying.[4]
- Gross hematuria, recurrent symptomatic UTI or unexplained suprapubic pain is investigated promptly. The AUA/SUFU guideline states that clinicians should perform cystoscopy for gross hematuria or symptomatic recurrent UTI after reconstruction with bowel , and that clinicians should not perform screening or surveillance cystoscopy in NLUTD patients .[4][20]
References
1. Linn JF, Hohenfellner M, Roth S, et al. "Treatment of Interstitial Cystitis: Comparison of Subtrigonal and Supratrigonal Cystectomy Combined With Orthotopic Bladder Substitution." The Journal of Urology. 1998;159(3):774-8. doi:10.1016/s0022-5347(01)63726-1
2. Gobeaux N, Yates DR, Denys P, et al. "Supratrigonal Cystectomy With Hautmann Pouch as Treatment for Neurogenic Bladder in Spinal Cord Injury Patients: Long-Term Functional Results." Neurourology and Urodynamics. 2012;31(5):672-6. doi:10.1002/nau.21239
3. Clemens JQ, Erickson DR, Varela NP, Lai HH. "Diagnosis and Treatment of Interstitial Cystitis/Bladder Pain Syndrome." The Journal of Urology. 2022;208(1):34-42. doi:10.1097/JU.0000000000002756
4. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Treatment and Follow-Up." The Journal of Urology. 2021;206(5):1106-1113. doi:10.1097/JU.0000000000002239
5. Osborn DJ, Dmochowski RR, Kaufman MR, et al. "Cystectomy With Urinary Diversion for Benign Disease: Indications and Outcomes." Urology. 2014;83(6):1433-7. doi:10.1016/j.urology.2014.02.030
6. Cheng PJ, Myers JB. "Augmentation Cystoplasty in the Patient With Neurogenic Bladder." World Journal of Urology. 2020;38(12):3035-3046. doi:10.1007/s00345-019-02919-z
7. Queissert F, Bruecher B, van Ophoven A, Schrader AJ. "Supratrigonal Cystectomy and Augmentation Cystoplasty With Ileum or Ileocecum in the Treatment of Ulcerative Interstitial Cystitis/Bladder Pain Syndrome: A 14-Year Follow-Up." International Urogynecology Journal. 2022;33(5):1267-1272. doi:10.1007/s00192-022-05110-y
8. Grilo N, Chartier-Kastler E, Grande P, et al. "Robot-Assisted Supratrigonal Cystectomy and Augmentation Cystoplasty With Totally Intracorporeal Reconstruction in Neurourological Patients: Technique Description and Preliminary Results." European Urology. 2021;79(6):858-865. doi:10.1016/j.eururo.2020.08.005
9. Madec FX, Hedhli O, Perrouin-Verbe MA, et al. "Feasibility, Morbidity, and Functional Results of Supratrigonal Cystectomy With Augmentation Ileocystoplasty by Combined Robot-Assisted Laparoscopy and Mini-Laparotomy Approach." Journal of Endourology. 2017;31(7):655-660. doi:10.1089/end.2017.0107
10. Peeker R, Aldenborg F, Fall M. "The Treatment of Interstitial Cystitis With Supratrigonal Cystectomy and Ileocystoplasty: Difference in Outcome Between Classic and Nonulcer Disease." The Journal of Urology. 1998;159(5):1479-82. doi:10.1097/00005392-199805000-00018
11. Kim HJ, Lee JS, Cho WJ, et al. "Efficacy and Safety of Augmentation Ileocystoplasty Combined With Supratrigonal Cystectomy for the Treatment of Refractory Bladder Pain Syndrome/Interstitial Cystitis With Hunner's Lesion." International Journal of Urology. 2014;21 Suppl 1:69-73. doi:10.1111/iju.12320
12. Balanca A, Even A, Malot C, et al. "Long-Term Clinical and Urodynamic Effectiveness of Augmentation Ileocystoplasty With Supra-Trigonal Cystectomy in Individuals With Spinal Cord Injury." World Journal of Urology. 2022;40(8):2121-2127. doi:10.1007/s00345-022-04028-w
13. Krebs J, Bartel P, Pannek J. "Functional Outcome of Supratrigonal Cystectomy and Augmentation Ileocystoplasty in Adult Patients With Refractory Neurogenic Lower Urinary Tract Dysfunction." Neurourology and Urodynamics. 2016;35(2):260-6. doi:10.1002/nau.22709
14. Chang JW, Kuo FC, Lin TC, et al. "Long-Term Complications and Outcomes of Augmentation Cystoplasty in Children With Neurogenic Bladder." Scientific Reports. 2024;14(1):4214. doi:10.1038/s41598-024-54431-z
15. Reddy M, Kader K. "Follow-Up Management Of Cystectomy Patients." The Urologic Clinics of North America. 2018;45(2):241-247. doi:10.1016/j.ucl.2018.01.001
16. EAU. Neuro-urology Guidelines. 2026. Bladder augmentation and follow-up. Guideline.
17. Batard T, Mesnard B, Levesque A, et al. Long-term functional outcomes and complications of robot-assisted laparoscopic supratrigonal cystectomy with augmentation cystoplasty in adult patients with neurogenic lower urinary tract dysfunction and interstitial cystitis/bladder pain syndrome: a single-centre experience. BJUI Compass. 2025;6(7):e70029. doi:10.1002/bco2.70029
18. Geretto P, De Cillis S, Osman NI, et al. The outcomes of robot-assisted surgery in the treatment of neurogenic lower urinary tract dysfunctions: a systematic review and meta-analysis. World J Urol. 2024;42(1):631. doi:10.1007/s00345-024-05312-7
19. Vizgan G, Huamán M, Rychik K, et al. "Ketamine-Induced Uropathy: A Narrative Systemic Review of Surgical Outcomes of Reconstructive Surgery." BJUI Compass. 2023;4(4):377-384. doi:10.1002/bco2.239
20. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU Guideline on Adult Neurogenic Lower Urinary Tract Dysfunction: Diagnosis and Evaluation." J Urol. 2021;206(5):1097-1105. doi:10.1097/JU.0000000000002235