Ureterocystoplasty
Ureterocystoplasty is a form of augmentation cystoplasty that uses a detubularized, reconfigured dilated ureter (megaureter) to enlarge the bladder. Bellinger reported it in children in 1993. The augmenting tissue is native urothelium with muscular backing, so bowel-segment mucus production and urine–intestinal electrolyte absorption are avoided when no bowel is incorporated into the urinary tract.[1][2] It is an option for selected patients with enough suitable ureteral tissue. Patch adequacy, renal preservation and the likely need for later augmentation determine candidacy.[3][4]
Indications
Ureterocystoplasty requires both a bladder that needs augmentation and enough suitable dilated ureter (megaureter).[1][2][3][5] For children with spinal dysraphism, the 2026 EAU/ESPU guideline summary states that enterocystoplasty should be offered when conservative treatment, including onabotulinumtoxinA, fails to maintain a low-pressure, compliant reservoir; it describes ureterocystoplasty as suitable only in selected cases with variable outcomes.[26] Clinical settings that may supply ureteral tissue or favor bowel-free reconstruction include:
- Neurogenic bladder with associated megaureter and VUR.
- Posterior urethral valves with VURD syndrome (vesicoureteral reflux dysplasia) and a nonfunctioning kidney with ipsilateral megaureter.
- Bladder exstrophy / cloacal exstrophy with dilated ureters.
- Massive VUR (grade IV–V) with a dilated, tortuous ureter.
- Ureterocele with associated megaureter.
- Patients with chronic renal failure in whom the metabolic consequences of enterocystoplasty would be poorly tolerated.[6]
Patient Selection — Predictors of Success
Husmann's multicenter study (n=64) reported associations with success in small subgroups:[4]
- Ureteral diameter > 1.5 cm in patients without reflux: none of 6 patients with diameter > 1.5 cm required re-augmentation (median capacity increased 6-fold and compliance 50-fold).[4] All 3 patients with diameter < 1.5 cm required re-augmentation.
- Compliance > 20 mL/cm H₂O in patients with reflux: in 6 patients with normal or mild noncompliance, compliance improved 1-fold and none required re-augmentation.[4]
- Moderately or severely noncompliant augmenting system (< 20 mL/cm H₂O): re-augmentation occurred or was pending in 21 of 26 patients (81%).[4]
In the distal-segment group (5 to 8 cm of a single megaureter), re-augmentation occurred or was pending in 23 cases, reported as 92%; the reported group sizes (8 and 16 patients) do not reproduce that percentage. Distal-segment results differ between series. Available tissue and the entire refluxing system are assessed on preoperative imaging and urodynamics.[4]
Surgical Technique
Scenario 1: Nonfunctioning ipsilateral kidney (classic)[1][2][7]
- Confirm the ipsilateral renal unit is nonfunctioning and that nephrectomy is appropriate; do not sacrifice a functioning kidney merely to obtain augmentation tissue.
- Mobilize the entire dilated ureter (and often the renal pelvis), preserving its blood supply. Multiple prior antireflux operations may compromise ureteral vascularity; assess patch perfusion because partial ureteral necrosis is a concern when vascularity is impaired.[25]
- Open the ureter longitudinally away from its preserved vascular attachments, avoiding injury to the adventitial blood supply.
- Fold opened ureter into a U-shape or patch.
- Bivalve the bladder (sagittal cystotomy).
- Suture the reconfigured patch to the opened bladder as a cup-patch augmentation.
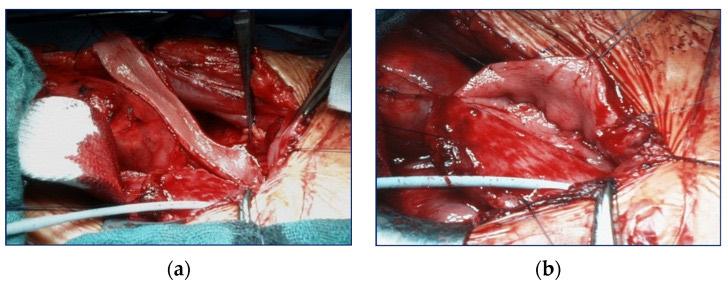
Ureterocystoplasty in a boy with valve bladder syndrome. (a) The megaureter incised anteriorly. (b) The opened megaureter folded into a U shape. From Hofmann A, et al. Children (Basel). 2023;10(4):692, Figure 1 (CC BY 4.0).[19]
Scenario 2: Functioning ipsilateral kidney (renal preservation)[8][9]
A functioning ipsilateral kidney is not a contraindication (Gosalbez–Kim).
- Transureteroureterostomy (TUU): ipsilateral ureter divided; proximal stump anastomosed to the contralateral ureter to maintain renal drainage.
- The distal dilated ureter is then used for augmentation.
- With partial ureteral duplication, ipsilateral upper-to-lower ureteropyelostomy can be added to maximize available ureter.[8]
- In the five-patient series, mean capacity at 30 cm H₂O increased from 142 to 500 mL (3.5-fold).[8]
The procedure can be performed entirely extraperitoneally (Dewan and Condron); renal preservation, TUU, and ureterocystoplasty are done without entering the peritoneal cavity.[9]
Scenario 3: Bilateral megaureters
When both ureters are dilated:[10][11][12][13][14]
- Bilateral ureteral tissue: the operative plan must preserve a drainage route from every functioning renal unit. Distal patches may be combined with proximal ureteral reimplantation or another reconstruction; TUU alone cannot restore drainage if both receiving distal ureters have been fully opened for augmentation. In Babu and Ragoori's case, both ureters and the Mitrofanoff channel were stented for 2 weeks, suprapubic drainage continued for 2 weeks, and a cystogram at 2 weeks showed no leak or reflux; CIC through the Mitrofanoff began at 4 weeks.[24] Bilateral nephrectomy belongs only to independently indicated management of nonfunctioning kidneys.
- Distal two-thirds of both ureters for augmentation, proximal ureters anastomosed to a tubularized ileal segment ("common ileal ureter") reimplanted in the bladder.[13]
- One ureter for augmentation, the other for a Mitrofanoff channel (teapot technique).[14]
Perovic advocated that ureterocystoplasty "could be performed more frequently" by dividing the megaureter, using the distal portion for augmentation and the proximal portion for reimplantation.[12]
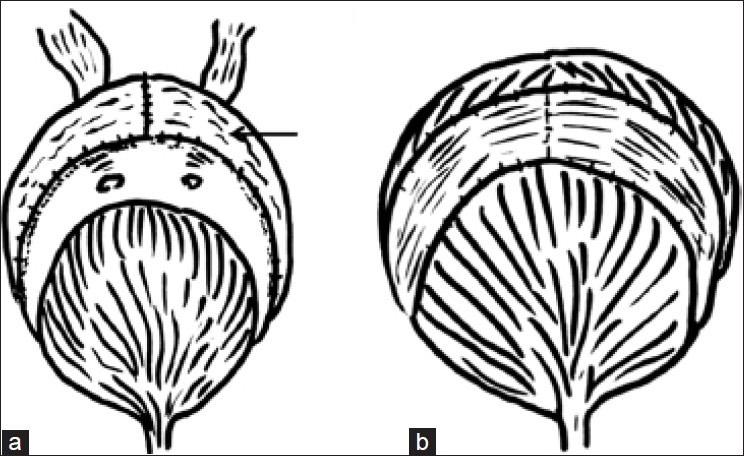
Distal ureterocystoplasty with proximal ureteric reimplantation. (a) The detubularized distal ureters are reconfigured into a patch (arrow) and anastomosed first to the posterior lip of the bladder. (b) The ureterocystoplasty is completed by anastomosing the ureteric patch to the anterior lip of the bladder with 4-0 polyglactin. From Babu R, Ragoori D. J Indian Assoc Pediatr Surg. 2012;17(4):165-167, Figure 2 (CC BY-NC-SA 3.0).[24]
Technical Modifications
- Teapot ureterocystoplasty (Kajbafzadeh) is used for bilateral megaureters with neurogenic bladder. The larger ureter is used for augmentation, with its distal 2 cm kept tubularized (the "teapot spout"), and the opposite ureter forms a ureteral Mitrofanoff channel. At median 121 mo (about 10 yr), all 13 patients were dry with clean intermittent catheterization and/or voiding, none needed repeat augmentation and none developed bladder calculi; median postoperative capacity 430 mL (versus 210 mL pre-op, p=0.001).[14]
- Teacup modification (Adams). When a single ureter is used as the augmenting patch rather than split between augment and channel, the distal 2–3 cm of ureter and the native ureterovesical junction are left intact instead of being incised, distinguishing this from the teapot technique's tubularized spout. In the original 7-patient series (mean follow-up 28 mo), six underwent pre- and postoperative video urodynamics; mean cystometric capacity increased from 103 to 236 mL (137% of expected capacity for age and size), with no uninhibited contractions or compliance problems, no bladder calculi, and one case of pyelonephritis.[21]
- Common ileal ureter (Frimberger) uses the distal two-thirds of both megaureters for augmentation. The proximal stumps are anastomosed to a tubularized, tapered ileal segment that is reimplanted in the bladder. In six patients at median 45.3 months, capacity increased up to 12-fold and mean compliance reached 58 mL/cm H₂O; none required repeat augmentation, but one required endoscopic incision of the reimplantation.[13]
- Laparoscopic ureterocystoplasty (Landa Juárez) was described in 4 pediatric patients with myelomeningocele, combined with a Mitrofanoff channel from the proximal ureter. At 2–4 yr, all patients had at least 75% of expected capacity for age; compliance 15–20 mL/cm H₂O; bladder leak-point pressure < 40 cm H₂O.[15]
Outcomes
| Series | n | Tissue used | Follow-up | Capacity | Reported clinical outcome | Re-augmentation |
|---|---|---|---|---|---|---|
| Churchill 1993[2] | 16 | Complete ureter ± pelvis | Mean 22 mo | Good capacity, low pressure in 12/13 with complete postoperative urodynamics | 10/16 fully continent | None reported |
| Landau 1994[16] | 8 (vs 8 ileum) | Megaureter | — | 417 mL (vs 381 mL ileum, p>0.05) | 7/8 with normal pressure-specific bladder volume and dynamic compliance | Not reported |
| Zubieta 1999[10] | 32 | Variable (1 or 2 ureters, partial) | Median 16 mo | Median capacity increase: 375% (groups 1–2) / 230% (distal-segment group 3) | 92–100% clinical improvement | 0% |
| Pascual 2001[6] | 22 | Single distal ureter | Mean 22 mo | Median capacity increase below 30 cm H₂O: 177% | 19/22 (86%) dry on CIC every 4 hr | 1/22 (4.5%; colocystoplasty after patch perforation) |
| Husmann 2004[4] | 64 | Variable | Variable | Selection-dependent | Variable | Distal segment: 23 cases (reported as 92%); noncompliant refluxing system: 21/26 (81%) |
| Johal 2008[17] | 17 | Ipsilateral kidney preserved in 9 | Mean 4.5 yr | Mean capacity 125 → 292 mL on 6-mo postoperative urodynamics | 13/17 avoided further augmentation | 4/17 (24%) |
| Kajbafzadeh (teapot)[14] | 13 | Bilateral megaureters | Median 121 mo | Median capacity 210 → 430 mL | 100% dry | 0% |
| Kilciler 2000[11] | 7 | Both ureters (functional kidneys) | Mean 30 mo | 279 mL mean at 3 mo; stable at follow-up | 100% continent | None reported |
| Tekgül 2000[3] | 6 | Variable | — | Average capacity increase: 263% | 100% continent | None reported |
Landau compared eight ureterocystoplasty patients with eight age- and diagnosis-matched ileocystoplasty controls. Mean capacity was 417 versus 381 mL and pressure-specific volume 413 versus 380 mL (both p>0.05). Pressure-specific bladder volume and dynamic compliance were normal in 7 of 8 ureterocystoplasty patients; all 8 ileocystoplasty controls had normal postoperative urodynamics.[16]
More recent retrospective series report similar patterns. In 10 boys with posterior urethral valves followed for a median of 64.5 months, none required conversion to enterocystoplasty; one of the five boys tested with invasive urodynamics had persistent low compliance.[19] Mean age-adjusted capacity increased from 77% to 102%, and eight boys voided spontaneously.[19] Of four nontransplanted boys with long-term renal data, two declined from CKD stage 1 or 2 to stage 2 or 3.[19] In a single-centre review of 168 augmentations, revision surgery was needed in 3 of 24 (12.5%) ureterocystoplasties, 6 of 72 (8.3%) simple ileal patches and 0 of 72 ileal cups.[20] Median follow-up differed: 6.2, 4.43 and 4.23 years, respectively. The authors estimated that ureterocystoplasty was feasible in about 14% of cases.[20]
Ureteral tissue quantity and outcomes (Zubieta)[10]
- Mixed two-ureter and complete-ureter groups (1–2): median capacity increased 375%; patients receiving a complete ureteral segment had clinical improvement, decreased hydronephrosis, and resolution of reflux.[10]
- Distal ureteral segment only (with TUU): median capacity increased 230%; clinical improvement in 92.3%.[10]
- This small study detected no significant difference between one and two ureters; adequacy of a single ureter depends on available tissue.
- Selected partial segments performed well in this series, but other cohorts had substantial failure.
Advantages Over Enterocystoplasty
| Issue | What can be said |
|---|---|
| Mucus and electrolyte absorption | A urothelial patch avoids bowel-specific mucus and urine–intestinal absorption if no bowel is used elsewhere in the reconstruction. |
| Metabolic or B₁₂ monitoring | Bowel-specific supplementation may not be needed for a purely ureteral patch, but kidney disease and other clinical indications still require laboratory monitoring. |
| Malignancy and stones | No enterovesical junction is created. |
| Bowel morbidity | Avoids bowel harvest in a bowel-free operation. |
| Complexity and applicability | Tissue availability and the need for TUU, reimplantation or renal surgery can make reconstruction complex. Neither approach is universally suitable. |
Complications
- Failure requiring re-augmentation varies substantially with selection and available tissue. Rates were high with short distal ureteral segments (5–8 cm) or moderate or severe noncompliance (< 20 mL/cm H₂O) of the augmenting system.[4]
- Contralateral ureterovesical obstruction occurred in 2/16 (12.5%) in the Churchill series.[2]
- Transient urine extravasation occurred in 2/16 (12.5%).[2]
- Spontaneous perforation of the ureteral patch occurred in 1/22 patients (Pascual) and required colocystoplasty.[6]
- Persistent VUR was noted in 1/22 (Pascual) and 3/16 (Perovic, without clinical symptoms).[6][12]
- TUU-related complications include anastomotic stricture and contralateral ureteral obstruction. In the Zubieta series, when TUU was performed (13 patients), a suprapubic tube was left for 2 weeks and a Double-J stent for 1 mo.[10]
Special Considerations
- Pediatric population: Ureterocystoplasty is performed predominantly in children with neurogenic bladder, PUV or exstrophy. It avoids bowel-specific consequences when the reconstruction is entirely bowel-free, but lifelong monitoring of the original bladder and renal disorder is still needed.[1][3][5][17][18]
- Renal insufficiency: A urothelial patch is attractive when chronic renal failure makes enterocystoplasty acidosis poorly tolerated. Five of 22 patients in the Pascual series had chronic renal failure; outcomes for that subgroup are not reported separately.[6]
- Transplant timing. For a patient approaching renal transplantation, ureterocystoplasty before transplantation has been described as a preference when bladder volume or compliance remains inadequate even with a non-detubularized ureter, to prepare the reservoir in advance. Retaining cyclic native urine filling where feasible, rather than removing a still-draining kidney solely to enable the reconstruction, has been described as permitting more liberal fluid intake, preserving residual renal metabolic function, and helping assess bladder emptying and the need for CIC; very high urine output from nephrogenic diabetes insipidus can still cause incontinence despite adequate compliance and capacity.[23]
- Growth and durability: Bladder capacity and pressures are monitored as the child grows. Superior growth compared with bowel augmentation has not been established.
- Combination with Mitrofanoff: With bilateral megaureters, one ureter is used for augmentation and the contralateral ureter for a Mitrofanoff catheterizable channel (teapot technique or laparoscopic approach).[14][15]
- Planning a future channel or reimplant. If a catheterizable channel or extravesical reimplantation of a transplant ureter may be needed later, the site is planned relative to the extent of the ureteral patch: a tunnel made across the patch may not form reliably and lacks the muscular support of native bladder wall.[22]
Long-Term Follow-Up
Surveillance remains necessary and should reflect the underlying bladder disorder, renal function and upper-tract reconstruction:[6][17]
- Renal ultrasound for hydronephrosis and upper-tract status.
- Urodynamic studies to confirm durable improvement in capacity and compliance.
- VCUG to assess for VUR.
- Renal function monitoring (serum creatinine).
- A purely ureteral patch does not itself create bowel-related B₁₂ malabsorption or urinary electrolyte exchange. Obtain metabolic tests as indicated by kidney disease or other clinical factors. A common ileal ureter or other bowel component requires bowel-reconstruction follow-up. Investigate hematuria or other new symptoms.
- CIC compliance. Most patients require CIC, though some neurologically normal patients can void spontaneously.[3]
Summary
Ureterocystoplasty can improve storage using native urothelium in a limited group with suitable megaureters. Counsel about renal drainage reconstruction, catheterization and possible later augmentation.[4][16][17]
References
1. Bellinger MF. "Ureterocystoplasty: A Unique Method for Vesical Augmentation in Children." The Journal of Urology. 1993;149(4):811-3. doi:10.1016/s0022-5347(17)36215-8
2. Churchill BM, Aliabadi H, Landau EH, et al. "Ureteral Bladder Augmentation." The Journal of Urology. 1993;150(2 Pt 2):716-20. doi:10.1016/s0022-5347(17)35596-9
3. Tekgül S, Oge O, Bal K, Erkan I, Bakkaloğlu M. "Ureterocystoplasty: An Alternative Reconstructive Procedure to Enterocystoplasty in Suitable Cases." Journal of Pediatric Surgery. 2000;35(4):577-9. doi:10.1053/jpsu.2000.0350577
4. Husmann DA, Snodgrass WT, Koyle MA, et al. "Ureterocystoplasty: Indications for a Successful Augmentation." The Journal of Urology. 2004;171(1):376-80. doi:10.1097/01.ju.0000100800.69333.4d
5. Diamond DA, Chan IHY, Holland AJA, et al. "Advances in Paediatric Urology." Lancet. 2017;390(10099):1061-1071. doi:10.1016/S0140-6736(17)32282-1
6. Pascual LA, Sentagne LM, Vega-Perugorría JM, et al. "Single Distal Ureter for Ureterocystoplasty: A Safe First Choice Tissue for Bladder Augmentation." The Journal of Urology. 2001;165(6 Pt 2):2256-8. doi:10.1016/S0022-5347(05)66178-2
7. Wolf JS, Turzan CW. "Augmentation Ureterocystoplasty." The Journal of Urology. 1993;149(5):1095-8. doi:10.1016/s0022-5347(17)36306-1
8. Gosalbez R, Kim CO. "Ureterocystoplasty With Preservation of Ipsilateral Renal Function." Journal of Pediatric Surgery. 1996;31(7):970-5. doi:10.1016/s0022-3468(96)90425-x
9. Dewan PA, Condron SK. "Extraperitoneal Ureterocystoplasty With Transureteroureterostomy." Urology. 1999;53(3):634-6. doi:10.1016/s0090-4295(98)00363-x
10. Zubieta R, de Badiola F, Escala JM, et al. "Clinical and Urodynamic Evaluation After Ureterocystoplasty With Different Amounts of Tissue." The Journal of Urology. 1999;162(3 Pt 2):1129-32. doi:10.1016/S0022-5347(01)68095-9
11. Kilciler M, Tan O, Tahmaz L, Dayanç M, Harmankaya C. "Ureterocystoplasty in Bilaterally Functional Kidneys." European Urology. 2000;38(6):742-7. doi:10.1159/000020372
12. Perovic SV, Vukadinovic VM, Djordjevic ML. "Augmentation Ureterocystoplasty Could Be Performed More Frequently." The Journal of Urology. 2000;164(3 Pt 2):924-7. doi:10.1016/S0022-5347(05)67219-9
13. Frimberger D, Klein J, Kropp BP. "The Common Ileal Ureter: A New Technique for Compliant Ureterocystoplasty." The Journal of Urology. 2007;178(4 Pt 2):1819-22. doi:10.1016/j.juro.2007.03.158
14. Kajbafzadeh AM, Farrokhi-Khajeh-Pasha Y, Ostovaneh MR, Nezami BG, Hojjat A. "Teapot Ureterocystoplasty and Ureteral Mitrofanoff Channel for Bilateral Megaureters: Technical Points and Surgical Results of Neurogenic Bladder." The Journal of Urology. 2010;183(3):1168-74. doi:10.1016/j.juro.2009.11.052
15. Landa Juárez S, Fernández AM, Castro NR, De La Cruz Yañez H, Hernández CG. "Laparoscopic Ureterocystoplasty With Mitrofanoff System." Journal of Laparoendoscopic & Advanced Surgical Techniques. 2014;24(6):422-7. doi:10.1089/lap.2013.0290
16. Landau EH, Jayanthi VR, Khoury AE, et al. "Bladder Augmentation: Ureterocystoplasty Versus Ileocystoplasty." The Journal of Urology. 1994;152(2 Pt 2):716-9. doi:10.1016/s0022-5347(17)32689-7
17. Johal NS, Hamid R, Aslam Z, et al. "Ureterocystoplasty: Long-Term Functional Results." The Journal of Urology. 2008;179(6):2373-5. doi:10.1016/j.juro.2008.01.170
18. Gilbert SM, Hensle TW. "Metabolic Consequences and Long-Term Complications of Enterocystoplasty in Children: A Review." The Journal of Urology. 2005;173(4):1080-6. doi:10.1097/01.ju.0000155248.57049.4e
19. Hofmann A, Ioannou A, Zöhrer PI, Rösch WH. "Ureterocystoplasty in Boys with Valve Bladder Syndrome-Is This Method Still up to Date?" Children (Basel). 2023;10(4):692. doi:10.3390/children10040692
20. Parkinson E, Robb A, McCarthy L. "Long-term Survival of Bladder Augmentation is Influenced by its Shape and Mucosal Lining." Journal of Pediatric Surgery. 2025;60(3):162051. doi:10.1016/j.jpedsurg.2024.162051
21. Adams MC, Brock JW 3rd, Pope JC 4th, Rink RC. "Ureterocystoplasty: Is It Necessary to Detubularize the Distal Ureter?" The Journal of Urology. 1998;160(3 Pt 1):851-3. doi:10.1016/S0022-5347(01)62819-2
22. Sturm RM, Yerkes EB. Ureterocystoplasty. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:436-439.
23. Koyle MA, Pfister RR, Kam I, Ford D, Lum G, Karrer FM. "Bladder Reconstruction With the Dilated Ureter for Renal Transplantation." Transplantation Proceedings. 1994;26(1):35-6. PMID:8109010
24. Babu R, Ragoori D. "Bladder Augmentation: Distal Ureterocystoplasty With Proximal Ureteric Reimplantation: A Novel Technique." J Indian Assoc Pediatr Surg. 2012;17(4):165-167. doi:10.4103/0971-9261.102337
25. Haferkamp A, Melchior D, Schumacher S, Müller SC. "Ureteraugmentation der Harnblase. Funktionelle Ergebnisse und mögliche Problembereiche." Urologe A. 2003;42(7):954-959. doi:10.1007/s00120-003-0316-5
26. Radmayr C, Abrahamsson K, Bogaert G, et al. "EAU-ESPU-ERN eUROGEN-ERN ITHACA-ERN ERKNet-IFSBH Guidelines on Spinal Dysraphism in Children and Adolescents: Summary of the Guideline." Eur Urol Open Sci. 2026;88:39-53. doi:10.1016/j.euros.2026.04.002