Cutaneous Ureterostomy
Cutaneous ureterostomy (CU) is the simplest form of incontinent urinary diversion: one or both ureters are brought directly through the abdominal wall to the skin surface, creating a stoma without using any bowel segment.[1][2] It is primarily used in elderly, frail, and highly comorbid patients undergoing radical cystectomy who may not tolerate the additional operative time and bowel manipulation of an ileal conduit.[1][3][4]
CU was one of the earliest urinary diversions but fell out of favor due to high stomal-stenosis rates. It has experienced a resurgence as tubeless techniques have matured and the elderly bladder-cancer population has grown.[4][5] The EAU bladder cancer guideline calls ureterocutaneostomy the preferred procedure for frail patients and for those with a solitary kidney who need a supravesical diversion, and reports that stoma stenosis and ascending UTI are more frequent than with an intestinal stoma.[19]
Configurations
| Configuration | Description |
|---|---|
| Single-stoma (SSCU) | Both ureters drain through one skin opening. They may be joined side-to-side at the stoma; transposition across the midline does not itself mean transureteroureterostomy. Configuration depends on reach and perfusion.[6] |
| Bilateral-stoma (BSCU) | Each ureter brought to its own stoma on each side of the abdomen[6] |
| Unilateral | A single ureter is exteriorized, for a solitary functioning kidney or for palliation[7][8] |
Urine drains continuously into an external collection device, similar to an ileal conduit, but no intestinal segment is interposed.
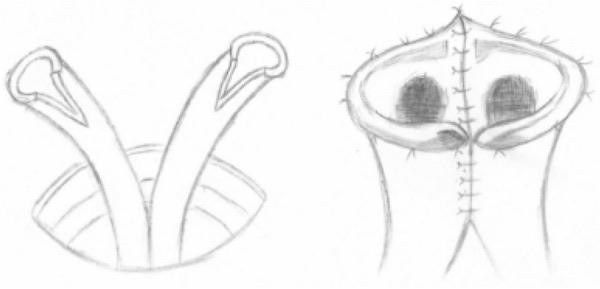
Single-stoma cutaneous ureterostomy. Left, both ureters are pulled out through the abdominal wall and a lateral incision is made on each. Right, the result of the ureteral anastomosis, with the two ureters joined into one stoma. From Fu Z, et al. Eur J Med Res. 2023;28(1):273, Fig. 2 (CC BY).[6]
Indications
CU is considered in:[1][2][3][4][8][7]
- Frail or highly comorbid patients, assessed for clinical fitness beyond chronological age and ASA score
- Limited life expectancy, when minimizing operative time is the priority
- Prior extensive abdominal surgery or radiation that precludes safe bowel mobilization
- Selected palliative diversion when appropriate; percutaneous nephrostomy or ureteral stenting may impose less initial burden than surgery
- Inflammatory bowel disease or short-bowel syndrome when diseased bowel or limited remaining length makes bowel harvest unsuitable; an ICS consensus report for benign reconstruction says ulcerative colitis alone is not an absolute contraindication to bowel use, while Crohn disease calls for assessment of phenotype and affected segments with an IBD team.[24]
- Exceptional anesthesia constraints: an extraperitoneal regional-anesthesia approach has been described in selected frail patients with a single functioning kidney after nephroureterectomy.[7]
- Pediatric patients: end CU as a temporizing measure for severe megaureter or hydronephrosis while awaiting reimplantation[9]
Surgical Technique
The aim is reliable low-resistance drainage while preserving ureteral perfusion. A tubeless stoma is desirable, but some patients require long-term stents and exchanges; this possibility belongs in preoperative counseling.
Rodríguez technique (reported adult series, n = 310)[10]
- Transposition of the left ureter above the inferior mesenteric artery
- Mobilization of the ileocecal segment with repositioning above each terminal ureter
- Abdominal-wall hiatus fixation with 4 angle sutures
- Y-V plasty of the ureters with edge-to-edge anastomosis for stomal creation
- Postoperative Double-J stenting. In the 272-patient stent-duration analysis, left obstruction was 4.5% with >3 months versus 13.7% with shorter stenting.[10]
Toyoda technique (Japanese origin, widely used)[11][12]
- Tubeless stoma created by everting ureteral mucosa and suturing to skin
- Yoshimura reported 92/103 renal units (89%) achieving a tubeless condition in 61 patients; 53/103 had no hydronephrosis, while 14 renal units were not evaluated during follow-up.[11]
Modified tubeless techniques
Separate retrospective studies describe different modifications: Li 2023 reported catheter-free renal units of 56/78 (71.8%) versus 89/98 (90.8%)[12]; Kim 2005 reported 26/43 (60.5%) versus 53/59 (89.8%) after adding tunnel stabilization.[13]
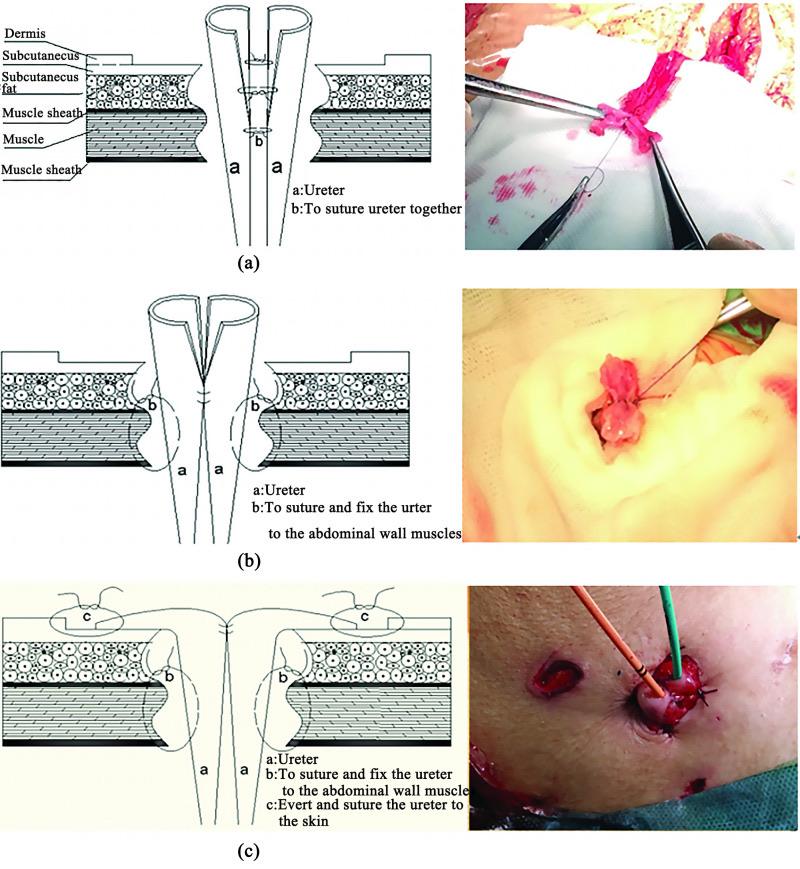
Modified tubeless ureterocutaneostomy, with a schematic (left) and matching operative photograph (right) for each step. (a) A 3 to 4 cm slit is made at each ureteral end and the ureters are conjoined side to side with three interrupted 4-0 sutures, leaving 2 to 3 cm unsutured to form a Y shape. (b) The abdominal-wall tunnel is closed between the anterior and posterior rectus sheaths, and the ureters are fixed to the tunnel with four interrupted 5-0 sutures. (c) The conjoined ureters are everted and sutured to the skin with 4-0 sutures, forming an everted double-nipple stoma. From Li M, et al. Technol Cancer Res Treat. 2023;22:15330338231192906, Figure 1 (CC BY-NC).[12]
Extraperitoneal approach for the very frail[7]
A selected unilateral diversion series reported early bowel recovery and a seven-day hospital stay under combined spinal/epidural anesthesia.
Pediatric temporary ureterostomy
- Ectopic ureter with sepsis or marked dilation. Temporary end ureterostomy has been described for prompt decompression before definitive surgery. Redundant ureter is left intact because it may shorten and the extra length may be needed for later reimplantation; the stoma is placed near the lateral end of a planned future Pfannenstiel incision. Function is reassessed shortly before definitive management by DMSA scan or differential urine collection; nephrostomy or endoscopic incision/stenting are alternatives.[21]
- Severe primary obstructive megaureter, urgent decompression. A small oblique or transverse inguinal incision with blunt muscle splitting into the perivesical space is used to identify the distal ureter; the obliterated umbilical artery may be divided and ligated to help mobilize it. The dilated ureter is brought out as a loop, secured to the fascia with absorbable suture, and the fascia is approximated to the ureter; the ureter is then opened transversely and its edges everted and sutured to the skin, with an optional drainage catheter left for 24–48 hours. These pediatric end and loop cutaneous ureterostomy approaches have been described for severe upper-tract dilation.[9][22] For primary obstructive megaureter, a pediatric consensus review cites stomal stenosis in 8–22% and pyelonephritis in up to 31% after temporary cutaneous ureterostomy; bilateral diversion can defunctionalize the bladder and may impair later capacity.[25]
Comparative Outcomes
Most comparisons are observational and vulnerable to selection differences. In one randomized study enrolling 100 adults aged ≥75 years (50 per arm), delayed complications were reported in 20 single-stoma CU recipients and 6 ileal-conduit recipients. FACT-BL domains did not differ significantly at 12 months.[23] CU often shortens surgery and avoids an intestinal anastomosis.
- Longo 2016. 35 CU versus 35 ileal-conduit patients, all over 75 with substantial comorbidity; CU had shorter surgery/hospitalization and fewer early complications, with overlapping BCI scores.[3]
- Deliveliotis 2005. 29 CU versus 25 conduit patients; intraoperative complications were 13.7% versus 40%, and early surgical complications 24.1% versus 60%.[4]
- Da Costa 2026. 57 CU versus 70 conduit patients, with older and less fit CU patients; recovery favored CU on several measures, but complication/mortality comparisons did not demonstrate a significant difference. This was a study combining prospective and retrospective data.[2]
- Tjiaman 2026 systematic review (11 studies). Ileal conduit was associated with more wound infection (OR 3.02) and early pyelonephritis (OR 3.04), especially versus single-stoma CU. Ileus and wound dehiscence did not differ significantly.[14] The EAU guideline separately reports more ascending UTI after CU than after intestinal stomas.[19]
A SEER study matched 285 patients per group aged ≥80 and detected no significant overall or cancer-specific survival difference.[15]
Complications
Stomal stenosis — the hallmark concern
- In Rodríguez’s 272 evaluable patients, obstruction occurred in 36 (13.2%), including left-only obstruction in 27 (9.9%)[10]
- A 2024 narrative review states that CU stomal stenosis exceeds 50%, but its cited study examined stents or nephrostomy for malignant extrinsic ureteral obstruction, not CU; reported rates vary widely by era, technique and modification.[20]
- Among those 36 obstruction cases, treatment was restenting in 20, revision in 12, and conduit conversion in four.[10]
- Stent duration must balance obstruction risk, infection, encrustation, and the burden of repeated exchanges; the reported duration association was nonrandomized[10]
- Chronic stenting may be needed when a tubeless trial fails or is unsuitable[1]
- Preoperative stoma site marking by a WOC nurse, in supine, sitting and standing positions, targets the soft-tissue contribution to stomal failure (skin folds, beltline, pannus geometry).
Other Complications
- Major perioperative morbidity. The Mayo cohort had 14/31 patients with Clavien ≥3 complications within 30 days. Sepsis affected four patients; 90-day readmission was 10/31.[1]
- Late infection, stones, ischemia, and renal decline remain concerns. In Li's retrospective cohort, stent reinsertion after a tubeless trial was associated with pyelonephritis, stones, and renal deterioration; worse underlying drainage may explain part of those associations.[12]
- Tube dependence. In a 56-patient retrospective comparison, a tube-free trial was performed in 48/56 (86%) patients (22/30 CU and 26/26 conduit); among those trialed, estimated tube-free survival at 12 months after tube removal was 70% for CU versus 76% for conduit, without a significant difference.[16]
Renal function
In a retrospective series of 70 elderly patients (median age 78), median estimated GFR declined from 74.3 to 54.6 mL/min/1.73 m² at six months (p < 0.001).[17] Among the 44 patients still followed at 60 months, median estimated GFR was 46.2 mL/min/1.73 m².[17] Patients requiring chronic catheter or stent placement had significantly higher rates of renal deterioration, pyelonephritis, and urolithiasis.[12]
What Avoiding Bowel Changes
CU avoids urine contact with bowel and the associated diversion-induced intestinal acid absorption, as well as loss of ileal absorptive surface and an intestinal anastomosis. However, patients can still develop acidosis from CKD or illness, nutritional deficiency from other causes, and postoperative ileus or bowel obstruction from cystectomy/abdominal surgery. The comparative meta-analysis did not show a significant ileus reduction.[14]
Quality of Life and Stoma Choice
The 2026 review found better physical QoL with ileal conduit than bilateral-stoma CU, while the comparison with single-stoma CU did not show a significant difference. The 2026 review offered no direct single-stoma versus bilateral CU comparison.[14]
A single appliance can simplify care, but safe reach and perfusion take priority. In Fu’s retrospective study, single-stoma CU had better first stent-removal success and lower costs than bilateral-stoma CU; the groups differed in age and ASA score.[6]
Offer realistic counseling about appliance fit, leakage, body image, possible permanent stents, exchanges, and caregiver support. Neither CU nor ileal conduit guarantees better global QoL or renal preservation.
Long-Term Surveillance
Lifelong monitoring given stenosis, renal-deterioration, and recurrent-infection risks:[17][12]
- Renal function. Establish a postoperative baseline and repeat according to renal/drainage risk; annual long-term review is commonly used when stable
- Upper-tract imaging. Ultrasound or CT for hydronephrosis and stones
- Stoma assessment. Regular evaluation for stenosis; early stenting or revision
- Urine cultures. Obtain for suspected infection or another specific indication; routine cultures of an asymptomatic, colonized diversion should not trigger antibiotics. Follow procedure-specific infection prevention for stent exchanges or mucosa-breaching interventions[18]
- Cancer surveillance. Per primary-disease protocol
- Psychological and practical support. Review adaptation, stoma care, and access to supplies
See Also
References
1. Nabavizadeh R, Rodrigues Pessoa R, Dumbrava MG, et al. "Cutaneous ureterostomy following radical cystectomy for bladder cancer: a contemporary series." Urology. 2023;181:162–166. doi:10.1016/j.urology.2023.08.018
2. da Costa RMM, Pereira do Nascimento LA, Silva TA, Panhoca R, Sadi MV. "Comparison between cutaneous ureterostomy and the ileal conduit in patients with urothelial bladder carcinoma undergoing radical cystectomy: expanding eligibility for the gold standard treatment." Urol Oncol. 2026;44(5):111031. doi:10.1016/j.urolonc.2026.111031
3. Longo N, Imbimbo C, Fusco F, et al. "Complications and quality of life in elderly patients with several comorbidities undergoing cutaneous ureterostomy with single stoma or ileal conduit after radical cystectomy." BJU Int. 2016;118(4):521–526. doi:10.1111/bju.13462
4. Deliveliotis C, Papatsoris A, Chrisofos M, et al. "Urinary diversion in high-risk elderly patients: modified cutaneous ureterostomy or ileal conduit?" Urology. 2005;66(2):299–304. doi:10.1016/j.urology.2005.03.031
5. Zingg EJ, Bornet B, Bishop MC. "Urinary diversion in the elderly patient." Eur Urol. 1980;6(6):347–351. doi:10.1159/000473370
6. Fu Z, Tian Z, Chen Y, et al. "Analysis of the efficacy of a single subumbilical stoma for bilateral cutaneous ureterostomy after radical cystectomy." Eur J Med Res. 2023;28(1):273. doi:10.1186/s40001-023-01250-z
7. Murali A, Philips MR, Patidar S, et al. "Total extra-peritoneal approach to radical cystectomy with ureterostomy: a novel technique for the elderly and frail." Urol Oncol. 2025;43(1):61.e19–61.e28. doi:10.1016/j.urolonc.2024.10.008
8. Kearney GP, Docimo SG, Doyle CJ, Mahoney EM. "Cutaneous ureterostomy in adults." Urology. 1992;40(1):1–6. doi:10.1016/0090-4295(92)90426-w
9. Kitchens DM, DeFoor W, Minevich E, et al. "End cutaneous ureterostomy for the management of severe hydronephrosis." J Urol. 2007;177(4):1501–1504. doi:10.1016/j.juro.2006.11.076
10. Rodríguez AR, Lockhart A, King J, et al. "Cutaneous ureterostomy technique for adults and effects of ureteral stenting: an alternative to the ileal conduit." J Urol. 2011;186(5):1939–1943. doi:10.1016/j.juro.2011.07.032
11. Yoshimura K, Maekawa S, Ichioka K, et al. Tubeless cutaneous ureterostomy: the Toyoda method revisited. J Urol. 2001;165(3):785–788. PubMed. doi:10.1016/s0022-5347(05)66526-3
12. Li M, Fu X, Zu X, Chen J, Chen M. "Modified tubeless ureterocutaneostomy in high-risk patients after radical cystectomy and its long-term clinical outcomes." Technol Cancer Res Treat. 2023;22:15330338231192906. doi:10.1177/15330338231192906
13. Kim CJ, Wakabayashi Y, Sakano Y, et al. "Simple technique for improving tubeless cutaneous ureterostomy." Urology. 2005;65(6):1221–1225. doi:10.1016/j.urology.2004.12.009
14. Tjiaman MP, Zaidan MZ, Ausath ZF, et al. "Quality of life and postoperative complications of single- or bilateral-stoma cutaneous ureterostomy compared to ileal conduit after radical cystectomy: a systematic review and meta-analysis." Urology. 2026;207:287–292. doi:10.1016/j.urology.2025.09.034
15. Huang S, Chen H, Li T, et al. "Comparison of survival in elderly patients treated with uretero-cutaneostomy or ileal conduit after radical cystectomy." BMC Geriatr. 2021;21(1):49. doi:10.1186/s12877-020-01861-9
16. Thakker PU, Refugia JM, Wolff D, et al. "Ileal conduit versus cutaneous ureterostomy after open radical cystectomy: comparison of 90-day morbidity and tube dependence at intermediate term follow-up." J Clin Med. 2024;13(3):911. doi:10.3390/jcm13030911
17. Creta M, Fusco F, La Rocca R, et al. "Short- and long-term evaluation of renal function after radical cystectomy and cutaneous ureterostomy in high-risk patients." J Clin Med. 2020;9(7):E2191. doi:10.3390/jcm9072191
18. European Association of Urology. EAU Guidelines on Urological Infections. 2026. Asymptomatic bacteriuria in reconstructed tracts, stents and before urological interventions. Guideline.
19. European Association of Urology. EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer. 2026. Section 6.7.5.a.1, Ureterocutaneostomy. Guideline.
20. Barone B, Napolitano L, Reccia P, et al. "Advances in Urinary Diversion: From Cutaneous Ureterostomy to Orthotopic Neobladder Reconstruction — A Comprehensive Review." J Pers Med. 2024;14(4):392. doi:10.3390/jpm14040392
21. Stanasel I, Peters CA. Ectopic Ureter, Ureterocele, and Ureteral Anomalies. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:1038-1063.
22. Rabinowitz R, Barkin M, Schillinger JF, Jeffs RD, Cook GT. "Surgical Treatment of the Massively Dilated Ureter in Children. Part I. Management by Cutaneous Ureterostomy." J Urol. 1977;117(5):658–662. doi:10.1016/s0022-5347(17)58576-6
23. Moeen AM, Faragallah MA, Zarzour MA, Elbehairy AA, Behnsawy HM. "Ileal conduit versus single stoma uretero-cutanoustomy after radical cystectomy in patients ≥75 years; which technique is better? a prospective randomized comparative study." Int Urol Nephrol. 2023;55(7):1719–1726. doi:10.1007/s11255-023-03609-x
24. Sihra N, Williams A, Emmanuel A, et al. "Implications of Inflammatory Bowel Disease for reconstructive surgery in non-malignant urinary tract dysfunction: An International Continence Society working group report." Continence. 2022;1:100018. doi:10.1016/j.cont.2022.100018
25. Farrugia MK, Hitchcock R, Radford A, et al. "British Association of Paediatric Urologists consensus statement on the management of the primary obstructive megaureter." J Pediatr Urol. 2014;10(1):26–33. doi:10.1016/j.jpurol.2013.09.018