Ileal Conduit
The ileal conduit is the most commonly performed urinary diversion following radical cystectomy, although its use varies by population and center.[1][2] It is an incontinent diversion in which a 15–20 cm segment of distal ileum serves as a passive conduit from the ureters to an external collection device via an abdominal stoma.[3][51] It is intended to drain continuously, rather than act as a storage reservoir; kinking or obstruction can still impair drainage.
Popularized by Eugene Bricker after World War II, it became the standard of care for incontinent urinary diversion in the 1950s once effective adhesive stoma appliances became available, and has remained the most frequently performed urinary diversion after radical cystectomy worldwide for more than 70 years.[1][4]
Indications
Ileal conduit is an established option after cystectomy for cancer and for selected refractory benign lower-tract disease.[5][6] Choice depends on comorbidity, renal/hepatic function, available bowel, support for stoma care, and patient preference.[5][6]
It is often suitable when a continent reconstruction's catheterization or training demands are impractical. In multiple sclerosis, a French multicenter retrospective cohort of 211 selected patients reported improved urinary quality of life and fewer UTI hospitalizations after diversion, with early complications in 42%; this remains major surgery.[7]
Severe renal or hepatic impairment limits continent bowel reservoirs; creatinine >2 mg/dL alone does not determine diversion choice. Ileal conduit still carries an absorptive/metabolic burden. Active bowel disease, short bowel, or damaged/irradiated ileum may preclude use of the proposed segment and require another reconstruction. Cutaneous ureterostomy may be considered in frail patients when avoiding bowel is a priority.[6]
Surgical Technique
Key steps
- Isolate a 15–20 cm ileal segment while preserving the terminal 15 cm when feasible and maintaining its mesenteric blood supply.[28][51]
- Restore bowel continuity (ileoileal anastomosis).
- Plan a tension-free route between the left ureter and right-sided conduit; the conventional route passes beneath the sigmoid colon through its mesentery and should avoid angulation at the window. When left-ureter reach is limited, a described alternative routes the proximal conduit leftward beneath the mesosigmoid without extensive ureteral dissection. Construct the ureteroileal anastomosis (Bricker or Wallace; see below).[1][15]
- Mature the stoma through the abdominal wall, typically in the right lower quadrant. See Stoma Site Marking for the preoperative WOC-nurse marking workflow.
In an obese patient with a short, bulky mesentery and a thick abdominal wall, a Turnbull-type loop stoma has been described as an alternative to an end-loop nipple stoma: the conduit end is left closed, the loop is brought through the stoma without tension or twist, opened transversely about 3 cm from the closed end, and matured over a temporary supporting rod with 2–3 cm of bowel exteriorized without tension.[34]
Ureteroileal anastomosis — Bricker vs Wallace
| Technique | Construction | Practical considerations |
|---|---|---|
| Bricker | Separate end-to-side ureteral anastomoses to the conduit | Allows separate treatment of unequal ureteral lengths. |
| Wallace | Spatulated ureters joined into a shared plate and then to the conduit | A stricture at the common outlet can affect both upper tracts. |
Bricker and Wallace differ in construction; the shared Wallace outlet can affect both upper tracts, but the techniques have no universal stricture-risk ranking. A 2025 meta-analysis of 14 studies (1,903 patients) found no significant overall stricture difference, but its ileal-conduit subgroup reported lower stricture odds with Wallace (OR 0.35, 95% CI 0.19–0.64).[44] Comparative cohorts have different selection and follow-up, and results conflict.[8][9][10]
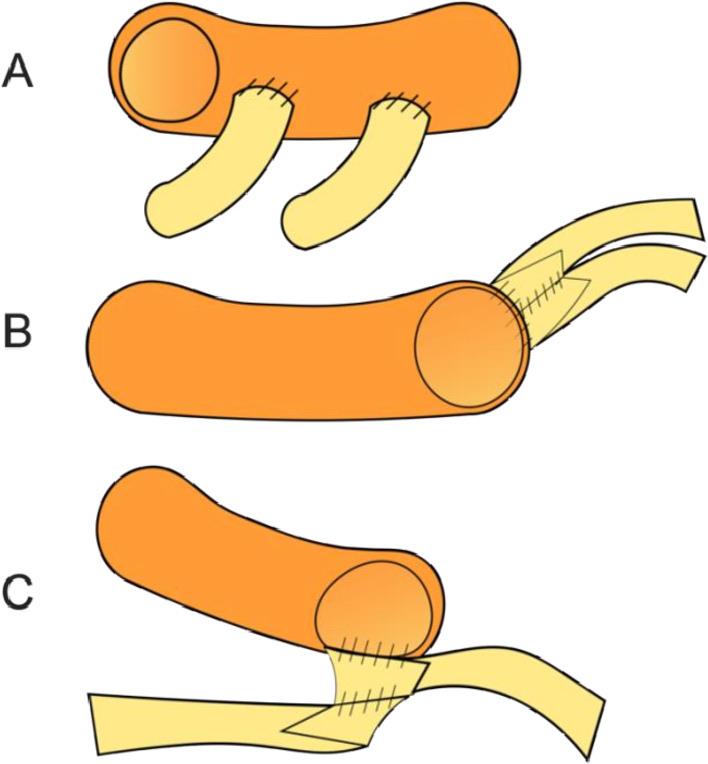
Ureteroenteric anastomoses for the ileal conduit: (A) Bricker, each ureter joined separately end-to-side to the conduit; (B) Wallace I, spatulated ureters joined head-to-head into a single plate; (C) Wallace II, ureters joined head-to-tail. A shared Wallace plate means one anastomotic stricture can obstruct both kidneys. From Martínez-Gómez C, et al. Int J Gynecol Cancer. 2021;31(1):1-10, Figure 2 (CC BY-NC 4.0).[41]
A 96-patient retrospective robotic cohort found no statistically significant differences in strictures, complications, or readmissions.[11] In the full-text Results of a single-center series of 140 patients (75 Bricker, 65 Wallace) without prior radiotherapy or neoadjuvant chemotherapy, strictures occurred in 19/75 (25.3%) versus 5/65 (7.7%; p = 0.001).[32] One surgeon performed each technique, and follow-up was longer after Bricker (36.5 versus 17 months).[32]
The Ren 2025 Bricker–Wallace comparison carries a June 2026 publisher expression of concern about reference reliability, which is not a retraction.[12]
Distal Ureter: Perfusion and Reach
In the retrospective Das 2024 cohort (366 patients; 711 anastomoses), 35 patients developed strictures affecting 40 anastomoses. Greater distal resection was associated with lower stricture odds, adjusted OR 0.73 (95% CI 0.58–0.92). Median distal ureteral resection lengths were 2.3 versus 1.65 cm in non-stricturing versus stricturing anastomoses.[13]
An earlier 463-patient cohort found no independent association between resection length and stricture. Preserve adventitial blood supply and construct a well-perfused, tension-free anastomosis; do not sacrifice reach simply to meet a length target. Perfusion assessment supplements, rather than replaces, those principles.[14][15] In the 2025 MOSAIC randomized trial of patients scheduled for robot-assisted cystectomy (303 randomized; 297 assessed for stricture), left-sided ureteroenteric strictures occurred in 6/148 (4.1%) with retrosigmoid conduit transposition versus 10/149 (6.7%) with conventional left-ureter routing at median follow-up of about 754 days (P = .31); a reduction was not demonstrated, and patients with prior pelvic radiotherapy or major bowel surgery were excluded.[50]
Core technical principles (irrespective of technique)
- Spatulate the distal end of each ureter to widen the anastomotic lumen.[1][9]
- Minimize periureteral dissection. Preserve adventitial blood supply; never strip the ureter.[15]
- Construct a tension-free mucosa-to-mucosa anastomosis with fine absorbable suture (4-0 or 5-0 polyglactin), running or interrupted.[1][9]
- Temporary ureteral stents are commonly used across the anastomoses. A removal interval of 10–14 days has been described; device and timing depend on drainage, healing, and the operative protocol.[1]
- For a ureter with a history of pelvic radiation, excising additional proximal ureteral tissue before the anastomosis has been described as a way to reduce stricture risk.[35]
Positioning, Catheter and Drain Management
Conduit construction follows cystectomy or another extirpative procedure in the same operation. Open construction is generally supine; robotic cystectomy may use low lithotomy and steep Trendelenburg for extirpation, but the tilt can change for diversion: one extracorporeal approach releases it after undocking, and one intracorporeal technique reduces it from 30° to 10° for bowel work.[48][49] Stoma-site marking is done preoperatively regardless of approach; see Stoma Site Marking. For radical cystectomy with urinary diversion, the EAU 2026 guideline recommends against preoperative bowel preparation .[6]
The urethral Foley drains the native bladder until urethral division during cystectomy; after bladder removal, pelvic drainage is provided by a separate drain or, in some protocols, a newly placed transurethral catheter.[45] A stoma appliance collects conduit urine. At the conduit itself, temporary ureteral stents and a closed suction pelvic drain are typical. Traditional practice stented the ureteroileal anastomoses and kept a pelvic drain for roughly two weeks, while some centers now remove stents earlier. In a 178-patient single-center cohort excluding prior abdominal or pelvic radiation and continent diversion, stent duration fell from about 15.5 to 5 days; no stricture difference was detected at a median 9.8 months, while 90-day readmissions and total UTIs were lower in the early-removal group.[29] In a separate retrospective ileal-conduit cohort of 228 patients, 19% had stents removed by postoperative day 5, with antibiotic exposure of about 8 versus 22 days.[30] No statistically significant difference was detected in 30-day symptomatic UTI (9.3% versus 10.8%), drain-creatinine-defined leak (2.3% versus 2.2%) or readmission (9.3% versus 11.4%).[30] No single stent or drain duration is universal; use drain output/creatinine and imaging, not the calendar alone, to guide removal.[29][30] These duration comparisons all stented every patient; the separate question of stenting versus no stenting at all has its own evidence.[29][30] A systematic review (11 studies) reported pooled single-proportion ureteroileal anastomotic leak rates of 1% in stented and 2% in unstented patients; a comparative meta-analysis of four studies found no significant difference between groups.[33] Comparative meta-analysis of 4 studies found a numerically higher stricture incidence with stenting that did not reach significance (OR 1.64, 95% CI 0.88–3.05, p = 0.12; pooled single-proportion stricture rate 7% stented versus 3% unstented), so stenting is not established to prevent leak or stricture at this anastomosis.[33]
VTE Prophylaxis
For patients undergoing radical cystectomy, including those receiving an ileal conduit, the AUA/ASCO/SUO 2024 guideline states that perioperative pharmacologic VTE prophylaxis should be given . Its discussion recommends combined mechanical and pharmacologic prophylaxis and says up to four weeks of postoperative coverage may be beneficial, although the optimal duration is undefined.[28] See the VTE Prophylaxis hub for dosing, timing, and the wider extended-prophylaxis evidence for major pelvic cancer surgery. This recommendation is specific to the cancer operation; it does not automatically apply to ileal conduit performed for benign indications, where the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on that page applies instead.
Complications
Complications accumulate with time. A positive urinalysis or culture is common after ileal conduit and does not alone warrant antimicrobial treatment; assess symptoms and upper-tract obstruction.[42] Before endourologic procedures associated with mucosal trauma, IDSA recommends screening for and treating asymptomatic bacteriuria .[43] In a historical series of 131 patients surviving at least five years, 87 (66%) had late conduit-related complications; among those surviving beyond 15 years, the reported rate was 94%.[16]
Early (within 90 days)[1]
- Urine leak / urinoma
- Urinary obstruction
- Postoperative fluid collections (hematoma, lymphocele, abscess)
- Fistula formation
- Wound infection
Late[1][16][17]
| Complication | Rate |
|---|---|
| Ureteroileal anastomotic stricture | 7.7% (5/65 Wallace) versus 25.3% (19/75 Bricker) in one retrospective comparison with unequal follow-up.[32] |
| Stomal complications (including parastomal hernia and stenosis) | 15.4% (163/1,057; mixed ileal/colonic conduits), including parastomal hernia in 13.9% (147/1,057); 24% (32/131) among five-year ileal-conduit survivors in a separate cohort.[16][17] |
| Renal/upper-tract functional or morphological complications | 20.2% (213/1,057; mixed ileal/colonic conduits) and 27% (35/131; five-year ileal-conduit survivors); definitions vary.[16][17] |
| Urolithiasis | 9% (12/131) among survivors of at least five years in one ileal-conduit cohort; 38% only among those surviving >15 years. A separate mixed ileal/colonic conduit cohort reported 15.3% (162/1,057).[16][17] |
| Symptomatic UTI / pyelonephritis | 23% (30/131 five-year ileal-conduit survivors).[16] |
| Bowel complications | 20.3% (215/1,057; mixed ileal/colonic conduits) and 24% (32/131; five-year ileal-conduit survivors).[16][17] |
| Ureteroarterial fistula | Potentially life-threatening. Intermittent or gross hematuria via the urostomy in a patient with a chronic ureteral stent or prior pelvic irradiation should raise suspicion before stent exchange; manipulation may trigger massive bleeding and warrants urgent urologic, vascular, and interventional-radiology assessment.[47] |
In the Mayo Clinic series (Shimko 2011, n = 1,057; ileal or colonic conduits), 643 patients (60.8%) had diversion-related complications. The reported mean of 2.3 complications was among those 643 patients, not all 1,057. Distribution: bowel 20.3%, renal 20.2%, infectious 16.5%, stomal 15.4%, urolithiasis 15.3%.[17]
Bowel anastomotic leak and enterocutaneous fistula
Leak at the ileoileal bowel anastomosis has been reported in about 1–5% of ileal-conduit patients; cited risk factors include poor nutrition, ischemia, prior intestinal surgery, chemotherapy or radiation, steroid use, anastomotic tension, and distal obstruction. A severe leak may require exploration with bowel resection and re-anastomosis, with proximal fecal diversion if needed. Fistulae after diversion are uncommon (<5%) and include enterocutaneous fistula, which can present like a wound infection around postoperative days 4–7 and is managed initially with infection and source control, drainage, fluid/electrolyte replacement, and nutritional support; spontaneous closure after six weeks of adequate nutrition without infection is considered unlikely, though ongoing drainage volume, sepsis risk, and the option of long-term nonoperative care still guide further management.[35] Acid-suppressive therapy and, in selected cases, a somatostatin analog to reduce enteric secretions have been described as adjuncts for enterocutaneous fistula.[37] The cited evidence for somatostatin comes from small-bowel fistula series; a conduit-specific comparison was not reported.[37]
Conduit and stomal necrosis
Progressive darkening and retraction of the conduit at the abdominal-wall opening should raise concern for ischemic necrosis, distinct from the transient maroon, dusky venous congestion and edema that is common above the fascia in the first several days. Viability can be assessed above and below the fascia by endoscopy, by bedside transillumination of the lumen through a transparent appliance or a test tube passed into the stoma, or by flexible cystoscopy if the bedside assessment is indeterminate; superficial mucosal injury may simply slough with improved stoma care, but confirmed full-thickness necrosis is a surgical emergency requiring urgent exploration, inspection of the conduit and adjacent small bowel, and excision and replacement of nonviable bowel. Sepsis, metabolic acidosis, hyperphosphatemia, or shock can accompany extensive nonviable bowel. True necrosis of the conduit itself is rare; more often the finding is limited to the superficial stoma above the fascia.[35]
Stomal variceal bleeding
Bleeding stomal varices are a rare late complication, most often associated with portal hypertension from hepatic dysfunction, typically arising within a few years of surgery. Local compression, suture ligation, or mucocutaneous disconnection may not achieve durable control while portal pressure remains elevated; case reports describe successful transjugular intrahepatic portosystemic shunt (TIPS) or angiographic embolization with sclerosis for refractory bleeding, though TIPS itself carries a substantial risk of hepatic encephalopathy in patients with more advanced liver disease. A patient with a bleeding stoma and known or suspected portal hypertension warrants hepatology/interventional-radiology involvement rather than repeated local measures alone.[38][39]
Metabolic Consequences
Intestinal diversions cause characteristic metabolic derangements:[18][19]
- Hyperchloremic metabolic acidosis results from ammonium chloride absorption and bicarbonate wasting and may require oral bicarbonate supplementation.
- The risk of vitamin B12 deficiency depends on the ileal segment used and underlying absorption. Terminal ileum is preserved where feasible; the AUA/ASCO/SUO guideline discussion notes that preserving the most distal 15 cm of ileum in a conduit can reduce problems with B12, fat-soluble vitamin and bile salt absorption. The EAU bladder cancer guideline states that B12 should be measured annually after cystectomy with bowel diversion (guideline text, not a graded recommendation).[20] The AUA/ASCO/SUO guideline advises checking B12 in follow-up because deficiency risk is increased after resection of more than 60 cm of ileum or use of the terminal ileum.[28]
- One retrospective comparative cohort reported metabolic abnormalities in 21% of its ileal-conduit group.[19]
For full pharmacologic management see Vitamin B12 supplementation, Urinary acidifiers & alkalinizers, and Mucus management.
Quality of Life — vs Other Diversions
Quality-of-life comparisons between ileal conduit and neobladder depend on the domain and the population:
- Meta-analyses generally show marginally better QoL with neobladder for physical, role and social functioning and global health, but neobladder patients experience more urinary symptoms (incontinence, need for self-cath).[21][22][23]
- When matched for age and comorbidities, global health is often similar; ileal-conduit patients report better long-term urinary function.[23][24][25]
- In women, a meta-analysis of four observational studies (283 patients) found no significant overall QoL difference, with wide confidence intervals.[26]
- Patient acceptance can be good, including in older patients, but counseling should address appliance care, leakage, body image, and available support.[5]
- In a prospective single-center cohort of 411 patients (205 ileal conduit, 206 continent diversion) followed for 2 years, sexual function was low before surgery with limited recovery across both diversion types, while body image scores worsened after surgery specifically among ileal-conduit patients (about a 10-point decline on a 100-point scale), a pattern not seen with continent diversion.[36]
Comparison with Other Diversions
| Feature | Ileal conduit | Orthotopic neobladder | Continent cutaneous reservoir |
|---|---|---|---|
| Emptying | Continuous drainage to an appliance | Timed urethral emptying; catheterization may be needed[40] | Scheduled catheterization through a stoma |
| Main practical burden | Appliance/stoma care | Continence training, nocturnal leakage, retention[40] | Reliable lifelong catheter access and mucus care |
| Shared concerns | Renal deterioration, obstruction, infection, stones, metabolic effects | Same, plus storage/emptying problems | Same, plus channel/continence-mechanism problems |
There is no randomized comparison establishing one diversion as best overall. Differences in age, comorbidity, selection, and follow-up complicate renal and quality-of-life comparisons.[23][24][25][6] In the 281-patient Nieuwenhuijzen cohort, late complications were lower after ileal conduit, largely because of fewer uncomplicated UTIs; late major complications did not differ significantly.[19]
Long-Term Surveillance
Lifelong surveillance is needed given the high cumulative complication burden:[16][27]
- Renal function (serum creatinine, eGFR)
- Upper-tract imaging for hydronephrosis and urolithiasis
- Annual serum vitamin B12 under EAU guidance.[20] NCCN post-cystectomy follow-up specifies annual testing after the first year based on clinical judgment (category 2A).[40]
- Metabolic panel for acidosis
- Stoma assessment by a wound or ostomy nurse
- Cancer surveillance per primary-disease protocol
In a Medicare claims cohort of 1,565 patients undergoing several types of urinary diversion, the estimated risk of renal failure/impairment approached 16% by five years. Obstruction and renal impairment were more common in the conduit group.[27] Functional follow-up remains necessary even after oncologic surveillance becomes less frequent.
Loopography
Loopography (conduitography) is the contrast-study analog of a VCUG for a urinary conduit. Indications include upper-tract evaluation after diversion (hematuria, obstruction, renal insufficiency), assessment of the bowel segment itself (obstruction, leak, infection, pain), and, in a patient who cannot safely receive IV contrast, a low-systemic-absorption option for upper-tract evaluation. Technique: obtain a plain film; pass a 14–16 Fr Foley through the stoma with the balloon deflated, inflate it within the conduit deep to the fascia, and apply gentle traction to limit outflow. Instill contrast under fluoroscopy for frontal and oblique films; a refluxing anastomosis may opacify the upper tracts. Obtain a post-drainage film; the catheter may be removed before drainage when evaluating conduit obstruction.[31][46] Because most intestinal diversions are colonized, periprocedural antibiotics should be considered.[31]
See Also
- Urinary Diversion landing
- Urinary Diversion Principles
- Stoma Site Marking
- Colon Conduit
- Urethrectomy: oncologic indications and implications for orthotopic reconstruction
- On WHITWIKI, the sister site for GU oncology: Ileal Conduit and Stoma, Diversion Complications and Follow-up.
Videos
References
1. Kobayashi K, Goel A, Coelho MP, et al. "Complications of ileal conduits after radical cystectomy: interventional radiologic management." Radiographics. 2021;41(1):249–267. doi:10.1148/rg.2021200067
2. Lowrance WT, Rumohr JA, Clark PE, et al. "Urinary diversion trends at a high-volume single American tertiary care center." J Urol. 2009;182(5):2369–2374. doi:10.1016/j.juro.2009.07.026
3. Khosla AA, Mendhiratta N, Jatwani K. "Urinary diversion after cystectomy for bladder cancer." JAMA Oncol. 2025. doi:10.1001/jamaoncol.2025.3644
4. Omar K, Khan NS, Shariat SF, et al. "Urinary diversion." In: Blandy's Urology, 3rd Edition. 2019;Chapter 22. ISBN: 9781118863374. doi:10.1002/9781118863343.ch22
5. Siddiqui KM, Izawa JI. "Ileal conduit: standard urinary diversion for elderly patients undergoing radical cystectomy." World J Urol. 2016;34(1):19–24. doi:10.1007/s00345-015-1706-1
6. European Association of Urology. EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer. 2026. Urinary diversion and patient selection. Disease management.
7. Chkir S, Michel F, Akakpo W, et al. "Non-continent urinary diversion (ileal conduit) as salvage therapy in patients with refractory lower urinary tract dysfunctions due to multiple sclerosis." Urology. 2022;168:216–221. doi:10.1016/j.urology.2022.06.014
8. Kouba E, Sands M, Lentz A, Wallen E, Pruthi RS. "A comparison of the Bricker versus Wallace ureteroileal anastomosis in patients undergoing urinary diversion for bladder cancer." J Urol. 2007;178(3 Pt 1):945–948. doi:10.1016/j.juro.2007.05.030
9. Liu L, Chen M, Li Y, et al. "Technique selection of Bricker or Wallace ureteroileal anastomosis in ileal conduit urinary diversion: a strategy based on patient characteristics." Ann Surg Oncol. 2014;21(8):2808–2812. doi:10.1245/s10434-014-3591-z
10. Krafft U, Mahmoud O, Hess J, et al. "Comparative analysis of Bricker versus Wallace ureteroenteric anastomosis and identification of predictors for postoperative ureteroenteric stricture." Langenbecks Arch Surg. 2022;407(3):1233–1240. doi:10.1007/s00423-021-02413-4
11. Carreno GL, Fu H, Messer J. "Comparison of perioperative outcomes between Bricker and Wallace anastomosis techniques in robotic-assisted radical cystectomy with intracorporeal diversion." World J Urol. 2025;43(1):415. doi:10.1007/s00345-025-05781-4
12. Frontiers Editorial Office. Expression of concern: comparative analysis of ureteroileal anastomotic stricture rates: Bricker versus Wallace techniques in ileal conduit urinary diversion—a single-surgeon study with BMI-matched design and long-term follow-up excluding cancer recurrence bias. Front Oncol. 2026;16:1912670. Published June 30, 2026. doi:10.3389/fonc.2026.1912670. Publisher notice in PMC.
13. Das A, Zeng E, Risk M, et al. Shorter ureters lead to fewer strictures following cystectomy and urinary diversion. Urology. 2024;184:272-277. doi:10.1016/j.urology.2023.12.005
14. Richards KA, Cohn JA, Large MC, et al. The effect of length of ureteral resection on benign ureterointestinal stricture rate in ileal conduit or ileal neobladder urinary diversion following radical cystectomy. Urol Oncol. 2015;33(2):65.e1-8. doi:10.1016/j.urolonc.2014.05.015
15. Li Y, Zhuang Q, Hu Z, et al. A modified ureteroileal anastomosis technique for Bricker urinary diversion. Urology. 2011;78(5):1191-5. doi:10.1016/j.urology.2011.07.001
16. Madersbacher S, Schmidt J, Eberle JM, et al. "Long-term outcome of ileal conduit diversion." J Urol. 2003;169(3):985–990. doi:10.1097/01.ju.0000051462.45388.14
17. Shimko MS, Tollefson MK, Umbreit EC, et al. "Long-term complications of conduit urinary diversion." J Urol. 2011;185(2):562–567. doi:10.1016/j.juro.2010.09.096
18. Lenis AT, Lec PM, Chamie K, Mshs MD. "Bladder cancer: a review." JAMA. 2020;324(19):1980–1991. doi:10.1001/jama.2020.17598
19. Nieuwenhuijzen JA, de Vries RR, Bex A, et al. "Urinary diversions after cystectomy: the association of clinical factors, complications and functional results of four different diversions." Eur Urol. 2008;53(4):834–842. doi:10.1016/j.eururo.2007.09.008
20. European Association of Urology. EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer. 2026. Functional follow-up after urinary diversion. Follow-up.
21. Shi H, Yu H, Bellmunt J, et al. "Comparison of health-related quality of life (HRQoL) between ileal conduit diversion and orthotopic neobladder based on validated questionnaires: a systematic review and meta-analysis." Qual Life Res. 2018;27(11):2759–2775. doi:10.1007/s11136-018-1902-8
22. Cerruto MA, D'Elia C, Siracusano S, et al. "Systematic review and meta-analysis of non-RCTs on health-related quality of life after radical cystectomy using validated questionnaires: better results with orthotopic neobladder versus ileal conduit." Eur J Surg Oncol. 2016;42(3):343–360. doi:10.1016/j.ejso.2015.10.001
23. Cerruto MA, D'Elia C, Siracusano S, et al. "Health-related quality of life after radical cystectomy: a cross-sectional study with matched-pair analysis on ileal conduit vs ileal orthotopic neobladder diversion." Urology. 2017;108:82–89. doi:10.1016/j.urology.2017.06.022
24. Kern SQ, Speir RW, Tong Y, et al. "Longitudinal health-related quality of life after open radical cystectomy: comparison of ileal conduit, Indiana pouch, and orthotopic neobladder." Urology. 2021;152:184–189. doi:10.1016/j.urology.2020.12.036
25. Gellhaus PT, Cary C, Kaimakliotis HZ, et al. "Long-term health-related quality of life outcomes following radical cystectomy." Urology. 2017;106:82–86. doi:10.1016/j.urology.2017.03.053
26. Xing W, Zeng S, Xu Z, Xing S, Liu Q. "Comparison of health-related quality of life between ileal conduit diversion and orthotopic neobladder in women: a meta-analysis." Front Oncol. 2022;12:862884. doi:10.3389/fonc.2022.862884
27. Gilbert SM, Lai J, Saigal CS, Gore JL. "Downstream complications following urinary diversion." J Urol. 2013;190(3):916–922. doi:10.1016/j.juro.2013.03.026
28. Holzbeierlein J, Bixler BR, Buckley DI, et al. Treatment of Non-Metastatic Muscle-Invasive Bladder Cancer: AUA/ASCO/SUO Guideline (2017; Amended 2020, 2024). J Urol. 2024;212(1):3-10. doi:10.1097/JU.0000000000003981
29. Beano H, He J, Hensel C, et al. Safety of decreasing ureteral stent duration following radical cystectomy. World J Urol. 2021;39(2):473-479. doi:10.1007/s00345-020-03191-2
30. Wenzel JL, Chou WH, Robinson EJ, et al. Evolution toward early stent removal and reduced antibiotic prophylaxis post-cystectomy. Can J Urol. 2026;33(3):649-656. doi:10.32604/cju.2025.071079
31. Bishoff JT, Rastinehad AR. "Urinary Tract Imaging: Basic Principles of CT, MRI, and Plain Film Imaging." In: Campbell-Walsh Urology. 12th ed. Elsevier; 2021:28-67.e5.
32. Christoph F, Herrmann F, Werthemann P, Janik T, Schostak M, Klopf C, Weikert S. Ureteroenteric strictures: a single center experience comparing Bricker versus Wallace ureteroileal anastomosis in patients after urinary diversion for bladder cancer. BMC Urol. 2019;19(1):100. doi:10.1186/s12894-019-0529-6
33. Peng YL, Ning K, Wu ZS, et al. Ureteral stents cannot decrease the incidence of ureteroileal anastomotic stricture and leakage: A systematic review and meta-analysis. Int J Surg. 2021;93:106058. doi:10.1016/j.ijsu.2021.106058
34. Patel AR, Fergany A. Supravesical Urinary Diversion: Conduits. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:358-368.
35. Donahue T, Chu C. Complications of Ileal Conduit Urinary Diversion: A Comprehensive Review. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:157-163.
36. Clements MB, Atkinson TM, Dalbagni GM, et al. "Health-related Quality of Life for Patients Undergoing Radical Cystectomy: Results of a Large Prospective Cohort." Eur Urol. 2022;81(3):294-304. doi:10.1016/j.eururo.2021.09.018
37. Donahue T, Bochner BH. Complications of Ileal Conduit Diversion. In: Daneshmand S, ed. Urinary Diversion. Springer; 2017:63-79. doi:10.1007/978-3-319-52186-2_6
38. Medina CA, Caridi JG, Wajsman Z. "Massive Bleeding from Ileal Conduit Peristomal Varices: Successful Treatment with the Transjugular Intrahepatic Portosystemic Shunt." J Urol. 1998;159(1):200-201. doi:10.1016/s0022-5347(01)64058-8
39. Valaydon Z, Desmond P. "Treatment of Refractory Stomal Variceal Haemorrhage with Embolisation and Sclerosis." Intern Med J. 2015;45(2):214-217. doi:10.1111/imj.12662
40. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Bladder Cancer. Version 3.2026. August 6, 2026. BL-E 3–4 of 6; Discussion MS-18. Guideline.
41. Martínez-Gómez C, Angeles MA, Martinez A, Malavaud B, Ferron G. "Urinary diversion after pelvic exenteration for gynecologic malignancies." Int J Gynecol Cancer. 2021;31(1):1-10. doi:10.1136/ijgc-2020-002015
42. Magistro G, Zimmermann L, Bischoff R, et al. "The natural course of urinalysis after urinary diversion." World J Urol. 2021;39(5):1559–1567. doi:10.1007/s00345-020-03355-0
43. Nicolle LE, Gupta K, Bradley SF, et al. "Clinical Practice Guideline for the Management of Asymptomatic Bacteriuria: 2019 Update by the Infectious Diseases Society of America." Clin Infect Dis. 2019;68(10):e83–e110. doi:10.1093/cid/ciy1121
44. de Araújo Neto FJ, de Sousa FRC, Aggensteiner CR, et al. "New Evidence on an old Question: a Meta-Analysis of Wallace versus Bricker Anastomoses." Int Braz J Urol. 2025;51(6):e20250100. doi:10.1590/S1677-5538.IBJU.2025.0100
45. Tan WS, Lamb BW, Sridhar A, Briggs TP, Kelly JD. "A comprehensive guide to perioperative management and operative technique for robotic cystectomy with intracorporeal urinary diversion." Urologia. 2017;84(2):71-78. doi:10.5301/uj.5000224
46. Amis ES Jr, Cronan JJ, Pfister RC. "Filling defects in small bowel urinary conduits." AJR Am J Roentgenol. 1981;137(4):787-792. doi:10.2214/ajr.137.4.787
47. Matsunaga F, Dambaeva A, Ponsky LE, Kashyap VS, Tavri S. "Systematic review of the management of ureteroarterial fistulas after ileal conduit urinary diversion." AJR Am J Roentgenol. 2021;216(6):1452-1461. doi:10.2214/AJR.20.23132
48. Iwamoto H, Morizane S, Yamamoto A, et al. "Utility of the HYBRID Method Incorporating the Advantages of Both Extracorporeal and Intracorporeal Urinary Diversion in Robotic-Assisted Radical Cystectomy." Yonago Acta Med. 2022;65(4):288-295. doi:10.33160/yam.2022.11.004
49. Bishop CV, Vasdev N, Boustead G, Adshead JM. "Robotic Intracorporeal Ileal Conduit Formation: Initial Experience from a Single UK Centre." Adv Urol. 2013;2013:642836. doi:10.1155/2013/642836
50. Brandt SB, Körner SK, Milling RV, et al. "Ureteroenteric strictures following retrosigmoid vs. conventional ileal conduit - The MOSAIC study (The DaBlaCa-16 study)." BJU Int. 2025;136(5):858-865. doi:10.1111/bju.16894
51. Catalá V, Solà M, Samaniego J, et al. "CT findings in urinary diversion after radical cystectomy: postsurgical anatomy and complications." RadioGraphics. 2009;29(2):461-476. doi:10.1148/rg.292085146