Studer Orthotopic Ileal Neobladder
The Studer neobladder combines a detubularized, folded ileal reservoir with an intact isoperistaltic afferent limb and a urethral outlet. Studer and colleagues began the Bern experience in 1985. The ureters drain through freely refluxing ureteroileal anastomoses, and the afferent limb is not a formal antireflux valve.[1][2]
Studer/Wiklund reconstruction accounted for 74% of procedures in a 2023 multicenter cohort of 732 men undergoing intracorporeal neobladder reconstruction.[3]
Patient Selection
Discuss conduit, continent cutaneous and orthotopic options with eligible patients. Selection depends on bowel suitability, kidney and liver function, urethral oncologic safety, sphincter function, ability to manage emptying and the patient's priorities.[4][5]
- Ability to empty and catheterize: patients must understand scheduled emptying, recognize retention and be willing and physically able to perform intermittent catheterization if needed. An inability to manage these requirements is a major barrier to a continent diversion.
- Renal and hepatic function: severe impairment limits the ability to handle the metabolic load of urine in bowel. The AUA guideline lists inadequate renal function, giving an eGFR below 45 as an example, among contraindications to continent diversion.[4] EAU uses the broader category of severe impairment.[5] Some authors use a higher lower-limit guide (eGFR below 50) and note that a creatinine elevation from an obstructing bladder tumor can improve once the obstruction is relieved; a preoperative nephrostomy can help distinguish reversible from fixed impairment in an equivocal case.[23]
- Urethral outlet: verify a negative urethral margin before orthotopic diversion. Invasive urethral tumor requiring urethrectomy precludes a neobladder. Non-muscle-invasive disease in a preoperative prostatic-urethral or bladder-neck biopsy does not necessarily preclude it when the retained urethra is oncologically suitable; it changes counseling and surveillance.[4][5]
- Other constraints: insufficient usable bowel, an uncorrectable urethral stricture or inability to catheterize may rule out reconstruction. EAU lists high-dose preoperative radiotherapy, complex urethral strictures and severe urethral sphincter-related incontinence as relative contraindications to orthotopic neobladder.[5] Age alone is not an absolute exclusion.[4][5] In node-positive disease, EAU states that orthotopic neobladder can be considered with N1 involvement but not with N2 or N3 involvement.[5]
For women undergoing orthotopic neobladder construction, EAU strongly recommends obtaining procedural information, including histologic evaluation, on the bladder neck and urethral margin before or at cystectomy.[34] EAU also strongly recommends sexual organ preservation in eligible women when the area to be preserved is tumor-free, and describes the uterus and vagina as supporting the neobladder and potentially reducing retention or postoperative prolapse.[5] In a multicenter cohort of 297 women without preoperative bladder-neck involvement who underwent cystectomy with ileal neobladder, solitary urethral recurrence was 0.6% and recurrence combined with another site was 1.5% at a median follow-up of 64 months; a positive final urethral margin was the only factor associated with urethral recurrence, and none of the 27 women with trigonal tumor involvement developed it.[27]
Anatomy and Construction
The reservoir, afferent limb and urethral outlet have distinct functions:
| Component | Construction and purpose |
|---|---|
| Reservoir | The distal ileal segment is opened along its antimesenteric border and folded in more than one plane to form a capacious reservoir. Detubularization reduces coordinated bowel contractions. |
| Afferent limb | An intact proximal ileal segment remains in continuity with the pouch and receives the ureters. Its length and orientation facilitate ureteral drainage, but reflux can occur. |
| Urethral outlet | A dependent, tension-free pouch-to-urethra anastomosis provides the route for emptying; continence also depends on the retained sphincter and storage/emptying behavior. |
Published modifications vary in segment length, folding sequence and anastomotic technique. For example, Bianchi's modification uses approximately 40 cm for the reservoir and 15 cm for the afferent limb; the USC robotic technique describes a longer total segment.[6][7]
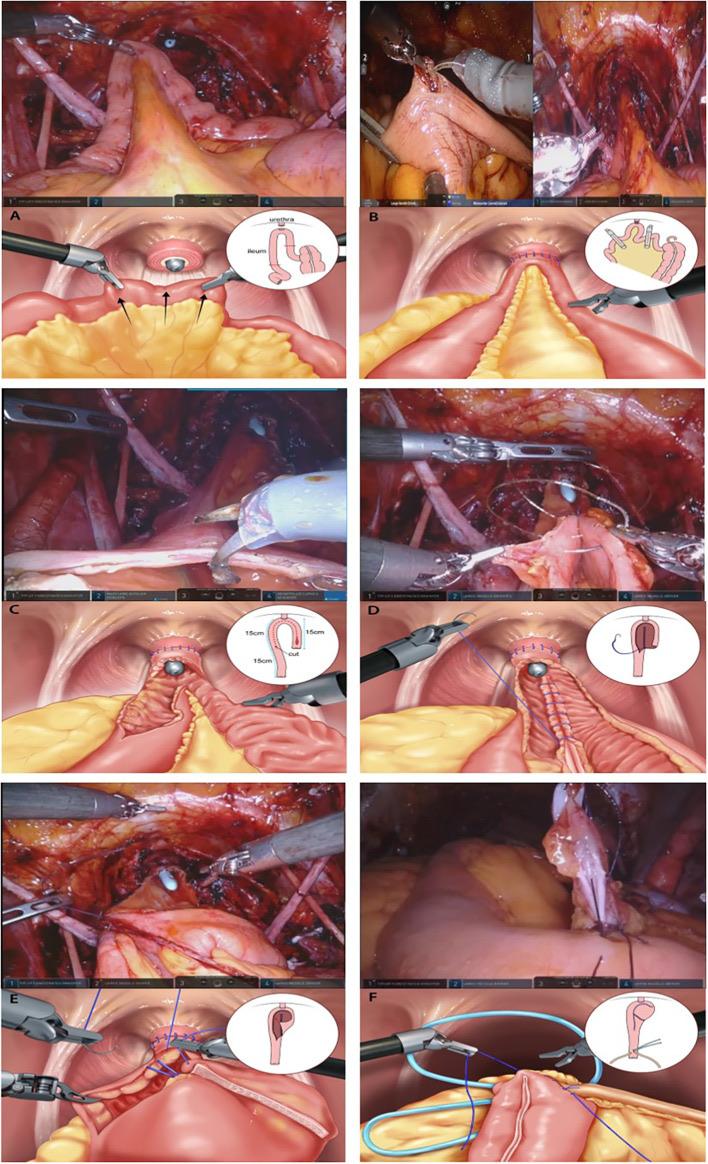
Intracorporeal modified Studer neobladder: (A) a 40–45 cm U-shaped reservoir segment is detubularized along the antimesenteric border after isolation of approximately 60 cm of ileum, leaving a proximal 15–20 cm afferent limb; (B) posterior stay sutures are placed from the far side of the urethra toward the urethral anastomosis site; (C) the posterior plate is closed with running barbed suture; (D) the anterior border is folded from the right side to the middle of the left side; (E) the anterior reservoir is closed with running barbed suture; (F) after one side of the ureteroenteric anastomosis is closed, a single-J stent is passed up the ureter and brought out through the isoperistaltic afferent limb. From Noh TI, et al. Front Oncol. 2022;12:975444, Figure 1 (CC BY).[31]
Operative framework
- Confirm reach before isolation. Select a well-perfused ileal segment whose mesentery allows the reservoir to reach the urethra without tension or twisting. Preserve bowel and ureteral blood supply and avoid unnecessary loss of terminal ileum.
- Isolate the planned segment and restore bowel continuity. Retain the designated proximal afferent limb intact.
- Detubularize the reservoir segment. Open the planned distal bowel along the antimesenteric border and construct the posterior plate.
- Fold and close the reservoir. The Studer configuration uses cross-folding to create a rounded pouch. A W-pouch made from ileum is not a Studer pouch. Close the reservoir with absorbable suture; exposed nonabsorbable metal staples in contact with urine have been linked to pouch-stone formation and are discouraged.[25]
- Join the dependent pouch to the urethra. Obtain a tension-free, watertight anastomosis over drainage. The order of folding and urethral anastomosis differs among open and intracorporeal techniques.
- Implant the ureters in the afferent limb. Preserve periureteral tissue, spatulate adequately and avoid angulation or ischemia. Direct implantation is refluxing; an added valve is a separate modification.
- Check closure, drainage and orientation. Document ureteral stents, pouch drainage and the planned postoperative assessment before catheter removal.[6][7][2] Plan reservoir irrigation to clear mucus and clots; in the original Studer protocol, a cystogram preceded catheter removal, followed by voiding training with postvoid residual checks. Catheter and stent timing varies by protocol.[35]
Dhar and Studer describe placing the urethral anastomosis broadly on the pelvic floor rather than at the pouch's funnel-shaped end, which they warn can kink and obstruct as the reservoir fills. For a short mesentery they describe flexing the operating table, making superficial mesenteric relaxing incisions, tying the urethrointestinal sutures loosely, and only rarely fixing the pouch laterally to the pelvic floor; for an obese patient they check whether bowel 12 cm from the distal harvested end reaches the base of the penis, then deepen the distal mesenteric release, unflex the table, and add superficial transverse serosal incisions, dividing a vessel proximal to Riolan's arcade only if tension persists while preserving collaterals on both sides. These are the named authors' operative descriptions, not comparative evidence.[22] For the anastomosis itself, Daneshmand describes six anterior 2-0 polyglycolic-acid sutures placed through mucosa and submucosa of the striated sphincter, followed by two posterior sutures incorporating the rectourethralis muscle or the caudal extent of Denonvilliers' fascia; this is one author's suture pattern, not a required minimum.[24]
Bianchi's 36-patient modification attached the reservoir to the levator ani and the afferent limb to the psoas. Anastomotic strictures were few and renal function was not impaired, and the series did not test fixation against no fixation.[6]
Open and intracorporeal approaches
Gill's 2002 report described the early completely intracorporeal laparoscopic experience. Subsequent robotic reports describe refinements in particular programs, including a fall in operating time within the USC program.[8][7] For the intracorporeal anastomosis itself, Hussein, Ahmed and Guru describe a continuous Van Velthoven urethro-ileal anastomosis over a silicone catheter marking the urethral stump, starting from an enterotomy in the most dependent antimesenteric ileum; when approximation is difficult, they describe reducing Trendelenburg, applying gentle Penrose traction, making a mesenteric release incision, selectively stapling the medial or proximal mesentery while protecting the neobladder's blood supply, or mobilizing ileum around the ileocecal region, with no fixed order among these options.[28]
The 2024 systematic review and atlas of intracorporeal neobladders included 19 studies and nine techniques. It found substantial variation in reporting and no eligible randomized or comparative cohort studies comparing the techniques.[9]
Does a Formal Antireflux Mechanism Help?
The USC-STAR randomized trial assigned 484 patients to Studer or T-pouch reconstruction; 423 had baseline outcome data and 260 contributed the three-year renal endpoint. The remaining baseline cohort included 124 deaths and 39 patients without three-year renal data, so the renal result is not a complete 484-patient long-term assessment.[2]
| Three-year outcome | Studer | T-pouch |
|---|---|---|
| Mean eGFR change, mL/min/1.73 m² | −6.4 | −6.6 |
| Cumulative diversion-related secondary surgical intervention | 13% | 22% |
The primary renal comparison was not statistically significant (p = 0.35); diversion-related reintervention was more frequent with T-pouch. Symptomatic UTI and overall late-complication rates did not differ significantly. Baseline renal function, age and urinary-tract obstruction were associated with renal deterioration. The trial did not demonstrate a renal benefit from the formal antireflux design. USC-STAR assessed only Studer and T-pouch, without establishing equivalence.[2]
Its search predates USC-STAR.[10]
A 2023 meta-analysis of 11 studies of bladder-cancer patients with orthotopic ileal neobladders found antireflux implantation associated with less vesicoureteral reflux (OR 0.24, 95% CI 0.10–0.59; I² = 75%) and more ureteroenteric stricture (OR 2.84, 95% CI 1.75–4.61; I² = 50%) than direct implantation.[37]
Emptying, Continence and Urodynamics
A neobladder retains bowel smooth muscle but lacks the native bladder's coordinated detrusor emptying mechanism. Patients generally empty by relaxing the outlet and increasing abdominal pressure. They need an individualized schedule, including overnight emptying when necessary, and assessment of residual urine. Persistent incomplete emptying requires evaluation and often intermittent catheterization. In the USC questionnaire study, 9.5% of respondents performed intermittent catheterization and 70.6% of them started within the first year; the authors describe emptying failure as uncommon and early.[5][1][11] The Bern group itself treats a permanent indwelling catheter or long-term intermittent catheterization outside dedicated nursing care as a treatment failure requiring further intervention rather than an accepted outcome; they report that 20% of their male patients needed an intervention for impaired emptying within the first postoperative decade, after which 94% remained able to void spontaneously. This is one high-volume center's management philosophy; intermittent catheterization is accepted elsewhere as part of long-term management when spontaneous emptying is inadequate.[23]
Continence estimates depend on the definition. Daytime versus nighttime continence, no pads versus a safety pad, patient questionnaires versus clinician reports and follow-up duration produce very different figures. In a separate retrospective cohort of 195 women with non-Studer orthotopic neobladders (180 Hautmann, six Kock and nine T-pouch) who were free of disease recurrence and available for follow-up, chronic urine retention was reported in 52 (27%) after a median 98 months; among 95 followed for more than 10 years, 31 (33%) had chronic retention at their last visit.[32]
| Evidence | What it actually reports |
|---|---|
| Bern experience, 482 reconstructions accumulated during 1985–2005 | One-year daytime and nighttime continence of 92% and 79%, and 93% voiding spontaneously at last follow-up. Of 442 evaluable men, 22.4% reported erections without and 15.4% with medical assistance. The experience accrued over 20 years and is not 20-year follow-up of every patient.[1] |
| Multicenter intracorporeal cohort, 732 men with several designs | At 12 months, 86% daytime and 66% nighttime continence when no pad or a security pad/one pad was counted; 20% and 32%, respectively, were in the security-pad-or-one-pad categories. After adjustment neobladder type was not associated with continence.[3] |
| USC male neobladder questionnaire study | Among respondents (68% response, mean follow-up 4.5 years, Studer and T-pouch combined), only 22.3% reported no pads. In the daytime 47% used at least one pad; at night 72% used pads and 38.9% used diapers. Mucus leakage was reported by 62.5%. Increasing age and diabetes predicted worse urinary function but were not associated with pad use.[11] |
| USC prospective pictorial pad-use questionnaire, 188 men (mostly modified Studer), 351 interval questionnaires over 3 years | Continence meant no pad or an almost-dry pad. Daytime continence was 92% in the 12–18-month interval (49 questionnaires); nighttime continence was 51% in the 18–36-month interval (61 questionnaires). Nearly half reported both daytime and nighttime continence at 18–36 months. Older age and diabetes were associated with worse daytime continence.[26] |
Nighttime leakage and the possibility of catheterization are part of preoperative counseling.[30] EAU 2026 cites a questionnaire study of 56 women with orthotopic neobladders: 35/56 (62.5%) used catheterization to some extent, and 25/56 (44.6%) depended on it to empty. These outcomes are neither Studer-specific rates nor the same endpoint as chronic retention in the cohort above.[14][33][12] A Swedish multicenter questionnaire study (452 of 491 identified patients responding, 92%) found that patients with an orthotopic neobladder more often reported a negative effect of their diversion on nocturnal sleep (37%) than those with a noncontinent urostomy (22%) or a continent cutaneous reservoir (14%), and that patients reporting a negative sleep effect more often reported reduced quality of life (88% vs 65%).[29] Counsel patients that nocturnal voiding needs are part of what distinguishes diversion types, alongside continence and catheterization.[29]
Urodynamics is used when symptoms, poor emptying or concern about storage pressure require investigation. Among Nam's 19 evaluated long-term survivors (>10 years), mean residual urine was 147 ± 83 mL; in the 13 who underwent urodynamics, mean maximum capacity was 484 ± 119 mL and maximum flow was 13.6 ± 9.7 mL/s.[13] Capacity, compliance, pressure, residual urine, continence and upper-tract findings are interpreted together.[13][5]
Complications and Metabolic Consequences
Both the operation and long-term functional care influence risk.[1][14]
In women with orthotopic neobladders, new vaginal leakage warrants assessment for a neobladder–vaginal fistula.[36] A systematic review assessed this complication in 17 publications and reported 3–6% incidence at higher-volume centers, often near the neobladder–urethral anastomosis.[36] Later problems include ureteroenteric or urethral-outlet obstruction, impaired emptying, infection, stones, hernias, metabolic acidosis and nutritional deficiency. Both the operation and long-term functional care influence risk.[1][14]
| Series | Findings |
|---|---|
| Hautmann 90-day report, 1,013 neobladders (1986–2008) | At least one complication in 587 (58%): infectious 24%, genitourinary 17%, gastrointestinal 15%, wound 9%. Minor (grade 1–2) 36%, major (grade 3–5) 22%; 90-day mortality 2.3%. Severity correlated with age, tumor stage, ASA score and comorbidity.[15] |
| Hautmann long-term report, 923 patients followed more than 90 days (median 72 months) | Overall long-term complication rate 40.8%, with 3 neobladder-related deaths. Twenty-year Kaplan-Meier estimates: hydronephrosis 16.9%, incisional hernia 6.4%, febrile UTI 5.7%, ileus or small-bowel obstruction 3.6%. Subneovesical obstruction occurred in 3.1% (neovesicourethral anastomotic stricture 1.2%). Long-term bicarbonate was needed by 307 of 923; 11 had severe metabolic acidosis and 2 received B12.[16] |
| Bern Studer series, 482 patients (447 with afferent limb) | 61 early and 115 late complications requiring treatment; ureteroileal stenosis 12 of 447 (2.7%); urethral recurrence 25 of 482 (5%); B12 substitution in 15 patients (reported as 5%, without a stated denominator for that percentage). Renal parenchyma decreased only with preoperative or postoperative ureteral obstruction, and patients with normal renal function had no long-term acidosis at 10 years.[1] |
Nam's report assessed 19 of 50 patients whose surgery had occurred more than 10 years earlier (original cohort 108 Studer pouches). Of the other 31, 22 had died and nine were lost to follow-up. Six had renal atrophy, five had moderate-to-severe hydronephrosis, five had recurrent pyelonephritis, and three had voiding difficulty and used intermittent catheterization, including two with bladder-neck contracture; seven had nocturnal incontinence, and one needed surgery for intestinal obstruction.[13]
- Hyperchloremic metabolic acidosis: serum electrolytes and bicarbonate are assessed alongside kidney function. Alkali requirements vary with urine contact, emptying and renal reserve.
- Vitamin B12 deficiency: risk may appear years after ileal surgery.[1] The Bern series reported B12 substitution in 15 patients (5%, denominator unstated).[1] EAU follow-up guidance advises annual vitamin B12 measurement after bowel diversion, because low levels have been reported in 17% of patients with bowel diversion (section 7.4 text; no strength rating).[14]
- Mucus: educate patients about the prescribed irrigation and drainage plan. Mucus obstruction, retention and stones remain possible in long-term follow-up.
- Renal assessment: routine monitoring includes serum creatinine/eGFR, electrolytes and appropriate upper-tract imaging. Reabsorption of creatinine across bowel mucosa was raised as a limit of urinary creatinine clearance in older neobladder management.[17] Scheduled nuclear GFR scans are not required for all patients.[18]
See Renal function and metabolic surveillance, Vitamin B12 supplementation, Urinary acidifiers & alkalinizers, and Mucus management.
Quality of Life and Choice of Pouch
An orthotopic reservoir avoids an external urine appliance but introduces different demands: scheduled emptying, possible leakage, mucus and potential catheterization. A conduit has its own stoma and appliance burdens. Neither provides universally better quality of life. Most comparative evidence is observational and is affected by selection, age, baseline health and the instrument used.[19][20]
In the 2016 meta-analysis of nonrandomized comparisons, the overall pooled quality-of-life difference was not statistically significant, although selected subgroup results favored neobladder. A 2022 review in women included only four studies and 283 patients; its nonsignificant result had wide confidence intervals that preclude an equivalence conclusion.[19][21]
The reservoir is chosen with the patient and an experienced reconstructive team. The Studer and T-pouch randomized result is the main comparative evidence, and no trial supports assigning similar renal function, continence and revision rates to every named neobladder.[2][9]
Long-Term Surveillance
Separate functional follow-up from cancer surveillance, and continue functional assessment beyond the period of intensive oncologic imaging.[14][18]
| Domain | Follow-up focus |
|---|---|
| Kidney function and metabolic status | Creatinine/eGFR, electrolytes and bicarbonate; investigate deterioration rather than attributing it automatically to age. AUA/ASCO/SUO Statement 31 advises laboratory assessment every 3–6 months for the first 2–3 years after treatment and then annually; additional testing is added as clinically needed.[18] |
| Upper tract | Imaging for obstruction, stones and other abnormalities, coordinated with cancer imaging. Select functional renal imaging when it answers a specific drainage or renal-function question. |
| Emptying and storage | Continence, voiding pattern, residual urine, catheterization ability and symptoms of infection or high-pressure storage. Investigate new retention, recurrent infection or upper-tract change. |
| Nutrition | EAU advises annual B12 measurement.[14] NCCN post-cystectomy follow-up specifies annual testing after the first year based on clinical judgment (category 2A).[30] Evaluate diarrhea, nutritional problems or unexplained anemia or neurologic symptoms. |
| Retained urothelium | Stage- and risk-appropriate cancer follow-up, including monitoring of the retained urethra . Urethral symptoms, bleeding or a high-risk history require investigation.[18] |
| Self-care | Review emptying, mucus management, hydration and access to urgent assessment for inability to drain, fever or new abdominal/flank pain. |
See Also
- Urinary Diversion landing
- Urinary Diversion Principles
- Hautmann Neobladder
- T-pouch
- Ileal Conduit
- Cutaneous Ureterostomy
- On WHITWIKI, the sister site for GU oncology: Continent Urinary Diversion.
Videos
References
1. Studer UE, Burkhard FC, Schumacher M, et al. Twenty years experience with an ileal orthotopic low pressure bladder substitute—lessons to be learned. J Urol. 2006;176(1):161–166. doi:10.1016/S0022-5347(06)00573-8.
2. Skinner EC, Fairey AS, Groshen S, et al. "Randomized trial of Studer pouch versus T-pouch orthotopic ileal neobladder in patients with bladder cancer." J Urol. 2015;194(2):433–439. doi:10.1016/j.juro.2015.03.101
3. Martini A, Falagario UG, Russo A, et al. "Robot-assisted radical cystectomy with orthotopic neobladder reconstruction: techniques and functional outcomes in males." Eur Urol. 2023;84(5):484–490. doi:10.1016/j.eururo.2023.04.009
4. American Urological Association / American Society of Clinical Oncology / Society of Urologic Oncology. Treatment of Non-Metastatic Muscle-Invasive Bladder Cancer. Amended 2024. Statements 13–14 and discussion, urinary diversion and urethral margins. Guideline PDF.
5. European Association of Urology. EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer. 2026. Disease management, section 6.7.5, urinary diversion. Guideline.
6. Bianchi G, Sighinolfi MC, Pirola GM, Micali S. "Studer orthotopic neobladder: a modified surgical technique." Urology. 2016;88:222–225. doi:10.1016/j.urology.2015.11.020
7. Chopra S, de Castro Abreu AL, Berger AK, et al. "Evolution of robot-assisted orthotopic ileal neobladder formation: a step-by-step update to the USC technique." BJU Int. 2017;119(1):185–191. doi:10.1111/bju.13611
8. Gill IS, Kaouk JH, Meraney AM, et al. Laparoscopic radical cystectomy and continent orthotopic ileal neobladder performed completely intracorporeally: the initial experience. J Urol. 2002;168(1):13–18. doi:10.1016/S0022-5347(05)64821-5.
9. Piramide F, Turri F, Amparore D, et al. "Atlas of intracorporeal orthotopic neobladder techniques after robot-assisted radical cystectomy and systematic review of clinical outcomes." Eur Urol. 2024;85(4):348–360. doi:10.1016/j.eururo.2023.11.017
10. Cody JD, Nabi G, Dublin N, et al. "Urinary diversion and bladder reconstruction/replacement using intestinal segments for intractable incontinence or following cystectomy." Cochrane Database Syst Rev. 2012;(2):CD003306. doi:10.1002/14651858.CD003306.pub2
11. Ahmadi H, Skinner EC, Simma-Chiang V, et al. "Urinary functional outcome following radical cystoprostatectomy and ileal neobladder reconstruction in male patients." J Urol. 2013;189(5):1782–1788. doi:10.1016/j.juro.2012.11.078
12. Hautmann RE, Volkmer B, Egghart G, et al. "Functional outcome and complications following ileal neobladder reconstruction in male patients without tumor recurrence: more than 35 years of experience from a single center." J Urol. 2021;205(1):174–182. doi:10.1097/JU.0000000000001345
13. Nam JK, Kim TN, Park SW, Lee SD, Chung MK. "The Studer orthotopic neobladder: long-term (> 10 yr) functional outcomes, urodynamic features, and complications." Yonsei Med J. 2013;54(3):690–695. doi:10.3349/ymj.2013.54.3.690
14. European Association of Urology. EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer. 2026. Follow-up, section 7.4, functional outcomes and complications. Guideline.
15. Hautmann RE, de Petriconi RC, Volkmer BG. "Lessons learned from 1,000 neobladders: the 90-day complication rate." J Urol. 2010;184(3):990–994. doi:10.1016/j.juro.2010.05.037
16. Hautmann RE, de Petriconi RC, Volkmer BG. "25 years of experience with 1,000 neobladders: long-term complications." J Urol. 2011;185(6):2207–2212. doi:10.1016/j.juro.2011.02.006
17. Broderick GA, Stone AR, deVere White R. Neobladders: clinical management and considerations for patients receiving chemotherapy. Semin Oncol. 1990;17(5):598–605. PubMed.
18. American Urological Association / American Society of Clinical Oncology / Society of Urologic Oncology. Treatment of Non-Metastatic Muscle-Invasive Bladder Cancer. Amended 2024. Statements 31–32 and discussion, laboratory follow-up and retained urethra. Guideline PDF.
19. Cerruto MA, D'Elia C, Siracusano S, et al. "Systematic review and meta-analysis of non-RCTs on HRQoL after radical cystectomy using validated questionnaires: better results with orthotopic neobladder versus ileal conduit." Eur J Surg Oncol. 2016;42(3):343–360. doi:10.1016/j.ejso.2015.10.001
20. Kern SQ, Speir RW, Tong Y, et al. "Longitudinal HRQoL after open radical cystectomy: comparison of ileal conduit, Indiana pouch, and orthotopic neobladder." Urology. 2021;152:184–189. doi:10.1016/j.urology.2020.12.036
21. Xing W, Zeng S, Xu Z, Xing S, Liu Q. "Comparison of HRQoL between ileal conduit diversion and orthotopic neobladder in women: a meta-analysis." Front Oncol. 2022;12:862884. doi:10.3389/fonc.2022.862884
22. Dhar NB, Studer UE. Ileal orthotopic bladder substitution. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:319–324.
23. Kiss B, Studer UE, Burkhard FC. Ileal orthotopic bladder substitution. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:400–406.
24. Daneshmand S. Orthotopic urinary diversion in men. In: Daneshmand S, ed. Urinary Diversion. Springer; 2017:11–24. doi:10.1007/978-3-319-52186-2_2
25. Suriano F, Daneshmand S, Buscarini M. "Use of nonabsorbable staples for urinary diversion: a step in the wrong direction." Urol Int. 2013;90(2):125–129. doi:10.1159/000339377
26. Clifford TG, Shah SH, Bazargani ST, et al. "Prospective evaluation of continence following radical cystectomy and orthotopic urinary diversion using a validated questionnaire." J Urol. 2016;196(6):1685–1691. doi:10.1016/j.juro.2016.05.093
27. Gakis G, Ali-El-Dein B, Babjuk M, et al. "Urethral recurrence in women with orthotopic bladder substitutes: a multi-institutional study." Urol Oncol. 2015;33(5):204.e17–23. doi:10.1016/j.urolonc.2015.01.020
28. Hussein AA, Ahmed YE, Guru KA. Robot-assisted intracorporeal urinary diversion. In: Daneshmand S, ed. Urinary Diversion. Springer; 2017:55–61. doi:10.1007/978-3-319-52186-2_5
29. Thulin H, Kreicbergs U, Wijkström H, Steineck G, Henningsohn L. "Sleep disturbances decrease self-assessed quality of life in individuals who have undergone cystectomy." J Urol. 2010;184(1):198–202. doi:10.1016/j.juro.2010.03.009
30. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Bladder Cancer. Version 3.2026. August 6, 2026. BL-E 3–4 of 6; Discussion MS-18. Guideline.
31. Noh TI, Shim JS, Kang SG, Cheon J, Pyun JH, Kang SH. "The learning curve for robot-assisted radical cystectomy with total intracorporeal urinary diversion based on radical cystectomy pentafecta." Front Oncol. 2022;12:975444. doi:10.3389/fonc.2022.975444
32. Zahran MH, Harraz AM, Baset MA, El-Baz R, Shaaban AA, Ali-El-Dein B. "Voiding and renal function 10 years after radical cystectomy and orthotopic neobladder in women." BJU Int. 2023;132(3):291–297. doi:10.1111/bju.16011
33. Bartsch G, Daneshmand S, Skinner EC, et al. "Urinary functional outcomes in female neobladder patients." World J Urol. 2014;32(1):221-228. doi:10.1007/s00345-013-1219-8
34. European Association of Urology. EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer. 2026. Diagnosis, section 5.5, primary assessment of presumably invasive bladder tumours. Guideline.
35. Thakare N, Lamb BW, Biers S. "Orthotopic bladder substitution: Surgical aspects and optimization of outcomes." BJUI Compass. 2021;2(6):359–369. doi:10.1002/bco2.84
36. Richter LA, Egan J, Alagha EC, Handa VL. "Vaginal Complications after Radical Cystectomy for Bladder Cancer: A Systematic Review." Urology. 2021;156:e20–e29. doi:10.1016/j.urology.2021.07.001
37. Zhang Y, Ding H, Zhang Y, et al. "Is Anti-Reflux Anastomosis an Advantage in an Orthotopic Ileal Neobladder? A Systematic Review and Meta-Analysis." Urol Int. 2023;107(1):1–14. doi:10.1159/000525017